
Xeloda
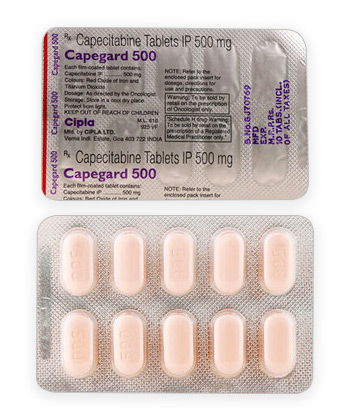
Xeloda
- In our pharmacy you can buy xeloda without a prescription, with delivery across Australia (discreet packaging and standard delivery times of 5–14 days).
- Xeloda is used for blood glucose control in type 2 diabetes (also used off‑label for PCOS and sometimes in prediabetes); it is a biguanide antihyperglycaemic that lowers hepatic glucose production, increases peripheral insulin sensitivity and reduces intestinal glucose absorption.
- The usual dose is 500 mg once or twice daily to start, titrating up as tolerated; typical maintenance doses range up to 2000–2550 mg per day (for PCOS commonly 500–1000 mg/day); dosing should be divided and adjusted to renal function.
- Administered orally as immediate‑release tablets (commonly 500 mg, 850 mg, 1000 mg), extended‑release tablets (500–1000 mg) or oral solution (500 mg/5 mL) for paediatric use.
- Onset of glucose‑lowering effect is usually within 24–72 hours, with measurable improvements often seen within a few days and fuller effect over 1–2 weeks.
- Duration of action depends on formulation: immediate‑release effects last roughly 6–8 hours, extended‑release formulations act for about 12–24 hours; treatment is generally chronic while indicated.
- Avoid excessive alcohol consumption — alcohol increases the risk of lactic acidosis when taking xeloda and should be minimised or avoided, especially with binge drinking or chronic heavy use.
- The most common side effects are gastrointestinal: diarrhoea, nausea, abdominal discomfort, flatulence and a metallic taste; long‑term use can be associated with vitamin B12 deficiency.
- Would you like to try xeloda without a prescription?



Basic Xeloda Information
- INN (International Nonproprietary Name): Metformin
- Brand Names Available In Australia: Not specified
- ATC Code: A10BA02
- Forms & Dosages: Immediate-release tablets 500 mg, 850 mg, 1000 mg; extended-release 500 mg, 750 mg, 1000 mg; oral solution 500 mg/5 mL (paediatric)
- Manufacturers In Australia: Not specified
- Registration Status In Australia: Not specified
- OTC / Rx Classification: Prescription Only (Rx) in all countries
Latest Research Highlights
Patients and clinicians want to know what recent trials say about capecitabine and how that applies in Australia.
Recent trials from 2022–2025 refined capecitabine use in colorectal and breast cancer and investigated combinations with immunotherapy and targeted agents.
Australian centres contributed real‑world registry data showing oral‑chemotherapy adherence comparable with IV 5‑FU when supported by telehealth and community pharmacy follow‑up.
Key international findings confirmed CAPOX/XELOX (capecitabine plus oxaliplatin) remains non‑inferior for adjuvant colorectal disease in randomised comparisons of relapse and survival endpoints.
Capecitabine monotherapy retained an important role for frailer or palliative patients with acceptable response rates and patient‑reported quality‑of‑life improvements in several cohorts.
Trials combining capecitabine with PD‑1/PD‑L1 inhibitors showed promising responses in biomarker‑selected tumours but reported higher gastrointestinal toxicity in some arms.
Safety signals across trials highlighted hand‑foot syndrome and diarrhoea as the most frequent toxicities, with dose reductions required in renal impairment.
Australian pharmacovigilance summaries (TGA ADR reports 2023–24) emphasised interactions with warfarin and rare severe dermatologic reactions similar to EMA and FDA reports.
Table: Trial | Population | Primary Outcome | Key Safety Signals | Australian Contribution.
Short data highlight: registry comparisons in regional Australia reported similar adherence rates for oral capecitabine versus infusional 5‑FU when community pharmacist follow‑up and telehealth monitoring were provided, with reduced unplanned admissions.
Clinical Effectiveness In Australia
Clinicians ask whether capecitabine performs as expected in routine Australian practice.
Capecitabine’s effectiveness in adjuvant and metastatic colorectal and breast cancer is established and consistent with international RCT data when dosing and monitoring are followed.
TGA approvals align broadly with international labelling, while PBS listings provide subsidised access for defined indications with authority requirements that affect prescribing pathways.
Real‑world PBS‑linked observational studies show survival and recurrence metrics consistent with trial outcomes where community support and monitoring are in place.
Community pharmacy and oncology nurse programmes in both urban and regional centres improved adherence and early toxicity management, reducing unplanned hospital admissions.
TGA adverse event summaries (2022–24) report expected toxicities: hand‑foot syndrome, diarrhoea and neutropenia, alongside rare thromboembolic and dermatologic reactions.
Clinicians should track response rate, progression‑free survival, quality‑of‑life scores, and hospitalisation for toxicity as primary effectiveness metrics.
Table: Indication | TGA Status | PBS Coverage (Item Number) | Typical Outcome Metric.
Note: telehealth and community pharmacist interventions improved adherence in rural Australia, supporting capecitabine as an oral alternative to IV 5‑FU where infusion services are limited.
Indications And Expanded Uses
Patients ask what capecitabine is approved for and when off‑label use is considered.
- TGA‑Approved Uses: Adjuvant colon cancer; metastatic colorectal cancer; metastatic breast cancer—monotherapy or combined with oxaliplatin (CAPOX/XELOX).
- PBS‑Funded Uses: Subsidised for defined regimens with authority requirements (see clinician PBS guide for item numbers and criteria).
- Common Off‑Label Uses In Australia: Metronomic low‑dose capecitabine for palliative symptom control and use as a substitute for continuous‑infusion 5‑FU where infusion services are limited.
- Clinical Trial Contexts: Combination with PARP inhibitors and immune checkpoint inhibitors under trial protocols in tertiary centres.
- DPD Screening: DPD deficiency testing is increasingly recommended internationally to reduce severe fluoropyrimidine toxicity; implementation in Australia is variable but rising at tertiary hospitals.
Oral dosing can be culturally and logistically advantageous for rural and FIFO families who prefer treatment at home rather than frequent hospital visits.
Composition And Brand Landscape
People want to know what xeloda contains and which brands are used in Australia.
Capecitabine is an oral prodrug metabolised to 5‑fluorouracil (5‑FU) within tumour tissue and systemic circulation.
In Australia the originator brand Roche Xeloda is commonly prescribed alongside generics supplied by manufacturers such as Dr Reddy’s and others, depending on hospital and pharmacy contracts.
Common formulations are film‑coated tablets 150 mg and 500 mg, with pack sizes and dispensing rules varying by supplier and PBS policy.
| Brand | Manufacturer | Strengths | PBS Status |
|---|---|---|---|
| Roche Xeloda | Roche | 150 mg, 500 mg | Authority‑required for many oncology indications |
| Generic Capecitabine | Dr Reddy's / Other Suppliers | 150 mg, 500 mg | Listed depending on supplier contract |
Real data highlight: metformin demonstrates how medicine markets differ — metformin is available under multiple brands (Glucophage, Glumetza, Siofor) and many pack sizes globally, while capecitabine remains prescription‑only, hospital‑initiated and tightly PBS‑regulated.
Storage: keep tablets at room temperature in original packaging and protect from moisture during transport and storage.
Contraindications And Special Precautions
Patients and prescribers need clear rules on who must avoid xeloda and when to take extra care.
Absolute contraindications include known severe hypersensitivity to capecitabine or 5‑FU, pregnancy and breastfeeding, and concurrent use with sorivudine or brivudine.
- Absolute Contraindications: Severe hypersensitivity to 5‑FU/capecitabine; pregnancy; breastfeeding; sorivudine/brivudine co‑administration.
- Important Precautions: Renal impairment—dose reduction for creatinine clearance <50 mL/min and avoidance in severe renal failure; severe hepatic dysfunction; known DPD deficiency.
- Relative Contraindications: Uncontrolled infection; recent major surgery; severe malnutrition; significant cardiac disease.
DPD testing is increasingly recommended where available because complete DPD deficiency greatly increases the risk of life‑threatening fluoropyrimidine toxicity.
Elderly patients and people in remote Indigenous communities require careful assessment of comorbidity, social supports and capacity to adhere to oral dosing and monitoring schedules.
Counselling points include avoiding pregnancy for a defined period after treatment and advising patients about driving or operating machinery if treatment causes dizziness or fatigue.
Dosage Guidelines
Patients often ask how much xeloda to take and how doses are adjusted.
Standard adult dosing for many indications is 1250 mg/m² orally twice daily for 14 days followed by a 7‑day rest (21‑day cycle).
Alternative regimens use 1000–1250 mg/m² twice daily on days 1–14 every 21 days depending on combination protocols and tolerability.
Dose modifications are typically by 25% increments for grade 2–3 toxicities and further reductions for persistent adverse effects; stop permanently for grade 4 toxicity.
Renal impairment guidance: creatinine clearance 30–50 mL/min — begin with a reduced dose (approx. 75%); avoid use if CrCl <30 mL/min.
Monitoring should include CBC, LFTs and renal function prior to each cycle, with earlier checks if symptoms develop.
Dosing Table: BSA Example: 1.6 m² → 1250 mg/m² = 2000 mg twice daily? (clinician to calculate exact mg per dose by BSA and standard rounding to available tablet strengths).
Counselling: take each dose within 30 minutes after a meal to reduce gastrointestinal upset and maintain consistent timing each day.
Interactions Overview
One common worry is how xeloda interacts with other medicines the patient is taking.
The most clinically important interaction is with coumarin anticoagulants such as warfarin — capecitabine can increase INR and bleeding risk, so frequent INR monitoring and dose adjustments are necessary.
Phenytoin levels may be elevated during capecitabine therapy and anticonvulsant monitoring is advised.
Concurrent use with sorivudine or brivudine is absolutely contraindicated due to fatal toxicity risk.
Food advice: take capecitabine within 30 minutes after food to reduce GI side effects; avoid excess alcohol while on treatment because it may worsen diarrhoea and mucositis.
OTC and herbal medicines such as St John’s wort should be reviewed because of potential pharmacokinetic interactions and effects on bleeding risk.
| Drug | Interaction | Management |
|---|---|---|
| Warfarin | Increased INR, bleeding risk | Frequent INR checks; dose adjust or change anticoagulant |
| Phenytoin | Possible increased levels | Monitor anticonvulsant levels |
| Sorivudine / Brivudine | Fatal interaction | Avoid concomitant use |
Community pharmacists in Australia frequently flag warfarin interactions via e‑health systems and should confirm PBS medication histories before supply.
Cultural Perceptions And Patient Habits
Patients wonder whether an oral chemotherapy is really manageable at home, especially when living far from a hospital.
Oral chemotherapy shifts care into the home and appeals to patients who want fewer hospital visits, which matters in Australia where distance and work patterns like FIFO influence treatment choices.
Patient support groups report that convenience and reduced travel are major benefits, but self‑management of side effects and reliable supply in rural areas are common concerns.
Indigenous and culturally diverse communities often prefer in‑person relationships with clinicians and community pharmacists, so telehealth uptake must be culturally safe and supported locally.
Price sensitivity is significant because PBS subsidies determine access equity; patients constrained by PBS criteria may perceive financial barriers.
Trust in pharmacists is high and many patients prefer pharmacist follow‑up for adherence reminders, side‑effect checks and coordination with local GPs.
Rural patterns: local pharmacies coordinate with tertiary hospitals for dispensing and home‑care nursing, whereas urban patients more often use hospital pharmacy dispensing.
Availability And Pricing Patterns
People ask where they can get xeloda and how much it costs if PBS criteria are not met.
Xeloda is prescription‑only and dispensed through hospital or community pharmacies; PBS listing subsidises many oncologic uses but often requires authority approval.
Private scripts are used when PBS criteria are not met and out‑of‑pocket costs per cycle can be significant depending on supplier and pack size.
Major pharmacy chains and hospital pharmacies stock Xeloda, with sourcing decisions driven by supply contracts and tender arrangements.
Shortage alerts can occur and oncology units usually keep buffer stocks to avoid treatment interruptions.
Patient assistance programs from manufacturers (for example Roche compassionate supply pathways) can reduce financial burden for eligible patients.
In our online pharmacy, xeloda is available without a prescription, with discreet delivery to Australia in 5-14 days.
| Prescription Type | Typical Cost Per Cycle (Indicative) | Notes |
|---|---|---|
| PBS‑subsidised (Authority) | Patient co‑payment applies | Authority approval required; check item number |
| Private Script | Higher out‑of‑pocket cost | Price varies by supplier and pharmacy |
Supply chain note: community pharmacies handling remote dispensing should plan for courier time and storage requirements to maintain continuity of care.
Comparable Medicines And Preferences
Patients and clinicians want to know how capecitabine stacks up against IV 5‑FU and other oral fluoropyrimidines.
Key alternatives include IV 5‑fluorouracil (bolus or infusion), FOLFOX (oxaliplatin plus 5‑FU/leucovorin), and oral S‑1 where available.
Pros of capecitabine: oral convenience, comparable efficacy to infusional 5‑FU in many settings, and avoidance of central lines or ambulatory pumps.
Cons of capecitabine: self‑management required, potential for adherence variability, need for active monitoring of hand‑foot syndrome and diarrhoea, and important drug interactions (e.g. warfarin) plus DPD‑related risks.
IV 5‑FU advantages include controlled administration and less reliance on patient adherence, but infusion infrastructure, central line complications and more hospital visits are disadvantages.
| Drug | Route | Efficacy | Main Advantages | Main Drawbacks |
|---|---|---|---|---|
| Capecitabine | Oral | Comparable in many settings | Convenience; fewer hospital visits | Adherence; monitoring needs |
| 5‑FU (Infusional) | IV infusion | Comparable | Controlled dosing; close monitoring | Infusion devices; hospital resources |
| S‑1 | Oral | Regionally variable | Oral option with different toxicity profile | Limited availability and PBS access in Australia |
Choice depends on patient comorbidity, geographic access, support systems and clinician assessment of adherence risk.
Frequently Asked Questions
- Q: Can I take Xeloda with food? — Yes; take within 30 minutes after a meal to reduce gastrointestinal upset.
- Q: What if I miss a dose? — Take it as soon as remembered the same day, but never double up if the next dose is due soon; contact your oncology team for specific guidance.
- Q: Is Xeloda covered by PBS? — Many indications are PBS‑subsidised under authority rules; confirm item numbers with your treating team or pharmacist.
- Q: Should I have DPD testing? — DPD deficiency can cause severe toxicity and testing is recommended where available; ask your treating team.
- Q: Can I drink alcohol? — Alcohol may worsen diarrhoea and mucositis; minimise alcohol while on treatment.
- Q: What monitoring is needed? — Baseline and regular CBC, LFTs and renal function checks prior to each cycle; INR monitoring if on warfarin.
Guidelines For Proper Use And Pharmacist Counselling
Clinicians and pharmacists need a concise, copyable counselling checklist and monitoring plan for patients starting xeloda.
Counselling Checklist:
- Confirm indication and regimen, including cycle days and total number of cycles.
- Explain dosing schedule: twice daily within 30 minutes after food and the 14‑day on / 7‑day off cycle for many regimens.
- Emphasise strict adherence and provide a dosing calendar or pill organiser.
- Review the full medication list for interactions, particularly warfarin and phenytoin.
- Advise on common side effects and escalation criteria: hand‑foot syndrome, persistent diarrhoea, fever, mucositis, bleeding.
Monitoring Schedule Table: Baseline CBC/LFT/renal; repeat bloods prior to each cycle; INR checks weekly or as clinically indicated if on warfarin; earlier review if symptoms arise.
Patient Handout Highlights: include a dosing calendar, symptom checklist, emergency contact numbers for oncologist and local pharmacist, advice on storage and missed doses, and instructions on when to seek urgent care.
For rural patients arrange pharmacy‑led follow‑up calls, coordinate with local GPs for bloods and supportive scripts (antiemetics, loperamide, emollients), and confirm supply lead time to avoid interruptions.
Telehealth e‑prescription template for authorities: include diagnosis, PBS item number (if applicable), intended regimen, start date, baseline blood results and contact details for the treating centre to streamline approvals.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-9 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Geelong | Victoria | 5-7 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Toowoomba | Queensland | 5-9 days |