
Casodex
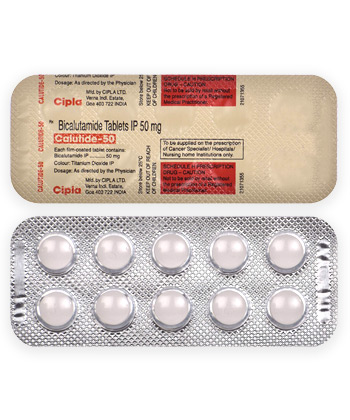
Casodex
- Casodex (bicalutamide) is legally a prescription-only medicine in Australia and most countries; it is supplied by pharmacies and hospitals — however, in some pharmacies it may be obtainable without a receipt (this can be unsafe and is not recommended; always seek a doctor’s prescription and supervision).
- Casodex is used to treat prostate cancer as an anti‑androgen; it is a non‑steroidal androgen receptor antagonist that competitively blocks the action of testosterone and dihydrotestosterone on prostate cancer cells, often given with LHRH analogues or as monotherapy in selected locally advanced cases.
- Usual doses are 50 mg once daily when combined with an LHRH analogue for metastatic disease, and 150 mg once daily when used as monotherapy for certain locally advanced, non‑metastatic cases; tablets are commonly available in 50 mg and 150 mg strengths.
- Administered orally as film‑coated tablets, taken once daily with or without food; follow the prescribing clinician’s instructions.
- Bicalutamide begins to block androgen receptors within hours of dosing, but meaningful clinical or PSA responses typically take days to weeks to become apparent.
- The drug is dosed once daily and has a long duration of action with a plasma half‑life of several days (steady‑state may take a few weeks), so effects persist between doses; treatment is usually continued until disease progression or unacceptable toxicity.
- Avoid heavy alcohol consumption — alcohol can worsen liver injury risk; use caution and avoid drinking heavily while on Casodex, and have liver function monitored as advised by your clinician.
- The most common side effect is hot flushes (hot flashes); other common effects include breast tenderness/enlargement (gynecomastia), fatigue, gastrointestinal upset and elevated liver enzymes.
- Would you like to try casodex without a prescription?
Basic Casodex Information
- INN (International Nonproprietary Name): Bicalutamide
- Brand Names Available In Australia: Not specified
- ATC Code: L02BB03
- Forms & Dosages: Tablet; strengths 50 mg and 150 mg; blisters of 28, 30, 60, 100; global (prescription only)
- Manufacturers In Australia: Not specified
- Registration Status In Australia: Not specified
- OTC / Rx Classification: Prescription only (Rx)
Latest Research Highlights
Patients and clinicians ask whether bicalutamide still has a role given newer androgen receptor inhibitors.
Recent literature from 2022 to mid‑2024 highlights two clear themes about bicalutamide and Casodex.
First, bicalutamide remains a well‑established first‑generation non‑steroidal anti‑androgen when used alongside LHRH analogues for metastatic prostate cancer.
Second, the landscape is shifting as second‑generation agents such as enzalutamide, apalutamide and darolutamide show superior outcomes in many non‑metastatic and metastatic settings.
Australian registry analyses and TGA adverse‑event summaries continue to report hepatic enzyme elevations and gynecomastia as persistent signals consistent with global safety data.
Real‑world studies in older cohorts report maintained symptom control and PSA suppression with 50 mg daily when combined with LHRH analogues.
Monotherapy at 150 mg remains regionally specific and less commonly used in contemporary practice outside selected locally advanced cases.
Comparative safety work from 2022–24 flags lower central nervous system effects for bicalutamide versus enzalutamide, though bicalutamide is less potent for survival endpoints in several high‑risk trials.
| Study/Source | Key Outcome | Safety Notes |
|---|---|---|
| Randomised Trials / RCTs | PSA response and symptom control when combined with LHRH; lower survival benefit vs some second‑generation AR inhibitors in high‑risk disease | ALT/AST rises reported; gynecomastia and hot flashes common |
| Australian Registries / TGA Summaries | PSA suppression maintained in older real‑world cohorts on 50 mg with LHRH | Persistent signal for hepatic enzyme elevations; monitoring advised |
| Comparative Safety Analyses | Lower CNS adverse event burden than enzalutamide | Less potency for survival endpoints in several modern trials |
Clinical Effectiveness In Australia
What outcomes do Australian clinicians see with Casodex and bicalutamide?
TGA registration aligns with global authorisations and the drug is used for prostate cancer in line with international practice.
Bicalutamide 50 mg once daily is typically combined with an LHRH analogue for metastatic disease, while 150 mg once daily may be used as monotherapy in selected locally advanced cases, per the available product information.
Australian effectiveness data largely come from hospital oncology units, regional registries and TGA adverse‑event reporting rather than large contemporary randomised trials.
Locally reported outcomes mirror global patterns with PSA reductions and symptomatic improvement most consistently seen in combination therapy with LHRH agents.
Monotherapy benefits at 150 mg appear limited when compared with newer androgen receptor inhibitors for high‑risk disease.
The TGA continues to emphasise liver function surveillance because early ALT/AST rises are the main laboratory signal observed.
Data Highlight:
- TGA adverse events: elevated liver enzymes, gynecomastia, hot flushes reported with frequency consistent with global experience.
- PBS and hospital utilisation: confirm PBS eligibility and local oncology protocols before initiating bicalutamide.
Indications And Expanded Uses
Patients often ask whether Casodex can be used outside standard indications.
Bicalutamide (INN) is indicated for prostate adenocarcinoma as anti‑androgen therapy consistent with the product information.
Typical adult dosing per product information is 50 mg once daily alongside an LHRH analogue for metastatic disease.
Monotherapy at 150 mg once daily is indicated for locally advanced non‑metastatic disease in certain regions and should be confirmed with local guidance.
Off‑label use in Australia is limited and usually restricted to individual circumstances such as intolerance to other agents or constrained access to alternatives.
Expanded or adjuvant uses have become uncommon after 2020 because second‑generation agents demonstrated superior efficacy in many settings.
- Approved Uses: Combination hormonal blockade for metastatic prostate cancer; selected regional monotherapy for locally advanced disease.
- Off‑Label Uses: Rare, case‑by‑case basis where other agents are unsuitable or unavailable.
Definitions:
- Combination Therapy: Bicalutamide 50 mg daily with an LHRH analogue such as goserelin, leuprorelin or triptorelin.
- Monotherapy: Bicalutamide 150 mg daily used alone in selected locally advanced, non‑metastatic cases where regionally authorised.
Always verify TGA and PBS listings and check institutional oncology guidelines before prescribing.
Composition And Brand Landscape
Which brands and packaging options should prescribers and pharmacists expect?
The active ingredient is bicalutamide (INN), with the originator brand Casodex supplied by AstraZeneca.
Major generics identified globally include Cipla, Intas and R‑Pharm, with local licensees in various markets.
Available dosage forms from the product information are 50 mg and 150 mg film‑coated tablets, commonly packed in blisters of 28, 30, 60 or 100 tablets.
| Brand | Strength | Packaging | Supplier / Manufacturer |
|---|---|---|---|
| Casodex | 50 mg, 150 mg | Bottles / Blister packs | AstraZeneca |
| Bicalutamide (generic) | 50 mg | Blister packs 28–100 | Cipla, Intas, Sun Pharma |
| Касодекс® | 50 mg | Tablets | AstraZeneca / R‑Pharm |
In Australia, Casodex is the recognised brand name, and generics may be available via import or local licences; check the TGA ARTG and PBS listings for current entries.
For patients: the medicine is prescription‑only, store below 25°C and keep in the original packaging until use.
Pharmacy channels such as Chemist Warehouse, Priceline and TerryWhite Chemmart typically dispense on a prescription, and online/telehealth supply is possible with a valid e‑prescription.
Contraindications And Special Precautions
Which patients must avoid Casodex and who needs closer monitoring?
Absolute contraindications include women and children, known hypersensitivity to bicalutamide or any excipient, and severe hepatic impairment.
Relative cautions apply for mild‑to‑moderate hepatic disease and prior exposure to hepatotoxic medicines.
Concomitant use with narrow‑therapeutic‑index medicines such as warfarin requires caution and close monitoring.
Elderly patients do not usually need dose adjustment, but comorbidity and polypharmacy increase risk and warrant careful review.
Special Australian considerations include higher prevalence of chronic liver disease in some Indigenous communities, which calls for extra vigilance and culturally safe counselling.
Remote patients may need coordinated pathology access to ensure timely liver function tests.
Daily‑life precautions: counsel patients about possible fatigue, dizziness and potential impact on driving or operating heavy machinery.
Advise minimising alcohol because it increases hepatic strain and may amplify liver injury risk.
Checklist:
- Contraindicated: women, children, severe hepatic impairment, hypersensitivity.
- Use with caution: mild‑moderate liver disease, prior hepatotoxins, warfarin co‑administration.
Dosage Guidelines
How should bicalutamide be dosed and monitored in routine practice?
Standard regimens per product information are 50 mg once daily alongside an LHRH analogue for metastatic prostate cancer.
Selected locally advanced cases may use 150 mg once daily as monotherapy where authorised regionally.
No routine dose adjustment is required for elderly patients, while moderate to severe hepatic impairment is a situation to avoid or use with extreme caution.
Missed dose advice: take as soon as remembered unless it is close to the next scheduled dose; do not double up.
Overdose management is supportive only and requires urgent medical review since no specific antidote exists.
Typical treatment duration is indefinite for metastatic disease until progression or unacceptable toxicity, and at least two years or per protocol for some locally advanced regimens.
| Indication | Dose | Monitoring |
|---|---|---|
| Metastatic Prostate Cancer (Combination) | 50 mg once daily with LHRH analogue | Baseline LFTs; monthly for first 3 months; periodic thereafter |
| Locally Advanced Non‑Metastatic (Monotherapy) | 150 mg once daily (where authorised) | Baseline LFTs; regular monitoring per oncology protocol |
Pharmacists and prescribers should keep a short regimen checklist for adherence counselling and monitoring tasks.
Interactions Overview
What drug combinations require extra caution with Casodex?
Bicalutamide is metabolised hepatically and interactions arise with medicines that alter liver enzymes or have narrow therapeutic indices.
Particular caution is flagged with warfarin because bicalutamide may alter INR, so frequent monitoring is advised when co‑prescribed.
Concurrent hepatotoxic drugs increase the risk of liver injury and should be avoided where possible.
Alcohol misuse further increases hepatotoxicity potential and should be minimised.
Second‑generation AR antagonists have differing interaction profiles and CNS risks, but hepatic pathways overlap for metabolic interactions in some cases.
For rural Australian patients on multiple chronic medicines, use e‑health medication lists and clinical decision support to check interactions and coordinate INR and LFT monitoring.
| Drug / Class | Interaction Risk | Action |
|---|---|---|
| Warfarin | Altered INR and bleeding risk | Increase INR monitoring during initiation and changes |
| Concomitant Hepatotoxics | Increased hepatic injury risk | Avoid combination where possible; monitor LFTs closely |
| Potent CYP Inhibitors/Inducers | Possible PK changes | Check for specific interactions and adjust monitoring |
Cultural Perceptions And Patient Habits
How do Australian patients view Casodex and what practical issues affect adherence?
Many users trust community pharmacists at chains such as Chemist Warehouse and TerryWhite for practical medicine information.
Cost and PBS subsidy status are decisive for patients and often drive the choice between older agents like bicalutamide and newer alternatives.
Rural populations may face delayed pathology access and rely on telehealth e‑prescriptions with local pharmacy dispense arrangements.
Regional oncologists sometimes favour older, more accessible agents where newer drugs are not PBS‑subsidised or affordable.
Indigenous patients may have concerns about medication safety, interactions with traditional practices and higher comorbidity such as chronic liver disease.
Culturally safe counselling and involvement of community health workers are essential for these communities.
Online forums commonly discuss gynecomastia, hot flushes and medicine cost, so clinicians should proactively address these topics in counselling.
| Setting | Access Barrier | Suggested Approach |
|---|---|---|
| Urban | Cost sensitivity; PBS reliance | Confirm PBS status; discuss generics and subsidies |
| Rural | Pathology access delays; stock issues | Coordinate local pathology and medicine delivery |
| Indigenous Communities | Higher liver disease prevalence; cultural concerns | Culturally safe communication and involve local health workers |
Availability And Pricing Patterns
Where can patients get Casodex and how much might it cost?
Casodex by AstraZeneca is the recognised brand and generics may be sourced via import or local licences per the supplier landscape.
Dispensing in Australia occurs through major chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart, and through accredited online pharmacies that accept valid e‑prescriptions.
Pricing varies markedly between PBS‑subsidised dispensing and private prescriptions for non‑PBS formulations, so always confirm PBS listing and authority requirements before prescribing.
Rural pharmacies may experience stock delays, and patients should be advised to allow extra time for repeat supplies or use pharmacy delivery networks.
Storage and transport guidance is to store below 25°C and keep the medicine in its original packaging during transport.
In our online pharmacy, casodex is available without a prescription, with discreet delivery to Australia in 5-14 days.
| Prescription Type | Typical Price Pattern |
|---|---|
| PBS‑Subsidised | Low patient co‑payment where listed and approved |
| Private Prescription | Higher out‑of‑pocket cost for brand or non‑PBS supply |
| Online Import/Generic | Variable pricing; check supplier and regulatory status |
Prescribers should verify PBS eligibility, authority requirements and local stock before finalising a treatment plan.
Comparable Medicines And Preferences
Which alternatives should clinicians consider when selecting hormonal therapy?
Main comparators include first‑generation anti‑androgens flutamide and nilutamide and second‑generation agents enzalutamide, apalutamide and darolutamide.
Advantages of bicalutamide include oral dosing, generally good tolerability for many patients and lower CNS side effects than enzalutamide.
Disadvantages are lower potency for survival endpoints compared with several modern agents and ongoing risks of gynecomastia and hepatic enzyme elevations.
In Australia, PBS subsidy status, cost, comorbidities (especially liver disease) and the risk of CNS effects influence agent selection more than theoretical efficacy alone.
| Agent | Efficacy Profile | Common AEs | PBS Status (Check Locally) |
|---|---|---|---|
| Bicalutamide (Casodex) | Effective with LHRH for symptom control; less potent vs some 2nd‑gen agents | Gynecomastia, ALT/AST rise, hot flushes | Varies; confirm current PBS listing |
| Enzalutamide (Xtandi) | Higher potency for several survival endpoints | CNS effects, fatigue, risk of seizures | Subsidy dependent; check PBS |
| Apalutamide / Darolutamide | Strong activity in non‑metastatic and metastatic settings | Fatigue, rash, variable hepatic effects | Subsidy and indication specific |
A pros and cons checklist and decision matrix helps pharmacists and prescribers support shared decision‑making tailored to each patient.
Frequently Asked Questions
Is Casodex on the PBS?
PBS listings can change and prescribers should check the current PBS schedule and any authority requirements.
How should Casodex be taken?
Usually once daily by mouth; 50 mg with an LHRH analogue for metastatic disease and 150 mg monotherapy in selected locally advanced cases where authorised.
What side effects should be reported urgently?
Report new jaundice, severe abdominal pain, persistent nausea, marked fatigue, unusual bruising or bleeding, or significant mood or CNS changes for urgent review and LFT/INR checks if on warfarin.
Can alcohol be consumed?
Alcohol should be limited as it increases hepatic risk while taking bicalutamide.
Definitions:
- PSA: Prostate‑specific antigen, a blood marker used to monitor prostate cancer.
- LHRH: Luteinising hormone‑releasing hormone analogues used to suppress testosterone production.
Guidelines For Proper Use
What should pharmacists cover when counselling patients starting Casodex?
Confirm the indication and review the full medication list, with attention to warfarin and other hepatotoxics.
Advise dosing clearly: 50 mg daily with an LHRH analogue, or 150 mg daily as monotherapy where authorised regionally.
Emphasise liver‑function monitoring with baseline tests and monthly checks for the first three months unless local oncology protocols state otherwise.
Encourage adherence and explain missed‑dose rules and storage below 25°C in the original pack.
For telehealth and rural patients, arrange local pathology access and coordinate medicine delivery or local dispensing.
Escalation triggers for urgent review include symptoms of liver injury, marked bleeding while on anticoagulants, or new psychiatric/CNS events.
Document PBS authority details where relevant and report adverse events to the TGA.
Pharmacist Counselling Script (One Page):
- Confirm patient understands indication and dosing schedule.
- Advise baseline LFTs and monthly monitoring for the first three months.
- Check interactions, especially with warfarin; advise additional INR checks.
- Warn about gynecomastia, hot flushes and common GI effects; provide symptomatic advice.
- Arrange delivery or local pharmacy pick up and provide contact details for urgent concerns.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Hobart | Tasmania | 5-9 days |
| Darwin | Northern Territory | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |