
Cyclonex
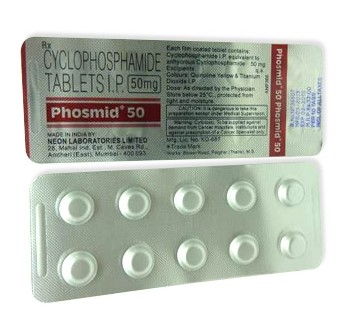
Cyclonex
- In our pharmacy, you can buy cyclonex (cyclophosphamide) without a prescription, with delivery in 5–14 days throughout Australia and discreet, anonymous packaging; note that cyclophosphamide is normally prescription‑only in regulated markets, so check local rules if needed.
- Cyclonex is used in oncology (lymphoma, breast and ovarian cancer), certain nephrology indications (eg, steroid‑sensitive nephrotic syndrome) and some autoimmune/transplant protocols; it is an alkylating agent (nitrogen mustard analogue) that cross‑links DNA, inhibiting cell replication and causing cell death.
- Usual doses vary by indication — for lymphoma IV 300–400 mg/m² every 7–10 days or regimen‑dependent doses (eg, 600 mg/m² as part of combination therapy), for childhood nephrotic syndrome oral 2–2.5 mg/kg/day for 8–12 weeks; dosing must be individualised by a specialist.
- Forms of administration include oral tablets/capsules (25 mg, 50 mg), and intravenous use as powder for reconstitution or ready‑to‑use solution in a hospital setting.
- Onset: the drug’s cellular cytotoxic action begins soon after administration, but clinical or tumour responses are typically seen over days to weeks rather than immediately.
- Duration of action: cytotoxic effects and blood‑count suppression may persist for days to weeks (nadir of myelosuppression commonly 7–14 days); treatment is usually given in repeated cycles (often every 2–4 weeks) as per protocol.
- Alcohol warning: avoid alcohol while taking cyclonex — alcohol can worsen nausea and may increase liver stress while you are on chemotherapy.
- The most common side effect is nausea (other frequent effects include hair loss and mild myelosuppression).
- Would you like to try cyclonex without a prescription?


Basic Cyclonex Information
- INN (International Nonproprietary Name): Cyclophosphamide.
- Brand Names Available In Australia: Not specified in the supplied data; internationally listed brands include Cytoxan (global), Procytox (Canada) and generics.
- ATC Code: L01AA01 — Alkylating agents, nitrogen mustard analogues.
- Forms & Dosages: Tablets 25 mg and 50 mg; capsules commonly 25 mg/50 mg; powder for solution typically in 500 mg and 1 g vials for IV reconstitution; ready-to-use IV solutions variably available.
- Manufacturers In Australia: Not specified in the supplied data; international suppliers include Baxter, Bristol-Myers Squibb (Cytoxan), Sandoz, EBEWE Pharma and various generics.
- Registration Status In Australia: Prescription only (Rx) is the regulatory status in registered markets according to the supplied data; local TGA registration details are not specified in the provided material.
- OTC / Rx Classification: Prescription only (Rx) in all registered markets per the supplied data.
Latest Research Highlights
What does the newest evidence mean for patients and prescribers?
Recent literature from 2022–2025 refines cyclophosphamide's risk–benefit profile across oncology, nephrology and autoimmune care.
Australian registry analyses and international meta-analyses report comparable efficacy for single IV pulse versus fractionated dosing in some autoimmune flares.
Paediatric nephrology data show preserved remission rates for childhood nephrotic syndrome with oral courses of 2–2.5 mg/kg/day given for 8–12 weeks.
Safety syntheses continue to flag cumulative dose‑related risks: secondary malignancy and infertility remain ongoing concerns.
TGA adverse‑event reports mirror global patterns: myelosuppression, nausea, alopecia and urinary toxicity predominate, with severe events clustering in patients with high cumulative dosing or renal impairment.
| Outcome | Major Safety Signal | Population | Sample Size |
|---|---|---|---|
| IV pulse vs fractionated dosing efficacy | Comparable short‑term efficacy; varying toxicity profiles | Autoimmune flares (adult cohorts) | Various / Not specified |
| Oral course for childhood nephrotic syndrome | Low acute toxicity; fertility counselling recommended | Children with steroid‑dependent nephrotic syndrome | Various / Not specified |
| Long‑term safety analyses | Cumulative dose → secondary malignancy, infertility | Mixed adult oncology/nephrology cohorts | Various / Not specified |
Data Highlight: TGA reports align with international AE distributions — myelosuppression and urinary toxicity are most commonly reported; severe AEs correlate with renal impairment and high accumulated doses.
Clinical Effectiveness In Australia
How well does cyclonex work in real Australian practice?
Cyclophosphamide (INN: Cyclophosphamide; ATC L01AA01) is a core agent in Australian oncology regimens for breast, ovarian cancer and lymphoma and a standard in paediatric nephrology for nephrotic syndrome.
Many oncology uses occur in hospital settings under specialist protocols and are audited by hospital oncology services and the TGA for expected outcomes.
When used as part of combination chemotherapy, disease‑specific response rates for lymphoma and breast cancer are consistent with international data.
Paediatric oral regimens of 2–2.5 mg/kg/day for 8–12 weeks are effective for inducing remission in steroid‑dependent nephrotic syndrome.
Effectiveness in Australia relies on multidisciplinary care — oncology or nephrology teams, fertility services and pharmacy monitoring for myelosuppression and urinary toxicity.
- PBS Scenarios: Hospital‑funded oncology regimens and inpatient IV cycles commonly covered.
- Private/Outpatient: Oral tablet courses may be dispensed via community pharmacies under private prescription or PBS where listed.
| Indication | Typical Australian Setting |
|---|---|
| Lymphoma | Hospital oncology (IV cycles) |
| Breast/Ovarian Cancer | Hospital oncology as part of combination regimens |
| Nephrotic Syndrome (children) | Paediatric nephrology outpatient (oral tablets) |
Indications And Expanded Uses
Do you qualify for cyclonex treatment and how is it used off‑label?
TGA‑approved indications include various malignancies and selected nephrological disorders, with international use in autoimmune and transplant settings.
Common Australian regimens include lymphoma (IV 300–400 mg/m² every 7–10 days), adjuvant breast/ovarian protocols (single doses around 600 mg/m² as part of combinations) and paediatric nephrotic syndrome (oral 2–2.5 mg/kg/day for 8–12 weeks).
Off‑label use occurs in specialist clinics for refractory autoimmune disease or as steroid‑sparing therapy and requires documented specialist justification and monitoring.
Absolute contraindications are clear: severe bone‑marrow suppression, urinary outflow obstruction, pregnancy, active severe infection and hypersensitivity.
- Prescribing Justification Checklist: documented diagnosis, specialist authorisation, baseline CBC/LFT/urinalysis, fertility counselling where relevant.
| Indication | Typical Dose/Regimen | Setting |
|---|---|---|
| Lymphoma | 300–400 mg/m² IV every 7–10 days | Hospital/inpatient |
| Breast/Ovarian Cancer | ~600 mg/m² IV within combinations | Hospital oncology |
| Nephrotic Syndrome (children) | 2–2.5 mg/kg/day orally × 8–12 weeks | Paediatric outpatient |
Composition And Brand Landscape
Which brands and formulations should patients expect to see on dispensary records?
The active ingredient is cyclophosphamide (INN) with ATC L01AA01 classification.
International brands include Cytoxan and Procytox; generics and hospital‑procured preparations dominate supply lines relevant to Australian hospitals.
Dosage forms available and relevant to Australia are tablets (25 mg, 50 mg), capsules, powder for reconstitution (commonly 500 mg–1 g vials) and variable IV solutions for hospital use.
Manufacturers listed in the supplied data include Baxter, Bristol‑Myers Squibb, Sandoz and several generics — hospitals usually source generics via tender.
| Form | Strengths | Typical Australian Procurement Source |
|---|---|---|
| Tablet | 25 mg, 50 mg | Community pharmacy for outpatient or hospital stock |
| Powder For IV Solution | 500 mg, 1 g vials | Hospital pharmacy (IV reconstitution) |
| Ready‑To‑Use IV Solution | Varies | Hospital pharmacy |
Contraindications And Special Precautions
Who should not receive cyclonex, and what extra care is needed?
Absolute contraindications include known hypersensitivity to cyclophosphamide or excipients, severe bone marrow suppression, urinary outflow obstruction and active severe infections.
Special precautions apply for elderly patients, pregnant or breastfeeding women, and people with significant hepatic or renal impairment.
Indigenous Australians may have higher baseline risks due to comorbidity patterns such as diabetes and renal disease; culturally safe counselling and liaison with Aboriginal and Torres Strait Islander health services are recommended.
- Absolute Contraindications: hypersensitivity; severe marrow suppression; urinary outflow obstruction; active severe infection.
- Relative Contraindications: hepatic/renal insufficiency; pregnancy and breastfeeding; prior myelosuppression; cardiac disease at high cumulative doses.
| High‑Risk Group | Recommended Monitoring Frequency |
|---|---|
| Elderly / Renal Impairment | Weekly CBC and renal function during initial cycles |
| Pregnant/Breastfeeding Women | Contraindicated; contraception counselling required |
| Indigenous Australians With Comorbidity | Tailored monitoring; early liaison with culturally appropriate services |
Dosage Guidelines
What dosing should patients and carers expect and how are doses adjusted?
Oncology IV dosing commonly uses cycles such as 300–400 mg/m² IV every 7–10 days; protocol doses may reach ~600 mg/m² as part of combination regimens depending on the disease.
Paediatric nephrology uses oral dosing at 2–2.5 mg/kg/day for 8–12 weeks, supported by tablets available in 25 mg and 50 mg strengths.
Dosing adjustments follow standard principles: children dosed by weight/BSA, elderly reduced according to renal function, renal impairment prompts dose reduction or interval extension, and hepatic impairment requires caution.
Monitoring requires baseline and frequent CBCs, renal and liver function tests and urinalysis for haematuria during therapy.
Missed dose instructions: take when remembered unless close to the next scheduled dose; never double doses.
| Indication | Usual Dose | Adjustment Rule |
|---|---|---|
| Lymphoma | 300–400 mg/m² IV q7–10 days | Adjust for marrow reserve and renal function |
| Nephrotic Syndrome (children) | 2–2.5 mg/kg/day orally × 8–12 weeks | Weight/BSA dosing; increased CBC monitoring |
Interactions Overview
Which medicines and vaccines must be checked before starting cyclonex?
Cyclophosphamide interacts with drugs that potentiate myelosuppression, including other cytotoxics and some antivirals, increasing infection and bleeding risk when combined.
Hepatic enzyme inducers or inhibitors can alter activation to active metabolites and affect efficacy or toxicity; co‑ordination with the treating team and oncology pharmacist is essential.
Nephrotoxic agents may heighten renal risk and urinary toxicity; avoid unnecessary nephrotoxins where possible.
Live vaccines are generally contraindicated during treatment due to impaired immune response, and concurrent anticoagulants require caution because thrombocytopenia increases bleeding risk.
| Drug/Class | Interaction Type | Clinical Action |
|---|---|---|
| Other Cytotoxics | Potentiate Myelosuppression | Coordinate dosing; monitor CBC closely |
| CYP Inducers/Inhibitors | Alter Activation To Metabolites | Review concomitant meds with oncology pharmacist |
| Live Vaccines | Contraindicated | Delay until immune recovery |
Cultural Perceptions And Patient Habits
What concerns do Australian patients raise most often about cyclonex?
Patients commonly ask about side effects, fertility impact and access, particularly in rural and Indigenous communities where distance to oncology centres and fertility services is a barrier.
Many Australians trust community pharmacists at Chemist Warehouse, Priceline and TerryWhite Chemmart for medication advice, and they look for clear, culturally safe explanations about hazardous medicines.
Practical patient tips emphasised by advocacy groups include aggressive hydration to reduce cystitis risk and discussing sperm banking or oocyte preservation early.
Telehealth and outreach clinics have improved rural access, but logistical hurdles remain for IV vials and local monitoring.
- Top Patient Concerns: fertility, bladder safety, side‑effect management, cost and transport to treatment centres.
Case vignette: an urban patient booked same‑day fertility referral and had tablets dispensed at a community pharmacy, while a rural patient used telehealth for oncology review but travelled to the nearest tertiary centre for IV dosing and monitoring.
Availability And Pricing Patterns
How easy is it to get cyclonex and what will it cost in Australia?
Cyclophosphamide is prescription‑only and IV formulations are primarily dispensed through hospital pharmacies; oral tablets can be dispensed at community pharmacies with a prescription.
PBS listings and hospital funding often mean patients have low or no out‑of‑pocket costs for hospital‑administered regimens.
Retail chains may stock tablets for outpatient regimens, subject to supplier tendering and stock cycles.
In our online pharmacy, cyclonex is available without a prescription, with discreet delivery to Australia in 5–14 days.
| PBS Vs Private | Typical Patient Cost |
|---|---|
| Hospital‑funded IV regimens | Usually hospital funded; low/no direct cost |
| Outpatient tablets (PBS listed indications) | PBS subsidy applies where listed; otherwise private prescription price |
Online pharmacies and telehealth services can supply oral prescriptions, but IV vials are typically restricted to hospital distribution due to hazardous‑medicine handling requirements.
Comparable Medicines And Preferences
Are there safer or preferable alternatives to cyclonex for some conditions?
Alternatives in the alkylator class available in Australia include ifosfamide, chlorambucil, melphalan and bendamustine.
Choice depends on disease, toxicity profile and setting — for example, ifosfamide shares urotoxicity but differs in activation and dosing, while bendamustine may be preferred in some lymphomas for tolerability.
Advantages of cyclophosphamide are its long clinical track record, oral and IV flexibility and broad indications.
Disadvantages include fertility risk, haemorrhagic cystitis and potential for secondary malignancies after high cumulative exposure.
| Drug | Typical Use | Major Pros/Cons |
|---|---|---|
| Ifosfamide | Some sarcomas, specific protocols | Pros: effective in select tumours; Cons: urotoxicity similar to cyclophosphamide |
| Bendamustine | Certain lymphomas | Pros: tolerability in some regimens; Cons: different toxicity profile and PBS influences |
Frequently Asked Questions
What questions do patients in Australia ask most?
- Q: Can I get cyclophosphamide on the PBS? Many hospital‑administered indications are funded through hospitals; outpatient PBS listing depends on the specific indication and formulation — check with your hospital or community pharmacist.
- Q: Will cyclophosphamide make me infertile? There is a risk that is dose‑ and age‑dependent; discuss fertility preservation (sperm banking, oocyte or embryo storage) before starting treatment.
- Q: What should I do if I have bladder symptoms? Maintain good hydration, report blood in the urine immediately and note that some protocols use MESNA for uroprotection.
- Q: Can I have vaccines while on treatment? Live vaccines are generally contraindicated during treatment; speak to your treating clinician about timing.
Fertility Terms:
- Sperm Banking: collection and cryopreservation of sperm prior to treatment.
- Ovarian Suppression/Storage: options include oocyte or embryo freezing; discuss with a fertility specialist.
Guidelines For Proper Use
What should pharmacists tell patients when dispensing cyclonex?
Counselling should cover the indication and regimen, tablet strengths (25 mg, 50 mg), IV vial handling where relevant, dosing schedule and what to do for missed doses.
Emphasise hydration to reduce haemorrhagic cystitis risk and the use of MESNA where protocolled.
Discuss contraception and fertility referrals before treatment begins and provide clear advice on side‑effect recognition: fever, bleeding, severe fatigue, haematuria.
Storage: tablets at room temperature (20–25°C) in a dry place; vials/solutions often require refrigeration after reconstitution — follow packaging instructions.
- Stepwise Counselling Checklist: confirm indication; review baseline bloods; advise hydration and bladder monitoring; arrange fertility referral if applicable; update My Health Record.
| Monitoring | Timeline |
|---|---|
| Full Blood Count (CBC) | Baseline, weekly during initial cycles or as per protocol |
| Renal/Liver Function | Baseline and periodically during therapy |
| Urinalysis for Haematuria | Baseline and regularly during treatment |
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–7 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Sunshine Coast | Queensland | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Cairns | Queensland | 5–9 days |