
Methotrexate
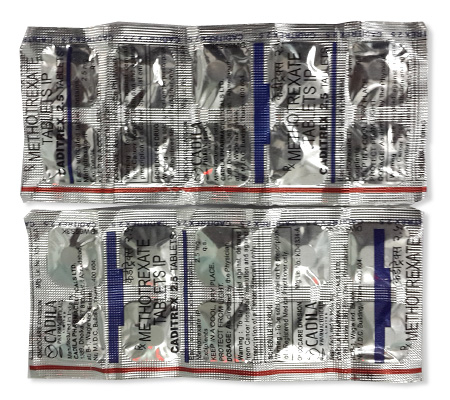
Methotrexate
- In our pharmacy, you can buy methotrexate without a prescription, with delivery in 5–14 days throughout Australia and discreet packaging; however, methotrexate is a potent prescription-only medicine in many regions and should only be used under medical supervision due to serious risks.
- Methotrexate is used for certain cancers, rheumatoid arthritis, psoriasis and other autoimmune conditions; it is an antimetabolite/antifolate that inhibits dihydrofolate reductase and other folate‑dependent enzymes, blocking DNA synthesis and exerting immunomodulatory effects at low doses.
- Usual doses vary by indication: for rheumatoid arthritis and psoriasis typical oral dosing is 7.5–25 mg once weekly (often 10–25 mg weekly); oncology dosing is much higher and varies by protocol (including high‑dose regimens given by weight or body surface area).
- The drug is given orally (tablets or oral solution) or by injection (intravenous, intramuscular or subcutaneous using vials, ampoules, prefilled syringes or autoinjectors).
- Symptomatic improvement for inflammatory conditions usually begins after 3–6 weeks (may take up to 3 months for full effect); cytotoxic effects in chemotherapy can occur sooner but clinical response timing varies.
- The duration of action depends on indication and dosing—weekly dosing provides ongoing effect over a week with intracellular polyglutamates persisting longer; maintenance therapy is required for continued benefit.
- Avoid alcohol while taking methotrexate — alcohol increases the risk of liver damage and other toxicities.
- The most common side effect is nausea (other frequent adverse effects include mouth ulcers, liver enzyme elevations and bone marrow suppression).
- Would you like to try methotrexate without a prescription?


Basic Methotrexate Information
- INN (International Nonproprietary Name): Methotrexate
- Brand Names Available In Australia: not specified
- ATC Code: L01BA01
- Forms & Dosages: Oral tablets 2.5 mg, 5 mg, 7.5 mg, 10 mg, 15 mg; oral solution 2 mg/ml and 2.5 mg/ml (Jylamvo, Xatmep); injection vials/ampoules 10 mg/ml and 25 mg/ml
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: not specified
Latest Research Highlights
Worried about whether methotrexate is still the right choice for arthritis, psoriasis or cancer?
Recent Australian and international research from 2022 to mid-2024 keeps low-dose weekly methotrexate as a mainstay for rheumatoid arthritis and psoriasis, with consistent real‑world effectiveness reported in cohort analyses.
Studies show that switching from oral to subcutaneous administration can improve bioavailability and reduce gastrointestinal side effects for some patients, supporting a practical choice when oral tolerance is limited.
Folic acid supplementation continues to appear protective against mucosal and hepatic toxicity and is the routine co-prescription in inflammatory disease regimens.
Combination strategies using methotrexate with targeted biologics or JAK inhibitors demonstrate faster disease control in early rheumatoid arthritis trials, though these approaches require specialist oversight for infection risk and monitoring.
Australian registry and cohort work mirrors global safety signals: pneumonitis is rare but can be serious, and cumulative hepatotoxicity remains a concern that regular monitoring reduces.
Ongoing trials through 2023–25 are exploring optimised dosing schedules and pharmacogenomic predictors of adverse events, with preliminary reports indicating genotype‑guided strategies might lower toxicity but are not yet standard practice.
| Study Type | Population | Key Outcome | Safety Signal |
|---|---|---|---|
| Real‑World Cohorts | RA and Psoriasis Patients | Consistent effectiveness of low‑dose weekly methotrexate | Rare pneumonitis; cumulative liver enzyme changes |
| Administration Route Trials | Patients intolerant to oral MTX | Subcutaneous MTX improves bioavailability and GI tolerance | Local injection site reactions; fewer GI AEs |
| Early RA Combination Trials | Early Rheumatoid Arthritis | Methotrexate + biologic/JAK gives faster control | Increased infection risk; needs monitoring |
| Pharmacogenomic Studies (Prelim) | Mixed Populations | Genotype‑guided dosing may reduce toxicity | Not yet routine; further validation required |
Clinical Effectiveness In Australia
Are Australians getting the same benefits from methotrexate as patients overseas?
In routine Australian practice, methotrexate delivers sustained improvements in disease activity and quality of life for rheumatoid arthritis and psoriatic disease and remains an important component of many oncology regimens.
PBS‑covered indications and common combination therapy pathways support measurable gains in primary and specialist care settings across the country.
TGA adverse‑event reporting and state health datasets show predictable toxicity patterns—myelosuppression, hepatotoxicity and interstitial pneumonitis—while confirming severe events are infrequent when monitoring protocols are followed.
Outcomes vary with route of administration, patient adherence and comorbidities, and rural patients may face delays in initiation or optimisation because of specialist access barriers.
| Route | Typical Outcome | Monitoring Notes |
|---|---|---|
| Oral | Good efficacy for many; GI intolerance possible | Regular FBC, LFTs; consider switch if GI AEs |
| Subcutaneous | Higher bioavailability; improved GI tolerability | Same blood monitoring; check injection technique |
| IV/High‑Dose (Oncology) | Protocol‑driven tumour control with rescue measures | Intensive monitoring, leucovorin rescue where indicated |
Indications And Expanded Uses
Wondering what methotrexate is approved to treat in Australia and where it’s used off‑label?
TGA‑recognised and routinely used indications include treatment within oncology regimens, moderate‑to‑severe rheumatoid arthritis, and severe psoriasis.
Clinicians also use low‑dose methotrexate off‑label for several inflammatory conditions where evidence supports benefit, but off‑label use requires specialist guidance and documentation.
- Approved Uses: Oncology regimens, rheumatoid arthritis, severe psoriasis.
- Common Off‑Label Uses: Selected cases of Crohn’s disease, some dermatological inflammatory disorders, and as medical management for certain ectopic pregnancies under specialist protocols.
Off‑label prescribing should always follow specialist direction, documented informed consent and PBS rules where subsidies are sought.
Composition And Brand Landscape
Curious which brands and forms of methotrexate you might see at the pharmacy or hospital?
Methotrexate is the International Nonproprietary Name and is classified as an antimetabolite folic‑acid analogue under ATC code L01BA01, indicating antineoplastic and immunomodulating activity.
Global brand diversity includes names such as Rheumatrex, Trexall, Otrexup, Rasuvo, Xatmep, Jylamvo, Nordimet, Ledertrexate, Maxtrex, Metex/Metoject and many generics.
Available forms are oral tablets (2.5–15 mg), oral solutions (2–2.5 mg/mL) and injectable vials/syringes (10 mg/mL and 25 mg/mL), with autoinjectors sold in some markets.
| Brand | Form/Dose | Australian Availability / PBS |
|---|---|---|
| Rheumatrex | Tablets 2.5 mg | not specified |
| Trexall | Tablets 5–15 mg | not specified |
| Rasuvo / Otrexup | Autoinjector (various doses) | Less commonly stocked; hospital/specialty supply |
| Jylamvo / Xatmep | Oral solution 2–2.5 mg/ml | not specified |
The Australian market is largely supplied by generics and PBS‑listed presentations, while branded autoinjectors and prefilled syringes are more often supplied through hospitals or specialty pharmacies.
Contraindications And Special Precautions
Worried about whether methotrexate is safe for you or a family member?
Absolute contraindications include pregnancy and breastfeeding because methotrexate is teratogenic and embryotoxic.
Major precautions cover significant hepatic impairment, severe renal dysfunction which reduces clearance, active infections, existing bone marrow suppression and recent live vaccination.
- High‑Risk Groups: Elderly patients on multiple medicines, people with chronic viral hepatitis, and some Indigenous communities where comorbidity and access barriers increase risk and require culturally safe assessment.
- Practical Advice: Use effective contraception during and after therapy as advised by your specialist, avoid excess alcohol, and report new breathlessness or respiratory symptoms immediately because of pneumonitis risk.
| Population | Precaution |
|---|---|
| Pregnant or Breastfeeding | Contraindicated |
| Severe Renal Impairment | Reduce dose or avoid; monitor clearance closely |
| Chronic Liver Disease | Consider alternative therapy; close LFT monitoring |
Dosage Guidelines
Not sure how often and how much methotrexate to take for arthritis or psoriasis?
For inflammatory diseases in Australia, low‑dose methotrexate is given once weekly, typically starting between 7.5 mg and titrating up to 25 mg once weekly according to response and tolerability.
Folic acid supplementation is standard practice to reduce mucosal and hepatic toxicity and is commonly prescribed as 5–10 mg weekly or 1 mg daily except on the methotrexate day.
Oncology regimens use much higher, weight‑based or protocol‑driven dosing with leucovorin rescue when indicated and require hospital administration and monitoring.
Renal impairment usually requires dose reduction or avoidance, and elderly patients frequently start at lower doses with more frequent blood tests.
| Regimen Type | Typical Dose Range | Adjustment Notes |
|---|---|---|
| Low‑Dose (Inflammatory Disease) | 7.5–25 mg once weekly | Start low, titrate; give folic acid |
| High‑Dose (Oncology) | Protocol/weight based | Hospital administration, leucovorin rescue as required |
| Renal Impairment | Reduced dose or avoid | Adjust by eGFR; consult specialist/PBS protocols |
Interactions Overview
Worried that your other medicines or habits might make methotrexate unsafe?
Non‑steroidal anti‑inflammatories and some antibiotics such as trimethoprim‑sulfamethoxazole can raise methotrexate levels and increase the risk of myelosuppression.
Proton‑pump inhibitors may alter methotrexate elimination, and concurrent hepatotoxins—alcohol and some statins—increase liver risk.
Live vaccines are contraindicated while on significant immunosuppression, and combining methotrexate with biologic agents or JAK inhibitors increases infection risk and needs specialist oversight.
| Drug/Agent | Risk | Recommended Action |
|---|---|---|
| NSAIDs | Increased MTX levels and myelosuppression | Review necessity; monitor blood counts |
| Trimethoprim‑sulfamethoxazole | Severe bone marrow suppression risk | Avoid or use with extreme caution |
| Alcohol | Increased hepatotoxicity | Advise avoidance or minimisation |
Moderation of coffee intake is reasonable but strict avoidance is not routinely required based on current evidence; focus on limiting alcohol and managing interacting medicines.
Cultural Perceptions And Patient Habits
Do Australians trust methotrexate, and what practical issues shape use across communities?
Patients often balance the clear benefits against understandable fears about toxicity and fertility, and these concerns commonly appear in pharmacy consultations and online forums.
PBS subsidies and price sensitivity strongly influence adherence and brand choice, with many people preferring generics or comparing prices across large chains and online pharmacies.
Rural patients may face delayed specialist input and longer gaps between monitoring tests, relying more on local pharmacists and telehealth for prescription renewals and advice.
Indigenous Australians may experience cultural barriers to care and benefit from culturally competent counselling, community engagement and flexible monitoring approaches.
Pharmacists are a trusted local resource to reinforce once‑weekly dosing, folic acid use and monitoring reminders, which improves adherence and safety.
| Access Factor | Rural | Urban |
|---|---|---|
| Specialist Access | Longer wait times | Shorter wait times |
| Monitoring Frequency | Potential delays | Regular local pathology access |
Availability And Pricing Patterns
How easy and affordable is it to get methotrexate across Australia?
Methotrexate is widely available through community pharmacies and hospitals nationwide, and PBS listings mean low co‑payments for eligible patients for approved indications.
Private scripts and non‑PBS presentations can vary in price between major chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart, and online pharmacies may offer different pricing.
Autoinjectors or specialist injectable brands are less common in community pharmacies and are often obtained via hospital procurement or specialty suppliers.
Telehealth and e‑prescriptions have improved access for many patients, but blood tests still usually require local pathology services.
In our online pharmacy, methotrexate is available without a prescription, with discreet delivery to Australia in 5-14 days.
| Supply Route | PBS Cost | Private Cost |
|---|---|---|
| PBS‑Listed Presentations | Low co‑payment for eligible patients | Not applicable |
| Private Scripts / Non‑PBS | Not subsidised | Varies by retailer |
| Autoinjectors / Branded Injectables | Often hospital or specialty supply | Higher out‑of‑pocket costs if private |
Comparable Medicines And Preferences
Thinking about alternatives to methotrexate for inflammatory disease?
Common alternatives include sulfasalazine, leflunomide and hydroxychloroquine, and for more severe or refractory disease, biologic agents such as TNF or interleukin inhibitors and JAK inhibitors.
Choice depends on disease severity, comorbidities, fertility plans and monitoring capacity, along with patient preferences and cost considerations.
| Medicine | Pros | Cons |
|---|---|---|
| Methotrexate | Effective, affordable under PBS | Requires monitoring; teratogenic |
| Leflunomide | Effective alternative | Teratogenic; long washout period |
| Sulfasalazine | Safer in pregnancy | Less potent for severe disease |
| Biologics / JAK Inhibitors | High efficacy for many patients | Costly; PBS restrictions in place |
For many rural and price‑sensitive patients, methotrexate remains the first choice because of PBS coverage and established efficacy.
Frequently Asked Questions
How often do I take methotrexate?
For inflammatory conditions in Australia it is taken once weekly; it is never taken daily unless on a specific oncology protocol that instructs otherwise.
Do I need blood tests?
Yes, baseline and ongoing full blood count, liver function tests and renal function are required, typically every 2–4 weeks when starting and spaced out if stable as per specialist or PBS guidance.
Can I drink alcohol?
Avoid or minimise alcohol because it raises the risk of hepatotoxicity; discuss safe limits with your prescriber.
What about family planning?
Methotrexate is teratogenic, so effective contraception is essential for men and women during treatment and for a specialist‑advised washout period before conception.
Guidelines For Proper Use
What should you expect from a pharmacist when starting or dispensing methotrexate?
Pharmacist counselling should confirm the weekly dosing day, explain and supply the folic acid regimen, and review current medicines for potential interactions.
Counselling should reinforce contraception advice, arrange or remind about monitoring blood tests, and provide clear actions for urgent signs such as fever, sore throat, unexplained bruising, jaundice or new breathlessness.
Storage and handling instructions include keeping tablets and solutions in original packaging at room temperature and following manufacturer directions for injectable preparations.
Training in subcutaneous injection technique is essential before self‑administration if an autoinjector or prefilled syringe is dispensed.
- Pharmacist Counselling Checklist: Confirm weekly dosing day; advise folic acid; review medicines; reinforce contraception; arrange monitoring.
| Monitoring Stage | Typical Tests | Frequency |
|---|---|---|
| Baseline | FBC, LFTs, Renal Function | Before starting |
| Initiation | FBC, LFTs, Renal Function | Every 2–4 weeks until stable |
| Maintenance | FBC, LFTs, Renal Function | Every 8–12 weeks or as advised |
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Darwin | Northern Territory | 5-9 days |