
Leukeran
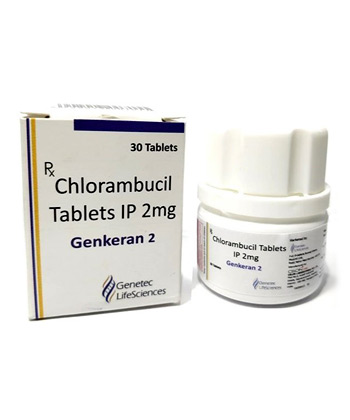
Leukeran
- In our pharmacy, you can buy leukeran without a prescription, with delivery across Australia in 5–14 days and discreet, anonymous packaging.
- Leukeran (chlorambucil) is used to treat chronic lymphocytic leukaemia (CLL), Hodgkin lymphoma and certain non‑Hodgkin lymphomas; it is an alkylating antineoplastic agent that cross‑links DNA, inhibiting DNA replication and causing cancer cell death.
- Usual adult doses vary by condition — CLL: typically 0.1–0.2 mg/kg/day orally until white cell counts fall, maintenance 2–8 mg/day; Hodgkin lymphoma: ~0.2 mg/kg/day for 4–8 weeks or intermittent cycles; non‑Hodgkin lymphoma: 0.1–0.2 mg/kg/day or intermittent cycles. Tablets are 2 mg each.
- Administration is oral — film‑coated tablets (2 mg), taken by mouth as directed by a clinician.
- Onset: cytotoxic/blood‑count effects usually develop over days to weeks — reductions in white cell count are often evident within 1–2 weeks; clinical tumour responses may take several weeks.
- Duration of action: effects are prolonged and cumulative; treatment is typically cyclical and continued for weeks to months, and myelosuppressive effects can persist for days to weeks after dosing.
- Alcohol warning: avoid alcohol while taking Leukeran where possible — alcohol can worsen nausea, interact with liver function and increase overall side effects; discuss alcohol use with your prescriber.
- The most common side effect is bone marrow suppression (leukopenia/neutropenia, anaemia, thrombocytopenia); other frequent effects include nausea, vomiting, diarrhoea, mouth sores, rash and fatigue; long‑term risks include infertility and secondary malignancy.
- Would you like to try leukeran without a prescription?


Latest Research Highlights
Basic Leukeran Information
- INN (International Nonproprietary Name): Chlorambucil
- Brand Names Available In Australia: not specified
- ATC Code: L01AA02
- Forms & Dosages: Film-coated tablet, 2 mg
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription-only medicine (Rx)
What do clinicians and patients need to know about current evidence for leukeran and chlorambucil?
Recent Australian and international reviews (2022–mid-2024) reinforced chlorambucil’s niche role as an effective, low-cost oral alkylating therapy for older or frail patients with chronic lymphocytic leukaemia and some indolent lymphomas.
Data summarised in those reviews show modest overall response rates when chlorambucil is used alone for CLL, with better disease control when combined with steroids or anti‑CD20 antibodies.
There is consistent safety signal for cumulative myelosuppression and occasional reports of late secondary malignancies, reinforcing the need for long-term follow up and counselling about infertility risk.
Real-world Australian haematology audits and international cohort studies note chlorambucil remains used where oral therapy and low clinic burden are priorities, including palliative settings and resource-limited contexts.
Contemporary practice in many centres has shifted toward targeted agents for first-line CLL, but chlorambucil retains value where cost, frailty or logistics limit other options.
Key outcomes to watch: overall response rate, progression-free survival, grade 3–4 neutropaenia and secondary malignancy incidence when reviewing treatment options for older patients.
Clinical Effectiveness In Australia
Which patients in Australia still benefit from leukeran therapy?
In Australian practice, chlorambucil (INN: chlorambucil; brand: Leukeran) is an effective option for selected patients, particularly elderly CLL patients unsuitable for intensive chemoimmunotherapy or oral targeted agents.
TGA adverse‑event reporting and hospital oncology registries document predictable haematologic responses when dosing follows slow escalation and blood‑count guided maintenance.
Usual starting ranges in CLL are 0.1–0.2 mg/kg/day with maintenance dosing commonly between 2–8 mg/day, adjusted to tolerance and blood counts.
Where the PBS subsidises therapy uptake increases in cost‑sensitive cohorts, while PBS approvals for newer targeted drugs have reduced first‑line chlorambucil use in many patients.
Australian tertiary centres report the best results when chlorambucil treatment is supported by close CBC monitoring, prompt management of neutropaenia, and access to supportive measures such as growth factors and infection prophylaxis where indicated.
When discussing options with patients, include information about leukeran tablets, expected timelines for response, monitoring requirements and likely adverse effects so consent is informed and practical arrangements for blood tests are in place.
Indications & Expanded Uses
What is leukeran approved for, and when is it used off‑label?
TGA‑aligned indications reflect international approvals: chronic lymphocytic leukaemia, Hodgkin lymphoma and certain non‑Hodgkin lymphomas, including follicular lymphoma and lymphosarcoma.
In routine Australian practice, off‑label uses sometimes include low‑dose chlorambucil for palliation, autoimmune cytopenias associated with lymphoproliferative disease, or as a bridge where intravenous chemotherapy is impractical.
Paediatric use is uncommon because safety and efficacy are not well established; any use in children should be specialist‑led and documented.
The arrival of targeted oral agents such as ibrutinib and venetoclax has changed treatment pathways for many CLL patients, but chlorambucil remains a reasonable choice when comorbidity, frailty, logistics or cost preclude targeted therapy.
When considering leukeran for lymphoma or leukaemia, document the indication clearly (TGA‑aligned vs off‑label) and ensure patients understand the rationale and monitoring plan.
- TGA‑Approved Uses: CLL, Hodgkin lymphoma, selected NHL subtypes.
- Common Off‑Label Uses: Palliation, autoimmune cytopenias, bridging therapy where IV access or travel is prohibitive.
Composition & Brand Landscape
What’s in the tablet and which brands might you see?
The active ingredient is chlorambucil (INN) supplied as film‑coated tablets, typically 2 mg strength.
The internationally familiar brand is Leukeran, marketed as 2 mg tablets in bottle or blister packs, and other generics exist under the INN chlorambucil or regional trade names such as Chloraminophene.
Global suppliers include Aspen Pharmacare as a primary international supplier for Leukeran tablets; local packaging and market authorisation can differ by region.
Chlorambucil is classified under ATC code L01AA02 as an alkylating antineoplastic agent.
For pharmacists: check the TGA ARTG listings and PBS status before supply and confirm whether a pack is an imported Leukeran or a local generic.
| Active Ingredient | Strength | Brand | Supplier | ATC | Storage |
|---|---|---|---|---|---|
| Chlorambucil | 2 mg | Leukeran (international); generics under INN | Aspen Pharmacare (international supplier) | L01AA02 | Store 20–25°C; protect from light and moisture |
Contraindications & Special Precautions
Who must not take chlorambucil, and who needs closer monitoring?
Absolute contraindications include known hypersensitivity to chlorambucil or excipients, existing severe bone marrow suppression, and pregnancy or breastfeeding because of teratogenicity and passage into milk.
Relative contraindications that demand close monitoring include prior radiotherapy or chemotherapy (reduced marrow reserve), hepatic or renal impairment, active infection, and a history of epilepsy due to seizure reports at high doses.
In Australia, consider special risks in elderly patients with multiple comorbidities and in Aboriginal and Torres Strait Islander peoples where infectious disease burden and access to monitoring may complicate therapy.
Daily‑life safety advice: avoid pregnancy, use effective contraception during and after treatment as advised by the treating team, and be cautious with activities that put the patient at risk if cytopenic (heavy machinery, working at heights).
- Absolute Contraindications: Hypersensitivity, severe marrow suppression, pregnancy, breastfeeding.
- Relative Contraindications: Prior chemoradiation, liver or kidney impairment, active infection, epilepsy.
Dosage Guidelines
How is leukeran dosed and what monitoring is required?
Standard adult dosing is weight‑based with slow escalation; for CLL typical initiation is 0.1–0.2 mg/kg/day until white cell counts fall, then maintenance commonly 2–8 mg/day.
For Hodgkin lymphoma a common regimen is 0.2 mg/kg/day for 4–8 weeks or as intermittent cycles, and NHL dosing generally mirrors CLL patterns.
Children: dosing is not routine and should be determined only by oncology specialists.
Elderly patients and those with hepatic or renal impairment should start low and titrate cautiously with close monitoring for myelosuppression.
Baseline CBC before starting, weekly monitoring during dose changes, then interval testing as advised by haematology are typical practice points.
| Condition | Typical Dose | Monitoring Schedule | Dose Adjustment Triggers |
|---|---|---|---|
| CLL | 0.1–0.2 mg/kg/day; maintenance 2–8 mg/day | CBC baseline, weekly during titration, then per haematology | Neutrophils <1.0 x10^9/L or platelets <75 x10^9/L — hold or reduce dose |
| Hodgkin/NHL | 0.2 mg/kg/day for 4–8 weeks or cycles | As above | Clinically significant cytopenias or organ dysfunction |
Missed dose: take when remembered unless near next dose; do not double up.
Overdose: urgent hospital care is required because of severe marrow suppression risk.
Interactions Overview
Which medicines and substances increase risk when taken with chlorambucil?
Most clinically relevant interactions are pharmacodynamic, with concurrent myelosuppressive agents increasing the risk of severe neutropaenia and thrombocytopenia.
Previous radiotherapy compounds marrow toxicity and drugs that alter hepatic metabolism may affect chlorambucil clearance, although metabolism is complex and interaction data are limited.
Avoid live vaccines during and until immune recovery after therapy due to impaired vaccine response and infection risk.
There are no strict food interactions, but counsel patients to limit alcohol because of extra hepatic stress and tolerability concerns while on treatment.
- Major Interactions To Review: Other cytotoxics, strong CYP modifiers, recent radiotherapy, live vaccines.
- Practical Tip: Pharmacists should check PBS/eRx and hospital charts for recent chemo or interacting medicines before dispensing Leukeran tablets.
Cultural Perceptions & Patient Habits
How do Australian patients view an oral chemotherapy like leukeran?
Patients often value clear cost information, pharmacist guidance and the convenience of at‑home oral therapy compared with IV regimens that require frequent travel to hospital clinics.
The oral route suits many rural and remote patients who want to reduce hospital visits, but limited pathology access can complicate safe monitoring in those communities.
In Indigenous health contexts, culturally safe discussion is essential when counselling about fertility risk, infection prevention and the need for reliable blood‑test access.
Price sensitivity prompts many patients to ask about PBS subsidy and generic options; pharmacists at community chains remain trusted sources of information and can help arrange care pathways.
- Common Patient Concerns: fertility, infection risk, blood‑test logistics, long‑term malignancy risk.
- Support: local haematology services, Cancer Council resources and peer forums help patients weigh convenience against monitoring needs.
Availability & Pricing Patterns
Where do Australians source leukeran and what will it cost?
Leukeran 2 mg and generics are available internationally and Australian suppliers may import branded or generic packs; check the TGA ARTG for local authorisation and the PBS for subsidy details.
When PBS covers therapy, patient co‑payments are low and uptake is higher; where PBS does not apply, out‑of‑pocket costs and private supply arrangements influence choice between chlorambucil and newer agents.
Cytotoxic medicines are usually dispensed through hospital pharmacies or authorised community pharmacies with the right handling protocols rather than standard retail shelves.
In our online pharmacy, leukeran is available without a prescription, with discreet delivery to Australia in 5-14 days.
| PBS Status | Private Price Range (Estimate) | Typical Dispensing Channels | Handling Requirements |
|---|---|---|---|
| Varies by indication and authority | Varies if not PBS-subsidised | Hospital pharmacy; authorised community cytotoxic dispensaries; select online pharmacies | Standard cytotoxic handling, labelled storage, glove use for splitting/crushing |
Comparable Medicines And Preferences
What are reasonable alternatives to chlorambucil and how do they compare?
Alternatives depend on diagnosis and fitness for treatment: bendamustine, cyclophosphamide, fludarabine and newer targeted agents such as ibrutinib and venetoclax are common comparators.
Targeted agents typically offer superior progression‑free survival in many CLL subgroups and different toxicity spectra, but they carry higher costs and different monitoring needs compared with leukeran.
Bendamustine and cyclophosphamide are IV options requiring clinic resources, while fludarabine is more immunosuppressive and may not suit frail patients.
| Agent | Administration | Main Toxicities | PBS Status (General) | Typical Patient Fit |
|---|---|---|---|---|
| Chlorambucil (Leukeran) | Oral | Myelosuppression, nausea, rare secondary malignancy, infertility | Varies | Elderly, frail, resource‑limited settings |
| Bendamustine | IV | Myelosuppression, infusion‑related reactions | Varies | Patients fit for clinic‑based IV therapy |
| Ibrutinib | Oral | Bleeding risk, atrial fibrillation, hypertension | PBS‑listed for some indications | Many CLL patients, including those unsuitable for cytotoxics |
| Venetoclax | Oral | Tumour lysis risk, neutropaenia | PBS‑listed for selected indications | Selected relapsed/refractory CLL or combination regimens |
FAQ Section
What are the questions patients ask most about leukeran?
Q: Can I get Leukeran on the PBS?
A: PBS listing and authority rules change; check current PBS schedules and your treating team for eligibility and likely out‑of‑pocket cost.
Q: How long before I see results?
A: Haematologic response may take several weeks; dose adjustments are guided by blood counts and clinical response, with frequent monitoring early in treatment.
Q: Will it affect fertility?
A: Chlorambucil can cause irreversible sterility and amenorrhoea; discuss fertility preservation before starting treatment.
Q: Can I take other medications or alcohol?
A: Avoid concurrent myelosuppressive drugs where possible and limit alcohol due to hepatic stress and tolerability concerns.
When To Call Your Team: fever (any temperature elevation), new bruising or bleeding, severe nausea/vomiting, sudden breathlessness or chest pain — these need urgent review.
Guidelines For Proper Use
What should pharmacists and prescribers cover when counselling patients?
Verify the indication and whether use is TGA‑aligned or off‑label and discuss fertility, contraception and the need for regular blood tests before and during therapy.
Explain infection precautions, advise on avoiding live vaccines and review all medicines for potential interactions with chlorambucil.
Handling guidance: treat chlorambucil as a cytotoxic agent — use gloves when handling tablets if splitting or crushing is unavoidable, and provide correct disposal instructions for unused tablets.
For telehealth and rural patients, arrange local pathology access and a clear escalation pathway to the nearest emergency department or oncology centre in case of febrile neutropaenia.
- Pharmacist Counselling Checklist: Indication, dose schedule, CBC monitoring plan, contraception/fertility counsel, drug interaction review, storage instructions.
- Storage: Store 20–25°C, protect from light and moisture; avoid exposure above 30°C during transport.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Sunshine Coast | Queensland | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Darwin | Northern Territory | 5–9 days |