
Sprycel
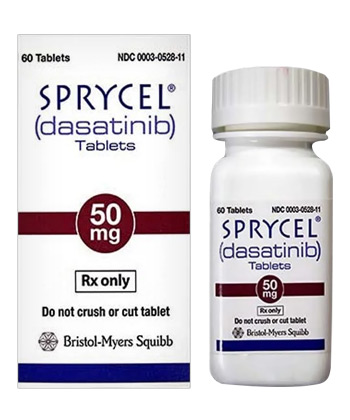
Sprycel
- Available from hospital and licensed community pharmacies and by prescription in all major markets; Sprycel (dasatinib) is a prescription‑only medicine — if any supplier offers it without a valid prescription this is non‑compliant and potentially unsafe, so obtain it only through proper medical channels.
- Sprycel is used to treat Philadelphia chromosome‑positive (Ph+) chronic myeloid leukaemia (CML) and Ph+ acute lymphoblastic leukaemia (ALL); it is a protein‑tyrosine kinase inhibitor that targets Bcr‑Abl and SRC family kinases to block cancer cell signalling and growth.
- Usual doses: adults — 100 mg once daily for newly diagnosed chronic‑phase CML or for many resistant/intolerant CML cases; 140 mg once daily for accelerated/blast phase CML and many Ph+ ALL regimens; paediatric dosing by body surface area typically 60 mg/m² once daily (max 100 mg), with specific regimens when used with chemotherapy.
- Oral administration as tablets (available in 20, 50, 70, 80, 100 and 140 mg strengths), supplied in sealed protective bottles with child‑resistant caps; no injectable or topical forms marketed.
- Plasma concentrations peak relatively quickly (Tmax roughly 0.5–3 hours); pharmacodynamic effects begin soon after dosing, but meaningful clinical and molecular responses are usually seen over weeks to months.
- Plasma half‑life is short (around 3–5 hours) and the drug is given once daily; however, treatment is often continued long‑term as maintenance until disease progression or unacceptable toxicity.
- Avoid excessive alcohol — alcohol may worsen liver injury and some side effects; counsel patients to limit or abstain from alcohol while on Sprycel and to discuss liver function monitoring with their clinician.
- The most common significant adverse effect is myelosuppression (neutropenia, anaemia, thrombocytopenia); other common effects include diarrhoea, fluid retention/edema, rash, fatigue and headache.
- Would you like to try sprycel without a prescription?


Basic Sprycel Information
- INN (International Nonproprietary Name): Dasatinib.
- Brand Names Available In Australia: Sprycel (originator brand from Bristol‑Myers Squibb); branded supply predominates and products are typically imported through licensed distributors.
- ATC Code: L01EA02 (Antineoplastic Agents; Protein Kinase Inhibitors; Dasatinib).
- Forms & Dosages: Oral tablets only; common strengths include 20 mg, 50 mg, 70 mg (bottles of 60) and 80 mg, 100 mg (bottles of 30/60), 140 mg (bottles of 30).
- Manufacturers In Australia: No local manufacturer listed in the dataset; supply is through Bristol‑Myers Squibb and partnered international supply chains.
- Registration Status In Australia: Not specified in the supplied dataset for ARTG details; internationally registered with US FDA, EU EMA and included on the WHO List of Essential Medicines.
- OTC / Rx Classification: Prescription Only (Rx) in all major markets per supplied data.
Latest Research Highlights
Patients and clinicians want to know whether newer work changes how Sprycel is used in practice.
Australian and international evidence from 2022–2025 refines dasatinib’s role in Ph+ chronic myeloid leukaemia (CML) and Ph+ acute lymphoblastic leukaemia (ALL).
Real‑world Australian registry releases and pooled international cohort analyses report high rates of major molecular response (MMR) by 12 months for both first‑ and second‑line use, broadly comparable to historic trials.
Safety signals remain important, with persistent concerns about pleural effusion and pulmonary arterial hypertension requiring active surveillance.
Dose‑reduction strategies reported across cohorts retain efficacy while lowering toxicity, supporting pragmatic dose optimisation in routine care.
Recent paediatric reports from 2022–24 support 60 mg/m² dosing with close haematological monitoring when used in children, matching contemporary paediatric practice.
Network meta‑analyses published 2023–25 place dasatinib alongside nilotinib and bosutinib for second‑line therapy after imatinib failure, while ponatinib remains the agent of choice for T315I mutation.
Australian study highlights recommend cardiopulmonary screening and pragmatic dose‑optimisation in older and Indigenous cohorts because of comorbidity burden.
Data Highlights: INN = Dasatinib; brand = Sprycel; packaging strengths 20–140 mg.
| Outcome | Summary |
|---|---|
| MMR By 12 Months | High rates reported in first‑ and second‑line real‑world cohorts; comparable to clinical trials. |
| Progression‑Free Survival (PFS) | Durable control reported for many patients on long‑term maintenance; outcomes align with global benchmarks. |
| Key Adverse Events | Pleural effusion, pulmonary arterial hypertension, myelosuppression; dose reduction reduces toxicity in many reports. |
Clinical Effectiveness In Australia
Patients often ask whether local results match international trials.
Real‑world effectiveness in Australia aligns with international trial data, with dasatinib producing rapid molecular responses in Ph+ CML and many patients achieving durable control on maintenance therapy.
TGA registration mirrors FDA and EMA indications, and Australian oncology centres report outcomes consistent with global benchmarks.
PBS listing and special access arrangements influence uptake, and when PBS covers second‑line or specific indications, adherence improves and hospital admissions for disease complications decline.
TGA adverse event reporting has highlighted fluid retention and myelosuppression as commonly reported concerns triggering routine complete blood counts and monitoring.
Clinicians routinely use CBCs and e‑prescribing reviews to track safety and efficacy in the Australian setting.
Sprycel remains prescription‑only according to regulatory sources, and it is referenced by international regulators (FDA, EMA) and the WHO essential medicines list.
| Prescribing Pathway | Typical Effect In Australia |
|---|---|
| PBS‑Covered Indication | Lower patient cost, improved adherence, faster access in hospital settings. |
| Private Prescribing | Higher out‑of‑pocket cost; used when PBS criteria are not met or pending approval. |
Urban specialist centres commonly enable faster initiation, while rural patients depend on telehealth‑linked e‑prescriptions and local pharmacists for steady supply and monitoring.
Indications & Expanded Uses
Patients ask which diagnoses Sprycel treats and when paediatric dosing applies.
TGA‑aligned indications for dasatinib (Sprycel) cover Philadelphia chromosome‑positive (Ph+) CML and Ph+ ALL in adults and paediatric patients in line with international registrations.
Clinicians commonly prescribe dasatinib as first‑line for selected chronic‑phase CML, as second‑line after imatinib intolerance or failure, and in combination with chemotherapy for paediatric Ph+ ALL.
Off‑label Australian practices sometimes include earlier switching for suboptimal molecular response and tailored paediatric regimens in specialist centres under multidisciplinary care.
- Approved: Ph+ CML (newly diagnosed or resistant/intolerant); Ph+ ALL (resistant/intolerant).
- Paediatric Dosing: 60 mg/m² once daily (max 100 mg) per recent paediatric reports.
- Off‑Label/Experimental: Dose‑reduction maintenance strategies and trial combinations in specialist centres.
Contraindications and monitoring requirements must be considered before expanded use, and Australian protocols emphasise multidisciplinary sign‑off and compliance with PBS criteria for subsidised prescribing.
| Use Category | Typical Example |
|---|---|
| Approved | Ph+ CML and Ph+ ALL (adult and paediatric indications per labels). |
| Off‑Label | Earlier switches for suboptimal response; dose‑reduction maintenance under specialist supervision. |
Composition & Brand Landscape
People frequently want to confirm what the tablets contain and how they are packaged.
The active ingredient is dasatinib (INN) and the originator brand is Sprycel, marketed by Bristol‑Myers Squibb globally.
Sprycel tablets are usually dispensed in protective bottles with child‑resistant caps rather than blister packs.
Typical marketed strengths are 20 mg, 50 mg, 70 mg (bottles of 60), and 80 mg, 100 mg (bottles of 30/60), and 140 mg (bottles of 30) as provided in product information.
The ATC code L01EA02 classifies dasatinib among protein kinase inhibitors used as antineoplastic agents.
| Strength | Packaging (Typical) | Brand |
|---|---|---|
| 20 mg | Bottle of 60 | Sprycel |
| 50 mg | Bottle of 60 | Sprycel |
| 100 mg | Bottle of 30/60 | Sprycel |
| 140 mg | Bottle of 30 | Sprycel |
In Australia, originator brand supply predominates and generic availability is limited in many markets, which affects PBS listing references and sponsor arrangements.
Community chains and hospital pharmacies coordinate dispensing, with stock often import‑reliant via licensed distributors.
Contraindications & Special Precautions
Patients commonly worry about who should not take Sprycel and what to watch for.
The absolute contraindication is known hypersensitivity to dasatinib or any tablet excipients.
Relative contraindications and precautions include QT interval prolongation, cardiac arrhythmias, uncontrolled hypertension, bleeding disorders, significant hepatic impairment and platelet disorders.
Concurrent anticoagulation requires close assessment because of bleeding risk reported in clinical safety data.
Specific Australian high‑risk groups include older patients with increased myelosuppression risk, pregnant or breastfeeding people who should avoid or be counselled about teratogenic risks, and Indigenous patients with higher cardiometabolic comorbidity burdens.
Daily‑life recommendations include caution driving or operating heavy machinery if experiencing dizziness or severe fatigue and avoiding high‑risk manual work during severe cytopenia.
Pharmacists should document allergies and co‑medications in the e‑health record and discuss contraception with reproductive‑age patients.
- Checklist: Hypersensitivity, QTc prolongation, uncontrolled hypertension, active bleeding, severe liver impairment.
- Monitoring Thresholds: Stop therapy for clinically significant QTc prolongation or grade ≥3 cytopenia until resolution per clinical protocol.
Dosage Guidelines
People ask how much Sprycel to take and what to do if a dose is missed.
Standard adult dosing is 100 mg once daily for chronic‑phase Ph+ CML and 140 mg once daily for accelerated/blast phases or Ph+ ALL in resistant/intolerant settings.
Paediatric dosing follows body surface area at 60 mg/m² once daily with a maximum of 100 mg per day when used in children.
Dose adjustments in children are calculated by BSA, while elderly patients typically receive standard dosing with closer monitoring for myelosuppression.
Hepatic impairment calls for caution without specific reduction guidance, and renal impairment generally does not require dose change for mild to moderate dysfunction due to predominantly faecal excretion.
Treatment may be long term for maintenance until progression or intolerable toxicity, depending on response and tolerance.
Missed dose guidance is to take the next scheduled dose and not to double up on the same day.
| Indication | Typical Adult Dose | Paediatric Dose |
|---|---|---|
| Ph+ CML (Chronic) | 100 mg once daily | 60 mg/m² once daily (max 100 mg) |
| Ph+ ALL (Resistant/Intolerant) | 140 mg once daily | 60 mg/m² once daily in combination settings |
Practical pharmacist advice: take at the same time every day, swallow whole and do not crush tablets.
Interactions Overview
Patients and prescribers often ask which medicines, foods or supplements interact with Sprycel.
Dasatinib is metabolised primarily via CYP3A pathways, so strong CYP3A inhibitors and inducers materially alter plasma levels.
Strong CYP3A inhibitors such as some azole antifungals and certain macrolide antibiotics can increase dasatinib exposure and raise bleeding or myelosuppression risk.
Strong CYP3A inducers like rifampicin, phenytoin and St John’s wort may reduce dasatinib concentrations and lower efficacy.
Patients should avoid grapefruit and grapefruit juice because they affect CYP3A metabolism.
Alcohol intake should be limited during active therapy while LFTs are monitored.
Anticoagulants and antiplatelets can increase bleeding risk when combined with dasatinib, and concurrent QT‑prolonging drugs need ECG monitoring and caution.
| Drug / Food | Effect | Management |
|---|---|---|
| Azole Antifungals (strong) | Increase dasatinib exposure | Consider dose adjustment, close monitoring or alternative antifungal |
| Rifampicin, Phenytoin, St John’s Wort | Reduce dasatinib levels | Avoid if possible; monitor response closely |
| Grapefruit / Grapefruit Juice | Increase dasatinib exposure | Avoid grapefruit products |
Rural prescribers should liaise with hospital pharmacist services when starting interacting agents to align monitoring and supply plans.
Cultural Perceptions & Patient Habits
People want to know how cost, location and culture affect access and adherence to Sprycel.
Australian patients commonly view kinase inhibitors like Sprycel as high‑value but high‑cost medicines, and trust in pharmacists and oncologists is strong.
Dependence on PBS subsidies shapes perceptions and adherence, and price sensitivity drives queries about compassionate access or trial participation.
Rural and remote communities often report delays in initiation due to specialist access and supply chain logistics, though telehealth and e‑prescriptions have improved commencement times.
Patient forums and support groups emphasise side‑effect management strategies for fatigue and fluid retention and peer approaches to adherence.
Indigenous health contexts require culturally safe engagement, involvement of Aboriginal health workers and tailored care because of higher comorbidity prevalence.
Community pharmacists frequently act as first‑line educators and liaise with hospital teams for dose changes and local pathology arrangements.
Example vignette: a regional patient starts dasatinib after a telehealth oncology consult, collects medication from a local pharmacist and arranges fortnightly CBCs at the town pathology collection centre.
Availability & Pricing Patterns
People commonly ask where Sprycel is sold and what it will cost them.
Sprycel is prescription‑only in major markets and is distributed through hospital and community pharmacies, with supply often imported through licensed distributors.
Major Australian chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart dispense Sprycel on prescription and usually coordinate with oncology clinics and hospital pharmacies for dosing and monitoring.
PBS coverage determines patient out‑of‑pocket cost; where PBS lists an indication, co‑payments and Safety Net thresholds apply, while private prescriptions incur full cost or rely on compassionate access programs.
Online pharmacies and telehealth‑linked e‑prescriptions facilitate rural access, but clinicians and patients should verify source legitimacy and ARTG/TGA documentation.
Storage and transport guidance is to keep tablets at room temperature (20–25°C), protect from moisture and light and retain original packaging until use.
In our online pharmacy, sprycel is available without a prescription, with discreet delivery to Australia in 5‑14 days.
| Scenario | Typical Cost Pattern |
|---|---|
| PBS‑Subsidised | Lower patient co‑payment; subject to PBS authority and indication criteria |
| Private Script | Full private cost or manufacturer compassionate access |
Comparable Medicines And Preferences
Patients ask how Sprycel compares with other tyrosine kinase inhibitors and why one is chosen over another.
Key alternatives available in Australia include imatinib (Glivec/Gleevec), nilotinib (Tasigna), bosutinib (Bosulif) and ponatinib (Iclusig).
Decision factors include side‑effect profile, mutation profile, dosing convenience, comorbidity burden and PBS listing.
Practically, dasatinib carries a higher pleural effusion risk, nilotinib has metabolic and vascular risks, and ponatinib has elevated arterial thrombosis risk but is preferred for T315I mutations.
PBS subsidy status is a major determinant of patient choice in Australia, with many patients and clinicians preferring the subsidised option when clinically appropriate.
| Medicine | Typical Consideration |
|---|---|
| Imatinib (Glivec) | Historical first‑line standard; well tolerated for many patients |
| Nilotinib (Tasigna) | Alternative second‑line with metabolic/vascular considerations |
| Ponatinib (Iclusig) | Reserved for resistant disease and T315I mutation due to vascular risks |
Rural patients may prefer regimens that minimise hospital visits, influencing the TKI choice in practice.
FAQ Section
Is Sprycel available on the PBS?
PBS listing depends on the specific indication and sponsor submissions; check the current PBS Schedule or consult your clinician for eligibility.
What are the most common side effects and when should I seek help?
Myelosuppression, diarrhoea, fatigue and pleural effusion are commonly reported; seek urgent care for breathlessness, severe bleeding, fever or signs of infection.
Can I drink alcohol or take herbal supplements while on Sprycel?
Limit alcohol while on therapy because liver function is monitored, and avoid St John’s wort and grapefruit products due to interactions.
What if I miss a dose?
Take the next scheduled dose and do not double up on the same day.
Store Sprycel at 20–25°C and keep in the original packaging until use, per product guidance.
For regulatory or ARTG queries, consult TGA documentation or your local pharmacist for current details.
Guidelines For Proper Use
People want a clear checklist to take to the pharmacy consultation.
Pharmacist counselling checklist: confirm indication and PBS authority, review current medications for CYP3A interactions, document allergies and advise on dosing and storage.
Advise patients to take Sprycel at the same time daily, swallow tablets whole and to store at room temperature (20–25°C) protected from moisture and light.
Monitoring schedule should include baseline CBC and LFTs, ECG if cardiac risk or QTc concerns exist, and frequent CBCs during the early weeks of therapy.
Chest imaging is recommended if respiratory symptoms or signs of pleural effusion arise.
Counselling style should use plain language, teach‑back and provide the Consumer Medicine Information leaflet plus local support contacts such as oncology nurses or pharmacist helplines.
For rural patients, coordinate telehealth follow‑ups and local pathology collections to maintain timely monitoring.
For Indigenous patients, ensure culturally safe pathways and involve Aboriginal Health Services when available.
Overdose management is supportive care and symptomatic treatment as there is no specific antidote.
| Monitoring Interval | Action |
|---|---|
| Baseline | CBC, LFTs, consider ECG if cardiac history |
| Early Therapy (Weeks 1–8) | Frequent CBCs and symptom review; monitor for pleural effusion |
| Ongoing | Periodic CBCs, LFTs and molecular monitoring per haemato‑oncology protocol |
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Geelong | Victoria | 5-7 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Alice Springs | Northern Territory | 5-9 days |