
Rheumatrex
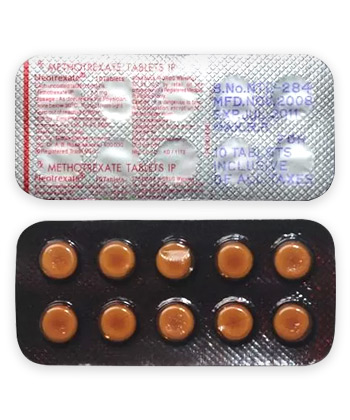
Rheumatrex
- In our pharmacy, you can buy rheumatrex without a prescription, with delivery across Australia and discreet packaging; note that methotrexate is officially prescription-only in most countries and should be used under medical supervision.
- Rheumatrex (methotrexate) is used for rheumatoid arthritis, juvenile idiopathic arthritis, psoriasis and certain cancers; it is an antimetabolite and folic acid analogue that inhibits dihydrofolate reductase, reducing DNA synthesis and exerting immunomodulatory effects.
- Usual dosages: for rheumatoid arthritis 7.5–15 mg once weekly (oral or subcutaneous); psoriasis 10–25 mg once weekly; juvenile idiopathic arthritis ~10–15 mg/m² once weekly; oncology dosing varies widely by protocol.
- Available forms of administration: oral tablets and oral solution, subcutaneous pre-filled syringes/auto-injectors, and injectable vials for intravenous or intramuscular use.
- Onset time: clinical improvement in inflammatory conditions often begins within 3–6 weeks, with fuller benefit seen by about 12 weeks.
- Duration of action: effects are maintained with regular (usually once-weekly) dosing and long-term maintenance therapy; therapeutic benefit persists while treatment continues.
- Alcohol warning: avoid alcohol—concurrent alcohol increases risk of liver toxicity and is contraindicated in alcohol dependence or chronic liver disease.
- The most common side effect is nausea; other frequent adverse effects include mouth sores, diarrhoea, mild cytopenias, elevated liver enzymes, rash and fatigue; folic acid supplementation is commonly recommended to reduce some side effects.
- Would you like to try rheumatrex without a prescription?


Basic Rheumatrex Information
- INN (International Nonproprietary Name): Methotrexate.
- Brand Names Available In Australia: not specified.
- ATC Code: L01BA01 — Antineoplastic and immunomodulating agents, antimetabolites, folic acid analogues.
- Forms & Dosages: Tablets 2.5 mg, 5 mg, 7.5 mg, 10 mg; Oral solution 2 mg/ml (e.g., Jylamvo in some markets); Pre‑filled syringes/injectors 7.5–30 mg; Vials for injection 25 mg/ml, 50 mg/2 ml, larger oncology vials.
- Manufacturers In Australia: not specified.
- Registration Status In Australia: not specified.
- OTC / Rx Classification: Prescription‑only (Rx) globally.
Latest Research Highlights (Australia + International, 2022–Mid‑2024)
Clinicians keep asking whether methotrexate performance has changed in recent years.
Recent literature continues to consolidate methotrexate as a first‑line DMARD for rheumatoid arthritis and psoriatic disease, with data through mid‑2024 supporting low‑dose once‑weekly regimens.
International randomised trials and registry data continue to show that subcutaneous dosing gives higher and more consistent bioavailability than oral tablets, especially above 15 mg per week.
Co‑prescription of folic or folinic acid consistently reduces gastrointestinal and haematologic adverse events and is standard practice in rheumatology publications.
Australian cohort analyses and hospital audits from state registries between 2020 and 2024 reported effectiveness consistent with international RCTs but noted under‑monitoring in some rural settings and slower escalation to subcutaneous or injectable forms.
Safety signals emphasise absolute teratogenicity, increased risk with renal impairment, and interactions with other renally cleared drugs.
Baseline and ongoing monitoring using CBC, LFTs and creatinine reduces the risk of severe toxicity when adhered to, according to contemporary guidance.
| Study Type | Outcome | n | Follow‑Up | Key Safety Signal |
|---|---|---|---|---|
| International RCTs | Consistent efficacy for RA and psoriatic disease. | not specified | 6–12 weeks to early response; longer for full effect up to 12 weeks. | Teratogenicity; hepatotoxicity; marrow suppression. |
| Registry / Cohort (Australia) | Real‑world effectiveness similar to RCTs; slower route escalation in rural areas. | not specified | 6–24 months in audits and registry reports. | Under‑monitoring in rural settings; interactions with renal impairment. |
Clinical Effectiveness In Australia (PBS And TGA Contexts)
Patients commonly ask whether methotrexate is subsidised and effective in everyday practice.
In Australia, methotrexate is a cornerstone DMARD used widely in primary and specialist care and is typically subsidised by the PBS for approved rheumatology indications, which helps keep treatment affordable.
The Therapeutic Goods Administration registers methotrexate formulations for use under prescription standards consistent with international practice.
Real‑world PBS dispensing and rheumatology clinic data show reductions in disease activity scores such as DAS28 within 6–12 weeks after starting typical low‑dose, once‑weekly regimens.
TGA adverse‑event reporting highlights hepatotoxicity and marrow suppression as the most clinically important risks, though they are uncommon with recommended monitoring.
Australian prescribers commonly start oral methotrexate at 7.5–15 mg once weekly and switch to subcutaneous pre‑filled syringes if response or tolerability requires it.
Available forms include methotrexate tablets in 2.5–10 mg strengths and subcutaneous injectors in ranges up to 30 mg, in line with international supplies such as Jylamvo for oral solution and Metoject or similar for injectables.
Barriers in rural and remote Australia include variable pharmacy stock, limited local pathology access, and telehealth prescribing constraints that can delay dose escalation or monitoring.
When available and used correctly, PBS‑supported methotrexate provides effective, affordable disease control for many patients with RA and psoriasis.
Indications And Expanded Uses (TGA‑Approved Vs Off‑Label)
People often want to know what methotrexate is approved for and what it may be used for off‑label.
TGA‑aligned indications mirror global approvals and include rheumatoid arthritis, juvenile idiopathic arthritis, severe psoriasis, and certain oncology protocols.
Off‑label uses in Australia under specialist supervision include medical treatment of ectopic pregnancy and low‑dose steroid‑sparing therapy in dermatology and some forms of vasculitis.
Oncology dosing differs substantially from rheumatology dosing, with oncology protocols ranging from low‑dose regimens of about 10–30 mg/m² weekly to high‑dose specialist schedules.
Off‑label prescribing requires informed consent, clear documentation, and any required PBS authority approvals if subsidy is sought.
Contraception counselling and pregnancy testing are mandatory before initiation because methotrexate is teratogenic and contraindicated in pregnancy and breastfeeding.
- TGA‑Approved Indications: Rheumatoid arthritis; Juvenile idiopathic arthritis; Severe psoriasis; Selected oncology indications.
- Common Off‑Label Uses: Ectopic pregnancy management (specialist); Low‑dose steroid‑sparing use in dermatology; Selected vasculitis regimens (specialist).
- Definition: "Low‑dose" rheumatology typically means once‑weekly doses in the 7.5–25 mg range, while "high‑dose" oncology refers to weight or surface area based intensive protocols.
Composition And Brand Landscape (Active Ingredient, Packaging)
Patients ask which brands exist and whether tablets and injectables are interchangeable.
The active ingredient is methotrexate sodium, marketed internationally under many brands including Rheumatrex, Trexall, Metoject, Rasuvo and others, with multiple generics available.
Common packaging and forms include tablets (2.5 mg, 5 mg, 7.5 mg, 10 mg), oral solution 2 mg/ml such as Jylamvo in some markets, pre‑filled syringes and auto‑injectors from 7.5 mg to 30 mg, and injectable vials for oncology use.
Global suppliers named in registration lists include Pfizer, Teva, Sandoz, Ebewe and others, while many generics are manufactured in India and Europe.
| Brand / Generic | Form | Typical Dose | PBS Listing Note |
|---|---|---|---|
| Rheumatrex, Trexall | Tablets | 2.5–10 mg | Often available as generics; PBS subsidy for approved indications. |
| Jylamvo | Oral Solution | 2 mg/ml | Market availability varies by country; not all markets carry the oral solution. |
| Metoject, Rasuvo | Pre‑filled Syringes / Injectors | 7.5–30 mg | Injectable forms may be imported and stock varies; PBS tends to favour generics. |
| Methotrexat Ebewe | Vials / Oncology Packs | 50 mg/2 ml, larger vials | Used in oncology; hospital procurement or specialist supply. |
Important: oral and injectable formulations are not interchangeable mg:mg without prescriber direction.
Contraindications And Special Precautions (Including Australian High‑Risk Groups)
Safety is the top concern for most patients starting methotrexate.
Absolute contraindications include pregnancy and breastfeeding, severe hepatic or renal impairment, active alcoholism or chronic liver disease, bone marrow hypoplasia, and hypersensitivity.
Relative contraindications and groups needing extra caution include people with mild to moderate liver or kidney dysfunction, active infections, peptic ulcer disease, elderly patients, those with prior hepatitis B or C, and people with diabetes.
In Australia, clinicians should also consider access and follow‑up barriers for Indigenous communities and arrange culturally safe care and involvement of community‑controlled health services where appropriate.
Practical lifestyle advice includes avoiding conception while on treatment, limiting or abstaining from alcohol because of additive hepatotoxic risk, and delaying live vaccines while on therapy.
Workplace exposure to infections should be managed sensibly and patients should report symptoms such as fever, severe mouth ulcers, unexplained bruising or shortness of breath immediately.
Checklist For Pre‑Treatment Assessment:
- Confirm negative pregnancy test and discuss contraception options.
- Baseline CBC, LFTs, renal function, and hepatitis B/C screening.
- Assess alcohol use, liver disease, and drug interactions.
- Document hypersensitivity history and current infections.
Dosage Guidelines And Monitoring (Australian Practice)
People frequently ask how methotrexate is dosed and how often they need blood tests.
Usual starting regimens in Australian rheumatology are 7.5–15 mg once weekly by mouth or subcutaneously for rheumatoid arthritis.
Psoriasis dosing commonly ranges from 10–25 mg once weekly depending on severity and specialist guidance.
Juvenile dosing is calculated by body surface area, typically about 10–15 mg/m² once weekly.
Route choice is often to start oral for convenience and switch to subcutaneous if response is incomplete or if gastrointestinal intolerance occurs.
Lower starting doses are advised for elderly patients or those with renal impairment, and methotrexate is contraindicated in severe hepatic or renal failure.
Baseline investigations should include CBC, LFTs, creatinine, hepatitis B and C screening, and a pregnancy test where relevant.
Once stable, the common monitoring cadence is CBC, LFTs and creatinine every 1–3 months.
Folic acid supplementation is standard to reduce gastrointestinal and haematologic side effects, with typical regimens including 5–7 mg weekly or 1 mg daily depending on prescriber preference.
| Indication | Typical Starting Dose | Route | Monitoring Cadence |
|---|---|---|---|
| Rheumatoid Arthritis | 7.5–15 mg weekly | Oral or Subcutaneous | Baseline then every 1–3 months once stable |
| Psoriasis | 10–25 mg weekly | Oral or Subcutaneous | Baseline then every 1–3 months once stable |
| Juvenile Idiopathic Arthritis | ≈10–15 mg/m² weekly | Oral or Subcutaneous | Specialist monitoring; baseline tests and frequent reviews |
Interactions Overview (Drugs, Food, Alcohol)
Many patients want a clear list of drugs and substances to avoid with methotrexate.
Important pharmaceutical interactions include drugs that reduce renal clearance or are nephrotoxic, which can raise methotrexate levels and toxicity.
Examples include certain high‑dose NSAIDs, some penicillins, and trimethoprim/sulfamethoxazole, which are reported to increase risk in clinical practice.
Proton pump inhibitors have been associated in some reports with altered methotrexate clearance and should be reviewed with prescribers for higher methotrexate doses.
Live vaccines are contraindicated while on methotrexate therapy due to reduced immune response and infection risk.
Alcohol potentiates hepatotoxicity and patients should be advised to limit or avoid alcohol during treatment.
Coffee has no strong evidence of interaction with methotrexate, but moderation is reasonable.
In aged care or polypharmacy situations, clinicians should check My Health Record and e‑scripts to identify interacting medicines and reduce risk.
- High Severity Interactions: Trimethoprim/sulfamethoxazole, high‑dose NSAIDs, some penicillins — review and consider alternative agents.
- Moderate Severity: Proton pump inhibitors — monitor and discuss with prescriber if on high methotrexate doses.
- Substance Advice: Alcohol — avoid or strictly limit; folic acid — use as protective supplementation.
Cultural Perceptions And Patient Habits (Australian Patient Experience)
Patients often say they are grateful for disease control but worried about safety and fertility.
Methotrexate is commonly perceived as effective, but many people associate it with chemotherapy and fear pregnancy risks.
Online forums and consumer groups show heavy reliance on pharmacists from major chains and local chemists for practical information and price comparisons.
PBS subsidy reduces cost concerns for many patients, though urban/rural disparities in access to injectables and pathology services persist.
Rural patients report longer travel for blood tests, variable local stock of injectables and more reliance on telehealth for prescriptions and follow‑up.
Indigenous communities emphasise culturally safe, community‑based education and support and prefer involvement of community health services in ongoing monitoring.
Price sensitivity leads some patients to compare pharmacy chains and use online scripts or telehealth services to find stock or lower co‑payments.
Availability And Pricing Patterns In Australia
People ask where to buy methotrexate and how much it will cost out of pocket.
Methotrexate tablets and generics are widely available through major retail pharmacy chains and community pharmacies across Australia.
Subcutaneous injectables are available but stock can be more limited locally and may need to be ordered or supplied through hospitals and specialist services.
Online pharmacies and telehealth services can provide e‑prescriptions and courier medications to remote patients, which helps with continuity of care.
PBS typically subsidises methotrexate for approved indications, with co‑payments varying by concession status and specific PBS listings.
Private or imported brands can vary in price and may be cheaper or more expensive depending on promotions and pharmacy pricing.
In our online pharmacy, rheumatrex is available without a prescription, with discreet delivery to Australia in 5–14 days.
| Item | Typical PBS Co‑Payment | Private Price Range Per Month | Availability Notes |
|---|---|---|---|
| Methotrexate Tablets (generic) | not specified | not specified | Widely stocked by major chains and community pharmacies. |
| Subcutaneous Injectors (pre‑filled) | not specified | not specified | May require ordering; stock variable between chains. |
Prescribers and pharmacists should remind patients that oral and injectable forms are not interchangeable by dose without clinical instruction.
Comparable Medicines And Patient Preferences (Alternatives In Australia)
Patients sometimes ask what to try if methotrexate is not suitable.
Other conventional DMARDs in Australian practice include leflunomide, sulfasalazine and hydroxychloroquine, which may be used alone or in combination.
Leflunomide is an oral once‑daily option but carries hepatic risk and requires its own monitoring plan.
Sulfasalazine and hydroxychloroquine are commonly used as part of combination or "triple" therapy where appropriate.
Biologic therapies such as adalimumab and etanercept are PBS‑restricted and often used when methotrexate is insufficient or not tolerated, and sometimes combined with methotrexate for optimal response.
Patient preferences usually centre on desire for oral dosing, concern about injections, cost, and fertility implications.
For many patients, switching from oral tablets to subcutaneous pre‑filled syringes improves tolerance and adherence.
- Pros Of Methotrexate: Proven efficacy, low weekly dosing, PBS subsidy for approved indications.
- Cons Of Methotrexate: Requires monitoring, teratogenicity, lifestyle restrictions (alcohol, vaccines).
- Alternatives: Leflunomide (oral), sulfasalazine, hydroxychloroquine, biologics (PBS‑restricted).
FAQ — Common Patient Questions
Q: Can I drink alcohol on methotrexate?
A: Best practice is to minimise or avoid alcohol because of additive hepatotoxicity risk, and any intake should be discussed with the prescriber in the context of baseline LFTs.
Q: What if I miss my weekly dose?
A: Do not double dose; take the missed dose if remembered within 24 hours, otherwise skip and continue the usual weekly schedule, and seek urgent care for any suspected overdose.
Q: Do I need contraception?
A: Yes, methotrexate is teratogenic and people with reproductive potential should use reliable contraception during treatment and for the interval advised by their specialist after stopping.
Q: Why am I prescribed folic acid?
A: Folic acid reduces gastrointestinal symptoms, mouth sores and haematologic toxicity and is routinely given either daily or as a weekly supplement depending on prescriber preference.
Guidelines For Proper Use And Pharmacist Counselling (PBS And National Advice)
Pharmacists play a key role in safe methotrexate use through clear, culturally sensitive counselling.
Before supply, confirm the weekly dosing day and emphasise that methotrexate is taken once weekly, not daily.
Discuss teratogenic risks and confirm contraception or pregnancy test status as required by the prescriber.
Recommend folic acid supplementation and explain the rationale and typical dosing options.
Review the patient's medication list for interactions and check My Health Record and e‑scripts for polypharmacy risks, especially in aged care.
Arrange or remind patients about baseline and ongoing blood tests, and help with pathology scheduling for rural patients where necessary.
Document counselling and provide a safety‑net plan for urgent symptoms such as fever, severe mucositis, unexplained bruising or respiratory symptoms.
- Pre‑Start Checks: Pregnancy test, CBC, LFTs, creatinine, hepatitis screening, medication review.
- Counselling Points: Weekly dosing, folic acid, alcohol restriction, vaccine advice, when to seek urgent care.
- Monitoring Timetable: Baseline tests, then CBC/LFT/creatinine every 1–3 months once stable per PBS and RACGP expectations.
Delivery Across Australia
| City | Region | Delivery time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Townsville | Queensland | 5–9 days |