
Vfend
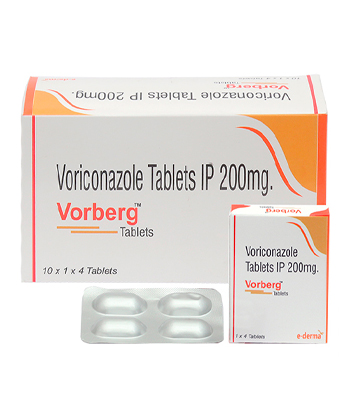
Vfend
- In our pharmacy, you can buy vfend without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Vfend (metformin) is used primarily for the treatment of type 2 diabetes and off‑label for polycystic ovary syndrome (PCOS). It is a biguanide that lowers blood glucose mainly by reducing hepatic gluconeogenesis, increasing peripheral insulin sensitivity and glucose uptake, and decreasing intestinal glucose absorption.
- The usual dose for adults (immediate‑release) starts at 500 mg once or twice daily with food, titrating up; typical maintenance is 1500–2000 mg/day (divided) and the maximum commonly used is 2000–2550 mg/day (divided). For extended‑release formulations, 500–1000 mg once daily (evening) is common, up to about 2000 mg/day. In PCOS, 500 mg 1–3 times daily is often used (up to ~2000 mg/day). Children ≥10 years: start 500 mg 1–2 times daily; max ~2000 mg/day, divided.
- Oral administration: tablets (immediate‑release and extended‑release) and oral solution/syrup (e.g. 500 mg/5 mL) where needed for paediatric or elderly patients.
- Onset: plasma levels peak in ~1–3 hours for immediate‑release and later (around 4–8 hours) for extended‑release; blood‑glucose lowering effects are often detectable within 48–72 hours, with full glycaemic benefit over days to weeks.
- Duration of action: immediate‑release effects typically persist ~8–12 hours (requiring divided dosing), while extended‑release formulations provide sustained effect up to 24 hours with once‑daily dosing.
- Alcohol warning: avoid excessive alcohol consumption — alcohol increases the risk of lactic acidosis and can worsen metformin‑related metabolic risks; chronic or binge drinking is a contraindication to use without close medical review.
- The most common side effect is gastrointestinal upset (nausea, abdominal discomfort, diarrhoea and flatulence); long‑term use can also be associated with vitamin B12 deficiency.
- Would you like to try vfend without a prescription?


Basic Vfend Information
- INN (International Nonproprietary Name): Metformin.
- Brand Names Available In Australia: not specified.
- ATC Code: A10BA02 — Biguanides subgroup; blood glucose‑lowering drugs (excluding insulins) for diabetes.
- Forms & Dosages: Tablets (immediate‑release) 250 mg, 500 mg, 850 mg, 1000 mg; tablets (extended‑release) 500 mg, 750 mg, 1000 mg; oral solution 500 mg/5 mL.
- Manufacturers In Australia: not specified.
- Registration Status In Australia: not specified.
- OTC / Rx Classification: Prescription‑only (Rx) in all markets according to supplied data.
Latest Research Highlights
Clinicians ask whether voriconazole remains the best option for invasive aspergillosis and complex mould infections.
Recent studies from 2022–2025 reinforce voriconazole (Vfend) as first‑line therapy for invasive aspergillosis and as an important salvage option for certain mould infections.
Therapeutic drug monitoring (TDM) is repeatedly linked to reduced toxicity and improved clinical response in multiple cohorts.
CYP2C19 genotype‑guided dosing shows reduced adverse events in populations with higher poor‑metaboliser prevalence, which is relevant for East Asian ancestry groups in Australia.
Australian hospital cohorts report lower 30‑ and 90‑day mortality when voriconazole is started early for proven invasive disease.
Emerging environmental azole resistance in Aspergillus has been described and may reduce treatment success in some regions.
Safety signals that persist include hepatotoxicity, transient visual disturbances and phototoxic skin reactions with a long‑term risk of squamous cell carcinoma noted in reporting.
| Study | Country | N | Indication | Outcome | Key Safety |
|---|---|---|---|---|---|
| TDM Meta‑analysis | International | Not specified | Invasive Aspergillosis | TDM Associated With Reduced Toxicity And Improved Efficacy | Hepatotoxicity, Visual Disturbances |
| CYP2C19 Genotype Study | East Asia / International | Not specified | Voriconazole Dosing Safety | Genotype‑Guided Dosing Reduced Adverse Events | Variable Drug Levels, Neuropsychiatric Effects |
| Australian Hospital Cohort Audits | Australia | Not specified | Proven Invasive Fungal Disease | Early Targeted Voriconazole Linked To Reduced 30/90‑Day Mortality | Hepatic Events, Visual Symptoms |
| Environmental Azole Resistance Reports | International | Not specified | Aspergillus From Environment | Rising Azole Resistance May Affect Clinical Success | Treatment Failure |
Clinical Effectiveness In Australia
Patients and prescribers want clear data on outcomes in local practice.
Australian tertiary centre audits and PBS/TGA pharmacovigilance note strong clinical effectiveness of voriconazole for invasive aspergillosis, chronic pulmonary aspergillosis and invasive mould disease in immunocompromised patients.
When started promptly for invasive aspergillosis, clinical response rates in hospital datasets range from about 50–70 percent.
Switching earlier from amphotericin to voriconazole often improves tolerability and reduces infusion‑related toxicity in many cases.
TGA adverse event reports commonly list hepatotoxicity and visual or neurological adverse events as reasons for dose adjustment or cessation.
In PBS‑funded settings, voriconazole is typically hospital‑initiated and continued outpatient under authority scripts when required.
Mortality and readmission metrics improve when TDM and specialist infectious diseases or clinical pharmacology input are used.
- Treatment response: ≈50–70% for invasive aspergillosis when started early.
- Rates of hepatotoxicity: commonly reported and a frequent cause for dose change.
- Rates of visual disturbances: common early, usually transient.
- TDM impact: associated with fewer adverse events and better target attainment.
Many Australian clinicians combine TDM with regular hepatic panels and use state pathology services for timely trough levels.
Indications And Expanded Uses
Patients often ask what conditions voriconazole is actually used for under the TGA framework.
TGA‑relevant, evidence‑based indications centre on invasive aspergillosis and serious invasive fungal infections caused by susceptible yeasts and moulds.
In Australia voriconazole is routinely used for invasive pulmonary or disseminated aspergillosis as a first‑line agent.
It is also used as an alternative for severe Candida infections in certain non‑neutropenic cases and as salvage therapy for multi‑drug resistant moulds.
Chronic pulmonary aspergillosis is another common indication for prolonged oral therapy when alternatives are unsuitable.
Off‑label but widely practiced uses include prophylaxis in high‑risk haematology and transplant patients following institution‑driven protocols.
Use is usually restricted by specialist initiation and PBS authority criteria when subsidy applies.
- TGA‑Approved Indications: Invasive aspergillosis and serious invasive fungal infections caused by susceptible organisms.
- Common Off‑Label Scenarios: Prophylaxis in high‑risk patients; prolonged oral therapy for chronic pulmonary aspergillosis.
- Specialist Referral Triggers: Suspected invasive mould infection, need for long‑term azole therapy, complex drug interactions or organ impairment.
Composition And Brand Landscape
Clinicians and pharmacy staff need to know formulations and supply channels.
The active ingredient is voriconazole, an azole antifungal agent.
Vfend formulations available internationally include tablets (commonly 50 mg and 200 mg), oral suspension (typical concentration around 40 mg/mL) and an intravenous concentrate for infusion with varying vial strengths.
Packaging for hospitals commonly includes IV vials and blister packs for tablets, with oral suspension used for paediatric or nasogastric administration.
Pfizer markets the branded Vfend product globally, and generics exist in some markets though brand presence remains strong in many hospitals.
| Form | Strengths | Typical Australian Supply Channel |
|---|---|---|
| Tablets | 50 mg, 200 mg | Community Pharmacy / Hospital Outpatient |
| Oral Suspension | Approx. 40 mg/mL | Community Pharmacy For Paediatric/NG Use |
| Intravenous Concentrate | Vial Strengths Vary | Hospital Supply (IV Therapy) |
Note that PBS listings for systemic antifungals are often authority‑restricted and IV supply is dominated by hospital formularies.
Contraindications And Special Precautions
Patients commonly ask whether liver disease, pregnancy or kidney problems change how voriconazole is used.
Absolute contraindication is known hypersensitivity to voriconazole.
Important precautions include hepatic impairment where dose reduction or avoidance in severe dysfunction is recommended.
Pregnancy carries animal teratogenicity signals, so voriconazole is used only when benefits justify potential risks.
Renal impairment is relevant for IV use because the SBECD vehicle can accumulate in severe renal dysfunction, making oral dosing preferable if eGFR is low.
Special Australian priorities are the elderly with polypharmacy and patients in remote or Indigenous communities who may have access and comorbidity challenges.
Patients must be warned about visual disturbances and phototoxic skin reactions, and advised to avoid hazardous tasks until effects are known.
Monitoring before and during treatment should include baseline liver function tests, repeat LFTs, an ECG if QT prolongation risk exists, and TDM where available.
- Screening Checklist Before Initiation: Current medicines, baseline LFTs, renal function, pregnancy status, QT risk.
- High‑Risk Groups: Severe hepatic dysfunction, pregnant or breastfeeding patients, severe renal impairment for IV use.
Dosage Guidelines
One of the first questions is what the typical dosing looks like for adults and children.
Typical adult oral dosing starts with a loading approach of 400 mg every 12 hours for two doses, or an IV loading dose of roughly 6 mg/kg every 12 hours for two doses when IV is required.
Maintenance adult dosing is commonly 200 mg orally every 12 hours or an IV maintenance dose around 3–4 mg/kg every 12 hours.
Specialist dosing is recommended for paediatric patients and those at extremes of weight because weight‑based regimens vary significantly.
In moderate hepatic impairment maintenance doses are typically reduced, for example by halving the maintenance dose, and severe hepatic dysfunction may contraindicate use.
For renal impairment the oral route is preferred when eGFR is reduced because the IV vehicle SBECD can accumulate.
TDM aims for trough concentrations approximately 1–5.5 mg/L, though lab targets vary between services.
| Scenario | Loading | Maintenance | TDM Target |
|---|---|---|---|
| Adult Oral | 400 mg PO q12h × 2 | 200 mg PO q12h | ~1–5.5 mg/L (varies) |
| Adult IV | 6 mg/kg IV q12h × 2 | 3–4 mg/kg IV q12h | ~1–5.5 mg/L (varies) |
| Hepatic Impairment | Use Specialist Advice | Reduce Maintenance (eg halve) | Frequent TDM Recommended |
For long treatment courses review the need for therapy every 4–6 weeks and monitor LFTs and patient quality of life.
Interactions Overview
Patients frequently ask whether voriconazole plays well with their other medicines, such as statins or antiretrovirals.
Voriconazole has extensive interactions mediated by CYP2C19, CYP3A4 and CYP2C9 pathways.
Contraindicated medicines include strong CYP inducers such as rifampicin, carbamazepine and St John’s wort because they markedly reduce voriconazole concentrations.
Certain drugs have levels increased by voriconazole and can reach dangerous concentrations; examples include some statins and immunosuppressants like sirolimus.
Antiretrovirals and some oncology agents require specialist review before co‑administration because management is complex.
Food interactions are practical: high‑fat meals can reduce voriconazole Cmax, so advise oral dosing on an empty stomach if practicable.
Alcohol does not have a direct pharmacokinetic interaction but will increase hepatic risk and should be minimised.
| Category | Examples | Recommendation |
|---|---|---|
| Contraindicated | Rifampicin, Carbamazepine, St John’s Wort | Do Not Co‑administer |
| Use With Caution | Sirolimus, Some Statins, Certain Benzodiazepines | Dose Adjustment And Close Monitoring |
| Monitor/TDM | Antiretrovirals, Oncology Agents | Specialist Review, TDM If Needed |
Pharmacists in Australia are a key safety checkpoint to check authority scripts and liaise with specialists on interaction management.
Cultural Perceptions And Patient Habits
Patients often bring concerns about side effects, cost and access, particularly in rural areas.
Common worries include hallucinations, vision changes and liver toxicity when taking vfend.
Price and PBS subsidy status strongly influence acceptability and adherence for many patients.
Urban tertiary centres typically have ready access to infectious diseases specialists and TDM services.
Rural and remote patients, including many Indigenous Australians, face access delays and rely on telehealth or hospital retrieval for IV therapy.
Culturally competent counselling means explaining risks and benefits in simple terms and involving families, local health workers or community liaison staff where appropriate.
Many patients prefer oral therapy to avoid hospital admission, and cost expectations shaped by PBS experience influence decisions.
- Patient Concerns: Visual effects, neuropsychiatric symptoms, hepatic monitoring, cost.
- Rural Access Barriers: Delayed TDM turnaround, need for hospital transfer for IV dosing.
- Telehealth Pathways: Specialist review and pathology arrangements can enable outpatient follow‑up.
Community pharmacists are trusted sources for clarifying confusion between systemic antifungals and topical OTC products.
Availability And Pricing Patterns
Patients and clinicians ask where to get Vfend and whether PBS will cover it.
Vfend is typically stocked in hospitals and major community pharmacies by prescription.
The IV formulation is hospital‑limited while oral tablets and suspension may be dispensed by community pharmacies but are often authority‑restricted on the PBS for specific indications.
When not subsidised, out‑of‑pocket costs can be substantial and vary between suppliers.
Major pharmacy chains may hold oral stock for prescription dispensing but PBS authority rules must be checked before dispensing.
Online pharmacies can dispense with a valid e‑prescription and telehealth script if authority requirements are met.
Patients in remote areas may require hospital transfer for IV therapy, which affects continuity and cost.
| Supply Channel | Formulation | PBS Status | Typical Private Cost (Estimate) |
|---|---|---|---|
| Hospital | IV, Tablets | Often Hospital Supply / Authority | Hospital‑funded |
| Community Pharmacy | Tablets, Suspension | Authority‑Restricted On PBS For Some Indications | Variable, Can Be Substantial If Unsubsidised |
| Online Pharmacy | Tablets, Suspension | Dispensed With Valid Script And Authority | Variable; delivery adds cost |
Pharmacists should check PBS authority requirements and consider patient assistance or hospital outpatient supply to reduce cost barriers.
In our online pharmacy, vfend is available without a prescription, with discreet delivery to Australia in 5-14 days.
Comparable Medicines And Preferences
Clinicians decide between alternatives based on pathogen, site, interactions and organ function.
Key alternatives include posaconazole for prophylaxis and salvage therapy, itraconazole for some chronic pulmonary disease, isavuconazole as a newer broad‑spectrum option, liposomal amphotericin B for severe disease and echinocandins for Candida.
Choice depends on susceptibility testing, oral bioavailability, drug–drug interactions, hepatic and renal safety and cost or PBS access.
- Posaconazole: Good for prophylaxis and salvage; absorption considerations apply.
- Isavuconazole: Fewer visual side effects and less QT risk but PBS access may be limited.
- Liposomal Amphotericin B: Effective for severe disease but IV only and higher toxicity profile.
Hospital formularies and infectious disease teams usually guide final selection in Australia and outpatient maintenance is influenced by PBS subsidy.
Frequently Asked Questions
Patients commonly ask straightforward practical questions that can be answered quickly at dispensing.
Q: Will Vfend affect my vision?
A: Transient visual disturbances such as blurring, colour changes or photophobia are common early in treatment and are usually reversible.
Q: Do I need blood tests?
A: Baseline and periodic liver function tests and therapeutic drug monitoring (trough levels) are recommended, with frequency guided by the specialist.
Q: Can I take Vfend with other medicines like statins?
A: Many interactions exist and some medicines are contraindicated; always provide a full medication list to your prescriber or pharmacist.
Q: Is Vfend safe in pregnancy or breastfeeding?
A: Voriconazole is generally avoided in pregnancy unless the expected benefit outweighs potential risk; discuss with your specialist.
Community pharmacists can triage queries but must liaise with prescribers for authority‑restricted treatments or complex interaction issues.
Guidelines For Proper Use
Pharmacist counselling and monitoring reduce harm and improve adherence.
Confirm indication and that a specialist initiated therapy before dispensing authority‑restricted voriconazole.
Advise patients to take oral doses on an empty stomach where practicable to reduce variability in absorption.
Warn about visual and neuropsychiatric effects and advise patients not to drive until they know how the medicine affects them.
Counsel on photosensitivity and the need for sun protection, and instruct patients to report new or changing skin lesions promptly.
Monitoring Schedule: baseline LFTs and renal function, ECG if QT risk, and TDM trough level after steady state (typically 4–7 days) or after interacting drug changes.
Storage Advice: store tablets and suspension at room temperature and protect from moisture.
- Missed Dose: Take as soon as remembered unless close to next dose; do not double dose.
- Overdose: Seek urgent medical care; toxicity can include visual, neurological and hepatic effects.
- Follow‑Up: Use telehealth where TDM logistics allow and check PBS authority before dispensing.
Sample Pharmacist Counselling Script: Confirm specialist initiation, explain dosing and empty‑stomach advice, outline monitoring plan and interactions, and provide sun‑safety and vision precautions.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Alice Springs | Northern Territory | 5-9 days |