
Lotrisone
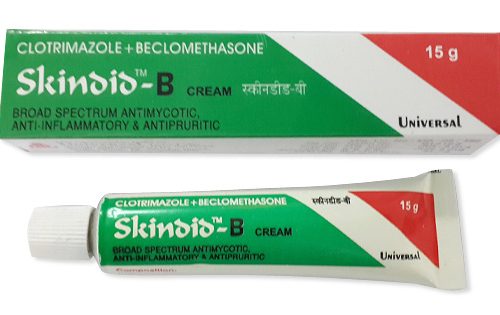
Lotrisone
- In our pharmacy, you can buy lotrisone without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Lotrisone is used for fungal skin infections such as athlete’s foot, jock itch and ringworm; it combines clotrimazole (an imidazole antifungal that impairs fungal cell membrane synthesis) with betamethasone dipropionate (a potent topical corticosteroid that reduces inflammation, itching and redness via glucocorticoid receptor‑mediated effects).
- The usual dose is to apply a thin film to the affected area twice daily (morning and evening) for adults and children 17 years and over — up to 2 weeks for tinea corporis/cruris and up to 4 weeks for tinea pedis; do not exceed 45 g per week.
- Form of administration: topical cream (most common; 1% clotrimazole / 0.05% betamethasone dipropionate) or lotion in some regions.
- Onset time: itching and inflammation commonly improve within 24–48 hours, while antifungal clearance may take several days to weeks.
- Duration of action: symptomatic relief typically lasts until the next application (about 24 hours); full antifungal effect requires completion of the prescribed course (up to 2–4 weeks depending on the condition).
- Alcohol warning: there is no specific interaction with drinking alcohol, but avoid alcohol‑based skin products on the treated area and be cautious with excessive alcohol if long‑term or large‑area use is necessary due to potential systemic steroid absorption.
- The most common side effect is burning or stinging at the application site.
- Would you like to try lotrisone without a prescription?



Basic Lotrisone Information
- INN (International Nonproprietary Name): Clotrimazole and Betamethasone dipropionate
- Brand Names Available In Australia: not specified
- ATC Code: D01AC20
- Forms & Dosages: Cream 1% clotrimazole / 0.05% betamethasone dipropionate (0.643 mg betamethasone dipropionate per 1 g cream) in 15 g and 30 g tubes; lotion available in some regions (country-dependent).
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription Only (Rx) in major markets.
Latest Research Highlights
Are you wondering whether combination antifungal–steroid creams really work faster?
Recent systematic reviews and clinical trials (2022–2025) consistently show that topical combination products containing an imidazole antifungal plus a potent topical corticosteroid deliver faster symptomatic relief for itch and erythema than antifungal monotherapy.
That faster relief comes with trade-offs: trials report increased local steroid adverse effects and concerns that the steroid component can mask ongoing infection.
Australian dermatology audits and TGA pharmacovigilance reports echo international findings and caution that short courses—typically two to four weeks—minimise skin atrophy and hypothalamic–pituitary–adrenal (HPA) axis effects.
Observational work from community pharmacy clinics in regional Australia reports quicker patient‑reported symptom relief with combination creams, but also a higher rate of follow‑up visits for steroid‑related irritation.
Safety-signal analyses during 2022–2025 highlight vulnerable groups such as children, pregnant women and Indigenous patients with inflamed or thinner skin who carry higher relative risk of systemic exposure or local harm.
Typical real-world product: clotrimazole 1% with betamethasone dipropionate 0.05% in 15 g or 30 g tubes, prescription-only.
Data Highlight: cases of HPA suppression are rare but reported after prolonged or large-area use; short supervised courses minimise this risk.
Clinical Effectiveness In Australia
Does the combination clear the fungus faster or just make it feel better?
Australian clinical experience aligns with global trial results: combination clotrimazole/betamethasone creams usually give rapid symptomatic control for tinea corporis, tinea cruris and tinea pedis.
Long-term mycological cure is not consistently superior to antifungal monotherapy, so faster symptom relief does not always mean quicker eradication of the fungus.
TGA adverse event reports and hospital dermatology referrals in Australia show common patterns of misuse such as extended duration, application to large areas and use in children, leading to local atrophy or systemic steroid effects.
On the PBS, combination steroid–antifungal creams are rarely seen as subsidised items, and many prescribers therefore prefer antifungal monotherapy when PBS coverage is a concern.
Community pharmacists at major chains routinely counsel patients to see their GP if symptoms persist beyond the recommended duration, or if rash morphology is unusual.
- Outcome Indicators: symptom relief rate, time-to-relief, recurrence rate, adverse event frequency.
- TGA Reporting Categories (short): serious, non-serious, expected, unexpected.
Indications And Expanded Uses
When is a combination cream appropriate, and when is it not?
TGA-aligned indications for clotrimazole plus betamethasone dipropionate focus on superficial dermatophyte infections with inflammatory symptoms—athlete’s foot, jock itch and ringworm—where fast anti‑itch and anti‑inflammatory effect helps patient comfort and adherence.
Clinicians sometimes use the combination off‑label for highly inflamed or pustular fungal lesions where a short steroid cover eases adherence to antifungal therapy, especially in remote areas where follow-up is difficult.
Australian dermatologists caution strongly against use in rosacea, perioral dermatitis, diaper dermatitis or superficial bacterial infections because steroids can worsen these conditions.
Off‑label prescribing is more common in rural GP practice when specialist access is limited, and telehealth e‑prescriptions are sometimes used—but duration must be explicitly limited.
- Approved Uses: inflamed tinea corporis/cruris, tinea pedis with significant inflammation.
- Off‑Label Situations (use with caution): short-term cover for very inflamed fungal lesions when close follow-up is arranged.
Recommended Durations: up to 2 weeks for tinea corporis/cruris and up to 4 weeks for tinea pedis.
Composition And Brand Landscape
What’s in the tube and what brands exist?
Active ingredients are clotrimazole 1% (an imidazole antifungal) combined with betamethasone dipropionate 0.05% (listed as 0.643 mg betamethasone dipropionate per 1 g cream).
Internationally the product appears as Lotrisone in the United States (15 g and 30 g tubes) and Lotriderm or generic equivalents in Canada, Europe and the Asia‑Pacific.
Generics are widely offered under the INN label “Clotrimazole and Betamethasone Dipropionate Cream”, and local manufacturers vary by market.
| Brand | Packaging | Notes |
|---|---|---|
| Lotrisone | 15 g, 30 g tubes | Primarily North America |
| Lotriderm / Pms-Clotrimazole And Betamethasone | Cream/lotion (varies) | Canada, Europe, Asia‑Pacific |
| Generic Clotrimazole + Betamethasone | 15 g, 30 g tubes (varies) | Widely available internationally |
Excipients can occasionally cause contact allergy; check for known excipient sensitivities in patients with multiple allergies.
Stocking patterns in Australian pharmacy chains tend to show branded stock in metropolitan pharmacies and generic alternatives in regional outlets.
Contraindications And Special Precautions
Who should avoid this cream, and when to be careful?
Absolute contraindications include known hypersensitivity to clotrimazole, betamethasone dipropionate or any excipients, and use on ocular, oral or intravaginal sites.
Relative cautions include children under 17 years (safety not established), pregnant or breastfeeding women (use only if essential), the elderly (monitor for atrophy), and application to extensive, occluded or compromised skin.
Australian priorities include extra caution for Indigenous and remote communities who may have higher rates of skin infection and thinner or inflamed skin; short supervised courses are preferable.
Occupational advice: there are no driving or workplace restrictions, but cosmetic irritation on the hands may affect manual workers and should be discussed.
- Checklist For Contraindications: hypersensitivity, ocular/oral use, paediatric (<17), pregnant/breastfeeding unless essential.
- Decision Tree For Prescribers: assess age, area size, inflammation, occlusion and plan duration before prescribing.
Dosage Guidelines (Australian Practice)
How should patients use it, and what limits are important?
Standard adult dosing is to apply a thin film to the affected area twice daily—morning and evening.
Recommended durations are up to 2 weeks for tinea corporis and tinea cruris, and up to 4 weeks for tinea pedis.
Do not exceed 45 g per week of cream.
Children under 17 should avoid the product unless specifically prescribed, because safety and efficacy are not established in this age group.
Elderly patients require monitoring for skin atrophy and possible systemic effects though no formal dose reduction is specified.
For large-area infections or where occlusion is required, consider oral antifungal therapy or topical antifungal monotherapy to reduce steroid exposure.
| Condition | Frequency | Duration |
|---|---|---|
| Tinea Corporis / Cruris | Twice Daily | Up To 2 Weeks |
| Tinea Pedis | Twice Daily | Up To 4 Weeks |
Interactions Overview
Will topical use affect other medicines?
Typical short-course topical use has minimal systemic drug–drug interactions because systemic absorption is low.
Interaction risk rises with prolonged use, application to large areas, occlusion or broken skin when systemic corticosteroid exposure may become clinically relevant.
Monitor patients who are also taking systemic corticosteroids, or those with repeated topical steroid exposure, as cumulative steroid load could be significant.
There are no clinically relevant food or drink interactions for standard topical use, though excessive alcohol can hamper wound healing or skin recovery.
Prescribers should review concurrent steroid exposure and flag prolonged use for monitoring of possible HPA-axis suppression.
Cultural Perceptions And Patient Habits In Australia
Why do patients reach for a combination cream instead of a single antifungal?
Australian patients often prioritise rapid symptomatic relief, so combination creams that quickly reduce itch and redness are popular.
Price sensitivity and PBS reliance means many patients prefer subsidised antifungal monotherapy when cost is an issue.
Trust in pharmacists is high and community pharmacies are frequent first-contact points, particularly in urban areas.
Rural communities rely more on telehealth e‑prescriptions and local pharmacy stock; remote clinicians may favour short supervised combo use when follow-up is harder.
Indigenous health services emphasise culturally safe skin care and caution on steroid misuse, with an emphasis on close monitoring and short durations.
| Setting | Access Pattern |
|---|---|
| Urban | Walk-in pharmacy advice and metro GP prescribing |
| Rural / Remote | Telehealth e‑prescriptions and local pharmacy dispensing |
Availability And Pricing Patterns In Australia
Can you buy Lotrisone locally, and what will it cost?
Lotrisone is primarily a North American brand and exact brand availability in Australia can vary.
Clinicians in Australia typically prescribe generic clotrimazole + betamethasone combinations where registered, or prefer single-agent antifungals such as clotrimazole or terbinafine.
Combination creams are generally prescription-only in major markets, and PBS listings for steroid–antifungal combinations are uncommon, so out-of-pocket costs vary by pharmacy and brand.
Major chains stock OTC antifungals, and can dispense prescribed combination creams if available.
In our online pharmacy, lotrisone is available without a prescription, with discreet delivery to Australia in 5-14 days.
Comparable Medicines And Prescribing Preferences
What are reasonable alternatives and when should prescribers pick them?
Alternatives in Australia include antifungal monotherapy such as clotrimazole cream (Canesten) or terbinafine (Lamisil), and other combination products available internationally like isoconazole with triamcinolone (Travocort).
Pros of the combination cream are faster symptom relief and potentially better adherence when inflammation is severe.
Cons include steroid-related local atrophy, the risk of masking persistent infection and the lack of PBS subsidy in many cases.
For uncomplicated tinea, many prescribers favour antifungal monotherapy for cost-effectiveness and reliable long-term mycological cure.
- Decision Matrix Example: inflamed short-duration lesions → consider short-course combination; uncomplicated mild tinea → antifungal monotherapy.
Frequently Asked Questions
Can I buy Lotrisone over the counter in Australia?
No, combination clotrimazole/betamethasone creams are typically prescription-only in major markets; check with your GP or pharmacist about local availability.
How long before I see improvement?
Many patients notice itch and redness improve within days, but the complete course should not exceed the recommended duration—up to 2–4 weeks depending on the site.
Can I use it on my child?
Avoid use in children under 17 unless prescribed by a clinician, because safety and efficacy are not established in this age group and systemic steroid risk is higher.
What if symptoms return after stopping?
Return to your GP for re-evaluation and consider mycological testing—steroid masking can delay correct diagnosis and treatment.
Definitions:
- Mycological Cure: laboratory confirmation that the fungus is eradicated.
- Masking: reduction of inflammation by steroid that hides ongoing fungal infection.
Guidelines For Proper Use And Pharmacist Counselling
What should pharmacists tell patients when dispensing a prescription?
Confirm the diagnosis by asking about ring-shaped lesions, itching between toes, and changes with previous treatments.
Reinforce age limits (product for 17 years and older) and advise applying a thin film twice daily to the affected area.
Set an explicit stop date—2 weeks for body infections and 4 weeks for feet—and warn patients not to exceed 45 g per week.
Give site-specific advice such as drying thoroughly between toes for tinea pedis and avoiding occlusion unless directed by a clinician.
Provide written instructions or pictorial aids for remote or Indigenous patients, and arrange telehealth follow-up when in-person review is difficult.
Document counselling in the patient record and report any adverse events to the TGA through the standard reporting channels.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |