
Rocaltrol
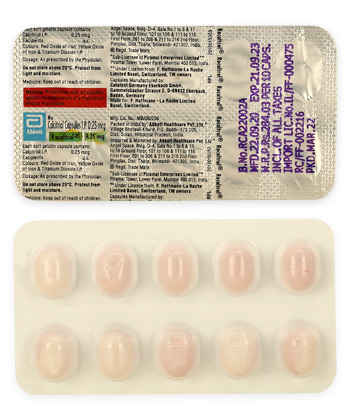
Rocaltrol
- In our pharmacy, you can buy rocaltrol without a prescription (no receipt required), with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Rocaltrol is used to treat and prevent hypocalcaemia, secondary hyperparathyroidism due to chronic kidney disease or dialysis, renal osteodystrophy and hypoparathyroidism. Mechanism: calcitriol is the active form of vitamin D3 that binds the vitamin D receptor, increasing intestinal calcium and phosphate absorption, promoting bone mineralisation and modulating parathyroid hormone secretion.
- The usual dose for adults is commonly 0.25 mcg once daily, titrated (often by 0.25 mcg every 2–4 weeks) based on serum calcium, with typical maxima around 1–2 mcg/day; paediatric dosing is weight‑based (≈0.01–0.02 mcg/kg/day) and adjusted by labs.
- Forms of administration include oral capsules (0.25 mcg, 0.5 mcg), oral solution (1 mcg/mL), injectable ampoules (1 mcg/mL in some markets, e.g. Calcijex) and topical formulations for psoriasis in select regions — Rocaltrol as a brand is primarily oral.
- Onset time: changes in serum calcium are often seen within 24–72 hours after starting or changing dose; symptomatic improvement may take several days.
- Duration of action: clinical effect is generally maintained with once‑daily dosing (effects on calcium metabolism continue while therapy is ongoing), so daily administration and regular monitoring are required.
- Alcohol warning: avoid excessive alcohol intake — alcohol can affect calcium balance and hydration and may increase the risk of adverse effects; use caution and discuss alcohol use with your prescriber or pharmacist.
- The most common adverse effect is hypercalcaemia, which may present as nausea, vomiting, constipation, weakness, headache or drowsiness; regular monitoring of serum calcium and phosphate is essential.
- Would you like to try rocaltrol without a prescription?


Basic Rocaltrol Information
- INN (International Nonproprietary Name): Calcitriol
- Brand Names Available In Australia: Rocaltrol (capsules, oral solution) and Calcijex (intravenous form for hospital use); generic products labelled as calcitriol are also supplied by multiple manufacturers.
- ATC Code: A11CC04
- Forms & Dosages: Capsules 0.25 mcg and 0.5 mcg; oral solution 1 mcg/mL (dropper bottle 15 or 30 mL); injectable 1 mcg/mL ampoule; topical formulations (e.g., 3 mcg/g) available in some regions for psoriasis.
- Manufacturers In Australia: Originator Hoffmann‑La Roche is named in international listings, with numerous generic manufacturers globally (Teva, Sandoz, Amneal and local suppliers); local supplier listings vary by distributor and TGA register.
- Registration Status In Australia: Registered as a prescription medicine; the intravenous form is listed as Calcijex in some markets.
- OTC / Rx Classification: Prescription only medicine (Rx) in all countries.
Latest Research Highlights
Clinicians ask whether recent trials change how we use rocaltrol in practice.
Australian and international studies from 2022–2025 continue to show biochemical benefit from active vitamin D analogues in chronic kidney disease and hypoparathyroidism.
Reported effects consistently include reductions in parathyroid hormone (PTH) and improvements in serum calcium when calcitriol or other active analogues are started and titrated.
The main safety signal across trials and registries is hypercalcaemia, which appears as the adverse event most consistently associated with therapy.
Comparative analyses up to 2024 suggest paricalcitol can provide similar PTH suppression with possibly lower hypercalcaemia rates in some cohorts, though head‑to‑head randomised controlled trials remain limited.
Australian nephrology audits reporting 2022–2025 note effective biochemical control when clinicians follow dose titration and close laboratory monitoring.
| Study/Source | PTH Reduction | Serum Calcium Change | Hypercalcaemia Incidence | Safety Observations |
|---|---|---|---|---|
| Australian Nephrology Audits (2022–2025) | Biochemical improvement reported | Variable; monitoring essential | Observed; frequency not specified | Careful titration and lab follow‑up recommended |
| International RCTs/Observational (2022–2024) | Reduction reported; magnitude not specified | Modest increases possible | Elevated risk noted; rates not specified | Hypercalcaemia main safety signal |
| Comparative Work (Calcitriol vs Paricalcitol to 2024) | Similar PTH suppression reported | Calcium change variable | Some cohorts show lower incidence with paricalcitol; not specified | Head‑to‑head RCTs limited |
| Registries (2022–2025) | Consistent biochemical improvement | Monitoring recommended | Hypercalcaemia recorded as common AE signal | Long‑term mortality/morbidity data still not specified |
Evidence gaps remain in long‑term comparative mortality and morbidity and in optimal dosing algorithms for Indigenous and rural populations.
Regulators such as the TGA monitor adverse‑event trends and continue to highlight hypercalcaemia as the principal safety concern.
Clinical Effectiveness In Australia
Patients often want to know whether rocaltrol works the same here as overseas.
In Australia, calcitriol (Rocaltrol and generics) is a prescription‑only active vitamin D analogue used mainly in nephrology and endocrinology.
TGA registrations align with international indications for hypocalcaemia, secondary hyperparathyroidism and hypoparathyroidism.
PBS coverage varies by indication and formulation, with hospital intravenous formulations typically supplied via public hospitals.
Australian practice audits show reliable biochemical correction when prescribers follow dose titration and monitoring schedules.
The TGA’s adverse‑event reporting consistently flags hypercalcaemia and renal function changes as the main concerns during therapy.
Routine baseline and ongoing testing of serum calcium, phosphate and renal function is standard practice prior to starting calcitriol and during dose changes.
| Indication | Likely PBS Status |
|---|---|
| Hypocalcaemia | Variable; often prescription‑funded per authority |
| Secondary Hyperparathyroidism (CKD/dialysis) | Hospital supplied IV formulations common; community listing varies |
| Hypoparathyroidism | Prescription only; PBS listing depends on authority |
Clinical effectiveness is high when dosing is individualised and monitoring prevents severe adverse outcomes.
Indications And Expanded Uses
Patients ask which conditions really need active vitamin D rather than standard vitamin D supplements.
TGA‑approved indications for calcitriol mirror global labels and include treatment and prevention of hypocalcaemia.
Calcitriol is approved for management of secondary hyperparathyroidism in chronic kidney disease and dialysis, renal osteodystrophy and hypoparathyroidism.
Topical calcitriol formulations exist in some regions for psoriasis but are not interchangeable with oral or IV products.
Off‑label Australian uses reported in specialist clinics include short‑term post‑thyroid or parathyroid surgery, selected metabolic bone disorders and carefully tailored paediatric regimens using weight‑based dosing.
- TGA‑Approved Indications: Hypocalcaemia, secondary hyperparathyroidism, renal osteodystrophy, hypoparathyroidism.
- Common Off‑Label Uses: Post‑operative short courses, specialist bone clinic regimens, paediatric weight‑based therapy under endocrinology supervision.
- Evidence Strength: Strong biochemical data for approved uses; off‑label uses rely on specialist experience and smaller series.
Off‑label prescribing should be documented, consented and supported by explicit monitoring plans.
In Indigenous and remote settings clinicians often balance benefits against access and monitoring challenges and use telehealth‑linked laboratories and community nursing where available.
Composition And Brand Landscape
People commonly ask which brands are identical and which differ.
The active ingredient is calcitriol (INN) and the originator brand widely known is Rocaltrol from Hoffmann‑La Roche.
Generics are available from multiple suppliers such as Teva, Sandoz and Amneal, and local distributors may supply parallel imports.
| Brand | Formulation | Common Pack Sizes | Prescription Status |
|---|---|---|---|
| Rocaltrol | Capsules 0.25/0.5 mcg; oral solution 1 mcg/mL | Blisters/bottles; 15–30 mL solution | Prescription only |
| Calcitriol (Generic) | Capsules 0.25/0.5 mcg; oral solution 1 mcg/mL; injectable 1 mcg/mL | Blisters; ampoules 1 mL | Prescription only |
| Calcijex | Injectable 1 mcg/mL (hospital use) | 1 mL single‑use ampoules | Prescription only (hospital supply) |
Packaging and excipients can vary between manufacturers so check for known sensitivities when switching brands.
Clinically, brand and generic products are considered interchangeable, but always confirm the TGA local listing and any hospital formulary rules.
Contraindications And Special Precautions
Patients understandably worry about who should not take rocaltrol.
Absolute contraindications per product labelling are hypercalcaemia, vitamin D toxicity and known hypersensitivity to calcitriol or excipients.
Special precautions include elderly patients who have a higher risk of hypercalcaemia, and pregnant or breastfeeding women where use should be considered only if the expected benefit outweighs the risk.
Patients on digitalis require close monitoring because hypercalcaemia can increase the risk of cardiac arrhythmias.
Conditions such as sarcoidosis and certain malignancies that raise vitamin D sensitivity require careful assessment before starting calcitriol.
- Contraindications: Hypercalcaemia, vitamin D toxicity, hypersensitivity to components.
- Monitoring Triggers: Rising serum calcium or phosphate, worsening renal function, symptoms suggestive of hypercalcaemia.
- Workplace Safety Notes: If symptomatic (drowsiness, weakness, confusion) avoid driving or operating heavy machinery until reviewed.
In remote and Indigenous healthcare contexts, arrange community pathology or mobile services where possible to ensure safe monitoring.
Dosage Guidelines
One of the common questions is “what dose should I start on and how fast can it change?”.
Typical adult starting dose for chronic kidney disease or hypoparathyroidism is 0.25 mcg daily, with titration by 0.25 mcg every 2–4 weeks guided by calcium and PTH levels.
Maintenance doses commonly fall between 0.25–1 mcg per day, and maximum daily doses are often cited between 1–2 mcg depending on indication and product labelling.
Paediatric dosing is weight‑based at approximately 0.01–0.02 mcg/kg/day and requires specialist supervision.
Calcitriol is indicated specifically for CKD so no routine dose reduction for renal impairment is recommended, but closer monitoring is mandatory.
| Condition | Starting Dose | Titration Steps | Typical Maintenance |
|---|---|---|---|
| Chronic Kidney Disease (Adults) | 0.25 mcg daily | Increase 0.25 mcg every 2–4 weeks | 0.25–1 mcg/day; max 1–2 mcg/day |
| Hypoparathyroidism (Adults) | 0.25 mcg daily | Titrate per serum calcium | Individualised; max usually 2 mcg/day |
| Children | 0.01–0.02 mcg/kg/day | Adjust based on response and labs | Specialist oversight required |
Dosing checklist for pharmacists: confirm baseline calcium, phosphate and creatinine, advise scheduled labs during titration, check for interacting medicines (e.g., thiazides), and document dose changes.
Interactions Overview
Patients often ask which common medicines clash with calcitriol.
Drugs that potentiate hypercalcaemia are the main interaction concern rather than classic metabolic drug interactions.
Thiazide diuretics can increase serum calcium and therefore potentiate hypercalcaemia when combined with calcitriol.
Concurrent digitalis therapy raises the risk of arrhythmias in the event of hypercalcaemia, so monitor closely.
Aluminium‑containing antacids may affect phosphate handling and should be considered in the overall mineral balance plan.
Concurrent high‑dose vitamin D supplements or large doses of calcium supplements will increase toxicity risk and should generally be avoided unless explicitly recommended by the prescriber.
| Drug | Effect | Monitoring |
|---|---|---|
| Thiazide Diuretics | Potentiates hypercalcaemia | Monitor serum calcium regularly |
| Digitalis | Increased arrhythmia risk if hypercalcaemia | ECG and calcium monitoring |
| Calcium Supplements / Vitamin D | Raises total calcium; risk of toxicity | Advise consistent dietary calcium; lab checks |
Advise patients to maintain a consistent dietary calcium intake and to report any nausea, vomiting or weakness promptly.
Cultural Perceptions And Patient Habits
Many Australians trust pharmacists and expect clear, practical instructions about medicines like rocaltrol.
Urban patients typically have easier access to community pathology and receive follow‑up quickly from pharmacies and specialists.
Rural and remote patients, including many Indigenous Australians, face longer journeys to pathology and rely heavily on telehealth and community nursing to support monitoring.
Patient forums frequently show concern about hypercalcaemia and the need for clear written monitoring plans.
Price sensitivity matters in Australia and PBS subsidy availability strongly influences adherence and the choice of brand versus generic.
- Counselling Tip: Provide a short “when to seek help” sheet and a schedule for blood tests.
- Follow‑Up: Pharmacist‑led phone or telehealth check‑ins improve adherence and safety.
For Indigenous healthcare settings, arrange telehealth links for laboratory review and involve community health workers or nurses in the monitoring plan.
Availability And Pricing Patterns
Customers ask where to buy rocaltrol and how much it will cost.
Calcitriol formulations are widely available through major Australian pharmacy chains, independent pharmacies and online prescriber services.
PBS listing depends on indication and formulation; the intravenous product (Calcijex) is typically hospital‑supplied and not a standard community dispense.
Private prices for community oral formulations vary between chemists and online retailers; generic products are often less expensive than originator brands.
Stock and pack size variety can differ by chain and region, and online comparison shopping is common among price‑sensitive customers.
In our online pharmacy, rocaltrol is available without a prescription, with discreet delivery to Australia in 5–14 days.
| Outlet | Availability | Typical Price Pattern |
|---|---|---|
| Major Chains (Chemist Warehouse, Priceline, TerryWhite) | Usually stock generic and branded oral forms | Competitive private pricing; PBS rates apply where relevant |
| Independent Pharmacies | Stock varies; may order specific brands | Prices variable; may match local PBS authority |
| Online Pharmacies / Telehealth | Often list multiple brands and pack sizes | Private pricing; delivery time depends on location |
For rural patients, telehealth prescriptions and e‑scripts have improved access, but stock variability can still cause short delays.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–7 days |
| Wollongong | New South Wales | 5–7 days |
| Townsville | Queensland | 5–9 days |
| Geelong | Victoria | 5–7 days |
| Albury | New South Wales / Victoria | 5–9 days |
Comparable Medicines And Preferences
Clinicians and patients want to know when another active vitamin D analogue is preferred.
Alternatives available in Australia include alfacalcidol, paricalcitol and doxercalciferol, while native vitamin D (cholecalciferol or ergocalciferol) is used for simple deficiency states but is not suitable for advanced CKD or hypoparathyroidism.
| Agent | Main Benefits | Main Drawbacks | Australian Setting |
|---|---|---|---|
| Calcitriol (Rocaltrol) | Potent active form; widely available | Higher hypercalcaemia risk if not monitored | Common in nephrology and endocrinology clinics |
| Paricalcitol (Zemplar) | Similar PTH control; may have lower hypercalcaemia in some cohorts | Higher cost; availability varies | Selected patients where hypercalcaemia risk is a concern |
| Alfacalcidol (One‑Alpha) | Prodrug that is activated in the liver | Regional prescribing preferences; monitoring still required | Used in selected settings |
| Native Vitamin D | Useful for deficiency and general bone health | Not suitable alone for advanced CKD or hypoparathyroidism | Primary care and general supplementation |
Choice in Australia depends on comorbidity, cost and the capacity for monitoring.
FAQ
Q: Is Rocaltrol the same as vitamin D?
A: Rocaltrol is calcitriol, the active form of vitamin D, and is different from cholecalciferol because it is already active and used for specific medical conditions.
Q: What monitoring is needed?
A: Baseline and periodic serum calcium, phosphate and renal function are required, typically every 1–4 weeks during titration and at intervals thereafter as advised by the specialist.
Q: Can I switch brands?
A: Generic and branded forms are generally considered bioequivalent, but check excipients for known allergies and follow prescriber or pharmacist advice when switching.
Q: What if I miss a dose or suspect an overdose?
A: If you miss a dose, take it as soon as you remember unless it is near the next scheduled dose; do not double up.
In the event of an overdose, symptoms of hypercalcaemia include weakness, headache, vomiting, constipation and bone or muscle pain, and urgent medical attention is required.
Guidelines For Proper Use
Pharmacist counselling should open with the patient’s main concern about the medicine and what they expect from treatment.
Explain why an active form of vitamin D is needed for their condition rather than standard vitamin D supplements.
State the dosing schedule clearly and outline the likely titration plan with timeframes for laboratory checks.
Advise baseline and follow‑up blood tests for calcium, phosphate and renal function, and specify the monitoring frequency during titration.
Give clear food and supplement advice: avoid unsupervised high‑dose calcium supplements and inform prescribers of any major diet changes.
Describe the signs of hypercalcaemia and when to seek urgent care.
Storage instructions: store at room temperature (15–25°C), protect from light and do not freeze the solution.
Missed‑dose advice: take as soon as remembered unless close to the next dose and never double the dose.
For rural and Indigenous patients arrange telehealth follow‑up and community pathology or nurse‑led monitoring where possible.
Use a short written monitoring plan and a brief pharmacist script when handing over the medicine to improve clarity and adherence.
