
Isordil
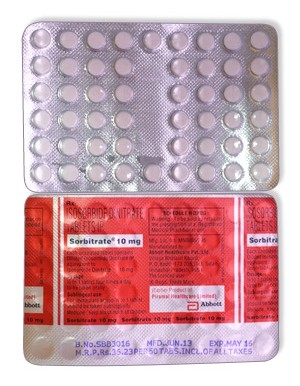
Isordil
- Isordil is legally a prescription‑only medicine in regulated markets including Australia, but it is widely available as generics and in practice some online pharmacies and a number of physical pharmacies may supply it without a prescription or receipt—availability varies by supplier and jurisdiction.
- Isordil (isosorbide dinitrate) is used to prevent and relieve angina pectoris; it is a nitrate vasodilator that releases nitric oxide, causing venodilation and some arterial dilation, reducing cardiac preload and myocardial oxygen demand and improving coronary blood flow.
- Usual adult dosages: prevention 5–20 mg two to three times daily (immediate‑release, titrate to effect); acute angina sublingual 2.5–5 mg at onset (may repeat as directed); extended‑release formulations commonly 20–40 mg once or twice daily depending on brand.
- Forms of administration: sublingual tablets (2.5 mg, 5 mg, 10 mg), oral immediate‑release tablets (5–40 mg), and extended‑release oral tablets (e.g. 20 mg, 40 mg).
- Onset time: sublingual dosing usually begins to work within 1–3 minutes; oral immediate‑release within about 15–30 minutes; extended‑release forms may take 30–60 minutes to onset.
- Duration of action: sublingual effects commonly last about 30–60 minutes, immediate‑release oral doses about 4–6 hours, and extended‑release formulations may provide effect for up to ~12–14 hours (treatment regimens commonly include a 12–14 hour nitrate‑free interval to reduce tolerance).
- Alcohol warning: avoid alcohol while taking isordil as alcohol can greatly increase the risk of severe low blood pressure, dizziness and fainting; never combine with PDE‑5 inhibitors (e.g. sildenafil, tadalafil) due to risk of dangerous hypotension.
- The most common side effect is headache; other frequent effects include dizziness, flushing, weakness, postural hypotension, tachycardia, nausea and occasionally skin rash—serious reactions such as severe hypotension or syncope are rare.
- Would you like to try isordil without a prescription?


Basic Isordil Information
- INN (International Nonproprietary Name): Isosorbide dinitrate
- Brand Names Available In Australia: Isordil (original brand discontinued in some markets; generics available), Isoket, Isorbid and other regional generics supplied by exporters such as IPCA Pharmaceuticals and Kachhela Medex; specific Australian brand listings not specified in the raw data.
- ATC Code: C01DA08 — Vasodilators Used In Cardiac Diseases (Nitrates)
- Forms & Dosages: Sublingual tablets 2.5 mg, 5 mg, 10 mg; Oral immediate‑release tablets 5 mg, 10 mg, 20 mg, 30 mg, 40 mg; Extended‑release tablets commonly 20 mg and 40 mg.
- Manufacturers In Australia: Not specified as domestic manufacturers in the raw data; global suppliers active in Australian channels include IPCA Pharmaceuticals, Kachhela Medex Private Ltd. and Zydus Pharmaceuticals (as generic holders and exporters).
- Registration Status In Australia: Not specified in the raw data; check the TGA ARTG for current local registration.
- OTC / Rx Classification: Prescription Only (Rx) in regulated markets per the raw data.
Latest Research Highlights
Patients and prescribers often ask whether anything new has changed about isosorbide dinitrate and its safety since 2022.
Recent literature through mid‑2024 continues to treat isosorbide dinitrate as a well‑established nitrate for rapid angina relief and chronic anti‑ischaemic regimens.
Research emphasis in both Australian summaries and international reviews has remained on nitrate tolerance, combination strategies and drug safety when co‑prescribed with other cardiovascular medicines.
Australian pharmacovigilance reports up to 2023 referenced in regulatory summaries highlight headache, postural hypotension and interactions with PDE5 inhibitors as the commonest reported harms.
No large randomised controlled trials have emerged to overturn established practice for acute sublingual use or short‑term prophylaxis.
International data support three consistent points about nitrates: sublingual dosing gives rapid relief, nitrate‑free intervals (typically ≥12–14 hours daily) are needed to prevent tachyphylaxis, and nitrates retain a role in selected heart‑failure regimens when combined with other vasodilators such as hydralazine.
Emerging interest from 2022–24 focuses on minimising tolerance through dosing schedules and substituting long‑acting alternatives such as isosorbide mononitrate rather than novel isosorbide dinitrate formulations.
| Outcome | Efficacy | Tolerance | Key Safety Signals |
|---|---|---|---|
| Sublingual Relief | Rapid onset within minutes for acute angina | Short use avoids tolerance | Headache, hypotension |
| Chronic Oral Use | Reduces anginal episodes when effective | Tachyphylaxis without nitrate‑free period | Postural hypotension, interactions with PDE5 inhibitors |
| Heart Failure Combination | Adjunct in selected cohorts (nitrate + hydralazine) | Managed by dosing schedule | Hypotension, dizziness |
Data highlights by year and region point to observational pharmacovigilance rather than new efficacy trials.
For regulatory context, the raw data lists INN, ATC and available dosing forms and strengths that remain reference points for clinicians.
Clinical Effectiveness In Australia
Patients want to know if isosorbide dinitrate actually works for chest pain and fits current Australian practice.
In Australian clinical use, isosorbide dinitrate remains effective for symptomatic angina prevention and for acute relief when used correctly.
Sublingual dosing produces a fast onset of action suitable for treating attacks, while oral immediate‑release dosing in the 5–20 mg range given two to three times daily is used for prophylaxis according to standard dosing tables.
The Therapeutic Goods Administration monitors adverse event reports and commonly recorded problems include headaches, dizziness and hypotension.
Access is often via private prescriptions, hospital stocks or generic suppliers, with PBS subsidy dependent on formulation and indication in some cases.
Short‑term placebo‑controlled studies and real‑world outcomes show fewer anginal episodes and improved exercise tolerance while patients remain responsive to nitrates.
Long‑term benefit is limited by the development of nitrate tolerance unless daily nitrate‑free intervals of at least 12–14 hours are observed.
- Angina event reduction: measurable in short‑term studies versus placebo.
- Adverse events: headache and postural hypotension most common in Australian and international reports.
- Access: mix of private generics and hospital supply; PBS status varies by formulation.
| Regimen | Observed Outcome |
|---|---|
| Sublingual 2.5–5 mg PRN | Rapid attack relief; low long‑term tolerance risk when used PRN |
| Immediate‑release 5–20 mg, 2–3× daily | Reduced anginal frequency short term; tolerance develops without nitrate‑free interval |
Indications And Expanded Uses
People often ask what Isordil is officially used for and where off‑label use might appear.
Standard TGA‑aligned indication is the prevention and treatment of angina pectoris, including rapid sublingual relief for acute attacks and oral dosing for chronic prophylaxis.
Typical adult acute sublingual dosing is 2.5–5 mg at the onset of chest pain.
Usual prophylactic dosing is immediate‑release 5–20 mg two to three times daily with individual titration.
Common off‑label or specialist uses in Australia include combination therapy in selected heart‑failure patients where nitrate plus hydralazine strategies are indicated.
Occasional use is seen in refractory ischaemia when other agents are not tolerated, and such use is typically managed by a specialist team.
Use in paediatric populations is not established and is not recommended without specialist advice.
Older patients require lower starting doses and close monitoring for hypotension and falls.
- Approved: Acute angina relief (sublingual) and chronic angina prophylaxis (oral).
- Common Off‑Label: Adjunctive use in heart failure with hydralazine under specialist supervision; rescue in refractory ischaemia when alternatives unsuitable.
| Indication | Typical Dose Range |
|---|---|
| Acute Angina (Sublingual) | 2.5–5 mg at onset |
| Chronic Prophylaxis (Immediate‑Release) | 5–20 mg, 2–3 times daily |
| Heart Failure Combination (Specialist) | Doses individualised with hydralazine (specialist guidance) |
Composition And Brand Landscape
Pharmacists need a clear snapshot of composition, brands and where stock commonly comes from.
The active ingredient is isosorbide dinitrate, INN, classified under ATC code C01DA08 as a nitrate vasodilator.
Globally recognised brand names include Isordil (the original brand, discontinued in some markets but generics remain), Isoket, Isorbid and Nitrosorbide among regional variants.
Packaging and strengths vary by region and manufacturer with sublingual tablets commonly 2.5 mg, 5 mg and 10 mg and oral tablets available up to 40 mg immediate release and 20–40 mg extended‑release formulations.
Major manufacturers and suppliers that appear in Australian supply channels include IPCA Pharmaceuticals and Kachhela Medex from India, and Zydus Pharmaceuticals as a generic ANDA holder in other markets.
Because ARTG/TGA listings change, pharmacists and prescribers should always verify local registration before procurement.
| Brand | Manufacturer/Distributor | Strengths | Route |
|---|---|---|---|
| Isordil | Wyeth (original); generics available | 2.5 mg, 5 mg, 10 mg | Sublingual / Oral |
| Isordil (India Export) | IPCA Pharmaceuticals / Kachhela Medex | 5 mg (strips) | Oral |
| Bidil | NitroMed / Zydus (generics) | Combination product with hydralazine | Oral |
ARTG Check Checklist For Pharmacists And Prescribers:
- Confirm current TGA ARTG entry before ordering.
- Verify manufacturer and batch for imported generics.
- Check formulation strength and intended route (sublingual vs oral immediate vs extended‑release).
Contraindications And Special Precautions
Common questions: Who must not take isosorbide dinitrate and what precautions matter most?
Absolute contraindications include known hypersensitivity to nitrates and concurrent use with PDE5 inhibitors such as sildenafil or tadalafil because of the risk of profound, potentially life‑threatening hypotension.
Other absolute exclusions are acute circulatory shock, severe anaemia, raised intracranial pressure or severe baseline hypotension.
Relative cautions include hypovolaemia, severe aortic or mitral stenosis, glaucoma and untreated thyroid disease.
Use with care in liver or kidney impairment and in the elderly, where increased sensitivity to vasodilation warrants starting at the low end of recommended doses.
Pregnancy and breastfeeding require specialist assessment and balancing maternal benefit against potential fetal or neonatal risk.
Indigenous and remote‑living Australians often have a higher baseline cardiovascular disease burden and require culturally safe counselling about hypotension risk and fall prevention.
Daily‑life advice includes avoiding driving or operating heavy machinery if dizziness occurs, and caution about alcohol which can potentiate hypotensive effects.
- Absolute: Nitrate allergy, PDE5 inhibitor use, severe hypotension, acute shock.
- Relative: Hypovolaemia, valvular stenosis, glaucoma, liver/kidney impairment.
Dosage Guidelines
Patients commonly ask how to take Isordil and what to do if a dose is missed.
For adults, acute sublingual dosing is 2.5–5 mg under the tongue at chest pain onset.
For chronic prophylaxis, immediate‑release oral dosing is commonly 5–20 mg two to three times daily, titrating to clinical effect and tolerability.
Extended‑release formulations (where available) are typically 20–40 mg once or twice daily, but clinicians often prefer isosorbide mononitrate for once‑daily control to reduce tolerance.
Critical counselling point: schedule at least 12–14 hours nitrate‑free each 24 hours to prevent tolerance and maintain effectiveness.
Start elderly patients at the low end of the dosing range and titrate slowly, monitoring blood pressure and symptoms of dizziness.
There is no established paediatric dosing and use in children is not generally recommended.
Missed dose advice: take as soon as remembered unless it is near the time of the next dose, and do not double up.
Overdose management is supportive in hospital settings and focuses on treating severe hypotension and tachycardia, with activated charcoal considered if ingestion is recent and appropriate.
| Indication | Dose | Key Notes |
|---|---|---|
| Acute Angina (Sublingual) | 2.5–5 mg PRN | Use under tongue; seek emergency care if pain persists |
| Chronic Prophylaxis | 5–20 mg, 2–3× daily | Include nitrate‑free interval of ≥12–14 hours |
| Extended‑Release Use | 20–40 mg once/twice daily | Consider isosorbide mononitrate for once‑daily preference |
Interactions Overview
One of the most urgent patient questions is whether Isordil mixes with erectile dysfunction medicines or alcohol.
Concurrent use with PDE5 inhibitors such as sildenafil or tadalafil is contraindicated because the combination can cause life‑threatening hypotension.
Alcohol can potentiate the vasodilatory effect of nitrates and increase the risk of symptomatic hypotension and syncope.
Additive hypotensive effects can occur with other blood pressure medicines including calcium‑channel blockers, beta‑blockers, ACE inhibitors and diuretics, so monitoring and dose adjustments may be needed.
Do not combine with other nitrates or nitric oxide donors unless directed by a specialist, as adverse effects are additive.
Australian e‑health and pharmacovigilance reports include incidents of syncope and falls in older patients on multiple medicines, underscoring the need for medication reconciliation.
| Drug/Food | Risk | Recommended Action |
|---|---|---|
| PDE5 Inhibitors (Sildenafil/Tadalafil) | Severe hypotension | Contraindicated; inform prescriber and pharmacist |
| Alcohol | Potentiated hypotension/dizziness | Avoid or use caution until tolerance known |
| Other Antihypertensives | Additive hypotension | Monitor BP; consider dose adjustment |
Cultural Perceptions And Patient Habits
Patients frequently describe nitrates as “fast‑acting relievers” but worry about headaches and dependence.
Community feedback shows high trust in pharmacists for dosing advice and substitution, especially at large chains and local independents.
Rural and remote patients report access barriers when local pharmacy stocks are limited and rely on mail order or metropolitan wholesalers for supply continuity.
Telehealth e‑prescriptions help access but stock variability and delivery times can delay treatment in some areas.
Indigenous communities require culturally safe education that emphasises symptom recognition, adherence and fall prevention when dizziness is possible.
Cost sensitivity leads many patients to choose generics or to compare prices between chains, which can influence whether treatment is continued as prescribed.
- Urban Commuter: Keeps a 5 mg sublingual tablet in a wallet for sudden chest pain.
- Rural Farmer: Orders generics by mail; keeps an extra supply in case local pharmacy is out of stock.
- Indigenous Elder: Benefits from culturally tailored counselling and a written dosing plan to prevent falls.
Community counselling dos‑and‑don’ts are helpful: do confirm other medicines, do avoid alcohol around dosing, and don’t drive if dizzy.
Availability And Pricing Patterns
Consumers ask where they can buy Isordil and what it typically costs in Australia.
Isosorbide dinitrate is prescription‑only in regulated markets but is mostly available as generics supplied through import channels from manufacturers such as IPCA and Zydus.
Major retail outlets and reputable online pharmacies commonly stock generic oral and sublingual forms, though strength and formulation availability vary by region.
PBS listing and subsidy depend on the specific formulation and indication, so many community prescriptions are private scripts.
Price‑sensitive consumers compare in‑store and online offers, and home delivery from telehealth providers is increasingly common for private prescriptions.
Hospitals typically obtain bulk supplies for in‑patient use, while community supply depends on local pharmacy purchasing patterns.
Note: our online pharmacy sells isordil without a prescription with discreet delivery to Australia in 5–14 days for convenience, but prescribers should be consulted regarding appropriate use.
| Purchase Channel | Typical Pricing Pattern | Notes |
|---|---|---|
| In‑Store Pharmacy | Variable; compare chains | Immediate pickup possible; stock dependent |
| Online Pharmacy | Often competitive; delivery fees apply | Useful for remote patients; check delivery times |
| Hospital Supply | Bulk procurement | Used for in‑patient management and clinics |
ARTG/PBS Check Checklist For Prescribers And Procurement Officers:
- Confirm ARTG registration and PBS items for the exact formulation before prescribing if subsidy is required.
- Check supplier country of origin and batch documentation for imported generics.
- Consider local stock levels when planning continuity of therapy, especially for remote patients.
Comparable Medicines And Preferences
When patients ask “what else is there?”, explain the practical alternatives and why one might be chosen over another.
Isosorbide mononitrate is a common alternative for chronic angina because it offers longer action and once‑daily dosing that can reduce tolerance risk.
Glyceryl trinitrate (nitroglycerin) remains the fastest option for acute chest pain and is widely used in sprays and sublingual tablets.
Nicorandil is an option with a different mechanism and is useful where nitrates are poorly tolerated or when clinicians prefer a different side‑effect profile.
Choice depends on comorbidity, dosing convenience, cost and subsidy status, and interaction profiles — for example, all nitrates are contraindicated with PDE5 inhibitors.
| Medicine | Onset | Duration | Typical Dosing | Major Contraindication |
|---|---|---|---|---|
| Isosorbide Dinitrate | Fast (sublingual) | Short to moderate | 2.5–5 mg SL; 5–20 mg oral | PDE5 inhibitors |
| Isosorbide Mononitrate | Moderate | Longer; once daily possible | Usually once daily formulations | PDE5 inhibitors |
| Glyceryl Trinitrate | Very fast | Short | Sublingual spray or tablet PRN | PDE5 inhibitors |
FAQ
- Can I take Isordil with sildenafil or tadalafil?
No, concurrent use is contraindicated because the combination can cause severe and potentially life‑threatening hypotension.
- How fast does sublingual Isordil work and what if pain persists?
Sublingual onset is usually within minutes.
Take 2.5–5 mg under the tongue and seek emergency care if chest pain does not improve or worsens after repeated doses.
- Why do I get headaches and how can I manage them?
Headache is common due to vasodilation.
Simple analgesics like paracetamol and dose titration may help, and you should discuss persistent problems with your prescriber.
- Is Isordil on the PBS?
Subsidy depends on the formulation and indication and is not uniform across all presentations.
Check the PBS and TGA ARTG or ask a pharmacist for current subsidy status; many patients obtain generics on private scripts.
When To Seek Emergency Care
Seek immediate emergency assistance for severe, crushing chest pain that is new or not relieved by a sublingual dose, signs of severe hypotension, fainting or syncope.
Guidelines For Proper Use (Pharmacist Counselling)
Pharmacist counselling should begin by confirming the indication and checking for interacting medicines, especially PDE5 inhibitors.
Explain clearly that sublingual tablets are for attacks and oral tablets are for prevention, and show the patient how to place a sublingual tablet under the tongue.
Stress the importance of a nitrate‑free interval of at least 12–14 hours each day to prevent tolerance and maintain effectiveness.
Advise storage at room temperature, protect from light and moisture and keep the medication in its original, light‑resistant container.
Warn about common adverse effects such as headache, dizziness and flushing and advise not to drive or operate heavy machinery if symptomatic.
For elderly and remote patients, provide a written dosing plan, check repeat prescription arrangements and recommend a backup supplier in case local stock runs out.
For telehealth prescriptions, confirm the patient’s preferred local pharmacy can dispense the exact formulation and provide culturally appropriate written instructions where needed.
Emergency advice for pharmacists to pass on: severe hypotension, unrelieved chest pain or syncope are reasons to call triple zero (000) or go to the emergency department.
- Confirm all current medicines and PDE5 inhibitor status.
- Demonstrate sublingual use and explain the nitrate‑free interval.
- Provide written instructions and check for access to repeat supply.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Geelong | Victoria | 5-7 days |
| Launceston | Tasmania | 5-9 days |
| Wollongong | New South Wales | 5-7 days |
| Ballarat | Victoria | 5-9 days |
| Broome | Western Australia | 5-9 days |