
Prograf
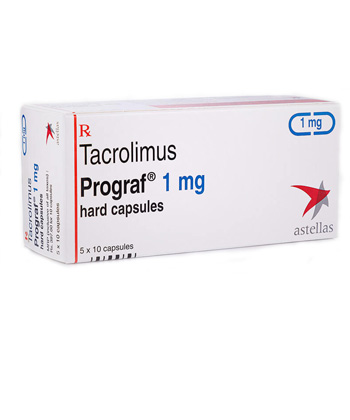
Prograf
- Prograf (tacrolimus) is normally dispensed via hospitals, specialty pharmacies and authorised wholesalers and is prescription-only in most countries (including Australia). Some community pharmacies or online sellers may offer Prograf without a prescription or receipt, but this is not recommended and may be illegal or unsafe — it should be used only under medical supervision.
- Prograf is used to prevent organ rejection after kidney, liver, heart and lung transplantation; it is a calcineurin inhibitor that binds FKBP‑12 and suppresses T‑lymphocyte activation and interleukin‑2 production.
- Typical starting oral dosing is about 0.1–0.2 mg/kg/day divided every 12 hours for adults (liver transplants often 0.10–0.15 mg/kg/day); doses are adjusted to trough blood levels (commonly 5–15 ng/mL early post‑transplant) and individual response — paediatric dosing is higher per kg and elderly/liver‑impaired patients require careful adjustment.
- Available as immediate‑release oral capsules (0.5, 1, 5 mg), granules for oral suspension (sachets), intravenous injection (vials) and extended‑release formulations (once‑daily tablets/capsules).
- Tacrolimus reaches measurable blood levels within 1–3 hours after an oral dose and begins to exert immunosuppressive effects within hours, though clinical protection against rejection develops over days with therapeutic monitoring.
- Immediate‑release Prograf is usually dosed twice daily with an effective duration of about 12 hours per dose; extended‑release formulations provide more sustained levels for once‑daily dosing.
- Avoid heavy alcohol consumption; alcohol can increase the risk of liver injury, affect blood glucose and overall tolerability — discuss alcohol use with your transplant team or prescriber.
- The most common side effect is tremor (shaking); other frequent adverse effects include headache, gastrointestinal upset, hypertension, elevated creatinine and hyperglycaemia.
- Would you like to try prograf without a prescription?

Prograf (Tacrolimus) Guide
Basic Prograf Information
- INN (International Nonproprietary Name): Tacrolimus
- Brand Names Available In Australia: Prograf®, Advagraf®, Astagraf XL®, Envarsus XR®, Modigraf®, Tacrolimus Sandoz®, Tacrolimus Accord®, Tacrolimus Mylan® (brands listed in global data).
- ATC Code: L04AD02 (Calcineurin inhibitors; immunosuppressants).
- Forms & Dosages: Immediate‑release capsules 0.5mg, 1mg, 5mg; granules for oral suspension 0.2mg, 1mg sachets; injection 5mg/mL vials; extended‑release tablets/capsules 0.5mg, 1mg, 3mg, 5mg.
- Manufacturers In Australia: Not specified.
- Registration Status In Australia: Not specified.
- OTC / Rx Classification: Rx only (prescription required).
Latest Research Highlights
Patients often ask whether tacrolimus is still the best anti‑rejection drug.
Recent literature (2022–2025) continues to support tacrolimus as central to solid‑organ transplant immunosuppression and to show improved graft outcomes where tacrolimus replaced older regimens.
Australian registry analyses such as ANZDATA trend reports align with global trials showing steady graft survival improvements after widespread adoption of tacrolimus‑based regimens.
Extended‑release formulations (for example Advagraf® and Envarsus XR®) consistently reduce peak‑to‑trough variability and can improve adherence by offering once‑daily dosing for suitable patients.
Generics meet bioequivalence standards but recent guidance stresses the importance of not swapping between formulations without clinical oversight and repeat therapeutic drug monitoring.
Safety syntheses emphasise known risks: nephrotoxicity, neurotoxicity (tremor), new‑onset diabetes after transplant (NODAT), and infection/malignancy risks related to long‑term immunosuppression.
Pharmacokinetic work from 2022–2024 has focused on dose individualisation using trough levels and CYP3A pharmacogenetics to predict clearance, especially in children and some Indigenous populations.
| Formulation | Acute Rejection | Graft Survival | Adverse Events |
|---|---|---|---|
| Immediate‑Release (Prograf) | Low when TDM maintained | Good long‑term outcomes | Higher peak‑related effects (tremor) |
| Extended‑Release (Advagraf, Envarsus XR) | Comparable or slightly improved with adherence | Similar or improved with less variability | Fewer peak adverse effects; requires supervised conversion |
| Generics | Comparable if bioequivalence and TDM ensured | Comparable with monitoring | Switching formulations may need close monitoring |
TDM Targets: Early troughs generally 5–15 ng/mL; later maintenance 3–7 ng/mL (liver may aim higher early up to 20 ng/mL).
Clinical Effectiveness In Australia
Patients want to know how tacrolimus performs in Australian practice.
Tacrolimus is the predominant calcineurin inhibitor used for kidney, liver, heart and lung transplants in Australia, with product use aligned to international guidelines.
PBS listings and hospital formularies commonly favour tacrolimus‑based regimens combined with mycophenolate and steroids for improved graft survival and reduced acute rejection compared with older cyclosporine regimens.
TGA adverse events reporting captures nephrotoxicity, neuropsychological effects and infections, and hospital pharmacovigilance teams use these reports to refine local protocols.
Trough monitoring (pre‑dose) is routine in Australian centres and guides dose individualisation, with common product‑info targets: early 5–15 ng/mL and later 3–7 ng/mL.
Rural and remote patients face practical barriers to frequent TDM; regional centres, local pathology partnerships and telehealth models are increasingly used to support monitoring and follow‑up.
| TGA / PBS Position | Clinical Indications | Observed Outcome Metrics |
|---|---|---|
| Hospital formularies favour tacrolimus | Kidney, Liver, Heart, Lung transplant prevention | Improved graft survival; fewer acute rejections vs older regimens |
| PBS subsidy with authority checks for many recipients | Long‑term maintenance immunosuppression | Routine TDM and dose individualisation recorded in PBS hospital data |
- TDM: Therapeutic Drug Monitoring — blood tests to measure trough levels.
- Trough: Pre‑dose concentration used to guide dosing.
- NODAT: New‑Onset Diabetes After Transplant — a known complication associated with tacrolimus.
Indications And Expanded Uses
People often ask whether tacrolimus is used beyond the main transplant indications.
TGA‑aligned systemic indications mirror international approvals: prevention of organ rejection in kidney, liver, heart and lung transplantation.
Product‑information lists multiple systemic formulations: immediate‑release capsules, granules for oral suspension, IV injection and extended‑release preparations.
Off‑label and expanded uses seen in Australia include steroid‑sparing regimens and desensitisation protocols in complex re‑transplant cases when clinically justified.
Topical tacrolimus (Protopic®) is used in dermatology for atopic dermatitis but is a different formulation and separate indication; systemic and topical uses must not be interchanged.
Paediatric practice often requires higher mg/kg dosing with close TDM due to faster metabolism in children.
| Indication | Typical Initial Dose | Target Trough |
|---|---|---|
| Kidney Transplant | 0.1–0.2 mg/kg/day oral divided q12h | Early 5–15 ng/mL; maintenance 3–7 ng/mL |
| Liver Transplant | 0.10–0.15 mg/kg/day oral divided q12h | Early 5–20 ng/mL; maintenance 5–15 ng/mL |
| Heart / Lung Transplant | 0.075–0.15 mg/kg q12h (variable) | As above, individualised |
- Off‑Label Practices: Steroid‑sparing regimens, desensitisation — evidence varies; specialist supervision required.
- Topical Use: Protopic® for eczema is topical tacrolimus and not interchangeable with systemic tacrolimus.
Composition And Brand Landscape
Patients ask which brands and formulations are available when filling a prescription.
INN is tacrolimus and the originator product is Prograf® (Astellas).
Extended‑release family members include Advagraf® and Astagraf XL®, while Envarsus XR® is another extended‑release option.
Several generics are marketed globally including Tacrolimus Sandoz®, Tacrolimus Mylan®, Tacrolimus Accord® and others.
| Formulation | Strengths | Common Brands | Packaging Notes |
|---|---|---|---|
| Immediate‑Release Capsules | 0.5mg, 1mg, 5mg | Prograf®, Generics | Blister packs or bottles; typically 30–100 units |
| Granules For Oral Suspension | 0.2mg, 1mg sachets | Modigraf®, Prograf® Granules | Single‑dose sachets for paediatrics or dysphagia |
| Injection (IV) | 5mg/mL vial | Prograf® Injectables, generics | Vials for hospital use |
| Extended‑Release Tabs/Caps | 0.5mg, 1mg, 3mg, 5mg | Advagraf®, Envarsus XR® | Different PK; once‑daily options |
- Substitution Cautions: Do not interchange immediate‑release and extended‑release preparations without prescriber approval and repeat TDM.
- Packaging: Some packs are child‑resistant and include light/temperature protection for stability.
Contraindications And Special Precautions
Patients commonly worry about who should not take tacrolimus.
Absolute contraindication is known hypersensitivity to tacrolimus or formulation excipients.
High‑risk groups needing special caution include people with significant hepatic impairment, those with renal impairment, the elderly, pregnant or breastfeeding women and people with prior malignancy.
Concurrent nephrotoxic drugs increase risk and need careful review by prescribers and pharmacists.
Special attention is needed for Indigenous Australians because of higher prevalence of comorbidities such as chronic kidney disease and diabetes; culturally safe monitoring and easier access to TDM are important.
- Absolute Contraindications: Hypersensitivity to tacrolimus or excipients.
- Relative Contraindications: Hepatic impairment, renal impairment, concurrent nephrotoxic therapy, history of severe infections or malignancy.
- Definitions:
- NODAT — New‑Onset Diabetes After Transplant.
- Nephrotoxicity — Kidney injury linked to calcineurin inhibitors.
Avoid live vaccines while immunosuppressed and give workplace counselling about tremor or neurotoxicity affecting alertness.
Dosage Guidelines
One of the most frequent patient questions is "How much should I take and how do we check it?"
| Indication | Starting Dose | Target Trough | Monitoring Frequency |
|---|---|---|---|
| Kidney Transplant | 0.1–0.2 mg/kg/day orally divided q12h | Early 5–15 ng/mL; maintenance 3–7 ng/mL | Daily–weekly early; monthly once stable |
| Liver Transplant | 0.10–0.15 mg/kg/day divided q12h | Early 5–20 ng/mL; later 5–15 ng/mL | Daily–weekly early; individualised |
| Heart / Lung | 0.075–0.15 mg/kg q12h (variable) | Individualised | Frequent early monitoring |
| Paediatrics | Often higher mg/kg; close TDM | 5–20 ng/mL target ranges depending on age | Very frequent TDM |
Missed Dose: Take as soon as remembered if only a few hours late.
If near the next scheduled dose, skip the missed dose and continue the usual schedule.
Never take a double dose to make up for a missed dose.
Overdose: May cause nephrotoxicity, neurotoxicity, hyperkalaemia and severe immunosuppression and requires urgent medical assessment and supportive care.
Interactions Overview
Patients often ask "Will my other medicines affect tacrolimus?"
Tacrolimus is metabolised by CYP3A4 and transported by P‑glycoprotein, so many drug interactions change blood levels quickly.
Strong CYP3A inhibitors raise tacrolimus levels and increase the risk of nephrotoxicity and neurotoxicity.
Strong CYP3A inducers lower tacrolimus levels and risk acute rejection.
Grapefruit and grapefruit juice increase tacrolimus exposure and should be avoided.
- Strong Inhibitors: Azole antifungals (e.g., ketoconazole), macrolide antibiotics (e.g., clarithromycin), some protease inhibitors — expect increased tacrolimus levels; monitor closely and adjust dose.
- Strong Inducers: Rifampicin, carbamazepine, St John’s Wort — expect reduced levels and potential loss of efficacy.
- Other Notes: Alcohol may worsen liver function but does not directly alter tacrolimus pharmacokinetics; caffeine can worsen tremor but is not a pharmacokinetic interaction.
| Drug / Food | Expected Effect On Tacrolimus | Clinical Action |
|---|---|---|
| Ketoconazole (azole) | Increase levels | Avoid or reduce tacrolimus dose; close TDM |
| Rifampicin | Decrease levels | Avoid or increase monitoring; specialist advice |
| Grapefruit Juice | Increase levels | Avoid grapefruit products |
Pharmacists should use real‑time interaction checkers and liaise with transplant teams when new medicines are prescribed.
Cultural Perceptions And Patient Habits
People ask how tacrolimus fits into daily life and cultural expectations.
Australian patients commonly express strong trust in pharmacists and rely on PBS subsidies when eligible.
Price sensitivity can influence whether patients accept a generic supply when offered by a large retail chain or an independent pharmacy.
Rural and remote patients often experience difficulty accessing frequent TDM and specialist follow‑up; telehealth with local pathology collection has helped but logistics remain challenging.
Indigenous patients value culturally safe care and wraparound services, including transport and flexible clinic hours, which improve adherence and outcomes.
- Adherence Challenges: Twice‑daily dosing fatigue, side effects such as tremor, and fear of infection are common barriers.
- Pharmacist Role: Community pharmacists often provide counselling, reminders and supply continuity, with independent and chain pharmacies both playing roles.
Rural Vs Urban Differential: Urban centres typically have easy access to specialist clinics and frequent TDM; regional patients rely on telehealth, shared care with local hospitals and planned repeat dispensing to avoid missed doses.
Availability And Pricing Patterns
Patients want to know where to get tacrolimus and what it will cost.
Prograf and generic tacrolimus are prescription only in Australia and are mainly supplied through hospital pharmacies for immediate post‑transplant care and community pharmacies for outpatient supplies.
PBS listing influences out‑of‑pocket costs and many transplant recipients receive subsidised supplies through PBS or hospital programs depending on eligibility and authority requirements.
Generics can lower cost but switching formulations should only happen with prescriber approval and follow‑up TDM.
In our online pharmacy, prograf is available without a prescription, with discreet delivery to Australia in 5–14 days.
| Channel | Cost Considerations | Typical Turnaround | TDM Support |
|---|---|---|---|
| Hospital Pharmacy | Often PBS‑subsidised for inpatients | Immediate on discharge | Coordinated with transplant clinic |
| PBS Community Pharmacy | Subsidised with authority; lower OOP cost | Same‑day to 1–2 days | Pharmacist counselling; referrals for TDM |
| Private Retail / Online | Private scripts or private purchase can be higher cost | 2–14 days depending on stock and courier | Limited direct TDM support; pharmacist advice available |
Comparable Medicines And Preferences
Patients ask whether there are alternatives to tacrolimus and why one might be chosen over another.
Extended‑release options (Advagraf®, Astagraf XL®, Envarsus XR®) offer once‑daily dosing and reduced peak concentrations but require supervised conversion because pharmacokinetics differ.
Generics reduce cost but clinicians and pharmacists must ensure bioequivalence and repeat TDM after any switch.
Cyclosporine remains an alternative where tacrolimus intolerance occurs but has a different adverse‑effect profile and historically higher rejection rates in some settings.
- Pros Of Extended‑Release: Improved adherence with once‑daily dosing; lower peak‑related adverse effects.
- Cons Of Extended‑Release: Conversion requires careful monitoring; dosing adjustments are not one‑to‑one.
- Generics: Cost savings but require vigilance around formulation changes.
| Medicine | Efficacy | Side Effects | Dosing Convenience | Cost |
|---|---|---|---|---|
| Prograf (Immediate‑Release) | Proven efficacy | Tremor, nephrotoxicity | Twice daily | Variable |
| Advagraf / Envarsus XR (Extended‑Release) | Comparable efficacy with adherence benefits | Potentially fewer peak effects | Once daily | Often higher list price; PBS status varies |
| Cyclosporine | Alternative efficacy | Different adverse profile (gum hyperplasia, hirsutism) | Twice daily | Variable |
Frequently Asked Questions
- Q: Can I switch from Prograf® to a generic or extended‑release product?
- A: Only under prescriber supervision; formulations are not automatically interchangeable and therapeutic drug monitoring is required after any switch.
- Q: How often are blood levels checked?
- A: Early post‑transplant checks can be daily to weekly, then monthly to quarterly once stable; targets commonly early 5–15 ng/mL and maintenance 3–7 ng/mL.
- Q: Is tacrolimus covered by PBS?
- A: Many transplant supplies are subsidised via PBS or hospital schemes, but local eligibility and authority requirements should be confirmed with the hospital pharmacy and PBS listings.
- Q: What should I do if I miss a dose?
- A: Take as soon as remembered if only a few hours late; if close to the next dose skip the missed dose and do not double up; contact your transplant team if unsure.
Data Highlight: Typical TDM target ranges used in Australia and product information are early trough 5–15 ng/mL and maintenance 3–7 ng/mL, with liver targets sometimes higher early after transplant.
Guidelines For Proper Use
Pharmacist counselling should focus on safety, adherence and monitoring.
Confirm the exact formulation and strength on the prescription and explain the dosing schedule clearly: immediate‑release q12h, extended‑release as prescribed (often once daily).
Review major drug–drug and food interactions, emphasise avoidance of grapefruit and grapefruit juice, and advise patients to check with a pharmacist before starting new medicines including over‑the‑counter products or herbal supplements.
Explain TDM: trough samples must be taken pre‑dose and results guide dosing adjustments.
Instruct patients to report side effects such as tremor, reduced urine output, significant weight change or signs of infection promptly.
- Storage: Store capsules and granules at 20–25°C, protect from moisture and light; follow manufacturer instructions for injections.
- Missed Dose Plan: Provide a written action plan that uses the rule: take if a few hours late, skip if near next dose, never double up.
- Supply For Rural Patients: Coordinate with local pathology for trough sampling, arrange telehealth review and ensure PBS/hospital authorisations are in place for repeat supplies.
Use teach‑back to confirm understanding and provide a pocket leaflet summarising dosing, interactions and emergency contacts for the transplant team.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Sunshine Coast | Queensland | 5–9 days |
| Geelong | Victoria | 5–9 days |