
Mysoline
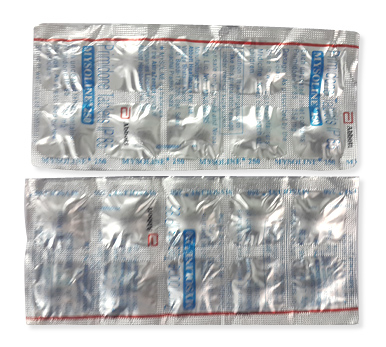
Mysoline
- Mysoline (primidone) is generally a prescription-only medicine in most countries; availability varies by jurisdiction and pharmacy — while some pharmacies may supply Mysoline without a prescription or receipt, this is not standard practice, may be unlawful, and you should check local regulations and seek medical advice before obtaining it.
- Mysoline (primidone) is used mainly to treat epilepsy (generalised and focal seizures) and is also used off‑label for essential tremor; it is a barbiturate‑type antiepileptic that is partly metabolised to phenobarbital and acts by enhancing GABAergic inhibition and depressing neuronal excitability.
- Typical dosing starts at about 100–125 mg at bedtime for adults with gradual titration; maintenance is commonly 250 mg three or four times daily for adults (children and elderly require lower, weight‑adjusted or more cautious dosing; essential tremor is often titrated toward 250 mg twice daily).
- Mysoline is administered orally, most commonly as tablets (available in 100 mg and 250 mg strengths); formulations such as suspensions are occasionally available in some markets.
- Sedative effects may begin within 30–60 minutes of an oral dose, though anticonvulsant benefits may require titration and may take several hours to days to become fully apparent.
- The primary duration of action for primidone is typically around 6–12 hours, but effects may be prolonged by active metabolites (notably phenobarbital), which can extend clinically relevant action for up to 24–48 hours in some patients.
- Do not drink alcohol while taking Mysoline — alcohol markedly increases central nervous system depression, drowsiness and risk of falls or respiratory depression.
- The most common side effects are drowsiness and dizziness, with other frequent effects including ataxia, nausea, vomiting and nystagmus; mood changes or agitation can occur, particularly in children.
- Would you like to try “mysoline” without a prescription?

Latest Research Highlights — Australian & Global
Basic Mysoline Information
- INN (International Nonproprietary Name): Primidone.
- Brand Names Available In Australia: not specified.
- ATC Code: N03AA03.
- Forms & Dosages: Tablets 100 mg and 250 mg; occasional suspensions or syrups not widely available.
- Manufacturers In Australia: not specified; international licensors and suppliers include Bausch Health, Global Pharma Tek, Shandong Octagon Chemicals and Nantong Jinghua.
- Registration Status In Australia: not specified; refer to local national health agency for current registration and subsidy details.
- OTC / Rx Classification: Prescription-only (Rx) in major markets.
What does the recent literature say about primidone and safety?
Recent Australian and international literature from 2022–2025 has emphasised tolerability and real‑world outcomes with primidone rather than new efficacy claims.
Older randomised controlled trials and meta‑analyses continue to support primidone’s efficacy for generalised tonic‑clonic seizures and as one of the first‑line options for essential tremor.
Contemporary work focuses on comparative adverse‑effect burden, especially sedation and ataxia, and on dose‑titration strategies designed to reduce early discontinuation.
Australian pharmacoepidemiology reports, including TGA adverse‑drug reaction summaries and state hospital datasets, flag increased falls and sedation in older adults taking barbiturate derivatives.
Studies in Indigenous and remote cohorts highlight access and monitoring gaps more than novel efficacy data.
Global pharmacovigilance data reiterate pregnancy risks such as neonatal bleeding and withdrawal, and recommend monitoring CBC and LFTs during long‑term therapy.
Primidone is the International Nonproprietary Name, and Mysoline appears as a 250 mg branded tablet produced by Bausch Health.
The ATC classification remains N03AA03 as a barbituric acid derivative antiepileptic.
| Indication | Effectiveness | Common AEs | Level Of Evidence |
|---|---|---|---|
| Generalised Tonic‑Clonic Seizures | Established efficacy in older RCTs and clinical series | Drowsiness, ataxia, nystagmus | High (historical RCTs, meta‑analyses) |
| Essential Tremor (Off‑Label) | Good clinical response when propranolol unsuitable or ineffective | Sedation, dizziness, coordination problems | Moderate (clinical trials and long clinical experience) |
| Partial Seizures (Adjunct) | Used adjunctively with benefit in some patients | CNS depression, GI upset | Moderate to Low (older trials, observational) |
Data Highlights: TGA adverse‑event reports and PBS/state signals emphasise falls and sedation in older adults and the need for pregnancy counselling and perinatal planning.
Clinical Effectiveness In Australia
How well does primidone work in everyday Australian practice?
Clinical use in Australia largely mirrors older international practice with primidone effective for specific seizure types and commonly used off‑label for essential tremor.
TGA adverse‑event monitoring and state hospital audits show good efficacy once therapeutic dosing is achieved, but discontinuation rates are higher than with many newer antiepileptics because of CNS side effects.
Typical adult initiation starts at 100–125 mg at bedtime with maintenance often 250 mg three or four times daily for epilepsy.
For essential tremor regimens, clinicians commonly titrate toward 250 mg twice daily as tolerated.
PBS status varies by formulation and state formulary, so prescribers and pharmacists should check the PBS Schedule for current subsidy information before advising patients.
Shared decision‑making is central in Australian practice, and clinicians must weigh seizure control against sedation risk especially for patients who drive or work in safety‑critical roles.
- Outcome Measures: seizure frequency reduction, seizure‑free intervals, tremor rating scales, patient‑reported sedation scores.
- Monitoring Outcomes: retention rates, adverse‑event reports, falls, and functional status in older adults.
| Measure | Older AEDs (Primidone/Phenobarbital) | Newer AEDs |
|---|---|---|
| Retention Rate | Lower due to sedation/ataxia | Higher generally |
| Side‑Effect Rates | Higher CNS adverse events | Lower CNS burden for many agents |
Indications And Expanded Uses
What is primidone approved for and when is it used off‑label?
Primary indications internationally include epilepsy and common off‑label use for essential tremor.
In Australian clinical practice primidone is prescribed for generalised tonic–clonic seizures and as an adjunct for partial seizures.
Clinicians also commonly prescribe primidone off‑label for essential tremor when propranolol is unsuitable or ineffective.
TGA registration status and product information can vary by brand and pack, so prescribers should check local product information before prescribing.
- Approved
- Epilepsy (multiple seizure types as per historical approvals).
- Off‑Label
- Essential tremor, titrated to clinical response, often toward 250 mg twice daily.
Prescriber Checklist:
- Confirm indication and seizure type before starting primidone.
- Document prior treatments tried, including propranolol for tremor.
- Arrange baseline monitoring (CBC, LFTs) if long‑term therapy planned.
Composition And Brand Landscape
What is in the tablet and who makes it?
The active ingredient is primidone, the International Nonproprietary Name for this medicine.
International brand names include Mysoline, usually presented as 250 mg tablets, plus several international generics such as Primaclone, Lepimidin and Liskantin.
In many markets tablets are available in 100 mg and 250 mg strengths and packaging frequently comes as a bottle of 100 tablets.
Bausch Health is listed as the licensor for Mysoline in the United States and several API suppliers are documented in Asia.
| Form | Available Dosages | Packaging Example | Likely Australian Equivalent |
|---|---|---|---|
| Tablet | 100 mg, 250 mg | Bottle of 100 tablets | Generic primidone tablets (labelled primidone) |
| Oral Liquid | Occasional formulations | Not widely available | Not commonly stocked |
Noted global suppliers and manufacturers in the raw data include Bausch Health, Global Pharma Tek (India), Shandong Octagon Chemicals (China) and Nantong Jinghua (China).
Contraindications And Special Precautions
Who should not take primidone and who needs extra caution?
- Absolute Contraindications: Hypersensitivity to primidone, phenobarbital or other barbiturates, and acute intermittent porphyria.
- Use With Caution: Severe hepatic or renal impairment, significant respiratory depression, frailty in elderly patients, and pregnancy and breastfeeding.
Australian practice must pay attention to high‑risk groups such as older adults at increased fall risk and Aboriginal and Torres Strait Islander people who may face access and monitoring barriers.
Pregnancy warnings are significant: primidone has been associated with neonatal bleeding and withdrawal, so discuss pregnancy planning with obstetric and neurology teams.
| Risk Group | Precaution |
|---|---|
| Elderly | Start low, monitor for falls and sedation |
| Pregnant People | Discuss risks, plan folate and perinatal monitoring |
| Respiratory Compromise | Avoid or monitor closely due to respiratory depression risk |
Regulatory Note: Pregnancy warnings and monitoring requirements are reflected in regulatory safety advice and pharmacovigilance summaries.
Dosage Guidelines
How should primidone be started and titrated safely?
Adults commonly initiate primidone at 100–125 mg at bedtime then titrate upward based on response and tolerability.
Maintenance for epilepsy is often 250 mg three or four times daily, while essential tremor regimens usually target about 250 mg twice daily.
Children start at lower doses, often around 50 mg per day divided, and titrate by weight and response.
Elderly patients require lower starting doses and slower titration due to increased sensitivity and fall risk.
In renal or hepatic impairment reduce dose or titrate cautiously, monitoring clinically and with labs as indicated.
Treatment is usually long term and abrupt withdrawal risks seizure exacerbation, so tapering is required when stopping.
| Population | Starting Dose | Target/Maintenance | Titration Steps |
|---|---|---|---|
| Adults (Epilepsy) | 100–125 mg at bedtime | 250 mg three or four times daily | Increase every few days as tolerated |
| Adults (Tremor) | Start low, bedtime dose | ~250 mg twice daily | Slow upward titration to effect |
| Children | ~50 mg/day divided | Weight‑adjusted maintenance | Increase cautiously by weight |
| Elderly | Lower than adult start | Individualised | Very slow titration with monitoring |
Monitoring checklist during titration: watch for CNS effects, check baseline and periodic LFTs and CBC, assess adherence and fall risk.
Storage advice: keep tablets at room temperature 20–25°C in a tightly closed container away from moisture.
Interactions Overview
Which medicines and substances interact with primidone?
Primidone has broad interaction potential via additive CNS depression and via hepatic enzyme effects from its barbiturate activity.
Clinically relevant interactions include increased sedation with alcohol and other CNS depressants such as benzodiazepines and opioids.
Primidone may have pharmacokinetic interactions with enzyme‑inducing antiepileptics like phenytoin and carbamazepine.
There are possible effects on anticoagulant activity and a pregnancy‑related concern for neonatal bleeding.
| Drug/Class | Expected Effect | Management |
|---|---|---|
| Alcohol, Benzodiazepines, Opioids | Additive CNS depression | Avoid combination; counsel patient |
| Phenytoin, Carbamazepine | Pharmacokinetic interactions; altered levels | Monitor levels and clinical response |
| Anticoagulants | Potential interaction; altered bleeding risk | Monitor INR/PT if applicable |
Counselling points for pharmacists: reconcile medicines at each dispensing, warn about alcohol, and check for CNS depressant co‑prescriptions during medication reviews.
Cultural Perceptions And Patient Habits
How do Australian patients view primidone and where do they shop?
Patient behaviour is influenced strongly by price sensitivity and trust in community pharmacists.
Many Australians compare private prices across chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart when choosing generic primidone tablets.
Rural and remote patients can face access and monitoring barriers, with telehealth commonly used for specialist follow‑up.
Aboriginal and Torres Strait Islander communities may express concerns about side effects and face logistical obstacles to regular laboratory monitoring.
Patient forums frequently report early sedation and discontinuation, and pharmacists often help by advising slow titration and side‑effect management.
| Setting | Access Issue |
|---|---|
| Urban | Ready access to pharmacies and lab services |
| Rural/Remote | Longer wait for specialist review and lab monitoring |
Availability And Pricing Patterns
Where can patients get primidone and how much does it cost?
Branded Mysoline is listed in international data but local Australian supply is typically generic primidone tablets.
Retail channels include major pharmacy chains and accredited online pharmacies that accept e‑prescriptions and telehealth scripts.
Check the TGA ARTG and the PBS Schedule for the current listing and subsidy status before advising a patient on cost.
In our online pharmacy, mysoline is available without a prescription, with discreet delivery to Australia in 5-14 days.
| Outlet | Typical Private Price Range | PBS Subsidy Status |
|---|---|---|
| Chemist Warehouse | Varies by brand and pack | Check PBS |
| Priceline | Varies by store | Check PBS |
| TerryWhite Chemmart | Varies by location | Check PBS |
| Accredited Online Pharmacy | Varies; price comparisons recommended | Check PBS |
Packaging examples commonly sold are bottles of 100 tablets in 100 mg or 250 mg strengths.
Pharmacists should have supply contingencies such as switching to a generically equivalent product or ordering from wholesalers when stock shortages occur.
Comparable Medicines And Preferences
What are the alternatives and how do they compare?
Alternatives for seizures include phenobarbital, phenytoin, carbamazepine and valproic acid, with choice guided by seizure type and comorbidity.
For essential tremor propranolol is often first‑line, with gabapentin and other antiepileptics as alternatives if beta‑blockers are unsuitable.
Pros of primidone include established efficacy, low cost where generics are available, and a long clinical history.
Cons include a higher risk of sedation and ataxia, meaningful teratogenic and neonatal risks, and a relatively broad interaction profile.
- Pros: Effective, low cost (generics), long clinical experience.
- Cons: Sedation/ataxia, pregnancy risks, polypharmacy concerns.
| Drug | Indication | Main AEs | PBS Status |
|---|---|---|---|
| Primidone | Epilepsy, essential tremor (off‑label) | Sedation, ataxia | Varies; check PBS |
| Propranolol | Essential tremor | Bradycardia, fatigue | Listed for some indications; check PBS |
| Valproic Acid | Broad spectrum epilepsy | Weight gain, teratogenicity | Listed; check PBS and pregnancy guidance |
FAQ — Common Patient Questions
Q: Is Mysoline available in Australia and on the PBS?
A: Mysoline is an international brand listed in the raw data, but in Australia patients usually receive primidone generics; check the PBS and the TGA ARTG for current listings and subsidy details.
Q: Will primidone make me drowsy?
A: Yes, drowsiness and ataxia are common, so start low and titrate slowly and avoid driving until you know how it affects you.
Q: Can I drink alcohol while on primidone?
A: Avoid alcohol because it increases sedation and fall risk and can worsen side effects.
Q: What if I am pregnant or planning pregnancy?
A: Discuss risks with your obstetric and neurology teams as primidone carries teratogenic and neonatal risks; plan folate supplementation and perinatal monitoring.
For follow‑up, contact your local neurology service or consult TGA and PBS resources for current regulatory details.
Guidelines For Proper Use And Pharmacist Counselling
What should pharmacists tell patients starting primidone?
Confirm the indication and previous treatments tried, for example propranolol for tremor.
Explain the titration schedule clearly and stress the need to start low and increase slowly to reduce early sedation.
Warn strongly about alcohol and other CNS depressants and advise patients not to drive until sedation has settled.
Reinforce storage at room temperature 20–25°C in the original container and out of reach of children.
Monitoring timeline:
- Baseline: CBC, LFTs, renal function, medication reconciliation.
- 1–3 Months: Clinical review for CNS side effects and adherence.
- 6–12 Months: Repeat labs if long‑term therapy; assess falls risk in older patients.
- Annual: Ongoing review, labs as clinically indicated.
Missed dose advice: take when remembered unless close to the next dose and do not double up.
Overdose instructions: seek emergency care for severe CNS depression, ataxia, nystagmus or unconsciousness; supportive treatment is standard and dialysis may be considered in severe cases.
For telehealth or rural dispensing, arrange pharmacist‑led MedsChecks or Home Medicines Reviews to ensure adherence and interaction checks occur despite geographic distance.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Townsville | Queensland (Regional) | 5-9 days |
| Darwin | Northern Territory | 5-9 days |
| Geelong | Victoria (Regional) | 5-9 days |
| Wollongong | New South Wales (Regional) | 5-9 days |
| Ballarat | Victoria (Regional) | 5-9 days |
| Sunshine Coast | Queensland (Regional) | 5-9 days |
| Albury | New South Wales/Victoria (Regional) | 5-9 days |