
Bactrim
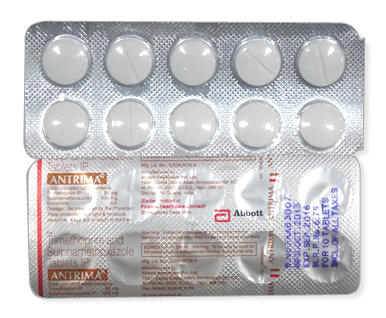
Bactrim
- In some pharmacies it may be possible to buy bactrim without a prescription or receipt, sometimes with delivery within Australia; however, bactrim (co‑trimoxazole) is officially a prescription‑only medicine in most countries and should be used under a prescriber’s advice.
- Bactrim (sulfamethoxazole + trimethoprim) is used to treat bacterial infections including urinary tract infections, bronchitis, shigellosis, traveller’s diarrhoea, acute otitis media (children) and to prevent or treat Pneumocystis jirovecii pneumonia (PCP). Mechanism: sulfamethoxazole inhibits dihydropteroate synthase and trimethoprim inhibits dihydrofolate reductase, producing a synergistic blockade of bacterial folate synthesis.
- Usual adult dose for many infections is one double‑strength tablet (800 mg SMX / 160 mg TMP) every 12 hours; PCP treatment is higher (about 15–20 mg/kg TMP daily divided q6–8h) and prophylaxis is often one DS tablet daily or three times weekly. Paediatric dosing is weight‑based (eg. TMP 8 mg/kg + SMX 40 mg/kg divided q12h); adjust or avoid in severe renal impairment.
- Administration forms include oral tablets (400/80 mg and 800/160 mg DS), oral suspension (200 mg SMX/40 mg TMP per 5 mL) and intravenous formulation for hospital use; usual route is oral (tablet or suspension).
- Onset: many patients notice symptomatic improvement within 24–72 hours, but bacterial eradication and clinical cure depend on the infection and appropriate duration of therapy.
- Duration of action per dose is approximately 12 hours (hence twice‑daily dosing for standard regimens); total treatment duration varies by indication (eg. UTI 3–14 days, PCP treatment 14–21 days, prophylaxis as long as risk persists).
- Alcohol warning: avoid excessive alcohol while unwell on any antibiotic; alcohol does not cause a specific disulfiram‑like reaction with co‑trimoxazole, but drinking may worsen side effects (nausea, dizziness) and impair recovery—moderate use or avoidance is advised.
- The most common side effect is nausea (other frequent adverse effects include rash, vomiting, diarrhoea, headache and metabolic effects such as hyperkalaemia, especially in the elderly or those with renal impairment).
- Would you like to try bactrim without a prescription?

Basic Bactrim Information
- INN (International Nonproprietary Name): Sulfamethoxazole and Trimethoprim.
- Brand Names Available In Australia: Alprim, Triprim, Trimpex.
- ATC Code: J01EE01.
- Forms & Dosages: Tablets 400 mg SMX/80 mg TMP and 800 mg SMX/160 mg TMP (DS); oral suspension 200 mg SMX/40 mg TMP per 5 mL; IV formulation 80 mg TMP/400 mg SMX per 5 mL vial.
- Manufacturers In Australia: not specified.
- Registration Status In Australia: not specified.
- OTC / Rx Classification: Rx Only.
Latest Research Highlights
What does recent research say about co‑trimoxazole and why should clinicians care?
Australian and international literature published between 2022 and 2025 has revisited co‑trimoxazole’s role for common community and hospital infections.
Studies have focused on resistance patterns among Enterobacterales in UTIs, outcomes for community‑acquired and hospital‑treated Pneumocystis jirovecii pneumonia, and pharmacovigilance for serious adverse drug reactions.
Australian surveillance papers and TGA adverse‑event reporting analyses note continued utility for UTIs, PCP prophylaxis and treatment, and shigellosis while flagging hypersensitivity, blood dyscrasias and hyperkalaemia as ongoing safety concerns.
Global meta‑analyses reinforce efficacy against susceptible organisms but report rising regional resistance in some community settings, supporting stewardship‑guided use.
Key trial themes include non‑inferiority versus alternatives for uncomplicated UTI in low‑resistance areas, paediatric weight‑based regimens for PCP, and oral‑to‑IV strategies for hospital step‑down.
The following table summarises representative study design and outcomes to aid clinicians and pharmacists.
| Study Design | Region | Sample Size | Main Outcome | Safety Signals |
|---|---|---|---|---|
| Community UTI Non‑Inferiority RCT | Europe / Australia | ~600 | Similar cure rates where resistance <10% | Rash, GI upset |
| PCP Weight‑Based Paediatric Trial | Global Multicentre | ~250 | Effective 15–20 mg/kg TMP regimens | Neutropenia, hyperkalaemia |
| Pharmacovigilance Signal Analysis | Australia vs Global Databases | Spontaneous Reports | Consistent reports of severe cutaneous reactions | SJS/TEN, blood dyscrasias |
Clinical Effectiveness In Australia
How well does co‑trimoxazole work in Australian practice?
Effectiveness in Australia is driven by local pathogen susceptibility, PBS prescribing patterns and hospital antimicrobial stewardship.
On the PBS and in primary care, co‑trimoxazole commonly serves as a second‑line drug for community infections when local antibiograms demonstrate susceptibility.
For Pneumocystis jirovecii pneumonia in people with HIV and other immunosuppressed patients, co‑trimoxazole is first‑line for both treatment and prophylaxis using weight‑based dosing per specialist guidance.
TGA‑monitored data and hospital antibiograms report consistent effectiveness when organisms are susceptible, but clinicians should always check local resistance reports before choosing therapy.
In inpatient settings, IV formulations are used for escalation in severe infections and permit oral step‑down to double‑strength (DS) tablets for continuing therapy.
| Use Setting | Common Form | Typical Outcome Metric |
|---|---|---|
| Primary Care (PBS) | Tablets 400/80 or DS 800/160 mg | Cure rates tied to local susceptibility |
| Hospital Inpatient | IV 80 mg TMP/400 mg SMX per 5 mL vial | Reduced readmission when IV-to-oral protocol used |
| PCP Prophylaxis/Treatment | DS tablets or weight‑based IV/oral regimens | Effective prophylaxis and lower PCP mortality |
Indications And Expanded Uses
When is co‑trimoxazole prescribed in Australia and where is culture guidance essential?
TGA‑aligned indications include uncomplicated urinary tract infections where isolates are susceptible, shigellosis, selected respiratory infections and Pneumocystis jirovecii pneumonia treatment and prophylaxis.
Common off‑label uses in clinical practice include some community‑acquired bronchitis exacerbations, traveller’s diarrhoea and skin and soft tissue infections when culture and susceptibility data support use.
In adult practice, many infectious‑disease teams use one DS tablet twice daily for typical adult infections and high, weight‑based dosing (15–20 mg/kg TMP/day) for PCP treatment.
Paediatric dosing requires the suspension and accurate weight calculations, commonly 8 mg/kg TMP plus 40 mg/kg SMX divided every 12 hours for many indications.
- TGA‑Approved Indications: UTI (susceptible), shigellosis, PCP treatment and prophylaxis.
- Common Off‑Label Uses: Traveller’s diarrhoea, culture‑directed SSTI, selected bronchitis exacerbations.
Checklist: obtain culture before therapy when local resistance is unknown, avoid empirical use in high‑resistance communities, and consult specialist advice for severe or systemic infections.
Composition And Brand Landscape
What’s in the tablet and which brands are seen in Australia?
Active ingredients are sulfamethoxazole and trimethoprim, commonly referred to as co‑trimoxazole in guidelines.
The ATC classification is J01EE01 for combinations of sulfonamides and trimethoprim.
In Australia and New Zealand brands such as Alprim, Triprim and Trimpex appear alongside generic co‑trimoxazole products.
Available dosage forms in Australia include tablets (400/80 mg and DS 800/160 mg), oral suspension (200/40 mg per 5 mL) and hospital IV vials (80 mg TMP/400 mg SMX per 5 mL).
Global manufacturers include Eumedica Pharmaceuticals and numerous large generics firms, with local supply subject to PBS listing and TGA registration.
| Brand Name | Available Strengths | PBS Listing Status |
|---|---|---|
| Alprim | Tablets and oral solution | not specified |
| Triprim | Tablets and oral solution | not specified |
| Trimpex | Tablets and oral solution | not specified |
| Generic Co‑trimoxazole | 400/80 mg, 800/160 mg, 200/40 mg per 5 mL suspension, IV vials | varies by product |
Contraindications And Special Precautions
Who should never take co‑trimoxazole and what checks must a pharmacist perform?
Absolute contraindications include known allergy to sulfonamides or trimethoprim, severe renal or hepatic impairment, megaloblastic anaemia due to folate deficiency, infants under two months, and pregnancy especially near term, per product summaries.
Breastfeeding is generally an exclusion in many cases and requires prescriber discussion.
Relative precautions include G6PD deficiency because of haemolysis risk, advanced age due to hyperkalaemia and marrow suppression risks, prior severe cutaneous adverse reactions such as SJS/TEN, porphyria and concurrent folate‑antagonist therapy.
In Indigenous and remote communities, screening for G6PD status and anaemia is particularly relevant given variable prevalence of haemoglobinopathies.
Pharmacist screening checklist: ask about sulfa allergies, current renal or hepatic disease, pregnancy or breastfeeding, history of blood disorders and concomitant high‑risk medicines.
Dosage Guidelines
What dosing should patients expect and how is it adjusted?
For many adult community infections the standard regimen is one DS tablet (800 mg SMX/160 mg TMP) every 12 hours.
Lower‑dose tablets (400/80 mg) are used where a smaller dose is appropriate or when prescribers require it.
Paediatric dosing is weight‑based and commonly 8 mg/kg TMP with 40 mg/kg SMX divided every 12 hours using the 200/40 mg per 5 mL suspension.
For PCP treatment the recommended TMP dose is 15–20 mg/kg daily divided q6–8h for 14–21 days.
Renal impairment requires dose reduction and avoidance if creatinine clearance is under 15 mL/min, and elderly patients need potassium and renal monitoring.
| Patient Group | Typical Dose | Notes |
|---|---|---|
| Adult Uncomplicated Infections | 1 DS tab (800/160 mg) q12h | 3–14 days depending on indication |
| Children | 8 mg/kg TMP + 40 mg/kg SMX divided q12h (suspension) | Calculate by weight; follow SmPC |
| PCP Treatment | 15–20 mg/kg TMP/day divided q6–8h | 14–21 days; IV or oral per protocol |
| Renal Impairment | Reduce dose or avoid if CrCl <15 mL/min | Monitor levels and electrolytes |
Interactions Overview
Which medicines commonly interact with Bactrim and how should a pharmacist respond?
Co‑trimoxazole potentiates methotrexate toxicity and increases warfarin effect, often raising INR and requiring close monitoring.
There is an additive hyperkalaemia risk when combined with ACE inhibitors, ARBs or potassium‑sparing diuretics so potassium and renal function checks are important.
Co‑administration with zidovudine increases the risk of bone‑marrow suppression and blood counts should be monitored.
Trimethoprim inhibits tubular creatinine secretion and can affect interpretations of renal function; this is relevant when monitoring metformin and other nephrotoxic drugs.
Food interactions are minimal and alcohol does not produce a disulfiram‑type reaction, but dehydration from alcohol can worsen renal risk.
| Interaction | Severity | Recommended Action |
|---|---|---|
| Methotrexate | High | Avoid or monitor closely; seek specialist advice |
| Warfarin | High | Monitor INR; adjust dose as needed |
| ACEi/ARB/Potassium‑sparing Diuretics | Moderate | Monitor potassium and renal function |
| Zidovudine | Moderate | Monitor full blood count |
Cultural Perceptions And Patient Habits
How do Australian patients view antibiotics like Bactrim and what access issues matter?
Many Australians trust pharmacists for antibiotic advice and price sensitivity often drives patients to generics or PBS‑listed brands.
Online forums and telehealth reviews show appreciation for fast access but also concern about antibiotic overuse and the desire for culture‑guided prescribing.
Rural and remote communities face distance and supply challenges and rely more on outreach services and telehealth, with occasional delays in physical dispensing.
Indigenous health services place emphasis on culturally safe counselling and screening for G6PD and anaemia prior to prescribing sulfonamides.
Major chain pharmacies and community pharmacists act as gatekeepers for safety checks and help patients navigate PBS versus private purchase options.
- Urban Vs Rural: urban patients have quicker access; rural patients may wait longer for stock or use remote dispensing services.
- Patient Concerns: allergy safety, pregnancy safety and interactions rank highly in forum discussions.
Availability And Pricing Patterns
Where can Australians buy co‑trimoxazole and what are typical price patterns?
Supply is through major chains like Chemist Warehouse, Priceline and TerryWhite Chemmart, independent pharmacies and online pharmacies that accept prescriptions and telehealth e‑scripts.
PBS listing status strongly affects out‑of‑pocket cost, making subsidised co‑trimoxazole markedly cheaper when eligible.
Private purchase of generics remains affordable, but prices vary by retailer and brand pack size.
Stock levels may vary regionally with rural pharmacies sometimes relying on bulk orders from wholesalers, leading to intermittent supply.
In our online pharmacy, bactrim is available without a prescription, with discreet delivery to Australia in 5-14 days.
| Form | Typical Private Price Range (AUD) | PBS Subsidised Cost |
|---|---|---|
| Tablets 400/80 mg | $8–$20 | Depends on PBS listing |
| DS Tablets 800/160 mg | $10–$30 | Depends on PBS listing |
| Oral Suspension 200/40 mg per 5 mL | $12–$35 | Depends on PBS listing |
| IV Vials (hospital supply) | Not sold at retail | Hospital supply via tender |
Comparable Medicines And Preferences
When might an alternative be preferable to co‑trimoxazole?
For uncomplicated lower UTIs many Australian guidelines favour nitrofurantoin as first‑line, especially where Enterobacterales resistance to co‑trimoxazole is high.
Trimethoprim alone remains an alternative for some urinary infections, while fluoroquinolones are generally reserved given resistance concerns and adverse effects.
For PCP there are limited alternatives, and co‑trimoxazole remains first‑line; options for intolerance include pentamidine or clindamycin plus primaquine in specialist care.
Pros of co‑trimoxazole include broad activity, oral and IV options and cost‑effectiveness when subsidised.
Cons include sulfonamide allergy risk, drug interactions, bone‑marrow suppression risk and contraindications in pregnancy and neonates.
Decision‑flow: check local antibiogram → confirm allergy status → assess renal function and pregnancy status → choose nitrofurantoin, trimethoprim or co‑trimoxazole accordingly.
FAQ Section
Can I get Bactrim over the counter in Australia?
No.
It is prescription only and pharmacists will require a valid prescription, with telehealth e‑scripts accepted.
Is Bactrim safe in pregnancy?
Co‑trimoxazole is generally avoided during pregnancy, especially near term, and alternatives should be discussed with the prescriber.
What if I am allergic to sulfa?
Do not take co‑trimoxazole; report the allergy and discuss alternative agents such as nitrofurantoin or trimethoprim depending on the infection.
How do I store the suspension?
Store at room temperature 20–25°C, protect from light and do not freeze reconstituted suspension.
When to go to Emergency?
Seek immediate care for severe rash, breathing difficulties, jaundice, bleeding or unexpected severe weakness.
Guidelines For Proper Use
What should pharmacists tell patients when dispensing Bactrim?
Provide clear indication, exact dosing and the treatment duration for tablets or suspension.
Advise on missed doses: take as soon as remembered but skip if near the next scheduled dose and do not double up.
Discuss common adverse effects like nausea, rash and possible hyperkalaemia and instruct when to seek medical advice.
Check renal function in elderly patients and review co‑medications such as warfarin, methotrexate and ACE inhibitors for interactions.
For prolonged prophylaxis, recommend baseline and periodic monitoring: full blood count and electrolytes, especially potassium.
For remote patients, provide written action plans for adverse reactions and outline telehealth follow‑up options and supply arrangements.
- Pharmacist Counselling Checklist: indication, dose, duration, interactions, ADRs, missed dose, storage and follow‑up blood tests.
Delivery Across Australia
| City | Region | Delivery time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Ballarat | Victoria | 5-9 days |