
Xifaxan
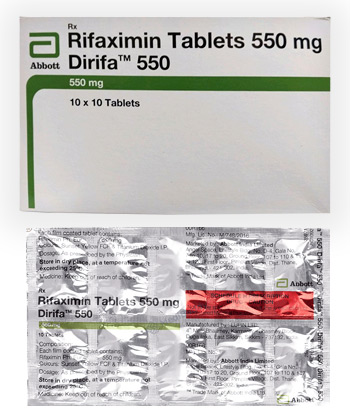
Xifaxan
- In our pharmacy, you can buy xifaxan without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging; note that in many countries Xifaxan (rifaximin) is formally prescription‑only and local regulations vary.
- Xifaxan (rifaximin) is used to treat traveller’s diarrhoea caused by E. coli, to relieve symptoms of IBS‑D (irritable bowel syndrome with diarrhoea) and to prevent recurrent episodes of hepatic encephalopathy. It is a non‑systemic rifamycin antibiotic that acts locally in the gut by inhibiting bacterial RNA synthesis (binding the β‑subunit of DNA‑dependent RNA polymerase).
- Usual doses: traveller’s diarrhoea — 200 mg orally three times daily for 3 days; IBS‑D — 550 mg orally three times daily for 14 days (repeat courses may be used for recurrent symptoms); hepatic encephalopathy — 550 mg orally twice daily as maintenance. Paediatric use is generally from age ≥12 years for some indications; safety in younger children is not established.
- Form of administration: oral tablets (200 mg and 550 mg); an oral suspension (100 mg/5 mL) is available in some countries but not universally.
- Onset time: symptom improvement for traveller’s diarrhoea is often seen within 24–72 hours; for IBS‑D some patients notice relief within days but may take up to a week or more; benefits for hepatic encephalopathy are observed over weeks with ongoing therapy.
- Duration of action: the clinical course determines duration — traveller’s diarrhoea treatment is 3 days, IBS‑D courses are 14 days (symptom relief may persist for weeks), and hepatic encephalopathy requires chronic/maintenance dosing. The drug exerts local gut activity while dosing continues and has negligible systemic half‑life.
- Alcohol warning: there is no specific disulfiram‑type interaction with alcohol, but avoid excessive alcohol intake — especially if you have liver disease or hepatic encephalopathy, as alcohol can worsen liver function and neurological symptoms.
- The most common side effects are gastrointestinal: nausea, constipation, abdominal pain, flatulence and bloating; other reported effects include headache, dizziness and rare hypersensitivity or skin rash.
- Would you like to try xifaxan without a prescription?
Basic Xifaxan Information
- INN (International Nonproprietary Name): Rifaximin
- Brand Names Available In Australia: not specified
- ATC Code: A07AA11
- Forms & Dosages: Oral tablet 200mg, 550mg; oral suspension 100mg/5mL (oral suspension not available in all regions)
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription-only (Rx) in major markets; local status should be checked with the ARTG/PBS
Latest Research Highlights
Clinicians and patients ask: does rifaximin really work for IBS‑D, hepatic encephalopathy and travel diarrhoea?
Randomised controlled trials show benefit for IBS‑D using a 14‑day course of 550 mg three times daily, with symptom reduction for many patients and modest relapse rates after treatment cessation.
Maintenance trials in hepatic encephalopathy report benefit with chronic dosing of 550 mg twice daily, reducing recurrence of overt encephalopathy episodes in studied cohorts.
For traveller’s diarrhoea caused by non‑invasive Escherichia coli, short courses of 200 mg three times daily for three days were favoured in trials versus placebo or symptomatic therapy.
Safety datasets consistently report mainly gastrointestinal adverse events such as nausea and constipation, occasional headache and rare hypersensitivity reactions.
Because rifaximin is minimally absorbed, systemic adverse events are uncommon.
| Indication | Typical Dose | Primary Outcome (Trial) | NNT / RRR | Common Adverse Events |
|---|---|---|---|---|
| IBS‑D | 550 mg TID × 14 days | Symptom reduction (global and stool consistency) | not specified | Nausea, constipation, abdominal pain |
| Hepatic Encephalopathy | 550 mg BID, chronic | Lower recurrence of overt encephalopathy | not specified | GI upset, rare rash |
| Traveller’s Diarrhoea | 200 mg TID × 3 days | Faster clinical cure for non‑invasive E. coli | not specified | Nausea, dizziness |
Key research gaps remain: long‑term microbiome impact, outpatient resistance surveillance and Australian post‑market reports through the TGA and PBS data streams are limited or not publicly comprehensive.
Clinicians should consult recent meta‑analyses and TGA safety notices for updates when making prescribing decisions.
Clinical Effectiveness In Australia
What should Australian clinicians expect from rifaximin in routine practice?
Local randomised trial data are limited, so Australian practice mainly extrapolates from international RCTs and registries for IBS‑D, hepatic encephalopathy and traveller’s diarrhoea.
TGA listing and PBS coverage must be checked via the Australian Register of Therapeutic Goods (ARTG) and the PBS eLookup before relying on subsidised access.
In real‑world Australian use, gastroenterologists and hepatologists commonly prescribe rifaximin for IBS‑D and maintenance of hepatic encephalopathy where clinically appropriate, with private prescriptions used if PBS coverage is absent.
TGA adverse event reports in Australia mirror international safety profiles: mainly GI upset and rare dermatologic hypersensitivity; clinicians should be alert for C. difficile when any antibiotic is used.
| Clinical Endpoint | Typical Effect Size | Monitoring Needs |
|---|---|---|
| Stool Frequency/Consistency (IBS‑D) | Symptom reduction reported in RCTs | Review symptoms at 2–6 weeks; consider retreatment plan |
| Encephalopathy Episodes (HE) | Reduced recurrence in maintenance trials | Coordinate with hepatology; monitor mental status and liver tests |
| Traveller’s Diarrhoea Resolution | Faster clinical cure for non‑invasive E. coli | Assess for systemic features; advise stop and seek care if fever/blood |
In rural and remote settings clinicians often monitor hepatic function more closely due to limited acute services and higher thresholds for hospital transfer.
Where available, state health registries or hospital readmission data can help quantify rifaximin’s effect on HE admissions and service planning.
Indications And Expanded Uses
Patients typically ask: what is rifaximin approved for, and when is it used off‑label?
Regulatory and trial‑based primary indications include traveller’s diarrhoea due to non‑invasive E. coli (200 mg TID for 3 days), IBS‑D symptom relief (550 mg TID for 14 days) and maintenance therapy for hepatic encephalopathy (550 mg BID chronically).
Off‑label or expanded uses encountered in Australian practice include adjunctive therapy for small intestinal bacterial overgrowth (SIBO) and carefully selected chronic diarrhoeal syndromes.
Rifaximin is contraindicated for febrile or bloody diarrhoea, where systemic antibiotics and further investigation are required.
| Indication | Recommended Regimen | Evidence Grade | PBS / TGA Note |
|---|---|---|---|
| Traveller’s Diarrhoea | 200 mg TID × 3 days | RCTs / clinical trials | Check ARTG / PBS status |
| IBS‑D | 550 mg TID × 14 days | RCTs / Meta‑analyses | Often private prescription if not PBS‑listed |
| Hepatic Encephalopathy | 550 mg BID, chronic | Maintenance RCTs | Coordinate with hepatology; check subsidy rules |
Prescribing teams should use an indication checklist before dispensing: confirm symptom profile, rule out febrile/bloody diarrhoea, consider stool testing where appropriate, and document informed consent for off‑label uses.
Composition And Brand Landscape
Pharmacists and prescribers want clarity on brands, strengths and supply.
The active ingredient is rifaximin (INN), classified under ATC A07AA11 as an intestinal antiinfective.
Common dosage forms are oral tablets in 200 mg and 550 mg strengths, with an oral suspension available in some European markets (100 mg/5 mL) but not universally.
Global brand names include Xifaxan (200 mg, 550 mg tablets) and Normix (200 mg tablets and a 100 mg/5 mL suspension in some countries), with regional brands such as Flonorm, Rifaxen and Rifaximina in Latin America and Europe.
| Brand | Strength | Form | Availability In Australia |
|---|---|---|---|
| Xifaxan | 200 mg, 550 mg | Tablets | not specified |
| Normix | 200 mg; 100 mg/5 mL suspension | Tablet, Oral Suspension | not specified |
| Flonorm / Rifaxen / Rifaximina | 200 mg, 550 mg (varies) | Tablets / Country Packaging | not specified |
Salix Pharmaceuticals (Bausch Health) is the global/main manufacturer, with regional partners and emerging generics in Asia and Latin America.
Packaging and formulation differences matter for paediatric dosing because oral suspension is not available in all regions.
Contraindications And Special Precautions
Patients frequently want to know who must avoid rifaximin.
Absolute contraindications are hypersensitivity to rifaximin or other rifamycins such as rifampicin, rifabutin or rifapentine.
Rifaximin should not be used for bacterial diarrhoea with fever or bloody stools because systemic therapy and further investigation are generally required.
Use caution in severe hepatic impairment (Child‑Pugh C), where monitoring for encephalopathy and adverse effects is advised.
Prior history of Clostridioides difficile infection is an important caution as any antibiotic can predispose to recurrence.
| Contraindication / Caution | Action |
|---|---|
| Hypersensitivity To Rifaximin Or Rifamycins | Do not prescribe; document allergy; advise alternative |
| Fever Or Bloody Diarrhoea | Avoid rifaximin; investigate and consider systemic antibiotics |
| Severe Hepatic Impairment | Use with caution; monitor closely |
| History Of C. difficile | Exercise caution; advise to report worsening diarrhoea/fever |
High‑risk groups include elderly patients with polypharmacy and people with advanced liver disease, particularly where access to specialist care is limited.
Practical counselling points: watch for dizziness affecting driving or work, avoid unnecessary alcohol if hepatic impairment exists, and report severe GI symptoms immediately.
Dosage Guidelines
Patients often ask exactly how to take rifaximin for their condition.
Standard adult doses are: traveller’s diarrhoea 200 mg three times daily for three days; IBS‑D 550 mg three times daily for 14 days; and hepatic encephalopathy 550 mg twice daily for chronic maintenance.
Paediatric use has been studied in those aged 12 years and older for some indications; safety in younger children is not established.
No dose adjustment is required for renal impairment because rifaximin has minimal systemic absorption.
Severe liver impairment requires caution and closer monitoring rather than a simple dose reduction.
| Indication | Adult Dose | Pediatric Note |
|---|---|---|
| Traveller’s Diarrhoea | 200 mg TID × 3 days | ≥12 years: same as adult |
| IBS‑D | 550 mg TID × 14 days | Not established <18 years |
| Hepatic Encephalopathy | 550 mg BID, chronic | Not indicated in children |
Missed dose advice: take as soon as remembered unless close to next dose; do not double up.
In overdose, treatment is supportive since there is no specific antidote due to low systemic absorption.
For recurrent IBS‑D, specialists may recommend retreatment intervals; pharmacists should flag repeat courses for review.
Interactions Overview
One common question is whether rifaximin interacts with other medicines.
Because rifaximin is poorly absorbed, clinically significant pharmacokinetic interactions are uncommon.
However, cross‑reactivity with other rifamycins is important for allergy and contraindication checks.
Concomitant use with other antibiotics increases the overall risk for Clostridioides difficile infection and should be considered carefully.
| Drug / Food | Interaction Risk | Action |
|---|---|---|
| Rifampicin, Other Rifamycins | Cross‑reactive allergy risk | Contraindicated if allergy present |
| Other Systemic Antibiotics | Increased C. difficile risk | Monitor for severe diarrhoea; avoid unnecessary combination |
| Alcohol | No direct interaction but caution in hepatic impairment | Advise limited alcohol if liver disease present |
Pharmacists should maintain interaction alerts in dispensing software and report new signals via the TGA and local eHealth systems.
Provide printed advice on recognising C. difficile symptoms and when to seek urgent care.
Cultural Perceptions And Patient Habits
Patients often tell pharmacists they want quick relief, clear cost options and reassurance about safety.
Australian patients typically trust the pharmacist for pragmatic advice about gastrointestinal medicines and compare major retail chains for price.
Online forums report many patients experiencing symptom relief for IBS‑D after a 14‑day course, alongside concerns about cost, the need for repeat courses and long‑term effects on gut flora.
Rural and remote patients rely on regional chemists, telehealth prescribers and mail‑order dispensing for access, and community health services or Aboriginal Medical Services often assist with specialist referrals.
For culturally and linguistically diverse communities, provide plain language counselling, involve family or carers where appropriate, and offer interpreter services as needed.
- Pharmacist script: confirm indication, check allergies, outline dosing and side effects.
- Telehealth steps: electronic prescription, discuss supply and mail delivery, follow‑up plan.
- Cultural liaison: engage local AMS or community health worker for complex cases.
Address patient concerns proactively about cost, retreatment and recurrence during counselling.
Availability And Pricing Patterns
How patients pay for rifaximin in Australia depends on ARTG registration and PBS listing.
If rifaximin is not PBS‑listed for a given indication, most prescriptions are private and out‑of‑pocket costs vary by retailer and supply route.
Major retail chains and accredited online pharmacies may stock rifaximin subject to supplier imports and ARTG entries.
Telehealth platforms can issue e‑prescriptions enabling mail delivery to remote areas, which is important for rural access.
| Retailer | Private Price Range | PBS Status | Mail‑Order Availability |
|---|---|---|---|
| Chemist Warehouse | not specified | Check PBS eLookup | Yes — subject to stock |
| Priceline | not specified | Check PBS eLookup | Yes — subject to stock |
| TerryWhite Chemmart | not specified | Check PBS eLookup | Yes — subject to stock |
For clinic stock management in rural clinics, plan for supply lag and consider holding common pack sizes for hepatic encephalopathy maintenance patients.
In our online pharmacy, xifaxan is available without a prescription, with discreet delivery to Australia in 5-14 days.
Where a product is not locally registered or stocked, clinicians can explore special access schemes or hospital pharmacy channels for chronic HE patients.
Comparable Medicines And Preferences
Clinicians weigh alternatives on efficacy, safety, access and cost.
For hepatic encephalopathy, lactulose remains a mainstay and neomycin is sometimes used off‑label as a non‑absorbed alternative to rifaximin.
For traveller’s diarrhoea, systemic agents such as ciprofloxacin or metronidazole may be used depending on suspected pathogens, but they carry systemic side effects and resistance concerns.
For IBS‑D symptom control, agents such as loperamide and eluxadoline are options for symptomatic relief; rifaximin offers a targeted, gut‑directed antibiotic strategy with low absorption.
| Agent | Indication | Relative Efficacy | Main Safety Concerns | PBS Status |
|---|---|---|---|---|
| Rifaximin | IBS‑D, Traveller’s Diarrhoea, HE | Effective in RCTs | GI upset, rare hypersensitivity | Check PBS eLookup |
| Neomycin | HE (off‑label) | Used clinically | Ototoxicity, nephrotoxicity | not specified |
| Ciprofloxacin / Metronidazole | Traveller’s Diarrhoea alternatives | Effective but systemic | Systemic adverse effects, resistance | not specified |
Use a prescriber checklist when switching: confirm indication, review comorbidities (especially liver and renal), and consider local resistance patterns where available.
Frequently Asked Questions
Is rifaximin on the PBS?
PBS listing varies by indication and over time; always check the PBS eLookup and the ARTG for the current subsidy and registration status.
Can I get Xifaxan over the counter?
No; rifaximin is prescription‑only in major markets and requires a clinician’s prescription for supply in pharmacy settings.
Is rifaximin safe in pregnancy or breastfeeding?
Human data are limited; rifaximin should be used in pregnancy or lactation only if the potential benefits justify the potential risks and after specialist advice.
How soon will I feel better for IBS‑D?
Many patients experience improvement during or shortly after a 14‑day 550 mg TID course, but some relapse and may need reassessment or retreatment planning.
What about C. difficile risk?
All antibiotics can predispose to C. difficile; advise patients to report severe diarrhoea, fever or bloody stools immediately and seek urgent care.
Guidelines For Proper Use And Pharmacy Counselling
Pharmacists should check indication, allergies and hepatic history before supplying rifaximin.
Confirm the intended use aligns with trial evidence or documented specialist rationale, especially for off‑label SIBO use.
Advise the patient on the correct regimen according to the indication and provide clear dosing instructions and expected timelines for improvement.
Storage advice: store tablets at 20–25°C, protect from moisture and keep in original packaging.
- Missed Dose: Take as soon as remembered unless it is almost time for the next dose; do not double up.
- Overdose: Provide supportive care; no specific antidote due to low absorption.
- When To Seek Help: Fever, bloody diarrhoea, severe abdominal pain, or worsening mental status for HE patients.
Provide a short printed patient handout that covers indication, dose, expected benefit timeline, common side effects and cost/PBS options.
For hepatic encephalopathy maintenance patients, coordinate with hepatology, community nursing and arrange medication reconciliation to reduce errors in polypharmacy.
Use telehealth and electronic prescription workflows for remote patients and plan for logistics if local stock is limited.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Sunshine Coast | Queensland | 5-7 days |
| Geelong | Victoria | 5-7 days |
| Wollongong | New South Wales | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |