
Dalacin C
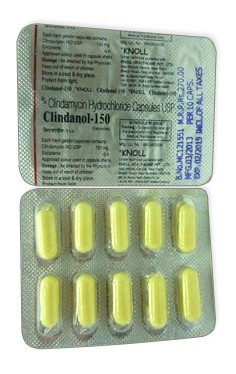
Dalacin C
- Dalacin C (clindamycin) is supplied through community pharmacies, hospital pharmacies and online suppliers; it is a prescription-only medicine in Australia and most countries — although some vendors or pharmacies may claim to supply it without a prescription, purchasing or using antibiotics without a valid prescription is not recommended and may be illegal.
- Dalacin C is used to treat serious bacterial infections (skin and soft tissue, bone and joint, respiratory tract, pelvic/intra‑abdominal and anaerobic infections, dental infections and as an alternative in penicillin‑allergic patients). It is a lincosamide antibiotic that inhibits bacterial protein synthesis by binding to the 50S ribosomal subunit.
- Usual adult oral doses are 150–450 mg every 6 hours (3–4 times daily); severe infections IV/IM dosing may be 600–2,700 mg per day divided 2–4 times (and up to 4,800 mg/day in life‑threatening cases). Paediatric oral dosing is typically 8–20 mg/kg/day (divided 3–4 times); IV 20–40 mg/kg/day (divided).
- Available forms and routes: oral capsules/tablets (75, 150, 300 mg), oral solution (75 mg/5 mL), injectable (IV/IM) formulations (e.g. 150 mg/mL, 300 mg/2 mL, 600 mg/4 mL), topical gels/foams (1–2%) and vaginal creams/ovules (2%, 100 mg).
- Onset: oral absorption is relatively rapid (plasma concentrations typically reached within about 1 hour); clinical improvement is often seen within 24–72 hours depending on infection severity and site; IV administration achieves therapeutic levels immediately.
- Duration of action: the elimination half‑life is about 2–3 hours, so dosing is commonly every 6–8 hours; treatment courses vary by infection (skin 7–10 days, respiratory/osteomyelitis 10–21 days, pelvic 10–14 days or longer for anaerobic infections).
- Alcohol warning: there is no direct severe interaction with moderate alcohol, but avoid alcohol if you have gastrointestinal symptoms, diarrhoea or significant liver disease; alcohol may worsen side effects and hinder recovery.
- The most common side effect is diarrhoea; other frequent adverse effects include nausea, vomiting, abdominal pain, rash and local irritation with topical or injectable forms; a serious risk is Clostridioides difficile‑associated diarrhoea, which requires urgent medical attention.
- Would you like to try dalacin c without a prescription?
Basic Dalacin C Information
- INN (International Nonproprietary Name): Clindamycin
- Brand Names Available In Australia: Cleocin HCl; Cleocin Pediatric; Cleocin Phosphate; Clindamycin‑Mepha; Dalacin C; ClindaMax; Clindesse; Numerous generics.
- ATC Code: J01FF01
- Forms & Dosages: Capsules/tablets 75 mg, 150 mg, 300 mg; oral solution 75 mg/5 mL; injection (IV/IM) 150 mg/mL, 300 mg/2 mL, 600 mg/4 mL; topical gel/foam 1% and 2%; vaginal cream/ovule 2% and 100 mg.
- Manufacturers In Australia: Not specified
- Registration Status In Australia: Not specified
- OTC / Rx Classification: Prescription Only (Rx)
Latest Research Highlights
Worried about whether clindamycin still works for common infections in Australia and what the safety signals are?
Recent Australian surveillance and international literature from 2022–2025 highlight three consistent themes: evolving susceptibility patterns, heightened awareness of Clostridioides difficile infection (CDI) risk, and a clearer role for topical or combination use in acne and bacterial vaginosis.
Australian hospital antibiograms report variable community MRSA susceptibility to clindamycin, prompting stewardship teams to recommend susceptibility‑guided prescribing and routine D‑testing for inducible resistance.
Systematic reviews continue to support clindamycin’s effectiveness for anaerobic pelvic and dental infections but flag a higher CDI incidence compared with many alternatives.
Dermatology trials from 2022–2024 support topical clindamycin combined with benzoyl peroxide to reduce resistance and improve outcomes in acne.
Paediatric pharmacokinetic updates reaffirm weight‑based oral dosing of 8–20 mg/kg/day and IV regimens of 20–40 mg/kg/day consistent with established formularies, while ICU studies reiterate high‑dose IV options for life‑threatening infections.
Post‑marketing safety reports emphasise gastrointestinal adverse events and rare but severe colitis as the dominant signals.
Quick Table — Study Type | Population | Outcome | Safety Observation:
- Australian Surveillance | Community/ Hospital | Variable MRSA susceptibility | Guidance: Susceptibility‑guided use
- Systematic Reviews | Anaerobic pelvic/dental | Good efficacy | Higher CDI incidence vs alternatives
- Dermatology RCTs | Acne patients | Improved clearance with combo therapy | Reduced topical resistance with benzoyl peroxide
- Paediatric PK Studies | Children | Confirms weight‑based dosing | Safety: GI adverse effects reported
Clinical Effectiveness In Australia
Are patients getting better when clindamycin is used here, and what do local prescribers watch for?
Clindamycin remains clinically effective for many anaerobic, skin and soft tissue, dental and pelvic infections when susceptibility is confirmed.
Australian outcomes rely on timely culture‑guided therapy and adherence to local antimicrobial stewardship protocols.
The Therapeutic Goods Administration (TGA) governs product safety and labelling, and hospital guidelines commonly reserve clindamycin as a second‑line choice for penicillin‑allergic patients or where anaerobic coverage is needed.
Pharmaceutical Benefits Scheme (PBS) involvement varies by indication, with many outpatient courses issued as private prescriptions.
Real‑world Australian audits report good cure rates for osteomyelitis and anaerobic intra‑abdominal infections when clindamycin is combined with prompt source control.
Key limitations are an elevated CDI risk and community MRSA resistance; clinicians increasingly perform D‑tests and full susceptibility panels before relying on clindamycin for staphylococcal infections.
Data Highlights:
- Good cure rates in bone and anaerobic infections when combined with source control.
- Increased CDI incidence compared with several alternatives noted in systematic reviews.
- Susceptibility‑guided use advised for MRSA and severe skin infections.
Indications And Expanded Uses
Which infections is clindamycin approved for, and where is it used off‑label in Australia?
TGA‑aligned indications reflect established uses: serious skin and soft tissue infections, bone and joint infections including osteomyelitis, respiratory tract infections, pelvic and intra‑abdominal anaerobic infections, dental abscesses and septicaemia.
Available product forms support systemic and local therapy, including oral capsules, oral solution, IV/IM injectables, topical gels and vaginal preparations.
Common off‑label practices in Australia include topical clindamycin for acne (often combined with benzoyl peroxide), intraligamentary dental application, and adjunctive use for selected MRSA skin infections when full susceptibility is documented.
Pregnancy guidance supports clindamycin where indicated for obstetric or gynaecological anaerobic infections, with prescribers consulting obstetric recommendations before use.
Clinicians working with Indigenous and remote communities weigh benefits against access‑related risks for follow‑up if CDI occurs; IV formulations may require transfer to regional centres for monitoring.
Forms‑to‑Indication Table:
- Capsules/Oral Solution — Skin infections, dental, respiratory infections.
- IV/IM Injectables — Severe systemic infections, ICU use, bone infections.
- Topical Gel — Acne management, often combined to reduce resistance.
- Vaginal Cream/Ovule — Bacterial vaginosis (local therapy).
Composition And Brand Landscape In Australia
Which brands and suppliers should pharmacists and patients recognise when searching for dalacin c?
The active ingredient across all products is clindamycin (INN), classified under ATC J01FF01 as a lincosamide antibiotic.
Major international brands and generics commonly encountered in supply chains include Cleocin, Dalacin C, Clindamycin‑Mepha and numerous generics from suppliers such as Pfizer, Sandoz, Teva and others.
Available forms and usual strengths include 75/150/300 mg capsules, 75 mg/5 mL oral solution, injectable vials and topical 1–2% formulations, as well as 2% vaginal creams or 100 mg ovules.
PBS listings for specific clindamycin products vary and many community prescriptions are dispensed privately.
| Brand | Form | Dosage | Supplier |
|---|---|---|---|
| Cleocin | Capsule/Injection/Oral | 75 mg, 150 mg, 300 mg; injection strengths | Pfizer |
| Dalacin C | Capsule/Injection | 150 mg, 300 mg; injection 150 mg/mL | Pfizer / Sandoz distributors |
| Clindamycin‑Mepha | Capsule/IV ampoule | 150 mg; 600 mg/4 mL ampoule | Mepha |
| Generics | Multiple | Capsules, oral solution, topical | Sandoz, Teva, Cipla, others |
Contraindications And Special Precautions
Who should avoid clindamycin and which patients need closer monitoring?
Absolute contraindications include known hypersensitivity to clindamycin or lincomycin and prior clindamycin‑associated Clostridioides difficile colitis.
High‑risk Australian groups for special caution include elderly patients with increased CDI risk and people with prior severe gastrointestinal disease.
Patients receiving neuromuscular blocking agents require caution because clindamycin may enhance neuromuscular blockade.
Severe hepatic impairment calls for close monitoring rather than routine dose adjustment, and clinicians should assess accumulation risk.
For Indigenous Australians and remote communities, clinicians must consider access to follow‑up and the potential consequences of CDI if it develops after community prescribing.
Pregnancy and breastfeeding: clindamycin may be used when benefits outweigh risks and prescribers should consult obstetric and lactation guidance.
Workplace and driving: no routine restrictions, but counsel patients that dizziness, severe diarrhoea or rash may transiently affect driving ability.
| Risk Group | Counselling Point |
|---|---|
| Prior C. difficile Colitis | Avoid clindamycin; document severe past reaction |
| Elderly | Warn about increased CDI risk; ensure prompt review for diarrhoea |
| Hepatic Impairment | Monitor liver function and for accumulation signs |
| Neuromuscular Blockade | Avoid concurrent use with neuromuscular blockers where possible |
Dosage Guidelines
What dose should I give for common infections and how do I adjust for kids or organ impairment?
Standard adult oral dosing commonly used is 150–450 mg every 6 hours, with typical outpatient courses of 7–14 days depending on indication.
IV regimens for severe infection commonly range from 600–2,700 mg/day divided every 6–8 hours, with specialised settings occasionally using up to 4,800 mg/day for life‑threatening infections.
Paediatric dosing aligns with established formularies: oral 8–20 mg/kg/day divided and IV 20–40 mg/kg/day divided in 3–4 doses.
No routine dose adjustment is required for renal impairment, but severe end‑stage renal disease warrants clinician review.
Hepatic impairment does not mandate routine dose reduction but requires monitoring for accumulation and hepatotoxicity.
Topical formulations should follow manufacturer instructions, often once or twice daily, and acne regimens usually combine clindamycin with benzoyl peroxide to limit resistance.
Dosing Checklist For Prescribers:
- Confirm patient weight and indication before choosing mg/kg dosing for children.
- Review culture and susceptibility results within 48–72 hours to de‑escalate if possible.
- Document duration and specify follow‑up for GI symptoms to catch CDI early.
Interactions Overview
Will clindamycin interact with other medicines I commonly see in pharmacy practice?
Clindamycin has few pharmacokinetic food interactions, though GI intolerance can be worse with alcohol or heavy meals.
Alcohol does not increase CDI risk per se but may exacerbate gastrointestinal side effects when combined with clindamycin.
Significant drug interactions include potentiation of neuromuscular blockade when used with agents such as tubocurarine or other neuromuscular blockers.
In vitro antagonism between clindamycin and erythromycin has been reported, so concurrent use is generally avoided or monitored.
Concurrent use with hepatotoxic drugs should prompt liver‑function monitoring due to possible additive effects on liver enzymes.
Interaction with oral contraceptives is inconsistent; counsel patients that routine contraceptive failure is unlikely, but advise extra precautions if severe vomiting or diarrhoea occurs.
TGA adverse‑event and e‑health records flag co‑prescribing broad‑spectrum antibiotics as stewardship concerns rather than classic pharmacokinetic interactions.
Cultural Perceptions And Patient Habits In Australia
How do Australians typically find and use clindamycin, and what should pharmacists expect when counselling?
Many Australian patients are price‑conscious and look to PBS subsidies and major chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart for affordability and advice.
Trust in pharmacists is high and patients commonly use pharmacy counselling, telehealth prescriptions and online ordering when convenient.
Rural and remote communities face access barriers to IV formulations and reliable follow‑up, which influences clinicians to be cautious when prescribing CDI‑risk antibiotics in those settings.
Common online searches and forum discussions focus on “acne clindamycin”, “Dalacin C 300 mg”, and “clindamycin for dental abscess”, with frequent patient concerns about side effects, CDI risk and cost.
Indigenous health services emphasise continuity of care and culturally safe follow‑up plans when antibiotics with higher CDI risk are used in community settings.
Telehealth prescribing has increased; pharmacists should confirm local dispensing arrangements and clear follow‑up plans for high‑risk antibiotics.
User Journey — Urban Vs Rural:
- Urban: Telehealth script → Major chain or local pharmacy → counselling and prompt dispensing.
- Rural: Prescriber phone consult → regional pharmacy or hospital supply → possible referral for IV therapy and planned follow‑up.
Availability And Pricing Patterns
Where can patients buy dalacin c in Australia and what should they expect to pay or to check when ordering online?
Clindamycin products are available through major pharmacy chains and online retailers, with availability varying by brand, strength and pack size.
Chemist Warehouse and Priceline often list generics at competitive retail prices, while community pharmacies commonly dispense private scripts.
PBS coverage is indication‑dependent and some inpatient or specialist prescriptions come via hospital formularies and state health services.
Online pharmacies and telehealth services supply clindamycin on prescription, and pharmacists must verify PBS eligibility and counsel on CDI risk.
Rural patients may need to order specific formulations via regional wholesalers or hospital supply chains, which can affect delivery time and price.
| Purchase Route | Typical Cost Pattern | Notes |
|---|---|---|
| Major Chain Pharmacy | Competitive retail pricing | Fast local availability for common strengths |
| Independent Community Pharmacy | Variable; pharmacist counselling included | May stock specific brands on request |
| Online Pharmacy / Telehealth | Private script pricing; delivery fees may apply | Verify prescription authenticity and storage instructions |
| Hospital Supply / PBS | Subsidised when indicated | Often used for inpatient IV formulations |
Purchase Note: In our online pharmacy, dalacin c is available without a prescription, with discreet delivery to Australia in 5–14 days.
Checklist For Buying Online:
- Have a valid prescription ready.
- Confirm brand and strength match the prescriber’s order.
- Check shipping times and storage instructions.
Comparable Medicines And Prescriber Preferences
When would a prescriber choose an alternative and what are the pros and cons of clindamycin?
Alternatives depend on infection type and organism susceptibility; common comparators include metronidazole for anaerobes, amoxicillin/clavulanate for many community infections, macrolides like azithromycin for certain patients, and linezolid for resistant Gram‑positives.
Clindamycin is often preferred when anaerobic coverage plus Gram‑positive activity is required or in genuine penicillin allergy.
Advantages include good tissue penetration into bone and abscesses and multiple formulations for IV, oral and topical use.
Disadvantages include a recognised higher CDI risk, rising resistance among some community MRSA strains, and the absence of routine renal dose reduction guidance.
Australian prescribers balance PBS availability, local stewardship guidance and TGA safety advice when selecting alternatives to clindamycin.
Quick Decision Matrix:
- Penicillin Allergy + Anaerobe Suspect → Clindamycin preferred if susceptible.
- Anaerobic Pelvic/Dental Infection → Metronidazole or clindamycin depending on flora and allergy.
- Resistant MRSA Skin Infection → Consider linezolid or other agents if clindamycin resistance present.
Frequently Asked Questions
People often ask about PBS access, C. diff risk and whether they can use clindamycin for acne.
- Q: Is Dalacin C available on the PBS? A: PBS listing varies by product and indication; check PBS Online or ask your pharmacist—many outpatient scripts are private.
- Q: Will clindamycin make me sicker with C. diff? A: Clindamycin has a well‑recognised higher association with CDI; seek prompt review for prolonged or bloody diarrhoea.
- Q: Can I take clindamycin if allergic to penicillin? A: Yes—clindamycin is commonly used as an alternative in true penicillin allergy after confirming the allergy history.
- Q: Is topical clindamycin OK for acne? A: Yes, topical clindamycin can be effective for acne and is best combined with benzoyl peroxide to reduce resistance risk.
Data Highlight: Seek urgent review for any diarrhoea lasting more than 48 hours or if bloody diarrhoea occurs after starting clindamycin.
Guidelines For Proper Use And Pharmacist Counselling
What practical checks and counselling points should pharmacists cover at the pharmacy desk?
Verify prescription authenticity, confirm the indication and review allergy history, specifically distinguishing penicillin allergy from prior reactions to clindamycin or lincomycin.
Explain dosing clearly (for example, 150–450 mg every 6 hours for adults), duration of therapy, missed‑dose advice and correct storage (capsules 15–25°C).
Emphasise CDI risk and instruct patients to seek urgent review for severe, bloody or prolonged diarrhoea and to avoid antidiarrhoeals until reviewed by a clinician.
For topical therapy, counsel on correct application, avoidance of ocular or mucosal contact and the benefit of combining with benzoyl peroxide for acne to limit resistance.
For rural patients ensure a clear follow‑up plan and local dispensing arrangements, and consider hospital referral for IV therapy if needed.
Counsel on relevant interactions such as neuromuscular blockers and concurrent hepatotoxic drugs, and advise on contraceptive precautions if severe vomiting or diarrhoea occurs.
Document counselling in the patient record and assist prescribers with PBS authority coding when required.
Pharmacist Counselling Checklist:
- Confirm identity, allergy history and indication.
- Explain dose, frequency, duration and missed‑dose instructions.
- Advise on CDI warning signs and when to seek urgent care.
- Review interactions and special precautions (pregnancy, breastfeeding, hepatic disease).
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Ballarat | Victoria | 5–9 days |
| Wollongong | New South Wales | 5–7 days |
| Broome | Western Australia | 5–9 days |
| Coffs Harbour | New South Wales | 5–9 days |
| Albury | New South Wales / Victoria | 5–9 days |
| Launceston | Tasmania | 5–9 days |