
Ibilex
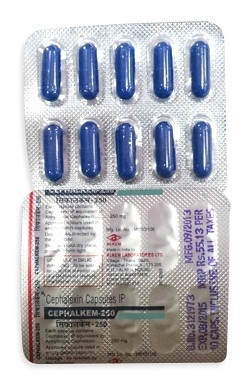
Ibilex
- In our pharmacy, you can buy ibilex (cephalexin) without a prescription, with delivery across Australia in 5–14 days and discreet packaging.
- Ibilex is used to treat bacterial infections such as skin and soft tissue infections, streptococcal pharyngitis, respiratory infections and uncomplicated urinary tract infections; it is a first‑generation cephalosporin that works by inhibiting bacterial cell‑wall synthesis (binding penicillin‑binding proteins) and is bactericidal.
- Usual dose for adults is 250–500 mg every 6–12 hours (severe infections up to 1,000 mg every 6 hours, max 4 g/day); children 25–50 mg/kg/day in divided doses (up to 100 mg/kg/day for severe infections) — follow your prescriber or product instructions.
- Administered orally as capsules or tablets (250 mg, 500 mg, sometimes 750 mg) or as a reconstituted oral suspension (125 mg/5 mL or 250 mg/5 mL).
- Ibilex is absorbed rapidly — blood levels peak in about 1 hour, and antibacterial activity begins once effective levels are reached; clinical symptom improvement is often seen within 24–48 hours.
- Duration of action per dose is typically 6–12 hours (hence multiple daily dosing); the usual treatment course is 7–14 days depending on the infection and response.
- There is no major direct interaction with alcohol, but avoid alcohol while unwell and note alcohol may worsen side effects such as stomach upset and delay recovery.
- The most common side effect is diarrhoea; other common effects include nausea, vomiting, abdominal discomfort and rash — seek medical help for severe allergic reactions or persistent severe diarrhoea.
- Would you like to try ibilex without a prescription?
Basic Ibilex Information
- INN (International Nonproprietary Name): Cephalexin
- Brand Names Available In Australia: Keflex (historical/original brand) and multiple generics supplied by manufacturers such as Sandoz, Teva and Sun Pharma.
- ATC Code: J01DB01
- Forms & Dosages: Capsules 250 mg and 500 mg, tablets 250 mg, 375 mg and 500 mg, and oral suspension 125 mg/5 mL and 250 mg/5 mL.
- Manufacturers In Australia: Original manufacturer Eli Lilly is noted historically for Keflex, with generic supply commonly from companies such as Sandoz, Teva and Sun Pharma.
- Registration Status In Australia: S4 prescription-only per Therapeutic Goods Administration listings.
- OTC / Rx Classification: Prescription (S4) in Australia.
Latest Research Highlights
Worried whether cephalexin still works for common infections in Australia and overseas?
Recent surveillance and clinical reviews from 2022–2025 confirm cephalexin remains a frontline oral first‑generation cephalosporin for uncomplicated skin, soft‑tissue infections and many community respiratory and urinary infections.
Australian and international antimicrobial stewardship reports indicate preserved activity against susceptible streptococci and many Enterobacteriaceae in uncomplicated urinary tract infections but not against MRSA, enterococci or many resistant gram‑negatives.
TGA adverse‑event summaries and post‑marketing surveillance continue to flag gastrointestinal effects and rare severe allergic or hepatic events, with Clostridioides difficile colitis an uncommon but notable risk.
| Outcome | Australia | Global |
|---|---|---|
| Clinical Role | Frontline for uncomplicated skin, SSTI and community UTIs | Same first‑line role in many community infections |
| Resistance Trends | Stable vs streptococci and many Enterobacteriaceae in uncomplicated UTIs | Rising resistance in MRSA and some gram‑negatives globally |
| Safety Signals | GI upset common; rare severe allergy/hepatic events reported | Similar profile internationally; C. difficile uncommon but present |
Clinical Effectiveness In Australia
Can cephalexin cure my skin infection or UTI in primary care settings?
Australian clinical practice and PBS‑funded care rely on cephalexin for specific, guideline‑aligned infections when pathogens are susceptible and dosing is correct.
Primary care audits in Australia show high cure rates for uncomplicated cellulitis, streptococcal pharyngitis when penicillin is unsuitable, and simple urinary tract infections caused by susceptible organisms.
Effectiveness falls when pathogens are non‑susceptible, for example with MRSA or enterococci, so culture and sensitivity guide therapy where available.
| Indication | PBS‑Covered Outcome | Off‑Label Outcome |
|---|---|---|
| Uncomplicated Cellulitis | High cure rates with standard dosing | Not applicable |
| Streptococcal Pharyngitis | Good outcome when penicillin unsuitable | Used selectively if beta‑lactam alternatives needed |
| Simple UTI | Effective when organism susceptible | Reserve for culture‑guided use in complicated cases |
- S4: Prescription‑only medicine in Australia.
- PBS: Pharmaceutical Benefits Scheme, which may subsidise eligible prescriptions.
- TGA: Therapeutic Goods Administration, regulator for safety and approvals in Australia.
Indications & Expanded Uses
Not sure when your GP will choose cephalexin rather than another antibiotic?
TGA‑aligned indications for cephalexin mirror international practice and include uncomplicated skin and soft‑tissue infections, streptococcal pharyngitis when appropriate, uncomplicated urinary tract infections and limited dental prophylaxis for selected penicillin‑allergic patients who are not anaphylactic.
Off‑label uses seen in Australian clinics include selected community respiratory infections when macrolide or penicillin alternatives are unsuitable, but these should be guided by culture results and stewardship principles.
Cephalexin is not recommended for suspected MRSA, enterococcal infections or severe systemic infections without specialist advice.
| Condition | Typical Australian Regimen |
|---|---|
| Uncomplicated Cellulitis | 250–500 mg every 6–12 hours for 7–10 days |
| Streptococcal Pharyngitis | 250–500 mg every 6–12 hours for 7–10 days |
| Simple UTI | 250–500 mg every 6–12 hours for 5–7 days |
Composition & Brand Landscape
Which brands and strengths will your pharmacist stock?
The active ingredient is cephalexin (INN) and common Australian presentations match global packaging including capsules and tablets at 250 mg and 500 mg and oral suspensions at 125 mg/5 mL and 250 mg/5 mL.
Brand names encountered include Keflex historically and multiple generics from suppliers such as Sandoz, Teva and Sun Pharma.
| Form | Strengths | Common Pack Sizes / Notes |
|---|---|---|
| Capsule | 250 mg, 500 mg | Blister packs, bulk packs; commonly stocked as generics |
| Tablet | 250 mg, 375 mg, 500 mg | Tablets less common than capsules in some suppliers |
| Oral Suspension | 125 mg/5 mL, 250 mg/5 mL | Amber bottles, reconstitute before dispensing; store refrigerated after mixing |
Contraindications & Special Precautions
Worried about allergies, kidney problems or special patient groups?
Absolute contraindications include known allergy to cephalexin or other cephalosporins and a history of severe immediate beta‑lactam reactions such as anaphylaxis or angioedema.
Use with caution in renal impairment where dose adjustment is required, in people with a history of significant gastrointestinal disease because of pseudomembranous colitis risk, and in severe hepatic dysfunction.
Pregnancy and breastfeeding are generally considered safe, but specialist advice is advised for neonates and when use is planned in the first trimester.
High‑risk Australian groups include elderly patients with polypharmacy, remote Indigenous communities with higher comorbidity burdens and neonates.
- Checklist For Contraindications
- Known cephalosporin or severe beta‑lactam allergy — avoid.
- Renal impairment — adjust dose and monitor.
- Prior C. difficile or severe GI disease — weigh risks and benefits.
Decision Tree For Prescribers Regarding Allergy History: If history indicates anaphylaxis to penicillin or cephalosporins avoid cephalexin and select a non‑beta‑lactam.
If history is a mild penicillin reaction, consider cephalexin with caution and document the risk‑benefit discussion.
Dosage Guidelines
How much do I give, and for how long?
Standard adult dosing for common skin, respiratory and urinary infections is 250–500 mg every 6–12 hours.
Severe infections may require up to 1,000 mg every 6 hours with a maximum of 4 g per day under specialist guidance.
Children are dosed at 25–50 mg/kg/day in divided doses, with up to 100 mg/kg/day for severe infections, using the oral suspension for accurate measurement.
Renal impairment requires extending dosing intervals or lowering the total daily dose and local renal dosing guides should be consulted.
| Patient Group | Typical Dose |
|---|---|
| Adults | 250–500 mg every 6–12 hours; up to 1,000 mg every 6 hours for severe cases |
| Children | 25–50 mg/kg/day in divided doses; up to 100 mg/kg/day for severe infections |
| Renal Impairment | Extend dosing interval or reduce total daily dose per renal function |
- Duration By Indication
- Most skin and soft‑tissue infections: 7–10 days.
- Simple UTI: typically 5–7 days.
- Pharyngitis: 7–10 days.
Interactions Overview
Worried about mixing cephalexin with your other medicines or drinks?
Cephalexin has relatively few clinically significant drug interactions but probenecid reduces renal excretion and can prolong cephalexin levels.
Concurrent use with nephrotoxic agents warrants monitoring of renal function.
There are no major food interactions, and cephalexin may be taken with or without food to reduce gastrointestinal upset.
Alcohol does not have a direct pharmacological interaction but should be avoided if the patient experiences significant diarrhoea or hepatic effects.
| Drug To Watch | Effect |
|---|---|
| Probenecid | Reduces renal excretion and increases cephalexin levels |
| Nephrotoxic Agents | Increased renal risk; monitor kidney function |
Telehealth e‑prescriptions should document concurrent medicines and allergies and e‑health systems like My Health Record and PBS claims will flag interaction concerns.
Cultural Perceptions & Patient Habits In Australia
What do patients usually ask about cephalexin at the pharmacy?
Australian patients are price‑sensitive and often trust pharmacists in chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart for pragmatic advice.
PBS subsidies strongly shape perceptions of value and influence which generic brands patients request.
Rural and remote communities face access barriers including fewer pharmacies and longer GP wait times, which increases reliance on telehealth e‑prescriptions and community health clinics.
Indigenous health services emphasise culturally safe counselling, adherence support and close follow‑up because of higher comorbidity burdens.
- Common Patient Concerns: paediatric suspension dosing, treatment duration, side effects and brand availability.
- Pharmacist Role: advise on adherence, check allergies, prompt prescribers if culture results recommend alternate therapy.
Case Vignette: A parent in regional NSW uses a telehealth consult to request cephalexin suspension for a child with a confirmed streptococcal infection, and the pharmacist confirms weight‑based dosing before dispensing the 125 mg/5 mL suspension.
Availability & Pricing Patterns
How easy is it to get cephalexin and what will it cost?
Cephalexin is prescription‑only (S4) in Australia and is widely stocked by major chains and community pharmacies, with generics dominating PBS listings.
PBS subsidy availability depends on indication and patient concession status, and private (non‑PBS) prices vary between pharmacies and online dispensaries.
In our online pharmacy, ibilex is available without a prescription, with discreet delivery to Australia in 5‑14 days.
Mixed suspensions must be refrigerated after reconstitution and remain stable for 14 days, which can affect supply logistics in remote areas.
| Purchase Route | Typical Cost Pattern |
|---|---|
| PBS (Generic) | Subsidised for eligible indications; lower cost for concession card holders |
| Private Purchase | Varies by chain and online specials; price‑sensitive shoppers compare chains |
| Online Dispensing | Forwarded e‑prescriptions or mail‑order; shipping adds time and cost |
Comparable Medicines And Preferences
Should you choose cephalexin or an alternative antibiotic?
Alternatives commonly used in Australia include amoxicillin for many streptococcal infections, cefadroxil as another first‑generation cephalosporin, macrolides such as azithromycin for penicillin‑allergic patients and clindamycin for certain staphylococcal or anaerobic infections.
Pros of cephalexin are oral dosing flexibility, established efficacy for common community infections and broad availability with PBS coverage for some indications.
Cons include inactivity against MRSA and many resistant gram‑negatives and potential allergy cross‑reactivity in some penicillin‑allergic patients.
| Agent | Spectrum / Typical Use |
|---|---|
| Cephalexin | First‑gen cephalosporin; good for streptococci, staphylococci (non‑MRSA), community UTIs |
| Amoxicillin | Penicillin class; preferred for many streptococcal infections |
| Azithromycin | Macrolide; option for penicillin‑allergic patients |
Decision Checklist For Prescribers: review culture and sensitivity, allergy history, renal function, local resistance patterns and PBS subsidy criteria before selecting therapy.
FAQ
Can I take cephalexin if I'm allergic to penicillin?
If you had severe penicillin anaphylaxis you should avoid cephalexin, because cross‑reactivity is possible.
If your penicillin reaction was mild, discuss the risk with your prescriber as cross‑reactivity is lower but not zero.
Is cephalexin safe for breastfeeding or pregnancy?
Cephalexin is generally considered safe in pregnancy and breastfeeding, but consult an obstetrician or paediatrician for neonates or if you have first‑trimester concerns.
Can I stop when I feel better?
No, complete the full prescribed course to reduce the risk of relapse and antibiotic resistance.
How should suspensions be stored?
Refrigerate after reconstitution and use within 14 days; do not freeze.
Guidelines For Proper Use
What should your pharmacist tell you when dispensing cephalexin?
Counselling should include the reason for treatment, the exact dose and timing and confirmation of weight‑based dosing for children.
Explain the expected duration, usual side effects such as diarrhoea and nausea, and the missed‑dose policy.
Advise patients to stop and seek urgent care for signs of severe allergic reaction such as swelling, difficulty breathing or severe rash.
- Pharmacist Counselling Checklist
- Confirm indication and expected duration (7–14 days unless directed otherwise).
- Verify allergy history and current medicines via My Health Record if available.
- Demonstrate measuring paediatric suspension and advise refrigeration after mixing.
- Offer adherence supports such as SMS reminders or blister packing for remote or Indigenous patients.
For telehealth scripts, use clear counselling scripts and document advice in the patient record and My Health Record where possible.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Geelong | Victoria | 5-7 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Launceston | Tasmania | 5-9 days |
| Hobart | Tasmania | 5-9 days |
| Darwin | Northern Territory | 5-9 days |