
Ceftin
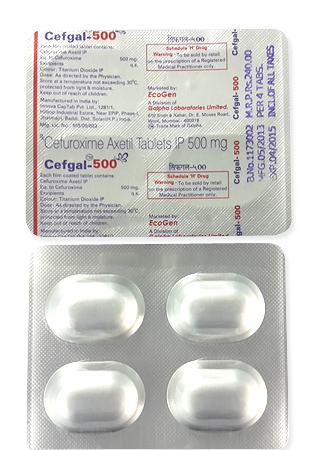
Ceftin
- In our pharmacy, you can buy ceftin without a prescription, with delivery in 5–14 days throughout Australia and discreet packaging; note that officially cefuroxime axetil (Ceftin) is a prescription-only medicine in Australia and most countries.
- Ceftin (cefuroxime axetil) is a second‑generation cephalosporin antibiotic used for respiratory tract infections (sinusitis, bronchitis, otitis media, pharyngitis), skin and soft tissue infections, uncomplicated urinary tract infections, early Lyme disease and uncomplicated gonorrhoea; it works by inhibiting bacterial cell‑wall synthesis (binding penicillin‑binding proteins) leading to bacterial death.
- Usual adult doses vary by indication: commonly 250 mg orally every 12 hours for mild respiratory infections, 500 mg every 12 hours for more severe lower respiratory infections or Lyme disease, 125 mg every 12 hours for uncomplicated UTI, and a single 1 g dose for uncomplicated gonorrhoea; paediatric dosing is weight‑based (eg 10–15 mg/kg every 12 hours, max 250–500 mg).
- Administered orally as film‑coated tablets (250 mg, 500 mg) or as an oral suspension (125 mg/5 mL, 250 mg/5 mL); take with or after food to improve absorption (injectable cefuroxime sodium is used in hospital but is not sold as Ceftin).
- Antibacterial activity begins after the drug is absorbed (cefuroxime axetil is converted to active cefuroxime); you may notice symptomatic improvement within 48–72 hours, though the antibiotic effect starts within a few hours of dosing.
- Therapeutic effect is maintained with twice‑daily dosing (every 12 hours for most indications); the plasma half‑life is short (~1–2 hours), which is why 12‑hour dosing is commonly used and treatment courses typically run 5–21 days depending on the infection.
- Avoid excessive alcohol while being treated — alcohol does not have a major direct interaction with cefuroxime but can worsen side effects and delay recovery, so alcohol intake is not recommended during therapy.
- The most common side effect is diarrhoea; other frequent adverse effects include nausea, vomiting, abdominal pain, rash or other hypersensitivity reactions, vaginitis and occasional transient liver enzyme elevations.
- Would you like to try ceftin without a prescription?
Basic Ceftin Information
- INN (International Nonproprietary Name): Cefuroxime axetil.
- Brand Names Available In Australia: Ceftin (tablets 250 mg, 500 mg; oral suspension 125 mg/5 mL and 250 mg/5 mL) is the brand name indicated for Australia in the product data.
- ATC Code: J01DC02 — Second‑generation cephalosporin antibiotics.
- Forms & Dosages: Film‑coated tablets 250 mg and 500 mg; oral suspension granules 125 mg/5 mL and 250 mg/5 mL; injectable cefuroxime sodium (750 mg, 1.5 g) is hospital use and not the oral Ceftin formulation.
- Manufacturers In Australia: GSK is listed as the original supplier for brands such as Ceftin and Zinnat; generics are supplied worldwide by companies such as Sandoz, Teva, Torrent and Sun Pharmaceuticals — check local pharmacy stock for specific Australian suppliers.
- Registration Status In Australia: Cefuroxime axetil is a prescription medicine registered with jurisdictional regulators including the TGA as an approved antibacterial agent.
- OTC / Rx Classification: Prescription only (Rx) in all jurisdictions according to the product data.
Latest Research Highlights Australian + Global — Key Findings 2022–2025
Clinicians ask whether cefuroxime axetil remains a reliable oral option for common community infections.
Recent surveillance and clinical literature through 2022–2025 continue to show cefuroxime axetil is widely used as an oral second‑generation cephalosporin for community‑acquired respiratory and skin infections.
Australian state and national laboratory surveillance reports maintain that common respiratory pathogens such as Streptococcus pneumoniae and Haemophilus influenzae show generally good susceptibility to cefuroxime.
Global data mirror Australian findings for respiratory isolates but show increasing Enterobacterales resistance driven by ESBL producers, which reduces cefuroxime utility for some urinary and intra‑abdominal infections.
Pharmacokinetic studies reaffirm predictable absorption of cefuroxime axetil when taken with food, improving bioavailability of the oral prodrug compared with fasting administration.
Safety surveillance since 2022 remains stable, with the most frequently reported adverse events being gastrointestinal symptoms, rash and occasional hepatic enzyme elevation.
Serious allergic reactions, while uncommon, are clinically important and remain a signal that guides stewardship and allergy screening.
Antimicrobial stewardship studies emphasise limiting cephalosporin use when narrow‑spectrum agents will do, to reduce selection pressure for resistant organisms.
Summary table of selected surveillance and clinical observations:
- Australian Surveillance (State/National Labs) — Outcome: Good respiratory pathogen susceptibility; Trend: Stable for S. pneumoniae and H. influenzae; Safety: GI events and rash predominating.
- Global Surveillance — Outcome: Respiratory coverage preserved in many regions; Trend: Rising ESBL Enterobacterales reducing urinary utility; Safety: Similar AE profile to Australian reports.
- PK/Absorption Studies — Outcome: Food increases oral absorption of cefuroxime axetil; Clinical Impact: Advise administration with meals for consistent exposure.
- Stewardship Studies — Outcome: Cephalosporin restriction lowers resistance selection; Clinical Impact: Reserve cefuroxime where clinically indicated beyond amoxicillin.
Clinical Effectiveness In Australia — Outcomes & PBS TGA Context
People often want to know how well cefuroxime axetil performs in Australian primary care.
In outpatient settings cefuroxime axetil is effective for indicated respiratory, ENT and uncomplicated skin infections where beta‑lactam coverage beyond amoxicillin is required.
General practice prescribing patterns in Australia show many GPs reserve cefuroxime for patients with penicillin allergy who tolerate cephalosporins or where penicillin resistance is suspected.
TGA adverse event reporting aligns with global safety profiles and serious adverse reactions remain rare but are monitored through DAEN reporting systems.
PBS listings and subsidy vary by indication and by state formularies, which affects access and prescribing choices in primary care.
Where PBS subsidy applies, treatment adherence commonly improves for price‑sensitive patients, which is particularly important for rural and Indigenous health contexts.
Data highlights panel:
- TGA DAEN Reporting Rates — Observations: Mostly mild GI and hypersensitivity reports; serious reactions uncommon according to product data.
- PBS Item Examples — Observations: PBS subsidy applies to some antibiotic indications; confirm current PBS schedule with a pharmacist.
Quick comparison of outcomes for common presentations:
| Indication | Typical Outcome |
|---|---|
| Community Respiratory Infections | Good clinical cure rates when pathogen susceptible and adherence maintained with food dosing. |
| Uncomplicated Urinary Tract Infection | Variable utility due to rising Enterobacterales resistance; consider local susceptibility before use. |
Indications & Expanded Uses — TGA‑Approved And Common Off‑Label Practices
Patients ask what conditions cefuroxime axetil treats and when clinicians might use it off‑label.
TGA‑aligned indications include acute otitis media, sinusitis, pharyngitis/tonsillitis, lower respiratory tract infections, uncomplicated skin and soft tissue infections and uncomplicated urinary tract infection.
Oral cefuroxime is also used in practice for early Lyme disease and has been used in some regimens for uncomplicated gonorrhoea.
Off‑label Australian uses include targeted respiratory therapy when penicillin allergy is reported and as step‑down therapy after intravenous cefuroxime sodium on hospital discharge.
Clinicians must avoid use for organisms inherently resistant to cefuroxime, including enterococci and MRSA.
Indication → Typical Adult Dose → Usual Duration:
- Respiratory Tract Infections (mild/moderate) → 250 mg orally every 12 hours → 7–10 days.
- Severe Lower Respiratory Infection → 500 mg orally every 12 hours → 7–10 days.
- Uncomplicated UTI → 125 mg orally every 12 hours → 5–7 days.
- Skin And Soft Tissue Infection → 250–500 mg every 12 hours → 7–10 days.
- Early Lyme Disease → 500 mg every 12 hours → 14–21 days.
- Gonorrhoea (Uncomplicated) → 1 g single oral dose → Single dose regimen.
Composition & Brand Landscape — Active Ingredients And Australian Brands PBS Generics
People want clarity on what is in the product and which brands are available locally.
The active moiety is cefuroxime axetil, the oral prodrug of cefuroxime.
International brand names include Ceftin, Zinnat, Cefurax and several generics such as Cefurox and Xorimax.
In Australia, Ceftin is the commonly referenced brand name for the oral formulation and generics from multiple manufacturers may appear in local pharmacies.
Pharmaceutical forms available include film‑coated tablets (250 mg and 500 mg) and oral suspension granules (125 mg/5 mL and 250 mg/5 mL).
| Form | Strength | Common Australian Brand/Generic | PBS Availability |
|---|---|---|---|
| Film‑Coated Tablet | 250 mg, 500 mg | Ceftin and generics | Check PBS schedule for specific subsidy and substitution rules |
| Oral Suspension (Granules) | 125 mg/5 mL, 250 mg/5 mL | Ceftin suspension and generics | Check PBS schedule for paediatric formulations and subsidy |
Storage advice from product information:
- Tablets: store at room temperature, ideally 20–25°C and protect from moisture and light.
- Reconstituted Oral Suspension: refrigerate after mixing and use within 10 days.
Contraindications & Special Precautions — High‑Risk Groups In Australia
Patients often ask whether cefuroxime is safe for them given age, pregnancy or other conditions.
Absolute contraindications include known hypersensitivity to cephalosporins and previous anaphylaxis to β‑lactam antibiotics.
High‑risk groups include older people with renal impairment, pregnant or breastfeeding people where benefits must outweigh risks, and Aboriginal and Torres Strait Islander patients who may have higher baseline comorbidity and who benefit from culturally safe counselling and closer monitoring.
Conditions requiring caution include history of colitis or C. difficile risk factors, severe malnutrition and diabetes.
The oral suspension contains sucrose and aspartame, so check ingredients for patients with diabetes or specific dietary restrictions.
Daily‑life advice includes possible dizziness or gastrointestinal symptoms that could affect driving or safety‑critical work.
Red Flags And Monitoring Checklist For Pharmacists/GPs:
- Known cephalosporin or severe β‑lactam allergy — do not supply.
- CrCl <30 mL/min or dialysis — extend dosing interval and consult specialist for dialysis dosing.
- History Of Colitis Or Recent C. difficile — consider alternative therapy and monitor closely for diarrhoea.
- Pregnancy Or Breastfeeding — use only after clinician assessment of risk vs benefit.
- Diabetes Or Sucrose/aspartame Sensitivity — check suspension ingredients before dispensing.
Dosage Guidelines — Standard Australian Regimens & Adjustments
Patients frequently ask how much to take and when to take it.
Adult dosing in community practice is commonly 250 mg every 12 hours for mild to moderate respiratory infections and 500 mg every 12 hours for more severe lower respiratory infections.
Uncomplicated UTI dosing is typically 125 mg every 12 hours, and skin infections commonly use 250–500 mg every 12 hours depending on severity.
Pediatric dosing is weight‑based at roughly 10–15 mg/kg per dose every 12 hours with maximums aligning to tablet strengths.
Renal impairment requires extending the dosing interval when creatinine clearance is below 30 mL/min and dialysis dosing should be managed by a specialist.
Food improves absorption — counsel patients to take tablets with or after meals for optimal bioavailability.
Concise Paediatric Dosing Table:
| Age/Weight | Typical Dose | Frequency |
|---|---|---|
| Children (Weight‑Based) | 10–15 mg/kg per dose (max 250–500 mg depending on indication) | Every 12 hours |
Interactions Overview — Food, Alcohol, Medicines & TGA Reports
People often worry whether cefuroxime interacts with their food, alcohol or other medicines.
Taking cefuroxime axetil with food increases absorption and is recommended for more consistent blood levels.
There is no specific disulfiram‑like interaction with alcohol, but alcohol can worsen gastrointestinal side effects and impair recovery.
Clinically relevant drug interactions are uncommon but include interaction considerations from broader cephalosporin literature.
Concomitant aminoglycoside use requires renal monitoring due to nephrotoxicity risk.
Probenecid can raise serum levels of cefuroxime and anticoagulants may require monitoring of INR when combined with cephalosporins.
TGA and e‑health adverse event systems mainly flag interactions that lead to renal accumulation when combined with nephrotoxic agents.
| Drug/Food | Clinical Impact | Pharmacist Action |
|---|---|---|
| Food | Improves cefuroxime axetil absorption | Advise taking with or after meals |
| Alcohol | No direct interaction but may worsen GI symptoms | Advise avoidance while unwell |
| Aminoglycosides | Possible additive nephrotoxicity | Monitor renal function and liaise with prescriber |
| Probenecid | May increase serum cefuroxime levels | Consider dose implications and monitor |
Cultural Perceptions & Patient Habits In Australia
Patients often compare price, brand and convenience when choosing an antibiotic at the pharmacy.
Australian shoppers are price sensitive and commonly trust pharmacists for practical advice on antibiotics and brands.
Major retail chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart are frequently compared on price by consumers.
Rural and remote patients depend on telehealth e‑prescriptions and local pharmacies for access, and supply interruptions or brand switching can affect adherence.
Indigenous health services emphasise culturally appropriate education about antibiotic risks and the importance of completing prescribed courses.
Common online concerns include allergy safety, gut health impact and preference for short‑course therapy when evidence supports it.
Patient Persona Scenarios:
- Urban Professional — Wants quick telehealth prescription, checks chain pharmacy prices, asks pharmacist about brand equivalence and food timing.
- Rural Parent — Relies on local pharmacy stock, values PBS subsidy and clear suspension dosing instructions for children.
- Indigenous Community Member — Prefers culturally safe counselling, wants clarity on why antibiotics are necessary and how to prevent side effects.
Availability & Pricing Patterns — Pharmacies, Online & PBS Comparisons
Patients ask where to get ceftin, how much it costs and whether it is subsidised.
Ceftin and generics are stocked by major chains and independent pharmacies and are listed by online pharmacies and telehealth services in tablet and suspension forms.
PBS subsidy status varies by indication and brand, and subsidised items considerably lower out‑of‑pocket cost for eligible patients.
Private pricing at chain pharmacies can vary substantially, and price comparison and generic substitution are common consumer behaviours.
Rural supply can be affected by logistics and community pharmacists frequently assist by coordinating repeats and sourcing alternative brands.
In our online pharmacy, ceftin is available without a prescription, with discreet delivery to Australia in 5‑14 days.
| Purchase Route | Typical Private Price Range | PBS Subsidy Notes |
|---|---|---|
| Chain Pharmacy (In Store) | Varies by brand and pack size | Check PBS schedule for subsidised items |
| Online Pharmacy / Telehealth | Often competitive; watch for dispensing fees | Some prescriptions may be eligible for PBS subsidy |
| Independent Pharmacy | Price varies; may stock specific generics | Pharmacist can advise on PBS substitution rules |
To confirm current PBS status and exact subsidy, ask your pharmacist or check the PBS schedule online.
Comparable Medicines And Preferences — Alternatives In Australian Practice
Clinicians weigh spectrum, resistance risk and tolerability when choosing an alternative to cefuroxime.
Alternatives include other second‑generation cephalosporins such as cefaclor, third‑generation oral agents such as cefixime and cefdinir, and amoxicillin‑clavulanate (Augmentin) when beta‑lactamase coverage is needed.
Cefuroxime is chosen when enhanced beta‑lactam coverage for H. influenzae is desired or when a patient is penicillin‑allergic but tolerates cephalosporins.
Trade‑offs include broader‑spectrum third‑generation cephalosporins which can drive resistance and Augmentin which covers beta‑lactamase producers but carries higher rates of gastrointestinal adverse events.
| Alternative | Pros | Cons |
|---|---|---|
| Cefaclor | Similar spectrum for respiratory infections | Variable availability and tolerability |
| Cefixime / Cefdinir | Third‑generation coverage, useful for some resistant organisms | Broader spectrum may encourage resistance |
| Amoxicillin‑Clavulanate (Augmentin) | Covers many β‑lactamase producers | Higher GI adverse event rates |
Local resistance patterns from surveillance should guide therapy choice, particularly for urinary and intra‑abdominal infections.
FAQ Section — Common Australian Patient Questions
Patients typically ask a few straightforward questions about ceftin.
Q: Can I get Ceftin on the PBS?
A: Some indications and brands may be PBS‑listed; ask your pharmacist or check the PBS schedule for current subsidy details.
Q: Can I drink alcohol while taking cefuroxime?
A: There is no specific disulfiram‑type interaction, but alcohol may worsen gastrointestinal side effects and slow recovery — best avoided while unwell.
Q: What if I miss a dose?
A: Take it as soon as you remember unless it is close to the next dose, in which case skip and do not double up.
Q: Is it safe in pregnancy?
A: Use only if the treating clinician judges the benefits outweigh the risks — consult your GP or obstetrician for personalised advice.
Guidelines For Proper Use — Pharmacist Counselling & Patient Advice
Pharmacists are trusted to clarify indication, dosing and safety.
Confirm the indication and document allergy history, distinguishing penicillin allergy from cephalosporin reactions.
Check renal function in older patients and advise dose adjustments or prescriber referral when creatinine clearance is low.
Advise taking tablets with food to enhance absorption and counsel on completing the full course, typically 7–10 days for most infections unless directed otherwise.
Warn patients to watch for diarrhoea and potential C. difficile symptoms and to seek medical attention if severe or persistent diarrhoea develops.
Provide storage instructions: tablets at room temperature and reconstituted suspension refrigerated and used within 10 days.
Counselling Checklist For Urban, Rural And Indigenous Contexts:
- Confirm identity and indication for telehealth prescriptions and provide written or digital patient information.
- Explain dosing schedule and food timing, and show how to measure oral suspension accurately for paediatric doses.
- Discuss PBS subsidy options, alternative brands and how to manage supply interruptions in rural areas.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–7 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–7 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Sunshine Coast | Queensland | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Cairns | Queensland | 5–9 days |