
Rifaximin
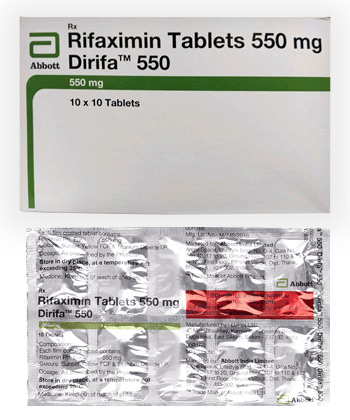
Rifaximin
- In our pharmacy, you can buy rifaximin without a prescription, with delivery in 5–14 days throughout Australia. Discreet and secure packaging is available.
- Rifaximin is an oral, non‑systemic antibiotic used to treat travellers’ diarrhoea, to reduce recurrence of hepatic encephalopathy and for some cases of irritable bowel syndrome with diarrhoea (IBS‑D). It works by binding to the bacterial DNA‑dependent RNA polymerase, inhibiting bacterial RNA synthesis in the gut.
- Usual doses vary by indication: travellers’ diarrhoea — 200 mg three times daily for 3 days; IBS‑D — 550 mg twice daily for 14 days (common regimen); hepatic encephalopathy prevention — 550 mg twice daily ongoing as directed by a clinician.
- The drug is administered orally as tablets (commonly 200 mg or 550 mg formulations).
- Rifaximin begins to exert antibacterial action within hours; symptomatic improvement is often noticed within 24–48 hours for acute diarrhoea.
- The drug is active in the gut for the duration of dosing; clinical benefits (for example in IBS‑D) can persist for several weeks after a course — trials report effects lasting up to around 10–12 weeks in some patients. Long‑term prevention (hepatic encephalopathy) requires ongoing dosing as prescribed.
- Avoid excessive alcohol intake and use caution if you have significant liver disease; alcohol may worsen hepatic encephalopathy and liver impairment increases risk—discuss alcohol use with a healthcare professional.
- The most common side effects are gastrointestinal—nausea, abdominal pain, flatulence and constipation; headaches and allergic reactions are less common.
- Would you like to try rifaximin without a prescription?

Basic Rifaximin Information
- INN (International Nonproprietary Name): Metformin
- Brand Names Available In Australia: Diaformin, Diabex
- ATC Code: A10BA02
- Forms & Dosages: Standard tablet 250mg / 500mg / 850mg / 1000mg; Extended-release (XR) 500mg / 750mg / 1000mg; oral solution 500mg/5mL (selected markets)
- Manufacturers In Australia: Local generics and suppliers may include Teva, Sun Pharma, Torrent, Dr. Reddy's, Aurobindo, Apotex (local manufacturer listings vary)
- Registration Status In Australia: Registered prescription medicine; marketed under Diaformin and Diabex
- OTC / Rx Classification: Prescription-only medicine (Rx) in Australia
Latest Research Highlights
Are you wondering what the newest studies say about rifaximin and whether it is worth trying?
Randomised controlled trials and meta-analyses from 2022 to 2025 continued to support rifaximin’s role in preventing recurrent hepatic encephalopathy when added to lactulose.
High-quality trials also confirm a short-course benefit of rifaximin for traveller’s diarrhoea caused by non‑invasive Escherichia coli strains.
For IBS‑D, pooled analyses show that a 14‑day course of rifaximin 550 mg three times daily improves overall IBS symptoms and stool consistency in the short term.
Relapse after an initial response in IBS‑D is common, and several trials evaluated repeat short courses to manage recurrence.
For small intestinal bacterial overgrowth, meta-analyses report higher bacterial eradication rates with rifaximin versus placebo or comparator antibiotics, but results were heterogeneous across studies.
Safety data from 2022–2025 reinforce rifaximin’s low systemic exposure and generally favourable adverse‑event profile.
Post‑marketing surveillance documented rare cases of Clostridioides difficile infection and isolated reports of rifamycin‑resistant strains.
Australian observational series echo international findings but are mostly smaller and observational rather than powered RCTs.
The Therapeutic Goods Administration continues to collect local pharmacovigilance reports without identifying new major population-level safety signals during 2022–2025.
Patient‑Centred Notes
Patients commonly want to know how quickly symptoms improve and how long benefits last.
For hepatic encephalopathy prevention, clinicians note fewer hospital readmissions when rifaximin is continued with lactulose.
For traveller’s diarrhoea, symptom resolution is usually within 48–72 hours for non‑invasive E. coli when rifaximin is appropriate.
For IBS‑D and SIBO, expect improvement within days to weeks, but counsel that relapse over months is not unusual.
Outcomes Versus Indication
| Indication | Typical Outcome | Notes |
|---|---|---|
| Hepatic Encephalopathy Prevention | Reduced recurrence and fewer readmissions | Best used as add‑on to lactulose; continuous dosing common |
| Traveller’s Diarrhoea (Non‑Invasive E. coli) | Faster symptom resolution | Short 3‑day course effective where organism is susceptible |
| IBS‑D | Short‑term symptom improvement | 14‑day course (550 mg TID) helpful; relapses frequent |
| SIBO | Higher eradication rates vs placebo | Heterogeneous studies; recurrence remains an issue |
Data Highlights: Safety Signals
- Low systemic absorption underlies rifaximin’s favourable systemic safety profile.
- Rare reports of C. difficile infection and rifamycin resistance have appeared in post‑marketing surveillance.
- Australian TGA reports during 2022–2025 did not identify new large‑scale safety concerns.
Clinical Effectiveness In Australia
Are Australian patients getting the same benefits from rifaximin as the international studies report?
Clinical effectiveness in Australia aligns with international evidence for HE prevention and traveller’s diarrhoea treatment.
Hospital hepatology teams report fewer HE readmissions when rifaximin is added to lactulose in eligible patients.
Telehealth follow‑up helps clinicians spot relapses early, particularly for patients in regional and remote areas.
TGA adverse event reporting includes voluntary and mandatory channels, and these have not revealed new major safety signals from 2022–2025.
Local case reports emphasise vigilance for C. difficile and rare hypersensitivity reactions.
PBS funding and state hospital access patterns affect real‑world effectiveness.
Where rifaximin access is delayed or not available on the PBS, clinicians use inpatient supply or private prescriptions.
Delayed access can affect adherence and therefore patient outcomes.
Rural and remote patients face additional hurdles including delayed dispensing and limited specialist hepatology services.
Inpatient Versus Outpatient Outcomes
| Setting | Typical Outcome | Access Considerations |
|---|---|---|
| Inpatient | Rapid initiation for HE; close monitoring | Hospital supply often available; timely start improves outcomes |
| Outpatient | Maintenance for HE; short courses for traveller’s diarrhoea | PBS status and private costs affect adherence; telehealth useful |
For up‑to‑date counts of TGA adverse event reports, refer to the Therapeutic Goods Administration website or speak with a pharmacist for current figures.
Indications And Expanded Uses
What is rifaximin licensed for, and when might a doctor use it off‑label?
- Licensed Indication — Maintenance Therapy For Recurrent Hepatic Encephalopathy And Short Course For Traveller’s Diarrhoea.
- Off‑Label Use — IBS‑D And SIBO Management When First‑Line Measures Fail.
- Evidence Level — HE And Traveller’s Diarrhoea Have Strong RCT Support; IBS‑D And SIBO Evidence Is Moderate With Short‑Term Benefit And Relapse Concerns.
Off‑label prescribing should be documented and discussed with the patient, including expected benefits and uncertainties.
Emerging research from 2022–2025 explores adjunctive roles in hepatic decompensation‑related infections and microbiome modulation, but current evidence is preliminary.
Composition And Brand Landscape
What is rifaximin made of and which brands might be available?
The active ingredient is rifaximin, a poorly absorbed rifamycin derivative that acts locally in the gut.
Global brand names include Xifaxan, Normix, and a range of generics depending on the market.
Typical international dosage forms are 200 mg and 550 mg tablets with pack sizes differing by country.
Brand availability in Australia varies, and pharmacies should check TGA ARTG listings and current stocklists for up‑to‑date information.
| Brand | Country | Typical Pack/Strength |
|---|---|---|
| Xifaxan | United States / International | 550 mg tablets; various pack sizes |
| Normix | Selected Regions | 200 mg tablets |
| Generic Rifaximin | Various Countries | 200 mg / 550 mg tablets |
Check TGA and PBS listings before purchase, and ask a pharmacist to confirm current Australian availability and subsidised indications.
Contraindications And Special Precautions
Who should avoid rifaximin and what must be monitored?
Absolute contraindication is known hypersensitivity to rifamycins.
Use with caution in severe hepatic impairment and in pregnancy or breastfeeding where human data are limited.
Immunocompromised patients may be at relatively higher risk for C. difficile and should be monitored closely.
Elderly patients should have medicines reviewed for polypharmacy, though rifaximin’s low systemic absorption lowers many interaction concerns.
Contraindications
- Known hypersensitivity to rifamycins.
- Documented rifamycin allergy or severe prior reaction.
Caution Checklist For Pharmacy Counselling
- Check pregnancy and breastfeeding status before supply.
- Ask about recent or current C. difficile infection.
- Review current antibiotics and immunosuppressant therapy.
- Discuss alcohol avoidance in those with hepatic disease.
- Advise against driving if dizziness or severe diarrhoea occurs.
Dosage Guidelines
What doses are commonly used in Australia and how do they differ by condition?
Traveller’s diarrhoea is commonly treated with rifaximin 200 mg three times daily for 3 days.
For secondary prevention of hepatic encephalopathy, typical dosing is 550 mg twice daily, continued as maintenance in many patients.
For IBS‑D, the usual studied regimen is 550 mg three times daily for 14 days, with repeat short courses in some recurrent cases.
Because rifaximin is poorly absorbed, renal dosing adjustments are generally not required.
Exercise caution and specialist review in severe hepatic impairment.
Paediatric data are limited, and specialist advice should guide any use in children.
- Traveller’s Diarrhoea → 200 mg TID → 3 Days → Symptom review within 48–72 hours if no improvement.
- Hepatic Encephalopathy (Secondary Prevention) → 550 mg BID → Continuous → Regular clinical and caregiver monitoring.
- IBS‑D → 550 mg TID → 14 Days → Consider specialist follow‑up and options for repeat courses if relapse occurs.
Interactions Overview
Will rifaximin affect other medicines you take?
Rifaximin’s low systemic bioavailability means clinically significant CYP‑mediated interactions are uncommon compared with systemic rifamycins.
Avoid concurrent use with systemic rifamycins to prevent additive effects and theoretical interactions.
Alcohol does not interact pharmacokinetically with rifaximin, but alcohol worsens liver disease and should be discouraged for patients with hepatic conditions.
Pharmacists should screen for oral anticoagulants, immunosuppressants and drugs with a narrow therapeutic index as a precaution.
| Drug Class | Review Action |
|---|---|
| Systemic Rifamycins | Avoid co‑administration; seek specialist advice |
| Oral Anticoagulants | Monitor INR or anticoagulant effect if indicated |
| Immunosuppressants | Consider specialist pharmacist review |
Cultural Perceptions And Patient Habits
What do Australians talk about when rifaximin is mentioned online?
On forums and social media, rifaximin discussions focus on IBS‑D and SIBO symptom relief and on relapse concerns.
Cost is a common worry because rifaximin is less consistently subsidised than long‑established medicines.
Urban patients often access private gastroenterology clinics and private prescriptions, while rural patients rely more on telehealth and regional hospitals.
Delays in access and travel costs influence adherence in remote communities.
Pharmacies such as community and chain outlets remain trusted to advise on availability and PBS options.
Typical Forum Themes
- Rapid symptom relief versus frustration over relapse.
- Questions about repeat courses and long‑term safety.
- Concerns about cost and PBS access.
Urban Versus Rural Barriers
- Urban: easier specialist access; private scripts more common.
- Rural: telehealth, delayed dispensing, travel costs for repeat prescriptions.
Counselling Tips
- Explain antibiotic stewardship and recurrence risks in plain language.
- Include family or carers in counselling when appropriate.
Availability And Pricing Patterns
Where do Australians get rifaximin and what will it cost?
Availability varies by brand and indication in Australia, so check the TGA Australian Register of Therapeutic Goods and local pharmacies for current stock.
Major retail chains and independent pharmacies can often arrange private supply or order stock into store.
Hospital formularies often supply rifaximin for inpatient indications and in some public hospital outpatient programs for HE.
Online pharmacies and telehealth services increasingly manage private prescriptions and discrete delivery to patients.
In our online pharmacy, rifaximin is available without a prescription, with discreet delivery to Australia in 5-14 days.
Private costs can be substantial compared with PBS‑subsidised medicines, so discuss affordability and possible hospital access options with a pharmacist.
| Purchasing Channel | Typical Time To Supply | Likely Cost / Notes |
|---|---|---|
| Hospital Pharmacy | Same Day To 2 Days | Often supplied for inpatients; outpatient access varies by hospital policy |
| Community Pharmacy (Private Script) | 1–7 Days | Out‑of‑pocket cost; may be able to order stock |
| Online Pharmacy / Telehealth | 5–14 Days | Discrete delivery; confirm legitimate TGA supply |
Comparable Medicines And Preferences
What are the alternatives to rifaximin and how do they compare?
| Indication | Rifaximin Vs Alternative | Key Pros / Cons |
|---|---|---|
| Traveller’s Diarrhoea | Rifaximin Vs Azithromycin / Ciprofloxacin | Rifaximin preferred for non‑invasive E. coli due to low systemic exposure; alternatives needed for invasive pathogens or where resistance is suspected |
| Hepatic Encephalopathy | Rifaximin + Lactulose Vs Lactulose Alone | Add‑on rifaximin reduces recurrence and readmissions; cost and access are considerations |
| IBS‑D / SIBO | Rifaximin Vs Metronidazole / Neomycin | Rifaximin has better tolerability and local action; evidence for long‑term benefit limited and relapse common |
Frequently Asked Questions
- Is rifaximin on the PBS?
PBS listing is indication‑specific and subject to change; many hospital uses are supported locally, but community access often requires private payment—check PBS.gov.au or ask your pharmacist.
- Will rifaximin cure my IBS‑D or SIBO long‑term?
Rifaximin often gives short‑term relief after a 14‑day course, but relapses are common and repeat courses may be used under specialist guidance.
- Is rifaximin safe in liver disease?
Rifaximin is commonly used to prevent hepatic encephalopathy, but severe hepatic impairment requires specialist oversight and closer monitoring.
- Can I take rifaximin with other medicines?
Major drug interactions are uncommon due to low absorption, but always tell a pharmacist or GP about all medicines including hormonal contraceptives and immunosuppressants.
Guidelines For Proper Use
What should pharmacists cover when supplying rifaximin and when should patients be referred?
Confirm the indication, dose and duration for the patient’s condition and explain likely time to symptom change.
For hepatic encephalopathy emphasise adherence because maintenance dosing reduces recurrence risk.
For traveller’s diarrhoea counsel on hydration and when to seek urgent care if systemic features appear.
Storage advice: store at room temperature and keep in the original pack.
Counselling Points
- Explain expected benefit and typical timeline for improvement.
- Stress adherence for HE maintenance dosing.
- Warn about signs of C. difficile infection: worsening diarrhoea, fever, bloody stools.
- Advise on pregnancy and breastfeeding precautions.
Monitoring Schedule
- Traveller’s diarrhoea: review if no improvement within 48–72 hours.
- IBS‑D: follow up within 2–4 weeks for response and relapse planning.
- HE: regular hepatology/GP review as per local protocol; monitor for encephalopathy triggers.
Red Flags For Immediate Referral
- Severe diarrhoea with systemic features or suspected sepsis.
- Sudden severe encephalopathy signs or worsening neurological status.
- Allergic reaction such as facial swelling, difficulty breathing or widespread rash.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 Days |
| Melbourne | Victoria | 5-7 Days |
| Brisbane | Queensland | 5-7 Days |
| Perth | Western Australia | 5-7 Days |
| Adelaide | South Australia | 5-7 Days |
| Canberra | Australian Capital Territory | 5-7 Days |
| Hobart | Tasmania | 5-9 Days |
| Darwin | Northern Territory | 5-9 Days |
| Gold Coast | Queensland | 5-7 Days |
| Newcastle | New South Wales | 5-9 Days |
| Wollongong | New South Wales | 5-9 Days |
| Geelong | Victoria | 5-9 Days |
| Townsville | Queensland | 5-9 Days |
| Cairns | Queensland | 5-9 Days |
| Ballarat | Victoria | 5-9 Days |
Final Practical Notes
Rifaximin is a useful, gut‑targeted antibiotic with evidence for HE prevention and traveller’s diarrhoea, and short‑term benefit in IBS‑D and SIBO.
Cost and PBS status influence access and adherence in Australia, so pharmacists should proactively discuss options including hospital supply pathways.
Document off‑label use carefully and arrange follow‑up according to the indication and local protocols.
If there is any uncertainty about interactions or severe hepatic impairment, seek specialist pharmacist or hepatologist advice before supply.