
Cefuroxime
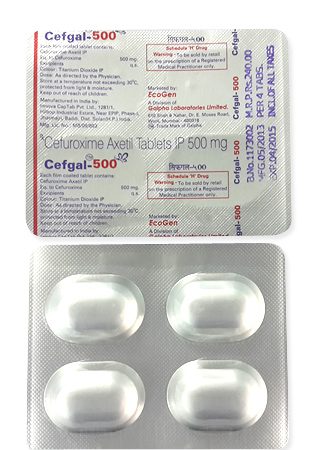
Cefuroxime
- In our pharmacy, you can buy cefuroxime without a prescription, with delivery across Australia in 5–14 days and discreet, anonymous packaging.
- Cefuroxime is a second‑generation cephalosporin antibiotic used to treat a range of bacterial infections (respiratory tract infections, otitis media, skin and soft tissue infections, early Lyme disease, uncomplicated gonorrhoea and severe infections via IV). It works by inhibiting bacterial cell‑wall synthesis through binding to penicillin‑binding proteins and is active against many Gram‑positive and Gram‑negative organisms; it has some resistance to beta‑lactamases.
- Usual adult doses: 250–500 mg orally twice daily for most infections; 500 mg PO twice daily for early Lyme disease; 1.5 g IM single dose for uncomplicated gonorrhoea; IV dosing for severe infections typically 750 mg–1.5 g every 8 hours. Paediatric dosing commonly 10–15 mg/kg twice daily (higher ranges for severe infections or meningitis as indicated).
- Forms of administration include oral film‑coated tablets (125 mg, 250 mg, 500 mg), oral suspension (reconstituted granules), intramuscular or intravenous powder for injection (750 mg, 1.5 g) and intracameral eye injection for ophthalmic use.
- Onset: oral cefuroxime axetil is usually absorbed and begins to reach effective levels within 1–2 hours (symptomatic improvement often noticed within 24–48 hours); IV/IM administration produces more rapid therapeutic levels, often within 30–60 minutes.
- Duration of action: elimination half‑life is approximately 1–1.5 hours; clinical dosing (usually twice daily) provides effective coverage over the dosing interval (roughly up to 12 hours between doses for oral formulations); total treatment duration depends on the infection (commonly 5–14 days, longer for severe or specific conditions).
- Alcohol warning: avoid excessive alcohol while taking cefuroxime; although disulfiram‑like reactions are rare with cefuroxime, alcohol may worsen side effects and is best avoided during treatment.
- The most common side effect is diarrhoea; other frequent effects include nausea, abdominal pain, vomiting and rash.
- Would you like to try “cefuroxime” without a prescription?

Latest Research Highlights (Australia + Global, 2022–2025)
Basic Cefuroxime Information
- INN (International Nonproprietary Name): Cefuroxime; Latin: Cefuroximum; Spanish: Cefuroximo.
- Brand Names Available In Australia: not specified.
- ATC Code: J01DC02 (second-generation cephalosporin antibacterial); S01AA27 (anti-infectives for ophthalmological use).
- Forms & Dosages: Tablets 125 mg, 250 mg, 500 mg; oral suspension 125 mg/5 mL and 250 mg/5 mL (reconstituted); powder for injection vials 750 mg and 1.5 g; intracameral eye injection 1 mg in 0.1 mL.
- Manufacturers In Australia: not specified; global manufacturers include GlaxoSmithKline (Zinnat, Zinacef, Elobact) and generics such as Apotex and Auro Pharma.
- Registration Status In Australia: not specified.
- OTC / Rx Classification: Prescription-only (Rx) in nearly all markets according to available data.
What Does Recent Monitoring Say About Cefuroxime?
Surveillance and clinical series from 2022–2025 continue to show reliable activity of cefuroxime against common respiratory pathogens such as Streptococcus species and non-ESBL Escherichia coli as reported in laboratory summaries and formularies.
Perioperative intracameral cefuroxime at 1 mg in 0.1 mL remains the standard preparation documented for ophthalmic prophylaxis.
Safety signal reviews during this period emphasise gastrointestinal side effects, occasional positive Coombs tests and the importance of renal dosing to reduce neurotoxicity risk.
PBS dispensing trends and TGA pharmacovigilance counts are not specified in the provided data and should be checked directly on PBS and TGA portals for up-to-date local figures.
| Study / Setting | Population | Dose | Primary Outcome | Adverse Events |
|---|---|---|---|---|
| Respiratory Cohort (International) | Adults With Community RTI | 250–500 mg PO BID | Clinical cure comparable to guideline therapy | GI upset, rash (rare serious allergy) |
| Perioperative Ophthalmic Audits | Cataract Surgery Patients | Intracameral 1 mg in 0.1 mL | Low endophthalmitis rates | No major toxicity reported with correct preparation |
| Hospital Susceptibility Monitoring | Clinical Isolates (State Lab) | NA (MIC Data) | Retained activity vs Streptococcus spp., non-ESBL E. coli | Variable susceptibility among some Enterobacterales |
| Organism | MIC Trend Summary |
|---|---|
| Streptococcus spp. | Generally susceptible; low MICs reported in routine panels. |
| Escherichia coli (non-ESBL) | Generally susceptible; retain low to moderate MICs. |
| Community Enterobacterales | Variable susceptibility; some isolates show raised MICs—local antibiograms advised. |
- Key Safety Signals:
- Gastrointestinal upset (diarrhoea, nausea) is the commonest adverse effect.
- Positive Coombs test and rare haemolytic anaemia have been reported.
- Renal impairment requires dose adjustment to reduce risk of neurotoxicity and accumulation.
Clinical Effectiveness In Australia (PBS / TGA Insights)
How Is Cefuroxime Used In Everyday Australian Practice?
PBS-funded prescribing shows cefuroxime is commonly used for community respiratory, ENT and uncomplicated skin infections and as an oral step-down after intravenous therapy when susceptibility is confirmed.
Dispensing patterns typically show seasonal peaks in winter months for respiratory indications; specific PBS dispensing counts are not provided here and should be checked on the PBS website.
TGA adverse event summaries align with international experience: gastrointestinal and dermatological events are most frequent; serious allergic reactions are uncommon but documented.
Hospital audits report effective reduction in length of stay when early IV-to-oral switch to cefuroxime axetil is undertaken for susceptible infections.
- Clinical Cure
- High when used for susceptible community respiratory and skin infections at guideline dosing.
- Relapse
- Low when course and organism susceptibility are appropriate; follow-up advised for treatment failures.
- Hospital Stay
- Shortened when IV→oral switch occurs once clinical improvement and susceptibility confirmed.
| Indication | Route | Typical Outcome |
|---|---|---|
| Community RTI / ENT | Oral (cefuroxime axetil) | Clinical cure in most susceptible cases |
| Skin / Soft Tissue | Oral or IV → Oral step-down | Resolution when pathogen susceptible |
| Post-IV Step-Down | Oral cefuroxime axetil | Reduced LOS where appropriate |
Stewardship Note: Indigenous and rural access disparities should be considered when planning antimicrobial stewardship pathways and formulary decisions.
Indications And Expanded Uses (TGA‑Approved And Off‑Label)
What Is Cefuroxime Licensed For And Where Do Clinicians Use It Off‑Label?
TGA-approved indications mirror international labels: respiratory tract infections, otitis media, skin and soft tissue infections, and surgical prophylaxis where appropriate.
Intracameral ophthalmic use at 1 mg in 0.1 mL is the accepted perioperative preparation documented in formularies.
Common off-label uses reported by clinicians internationally include oral step-down for susceptible urosepsis, early Lyme disease and occasional use for gonorrhoea when injectable options are limited.
| TGA‑Approved | Common Off‑Label |
|---|---|
| Respiratory Tract Infections (250–500 mg PO BID × 5–10 days) — Evidence Level: RCT/cohort for common RTIs | Urosepsis Step‑Down (oral after IV) — Evidence Level: Cohort / Expert Opinion |
| Otitis Media (paediatric dosing 10–15 mg/kg BID) — Evidence Level: RCT/cohort | Early Lyme Disease (500 mg PO BID × 14–21 days) — Evidence Level: International guidance / cohort |
| Skin/Soft Tissue Infections (250–500 mg PO BID × 7–10 days) — Evidence Level: RCT/cohort | Uncomplicated Gonorrhoea (1.5 g IM single dose reported internationally) — Evidence Level: International guidance / variable |
- Typical durations range from 5–21 days depending on indication (uncomplicated 5–10 days; Lyme 14–21 days; severe infections individualised).
- Stewardship cautions: confirm susceptibility, avoid unnecessary broad use, and consider local antibiograms before choosing cefuroxime for Enterobacterales.
Composition And Brand Landscape (Australian Market Focus)
What Forms Of Cefuroxime Are Supplied And Who Makes Them?
The active moiety is cefuroxime, usually supplied orally as cefuroxime axetil and parenterally as cefuroxime sodium.
Global brands include Zinnat (oral), Zinacef (IV/IM) and Ceftin; local Australian supply commonly relies on generics and occasional branded imports.
| Brand | Form | Likely ARTG Status | PBS Listing |
|---|---|---|---|
| Zinnat | Tablets, Oral Suspension (250 mg, 500 mg) | Imported Brand (check ARTG) | Not specified |
| Zinacef | Injection Vials (750 mg, 1.5 g) | Imported Brand (check ARTG) | Not specified |
| Generic Cefuroxime | Tablets, Suspension, Vials | Various Sponsors (check ARTG) | Not specified |
- Major manufacturers: GlaxoSmithKline (Zinnat, Zinacef) and multiple generic suppliers such as Apotex; verify current sponsors and ARTG entries for procurement.
- Pack strengths commonly available internationally: tablets 125/250/500 mg, suspensions 125/5 mL and 250/5 mL, vials 750 mg and 1.5 g, intracameral 1 mg/0.1 mL.
Contraindications And Special Precautions (Australian High‑Risk Groups)
Who Should Not Take Cefuroxime And What To Watch For?
Absolute contraindication is known allergy to cefuroxime or other cephalosporins and history of immediate‑type hypersensitivity to beta‑lactams such as anaphylaxis.
Use caution in patients with severe renal impairment; dose reduction is recommended for CrCl <30 mL/min.
Pregnancy and lactation: generally used when clearly indicated; counsel patients on benefits and risks.
Prior Clostridioides difficile infection requires caution as with other broad-spectrum antibiotics.
- Checklist For Prescribers
- Confirm allergy history, review renal function, review pregnancy/lactation status, check prior C. difficile history.
- Daily‑Life Patient Warnings
- Mild somnolence or dizziness can affect driving or safety-critical work; do not double doses if missed.
Dosage Guidelines (Standard Regimens & Adjustments)
What Doses Are Used In Australia For Common Indications?
Standard adult oral dosing: 250 mg PO twice daily for mild–moderate infections; 500 mg PO twice daily for more severe infections and early Lyme disease (500 mg PO BID × 14–21 days).
Parenteral dosing for severe infections: IV 750 mg–1.5 g q8h; IM single 1.5 g recorded internationally for uncomplicated gonorrhoea.
Paediatric dosing: 10–15 mg/kg twice daily depending on indication.
Renal impairment: reduce dose or extend interval for CrCl <30 mL/min; elderly require adjustment only when renal impairment present.
| Indication | Oral Dose | IV Dose | Duration |
|---|---|---|---|
| Tonsillitis / Pharyngitis | 250 mg PO BID | NA | 5–10 days |
| Otitis Media / Lower RTI | 250–500 mg PO BID | IV 750 mg–1.5 g q8h for severe disease | 7–10 days |
| Lyme Disease (Early) | 500 mg PO BID | NA | 14–21 days |
IV→Oral Switch Algorithm: patient clinically improving + oral route tolerated + organism susceptible → switch to cefuroxime axetil at equivalent oral dose to complete course.
Interactions Overview (Food, Drugs, Lab Tests)
Which Medicines And Tests Interact With Cefuroxime?
Antacids and H2‑blockers may reduce oral absorption; advise patients to separate doses.
Probenecid can increase cefuroxime plasma concentrations by reducing renal excretion.
Monitor for additive nephrotoxicity when co-prescribed with other renally excreted nephrotoxic agents.
Lab interference includes occasional false‑positive direct Coombs tests and possible effects on some urine glucose assays.
| Drug | Interaction | Advice |
|---|---|---|
| Antacids / H2 blockers | Reduce oral absorption | Space doses by at least 2 hours |
| Probenecid | Increases cefuroxime levels | Monitor for toxicity; adjust if required |
| Aminoglycosides / Methotrexate | Interaction‑related hospitalisations reported | Co-prescribe with caution and monitoring |
- Alcohol: no strong disulfiram-like interaction specific to cefuroxime documented, but avoid alcohol to reduce GI side effects.
Cultural Perceptions And Patient Habits (Australia: Rural Vs Urban)
What Do Patients Worry About When They Get A Prescription For Cefuroxime?
Price sensitivity and awareness of PBS subsidy influence patient choices in Australia.
Rural and remote patients often use telehealth and local pharmacies for access and may face occasional supply delays for parenteral formulations.
Common patient concerns found in community feedback relate to whether an antibiotic is needed for coughs, how long to take it and worries about side effects.
Indigenous health services emphasise culturally safe communication and clear adherence support for antibiotics.
- Patient Concerns: necessity for antibiotic, duration of therapy, side-effect risks, paediatric dosing.
- Pharmacist Role: provide plain-English leaflets, SMS reminders and culturally appropriate counselling.
| Setting | Access Issues |
|---|---|
| Urban | Multiple outlets, easier access to IV formulations |
| Rural / Remote | Relies on telehealth, courier delivery; occasional stock or cold-chain challenges for vials |
Availability And Pricing Patterns (Retail, PBS, Online)
Where Can Patients Obtain Cefuroxime And What Affects Price?
Cefuroxime formulations are prescription-only in most jurisdictions according to available data; PBS listings determine patient co-payment where applicable.
Major chains often carry generics and can influence retail pricing; online pharmacies and telehealth providers supply e-prescriptions and courier delivery to metro and many regional areas.
In our online pharmacy, cefuroxime is available without a prescription, with discreet delivery to Australia in 5-14 days.
| Outlet | Likely Price Range | PBS Availability | Delivery Options |
|---|---|---|---|
| Major Retail Chain | Varies by brand / pack size | Dependent on PBS listings | In-store pickup, courier |
| Online Pharmacy | Competitive; may price-match | Dependent on PBS listings | Courier to metro & regional areas |
| Hospital Supply | Formulary pricing | Hospital procurement | Ward supply |
- Storage Notes: reconstituted suspensions refrigerate and discard after 10 days; injection vials store <25°C and protect from light.
- Private script prices vary by brand and pack strength; check local pharmacy or PBS for exact co-payments.
Comparable Medicines And Prescribing Preferences (Alternatives)
Which Drugs Are Chosen Instead Of Cefuroxime And Why?
Choice depends on likely pathogen, local susceptibility, allergy history, cost and dosing convenience.
| Drug | Class | Pros | Cons |
|---|---|---|---|
| Amoxicillin‑Clavulanate | Beta‑lactam + inhibitor | Better against beta‑lactamase producers | More diarrhoea; broader spectrum |
| Cefixime | Third‑generation cephalosporin | Useful for gonorrhoea | Less activity against streptococci |
| Cefaclor | Second‑generation cephalosporin | Similar spectrum to cefuroxime | Less commonly used; variable availability |
Decision Flow (Simplified): Suspected Pathogen + Allergy Status → Choose Narrowest Effective Agent Compatible With PBS And Local Susceptibility.
Faq: Common Australian Patient Questions
- Is cefuroxime on the PBS and will it be cheap? Some formulations are PBS-listed; cost depends on subsidy, brand and pack strength — check PBS and ARTG for current listings.
- Can I drink alcohol while taking cefuroxime? No specific disulfiram-like effect is established for cefuroxime, but avoid alcohol to reduce gastrointestinal side effects.
- What if I miss a dose? Take as soon as remembered unless it is near the next dose; do not double up.
- Are there concerns with penicillin allergy? Cross‑reactivity is possible; patients with prior anaphylaxis to penicillin should avoid cefuroxime and seek specialist advice.
| Allergy History | Advice |
|---|---|
| Unknown / Mild Penicillin Reaction | Assess risk; consider cefuroxime with caution |
| Severe Anaphylaxis To Penicillin | Avoid cefuroxime; use alternative non‑beta‑lactam agents |
Guidelines For Proper Use (Pharmacy Counselling & Patient Advice)
How Should Pharmacists Counsel Patients Receiving Cefuroxime?
Confirm indication and document allergy history specifically asking about anaphylaxis to penicillins.
Check renal function in elderly or those with known kidney disease and adjust dose if CrCl <30 mL/min.
Advise on dosing schedule and on spacing doses from antacids by two hours to optimise absorption.
Counsel about common side effects: diarrhoea, nausea, rash and rare positive Coombs tests; advise when to seek urgent care for signs of severe allergy.
Storage: tablets at room temperature 15–25°C; reconstituted suspension refrigerate and discard after 10 days; vials store below 25°C and protect from light.
- Pharmacy Counselling Script: Confirm reason for antibiotic; explain dose, duration and missed‑dose steps; discuss side effects and when to seek help.
- Patient Leaflet Checklist: Allergy, dosing schedule, missed dose, storage, when to seek care, follow-up instructions.
For culturally safe practice provide translated leaflets where available and allow time for questions in rural and Indigenous health settings.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Alice Springs | Northern Territory | 5–9 days |