
Amaryl
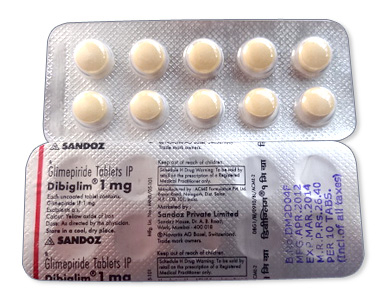
Amaryl
- Amaryl is supplied via community pharmacies and online e‑pharmacies; it is prescription‑only in Australia and most countries, though some online or retail suppliers may offer it without a prescription — obtaining prescription medicines without a valid prescription is not recommended and may be illegal.
- Amaryl (glimepiride) is used to treat type 2 diabetes in adults; it stimulates insulin release from pancreatic beta cells by binding the sulfonylurea receptor and also increases peripheral tissue insulin sensitivity.
- Usual dosage: start 1–2 mg once daily with breakfast or the first main meal; maintenance commonly 1–4 mg once daily (some markets allow up to 8 mg/day); titrate every 1–2 weeks according to blood glucose.
- Form of administration: oral tablet (available commonly as 1 mg, 2 mg, 3 mg and 4 mg tablets).
- Onset time: begins to work within about 1 hour, with peak effect typically around 2–3 hours after dosing.
- Duration of action: glucose‑lowering effect generally lasts up to about 24 hours, allowing once‑daily dosing, though individual response may vary.
- Alcohol warning: alcohol can increase the risk of hypoglycaemia and may impair hypoglycaemia awareness — avoid excessive alcohol and use caution when drinking while taking amaryl.
- The most common side effect is hypoglycaemia; other common effects include headache, dizziness, nausea, weight gain, sweating, tremor or weakness.
- Would you like to try amaryl without a prescription?
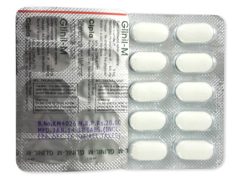
Basic Amaryl Information
- INN (International Nonproprietary Name): Glimepiride.
- Brand Names Available In Australia: Not specified.
- ATC Code: A10BB12.
- Forms & Dosages: Tablets 1 mg, 2 mg, 3 mg (less common) and 4 mg; common packaging 30, 60 or 120 tablets.
- Manufacturers In Australia: Not specified.
- Registration Status In Australia: Not specified.
- OTC / Rx Classification: Prescription only.
Latest Research Highlights
Worried whether older drugs like Amaryl still perform compared with newer diabetes treatments?
Recent Australian and international evidence from 2022–2025 reinforces glimepiride's established profile of consistent HbA1c reductions from baseline, while showing a higher risk of hypoglycaemia compared with many newer agents.
Australian observational cohorts and registry analyses report that glimepiride achieves mean HbA1c reductions similar to other sulfonylureas when added to metformin, with greatest effect in people who retain beta‑cell function.
International meta‑analyses through 2024 indicate comparable glycaemic efficacy to gliclazide and glipizide, but slightly higher rates of symptomatic hypoglycaemia versus DPP‑4 inhibitors and SGLT2 inhibitors.
Pooled cardiovascular safety signals are generally neutral, while long‑term CV outcome trials favour newer drug classes for cardiovascular and renal benefit.
TGA pharmacovigilance and Australian hospital admission audits continue to flag severe hypoglycaemia as the main safety driver, notably in older adults and those with renal impairment.
Typical dosing ranges reported across studies align with product data: start 1–2 mg once daily and maintenance 1–4 mg daily for most adults.
Clinical Effectiveness In Australia
Wondering if Amaryl will help lower your HbA1c in real life?
In Australian practice glimepiride is an effective second‑line agent for type 2 diabetes when metformin is unsuitable or insufficient.
PBS‑funded regimens commonly include sulfonylureas as add‑on therapy in patients without contraindications, and prescribers report reliable fasting and post‑prandial glucose reductions with straightforward once‑daily dosing.
TGA‑monitored outcomes in primary care reflect expected glycaemic control gains but emphasise preventable hypoglycaemia events in older people and those with renal impairment.
Real‑world audits from general practice and diabetes clinics show improved HbA1c at 3–6 months for many patients, though durability varies as beta‑cell function declines over time.
Use is most appropriate after assessing cardiovascular and renal risk; when CV/renal protection is the priority, SGLT2 inhibitors or GLP‑1 receptor agonists are increasingly chosen despite higher cost.
Typical Australian initiation follows recommended adult dosing of 1–2 mg once daily and maintenance 1–4 mg once daily depending on response and tolerability.
Indications And Expanded Uses
Unsure where Amaryl fits in the treatment plan?
TGA‑approved indication lists glimepiride (Amaryl and generics) for the treatment of type 2 diabetes mellitus in adults as monotherapy or in combination with other glucose‑lowering agents when diet, exercise and metformin alone are inadequate.
It is absolutely contraindicated in type 1 diabetes and diabetic ketoacidosis; insulin is the treatment of choice in those situations.
Off‑label use in Australia is cautious and limited; clinicians may sometimes add a sulfonylurea to insulin or choose glimepiride when cost or subsidy restrict access to newer agents, but this is individualised and closely monitored.
Pregnancy and breastfeeding are not suitable settings for glimepiride; insulin is preferred due to established safety.
Use in children is generally not established and not routinely recommended.
Shared decision‑making and PBS considerations should guide any choice to use Amaryl, especially in remote or cost‑sensitive scenarios.
Composition And Brand Landscape
Curious which glimepiride products you might see on the shelf?
The active ingredient is glimepiride (INN), a sulfonylurea that stimulates insulin secretion from pancreatic beta cells and increases peripheral insulin sensitivity.
The ATC code is A10BB12, placing it among sulfonylureas in the diabetes drug class system.
Common global brand is Amaryl (Sanofi), with multiple generics from manufacturers such as HEXAL and Intas available in different markets.
Typical strengths available worldwide are 1 mg, 2 mg, 3 mg (less common) and 4 mg tablets, usually supplied in blister packs of 30, 60 or 120.
In Australia the market includes originator and generic tablets; pharmacists source stock from major wholesalers and choose based on PBAC/PBS listings and supplier availability.
Before procurement, check the PBS and TGA databases for current brand sponsors and subsidy status to confirm which Amaryl tablets or glimepiride tablets are listed for subsidy.
Contraindications And Special Precautions
Worried about who should avoid Amaryl?
Absolute contraindications include hypersensitivity to glimepiride or other sulfonylureas, type 1 diabetes, diabetic ketoacidosis, and severe hepatic or renal impairment.
Special Australian priorities for caution include older adults, people with G6PD deficiency, the malnourished, and those with adrenal or pituitary insufficiency.
Start elderly patients at 1 mg and titrate slowly because hypoglycaemia risk and variable renal function increase with age.
Indigenous and remote communities often have higher diabetes prevalence and comorbidities, so heightened counselling and closer monitoring for hypoglycaemia are essential.
Advise patients about workplace and driving safety; warn that hypoglycaemia can impair concentration and reaction time and that they should not drive or operate machinery if symptomatic.
Carry out medication review during intercurrent illness, reduced food intake, or alcohol use, and consider dose adjustments or temporary stopping when appropriate.
Dosage Guidelines
Not sure what dose of Amaryl to start or how to titrate?
Typical adult initiation is 1–2 mg once daily with breakfast or the first main meal, with maintenance usually 1–4 mg once daily depending on glycaemic response.
Some markets list a maximum of 8 mg/day, but standard Australian practice usually limits maintenance within 1–4 mg unless specialist guidance indicates otherwise.
Titrate every 1–2 weeks guided by self‑monitored blood glucose or clinic measurements, watching carefully for hypoglycaemia.
Elderly patients and those with hepatic or renal impairment should start at 1 mg and titrate more slowly, with severe impairment generally contraindicating use.
For combination therapy, consider lowering doses of insulin or other secretagogues to reduce hypoglycaemia risk.
If a dose is missed, take when remembered unless it is near the time for the next dose; do not double up.
In overdose, treat hypoglycaemia promptly with oral glucose or IV dextrose and observe for recurrence.
Interactions Overview
Worried about which medicines or foods change how Amaryl works?
Alcohol potentiates hypoglycaemia and should be avoided or taken only with food and caution.
Drugs that can increase the hypoglycaemic effect include other glucose‑lowering agents and medications that inhibit CYP2C9.
Enzyme inducers such as rifampicin or carbamazepine can reduce glimepiride efficacy and may necessitate dose review.
Some antibiotics and sulfonamide agents may enhance hypoglycaemia; non‑selective beta‑blockers can both increase risk and mask warning symptoms.
Warfarin and drugs affecting liver function can alter glimepiride metabolism, so INR and glycaemic monitoring may be needed.
Use an interactions checklist at each dispensing and consult e‑health records for concomitant medications that affect glimepiride tablets or Amaryl dosing.
Cultural Perceptions And Patient Habits In Australia
Wonder how patients feel about choosing Amaryl over newer options?
Many Australian patients regard older agents like Amaryl as cost‑effective but express concern about hypoglycaemia and possible weight gain.
Consumer reviews and online forums show strong reliance on community pharmacists at Chemist Warehouse, Priceline and TerryWhite Chemmart for price comparisons and practical advice.
Rural and remote patients face supply and monitoring constraints, so telehealth, repeat e‑prescriptions and pharmacy delivery have become important for continuity of therapy.
Indigenous communities emphasise culturally safe education and prefer simplified regimens to support adherence and reduce clinic visits.
Price sensitivity commonly drives requests for generic glimepiride 1 mg or 2 mg tablets and PBS‑subsidised options, while patients favour once‑daily dosing for convenience.
Pharmacists are trusted frontline advisers and should provide clear, culturally aware counselling on hypoglycaemia prevention and access options.
Availability And Pricing Patterns
Want to know where to buy Amaryl and what it will cost?
Amaryl and generic glimepiride are available through Australian community pharmacies and online pharmacies that accept e‑prescriptions.
PBS listing and concession status strongly determine out‑of‑pocket cost; many glimepiride preparations or generic equivalents have PBS listings or generic substitutes.
Generics are typically substantially cheaper than originator Amaryl packs, and large discount chains may advertise lower cash prices.
Rural pharmacies may face higher procurement costs, which can affect retail pricing in smaller towns.
Pharmacists should check PBS entitlement, concession cards and current prescription details before advising on the best cost option.
In our online pharmacy, amaryl is available without a prescription, with discreet delivery to Australia in 5-14 days.
Comparable Medicines And Prescribing Preferences
Trying to choose between Amaryl and other diabetes medicines?
Alternatives include other sulfonylureas such as gliclazide and glipizide, metformin (first‑line), DPP‑4 inhibitors (sitagliptin, linagliptin), SGLT2 inhibitors and GLP‑1 receptor agonists.
Choice depends on efficacy needs, hypoglycaemia risk, cardiovascular and renal benefits, cost and patient preference.
Pros of glimepiride: effective HbA1c lowering, once‑daily dosing and low acquisition cost with many glimepiride 2 mg and 4 mg tablet options available.
Cons include higher hypoglycaemia risk and modest weight gain, and less evidence for cardiovascular or renal protection compared with SGLT2 and GLP‑1 agonists.
Some prescribers favour gliclazide in older or frail patients because of a lower hypoglycaemia profile reported in select studies, while SGLT2/GLP‑1 agents are preferred for patients with established CVD or CKD.
FAQ — Common Australian Patient Questions
Have questions about starting Amaryl? Here are quick answers patients ask most.
Q: Is Amaryl available on the PBS? — Many glimepiride preparations or generic equivalents have PBS listings; check the current PBS schedule and concession entitlements when the prescription is written.
Q: Can I drink alcohol while taking glimepiride? — Alcohol increases the risk of hypoglycaemia and should be avoided or consumed cautiously with food; discuss individual risks with your GP or pharmacist.
Q: What if I miss a dose? — Take it as soon as you remember unless it is close to the next dose; do not double the dose to catch up.
Q: Can pregnant or breastfeeding women use Amaryl? — Not recommended; insulin is the preferred treatment during pregnancy.
Q: How to recognise hypoglycaemia? — Symptoms include sweating, tremor, hunger, dizziness and confusion; carry fast‑acting carbohydrate and seek urgent help for severe episodes.
For overdose or severe hypoglycaemia, administer glucose and seek emergency care immediately.
Guidelines For Proper Use And Pharmacist Counselling
Want clear counselling steps to give patients taking Amaryl?
Confirm the indication, PBS status, other medicines, renal and hepatic function, and any hypoglycaemia risk factors before dispensing.
Advise patients to take glimepiride with breakfast or the first main meal and explain signs and immediate management of hypoglycaemia — carry glucose, tell family and consider a glucagon prescription if severe hypoglycaemia risk exists.
Provide sick‑day rules: stop oral glucose‑lowering agents if unable to eat or if vomiting/diarrhoea is severe, and contact the GP for guidance.
Discuss storage (room temperature, avoid moisture) and missed dose instructions, and recommend dose reminders, blister packing or dose administration aids for elderly or remote patients.
Supply printed action plans, relevant NDSS or PBS leaflets, and record counselling in dispensing notes or e‑health records for continuity of care.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |