
Metformin + Glibenclamide
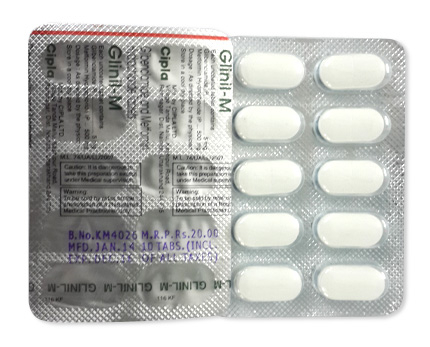
Metformin + Glibenclamide
- In our pharmacy you can buy metformin + glibenclamide without a prescription, with delivery across Australia; note that the combination is classified as prescription‑only in most countries and you should consult a healthcare professional if possible.
- Metformin + glibenclamide is used to treat type 2 diabetes by combining metformin (reduces hepatic glucose production and improves insulin sensitivity) with glyburide/glibenclamide (a sulfonylurea that stimulates pancreatic insulin secretion).
- Usual starting dose is 1.25 mg/250 mg once or twice daily with meals, titrated every 2 weeks as needed; maximum total daily dose is 20 mg glyburide / 2000 mg metformin.
- The form of administration is oral tablets (common strengths: 1.25 mg/250 mg, 2.5 mg/500 mg, 5 mg/500 mg).
- Initial blood‑glucose lowering from the glyburide component can occur within 1–3 hours; metformin begins to work within a few hours but full glycaemic effects develop over days to weeks.
- Duration of effect is generally 12–24 hours depending on dose and individual response; regular daily dosing is required for sustained control.
- Avoid excessive alcohol: alcohol increases the risk of metformin‑associated lactic acidosis and can worsen hypoglycaemia risk with glyburide.
- The most common side effect is gastrointestinal upset (nausea, diarrhoea, abdominal discomfort); hypoglycaemia (shakiness, sweating, confusion) is also a significant risk especially if meals are missed.
- Would you like to try metformin + glibenclamide without a prescription?


Basic Metformin + Glibenclamide Information
- INN (International Nonproprietary Name): Metformin and Glyburide.
- Brand Names Available In Australia: not specified.
- ATC Code: A10BD03.
- Forms & Dosages: Oral tablets in glyburide/metformin strengths 1.25mg/250mg, 2.5mg/500mg and 5mg/500mg.
- Manufacturers In Australia: not specified (global generics include Teva, Apotex, Aurobindo, Sandoz; Indian manufacturers include USV, Micro Labs).
- Registration Status In Australia: not specified.
- OTC / Rx Classification: Prescription only (Rx) globally, per product information.
Latest Research Highlights
Worried about whether older combination tablets still make sense in modern diabetes care?
Recent clinical literature from 2022–2025 continues to show that metformin plus a sulfonylurea produces meaningful glycaemic reductions compared with metformin alone.
Large observational cohorts and meta‑analyses report greater HbA1c lowering, especially when baseline HbA1c is ≥8%.
The trade‑off is a consistently higher rate of hypoglycaemia and modest weight gain when the regimen contains glyburide (glibenclamide).
Australian registry analyses and TGA adverse‑event summaries highlight hypoglycaemia reports concentrated in older adults and people with impaired renal function.
Comparisons with newer classes since 2022 show that SGLT2 inhibitors or DPP‑4 inhibitors added to metformin often give comparable glycaemic control with lower hypoglycaemia risk.
These newer combinations also demonstrate better cardiorenal outcomes in many trials, shifting prescribing in numerous Australian clinics.
Safety signals for lactic acidosis remain rare and are tied to metformin in the context of severe renal impairment or major intercurrent illness.
Evidence gaps remain, notably few contemporary RCTs comparing metformin+glibenclamide directly with modern combos in Australian primary‑care populations.
Real‑world PBS‑linked analyses are needed to reflect current Australian prescribing and outcome patterns.
For clinicians, the decision increasingly balances HbA1c potency with hypoglycaemia risk, renal status and cardiorenal benefits.
Clinical Effectiveness In Australia
Do patients achieve meaningful HbA1c drops with a fixed‑dose metformin + glibenclamide tablet in everyday practice?
In Australian primary care, escalation to dual oral therapy typically produces average HbA1c reductions of about 0.8–1.5%, depending on baseline control and adherence.
PBS data and primary‑care audits support those real‑world figures, though individual responses vary widely.
Effectiveness is tempered by patient factors: older adults, people with chronic kidney disease and some Indigenous communities show higher adverse‑event rates and may be directed to alternatives.
The TGA post‑market surveillance database flags hypoglycaemia as the most commonly reported safety issue with sulfonylurea‑containing combinations.
Severe lactic acidosis reports remain uncommon and occur predominantly where renal function is poor or during acute illness.
Beyond glycaemic control, newer metformin combinations with SGLT2 inhibitors have shown superior heart‑kidney protective effects in recent trials, informing specialist and GP choices.
On the PBS, access and subsidy rules influence whether clinicians choose a fixed‑dose glyburide/metformin tablet or prescribe separate agents such as gliclazide or glimepiride with metformin.
Clinicians should individualise therapy, weighing HbA1c lowering against hypoglycaemia risk and long‑term cardiorenal benefits.
Baselines such as eGFR, weight and occupational risks should guide which dual therapy is preferred for each patient.
Indications & Expanded Uses (TGA & Off‑Label)
Are there situations where a metformin + glyburide tablet is appropriate or clearly off‑limits?
TGA‑aligned indications focus on Type 2 diabetes in adults who need dual oral therapy after metformin monotherapy is insufficient.
Product information specifies starting at 1.25mg/250mg once or twice daily with meals, titrating every two weeks up to a maximum of 20mg/2000mg per day.
The combination is not recommended for Type 1 diabetes, children, pregnancy or lactation.
Off‑label uses sometimes seen in practice include short‑term perioperative bridging under close monitoring or short‑term use in patients who decline injectables, but these are clinician‑judgement calls.
Where the fixed‑dose product is not listed on the PBS, prescribers may use separate PBS items for metformin plus a sulfonylurea to secure subsidy for patients meeting criteria.
Approved Uses: Type 2 diabetes in adults requiring dual oral therapy after metformin monotherapy is inadequate.
Not Recommended: Type 1 diabetes, pregnancy, lactation, paediatric use and severe renal impairment (eGFR <30 mL/min).
Decision Flowchart For Prescribers: confirm Type 2 diagnosis → check eGFR and comorbidities → consider hypoglycaemia risk and patient preference → choose fixed‑dose or separate agents per PBS availability and subsidy.
Composition & Brand Landscape
How does a glyburide/metformin tablet work and what brands are common?
Fixed‑dose tablets combine metformin, a biguanide that improves insulin sensitivity, with glyburide (also called glibenclamide), a sulfonylurea that increases insulin secretion.
Common tablet strengths are 1.25mg/250mg, 2.5mg/500mg and 5mg/500mg (glyburide/metformin).
The ATC code for the combination is A10BD03, under combinations of oral blood glucose‑lowering drugs.
Glucovance was the original combined product from Bristol‑Myers Squibb, and generics now dominate the global market.
Global generics are produced by manufacturers such as Teva, Apotex, Aurobindo and Sandoz, with multiple Indian suppliers including USV and Micro Labs.
In Australia, fixed‑dose combos may be supplied as generics or clinicians may prescribe generic metformin products (Glucophage, Siofor) plus sulfonylureas depending on PBS listings and patient subsidy eligibility.
Synonyms and equivalents: glyburide is the same agent commonly known as glibenclamide in some markets.
When counselling, remind patients that tablet appearance and manufacturer can vary because generics dominate the supply chain.
Contraindications & Special Precautions
Who should definitely avoid metformin + glibenclamide, and who needs careful monitoring?
Absolute contraindications include severe renal impairment (eGFR <30 mL/min), metabolic acidosis including diabetic ketoacidosis, known hypersensitivity to metformin or glyburide, and Type 1 diabetes.
Relative contraindications where caution is required include older age, mild to moderate renal dysfunction, hepatic impairment, major surgery, trauma and alcohol abuse.
Australian high‑risk groups include older adults and many Indigenous communities with higher CKD prevalence, so renal screening is essential before starting therapy.
Advise patients to pause metformin during acute illnesses that may cause dehydration, hypoxia or AKI risk and before major surgery as clinically advised.
Occupational precautions: warn about hypoglycaemia risk when driving, operating machinery or working at heights and advise carrying fast‑acting carbohydrate.
Baseline tests before initiation should include eGFR and liver function tests, with periodic monitoring thereafter depending on age and comorbidities.
In renal decline approaching eGFR <30 mL/min, stop the combination and consider alternative glucose‑lowering agents that are safer in CKD.
Dosage Guidelines
What dosing schedule is used and how should clinicians adjust for comorbidities?
Initiate treatment at 1.25mg/250mg once or twice daily with meals, and increase the dose every two weeks based on glycaemic response and tolerability.
The maximum recommended combined dose is 20mg glyburide with 2000mg metformin per day.
For elderly patients and those with borderline renal function, start at the lowest dose and monitor renal function more frequently.
The combination is contraindicated when eGFR is below 30 mL/min and should be used with caution or avoided when eGFR is 30–45 mL/min depending on individual assessment.
Hepatic impairment is a reason to avoid the combination because of increased risk of toxicity.
Practical Australian advice: align doses with main meals to reduce the risk of hypoglycaemia and document changes in My Health Record if the patient consents.
Missed dose instructions: take as soon as remembered unless near the next dose and do not double the next dose.
Interactions Overview
Which common medicines and situations change how this combination works or increase risks?
Alcohol raises the risk of metformin‑associated lactic acidosis and can also potentiate hypoglycaemia when combined with sulfonylureas, so counsel patients to avoid heavy drinking.
Cimetidine and some other drugs can increase metformin levels by affecting renal excretion; review concomitant medicines that impact kidney function.
Beta‑blockers may blunt adrenergic warning symptoms of hypoglycaemia, so inform patients taking these agents to monitor glucose more closely.
ACE inhibitors and some SSRIs can modify glucose control and may increase hypoglycaemia risk in sensitive patients.
Iodinated contrast media: withhold metformin around procedures that require IV contrast if there is an AKI risk and re‑check renal function before restarting the drug.
Herbal products such as St John’s wort and high‑dose vitamin C can interfere with glucose measurements or interactions; ask about supplements at each visit.
Report suspected adverse drug interactions to the TGA adverse‑event reporting system as part of good clinical governance.
Cultural Perceptions & Patient Habits
How do different Australian communities view a combination diabetes tablet and how does that affect use?
Many patients view fixed‑dose combination tablets as convenient and cost‑effective, especially when PBS subsidy applies for at least one component.
Price‑sensitive consumers often favour PBS‑subsidised generics and may shop across major chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart for best value.
Rural patients may prefer less frequent dosing and reliable supply due to travel distances to pharmacies, and telehealth/e‑prescribing has improved access for some remote communities.
Trust in pharmacists is high and many patients consult a pharmacist first for medicine‑related questions and hypoglycaemia advice.
Indigenous Australians have higher rates of Type 2 diabetes and CKD and need culturally safe care, shared decision‑making and renal screening before initiating therapies with renal risk.
Patient forums and social media often reflect concern about hypoglycaemia and a preference for newer agents with lower hypoglycaemia risk despite higher costs.
Aged‑care residents and their carers require individualised plans, simpler regimens where possible and clear hypoglycaemia action plans.
Availability & Pricing Patterns
Where can patients get this tablet, and what will it cost them?
The fixed‑dose metformin+glibenclamide product is available worldwide but supply is dominated by generics from manufacturers such as Teva, Apotex, Aurobindo and Sandoz.
In Australia, availability depends on ARTG registration and PBS listings; when the fixed‑dose product is not listed, prescribers commonly supply metformin and a sulfonylurea separately to secure PBS subsidy.
Major retail chains and accredited online pharmacies distribute standard oral formulations and telehealth e‑prescriptions have improved access for remote patients.
In our online pharmacy, metformin + glibenclamide is available without a prescription, with discreet delivery to Australia in 5-14 days.
PBS subsidy substantially reduces the patient cost where criteria are met; private prices vary between pharmacies and online suppliers.
Price‑sensitive patients often compare private pricing across national chains and accredited online pharmacies to find the best private price where PBS does not apply.
Comparable Medicines And Preferences
Which alternatives should be considered and why might clinicians choose them?
Alternatives in Australia include metformin plus gliclazide or glimepiride, and combinations of metformin with DPP‑4 inhibitors or SGLT2 inhibitors.
Gliclazide is often preferred over glyburide for a lower hypoglycaemia risk profile in many patients.
SGLT2 inhibitors with metformin offer cardiorenal benefits and lower hypoglycaemia risk, which is particularly attractive for patients with cardiovascular or renal risk.
DPP‑4 inhibitors provide moderate glucose lowering with low hypoglycaemia risk and good tolerability for older adults.
Choice considerations include hypoglycaemia risk, renal function, effects on weight and PBS subsidy access, with clinicians balancing efficacy against safety and cost.
A side‑by‑side approach helps: sulfonylureas give strong HbA1c lowering but higher hypoglycaemia; SGLT2i give cardiorenal protection and weight loss but have eGFR thresholds and PBS criteria.
FAQ
Q: Is metformin + glibenclamide on the PBS?
A: Some fixed‑dose products may be listed, but often prescribers use separate PBS items for metformin plus a sulfonylurea; check the current PBS schedule and ARTG.
Q: What should I do for a hypoglycaemic episode?
A: Treat low blood sugar with 15–20g fast‑acting carbohydrate such as glucose gel or juice, recheck blood glucose after 15 minutes and repeat if needed; seek urgent care for severe symptoms.
Q: Can I drink alcohol while taking this combination?
A: Avoid heavy drinking because alcohol increases the risk of lactic acidosis with metformin and can worsen hypoglycaemia with sulfonylureas.
Q: How often should kidney function be checked?
A: Obtain baseline eGFR before initiation and monitor periodically thereafter, increasing frequency in older patients, those with CKD or when starting interacting medicines.
Emergency Protocols: for suspected lactic acidosis seek urgent medical attention immediately; for overdose, call emergency services and inform clinicians of combined metformin and glyburide ingestion.
Guidelines For Proper Use
What should pharmacists cover at counselling and what monitoring is recommended?
Confirm the diagnosis of Type 2 diabetes and review baseline renal function (eGFR) before dispensing the combination.
Counsel patients to take the tablet with meals to lower hypoglycaemia risk and to carry fast‑acting carbohydrate for emergencies.
Provide a written hypoglycaemia action plan and advise patients to inform family, employer or carers about signs and treatment steps.
Document counselling in My Health Record with patient consent and liaise with the GP regarding PBS criteria and any need to prescribe separate agents.
Advise patients to withhold metformin prior to procedures involving IV contrast if there is AKI risk, and to restart only after renal function is rechecked.
Report adverse events to the TGA and encourage patients to seek urgent review for severe hypoglycaemia or symptoms of lactic acidosis such as rapid breathing, severe lethargy or muscle pain.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |