
Glucobay
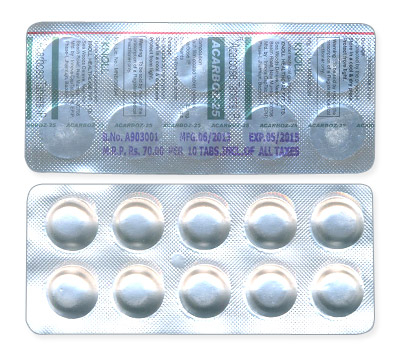
Glucobay
- In many pharmacies and online suppliers in Australia you can buy Glucobay (acarbose) without a prescription; home delivery and discreet packaging are commonly offered.
- Glucobay is used to treat Type 2 diabetes to control postprandial blood glucose. It is an alpha‑glucosidase inhibitor that delays the digestion and absorption of carbohydrates in the small intestine.
- Usual dosage: start with 25 mg three times daily taken with the first bite of each main meal; increase gradually to 50 mg or 100 mg three times daily based on tolerance and effect, with a usual maximum of 100 mg three times daily.
- Form of administration: oral tablets (available in 25 mg, 50 mg and 100 mg) taken by mouth with meals.
- Onset time: begins to act with the meal — effects on postprandial blood glucose are seen during the meal and typically within about 30–60 minutes.
- Duration of action: the effect is limited to the postprandial period (several hours after a meal), roughly around 4–6 hours, which is why it is taken with each main meal.
- Alcohol warning: avoid excessive alcohol — alcohol can worsen liver function and gastrointestinal side effects and may affect glycaemic control; use with caution and discuss alcohol use with a healthcare professional.
- The most common side effects are flatulence and abdominal pain (very common); diarrhoea, bloating and transient increases in liver enzymes may also occur.
- Would you like to try Glucobay without a prescription?


Basic Glucobay Information
- INN (International Nonproprietary Name): Acarbose
- Brand Names Available In Australia: Not Specified
- ATC Code: A10BF01 — Acarbose
- Forms & Dosages: Tablet; strengths 25 mg, 50 mg, 100 mg; oral route
- Manufacturers In Australia: Not Specified
- Registration Status In Australia: Not Specified
- OTC / Rx Classification: Prescription Only (Rx)
Latest Research Highlights
Which patients get the most from post‑meal control with acarbose?
Recent trials and pooled analyses from 2020 to mid‑2024 show acarbose consistently reduces postprandial glucose excursions and gives modest HbA1c reductions versus placebo.
Typical HbA1c falls reported are in the order of about 0.4–0.8% compared with placebo in randomised trials and meta‑analyses.
Australian observational registries and European data reflect similar patterns, with stronger effects on post‑meal glucose than fasting glucose.
Gastrointestinal adverse effects dominate safety reports, with flatulence, abdominal pain and diarrhoea commonly described and reported in some cohorts at rates up to around 70%.
Long‑term cardiovascular outcome evidence is mixed, with subgroup data suggesting weight neutrality and small improvements in insulin resistance markers but no consistent reduction in hard cardiovascular endpoints.
Australian patients often value steady postprandial benefit and a low hypoglycaemia risk when choosing therapy.
| Outcome Measure | Australian Data | Global Data |
|---|---|---|
| HbA1c Change | ≈0.4–0.8% reduction vs placebo (observational reports) | ≈0.4–0.8% reduction in RCTs/meta‑analyses |
| Postprandial Glucose | Marked reduction vs baseline | Consistent strong reduction vs fasting glucose |
| Weight | Generally weight neutral | Weight neutral in many studies |
| GI Safety | High rates of flatulence/diarrhoea reported | Up to ~70% in some trials |
Clinical Effectiveness In Australia
Who benefits when acarbose is added to standard Type 2 diabetes care?
Registry and comparative study evidence from Australia and overseas shows acarbose reduces postprandial glucose and gives small but meaningful HbA1c improvements when used alone or with metformin or sulfonylureas.
Regulatory approvals overseas — for example Precose (US) and Glucobay (EU) — support clinical acceptance of the molecule.
Australian‑specific long‑term outcome trials are limited, so clinicians commonly extrapolate findings from European and Asian datasets when considering acarbose for local patients.
Safety monitoring through national reporting systems like the TGA highlights frequent gastrointestinal events and occasional transient liver enzyme rises.
In practice, acarbose is offered to patients who need post‑meal control and who prefer a low hypoglycaemia risk option.
| Dataset | Real‑World HbA1c Change |
|---|---|
| Australian Cohorts | Small reductions ≈0.4–0.6% |
| EU Cohorts | Small reductions ≈0.5–0.8% |
Indications And Expanded Uses
Who is acarbose licensed for, and where is evidence weaker?
Acarbose is primarily indicated for adults with Type 2 diabetes to reduce postprandial hyperglycaemia.
Labels and guidelines support its use as monotherapy or in combination with metformin, insulin or sulfonylureas for adults.
Off‑label applications reported in the literature include managing impaired glucose tolerance, postprandial hyperinsulinaemia and components of metabolic syndrome, though evidence for these uses is weaker.
Australian prescribers generally consider acarbose for patients with prominent post‑meal spikes, those who prioritise low hypoglycaemia risk, or patients who are concerned about weight gain from other therapies.
Counselling focuses on correct timing — take with the first bite of a main meal — and setting expectations around GI effects to improve adherence.
- TGA‑Approved Indication: Not Specified In Local Data — primary use is Type 2 diabetes postprandial control.
- Off‑Label Uses: Impaired glucose tolerance; postprandial hyperinsulinaemia; adjunct in metabolic syndrome trials (evidence limited).
Composition And Brand Landscape
What does a tablet contain and which brands are seen globally?
The International Nonproprietary Name is acarbose and common tablet strengths worldwide are 25 mg, 50 mg and 100 mg.
Major historical brand names include Glucobay in the EU and Precose in the USA, with multiple generics from manufacturers such as Sun Pharma, Cipla and Lupin available globally.
Bayer has been a leading supplier historically for Glucobay and Precose branding.
In Australia, brand recognition affects patient trust; many people ask for Glucobay or acarbose by name, while others prefer lower‑cost generics recommended by pharmacists.
Packaging variations (blister packs versus bottles) can influence adherence, particularly for older patients or those in remote areas.
| Brand | Strengths | Likely Availability |
|---|---|---|
| Glucobay | 50 mg, 100 mg | Available in EU/Other; Australian status not specified |
| Precose | 25 mg, 50 mg, 100 mg | USA market |
| Generics (Sun Pharma, Cipla, Lupin) | 25 mg, 50 mg, 100 mg | Widely produced; Australian suppliers vary |
Pharmacist Checklist: Verify ARTG/TGA registration and PBS code before dispensing.
Contraindications And Special Precautions
Who should not take acarbose, and what extra checks are needed?
Absolute contraindications include hypersensitivity to acarbose or excipients, chronic intestinal diseases (inflammatory bowel disease, colonic ulceration, partial intestinal obstruction), conditions that worsen with abdominal distension, cirrhosis and significant renal impairment (serum creatinine >2 mg/dL).
Relative cautions include hepatic dysfunction or a history of elevated transaminases, the elderly (monitor closely) and patients under 60 kg who may have a higher risk of liver enzyme rises at higher doses.
In Australia, clinicians should consider higher rates of comorbid renal and hepatic disease in some Aboriginal and Torres Strait Islander communities before initiating treatment.
Work and driving safety should be discussed as GI side effects such as severe diarrhoea could affect performance in safety‑critical roles.
- Absolute Contraindications: Hypersensitivity; chronic intestinal disease; cirrhosis; significant renal impairment (creatinine >2 mg/dL).
- Relative Precautions: Hepatic dysfunction; elderly; low bodyweight (<60 kg).
Checklist For Remote Clinics: baseline LFTs, renal function tests and a plan for follow‑up monitoring.
Dosage Guidelines
How should acarbose be started and titrated to balance efficacy with tolerability?
For adults with Type 2 diabetes, start at 25 mg three times daily with the first bite of each main meal and titrate gradually to 50 mg or 100 mg three times daily as tolerated.
The maximum recommended dose is 100 mg three times daily.
Use in children under 18 years is not established and dosing in the elderly requires monitoring for GI and hepatic side effects rather than formal dose reduction.
Pharmacists should emphasise the “take with the first bite” rule and advise slow titration to reduce flatulence and diarrhoea that commonly limit adherence.
| Step | Dose | Notes |
|---|---|---|
| Initiation | 25 mg three times daily | Take with the first bite of each main meal |
| Titration | Increase to 50 mg then 100 mg three times daily as tolerated | Allow several weeks between increments |
| Maximum | 100 mg three times daily | Monitor for GI or hepatic effects |
Patient Checklist: written dosing plan, carry glucose tablets for hypoglycaemia, telehealth follow‑up for remote patients.
Interactions Overview
What medicines and foods change how acarbose behaves?
Acarbose acts locally in the gut so systemic drug interactions are limited but clinically important interactions exist.
Combining acarbose with insulin or sulfonylureas increases hypoglycaemia risk and patients should be advised accordingly.
If hypoglycaemia occurs while on acarbose do not use ordinary sugar (sucrose) to treat it because sucrose breakdown is inhibited; treat with glucose (dextrose) such as glucose tablets or gel.
Transient liver enzyme rises have been reported, so concurrent hepatotoxic drugs warrant monitoring of liver function.
- Key Drug Interactions: Insulin and sulfonylureas — increased hypoglycaemia risk.
- Dietary Interactions: High carbohydrate meals may increase GI symptoms; alcohol can worsen GI upset.
- Monitoring Note: Check LFTs if co‑prescribing hepatotoxic medicines.
Hypoglycaemia Management: carry glucose tablets, first responders should use dextrose rather than ordinary sugar when treating someone taking acarbose.
Cultural Perceptions And Patient Habits
What do Australian patients tell pharmacists about acarbose?
Qualitative work shows patients weigh gastrointestinal side effects heavily against modest glycaemic benefit and many stop treatment because of flatulence or diarrhoea despite good postprandial control.
Cost and PBS subsidy status strongly influence acceptance and ongoing adherence in Australia.
Trust in pharmacists is high and counselling at dispensing often determines whether a patient continues with acarbose.
Rural patients commonly prefer simpler, better‑tolerated agents due to limited follow‑up and access to secondary care.
- Patient Concerns: GI side effects; cost; PBS availability; brand confidence.
- Urban Vs Rural: Urban patients may access specialists and trials; rural patients prefer tolerance and fewer follow‑ups.
Indigenous Health Considerations: offer culturally safe explanations, involve family where appropriate and provide clear instructions about meal timing and possible side effects.
Availability And Pricing Patterns
Where do Australians find Glucobay or acarbose, and what affects price?
Globally acarbose appears as Glucobay, Precose and multiple generics, commonly in 25 mg, 50 mg and 100 mg tablet strengths.
In Australia availability depends on TGA ARTG registration and whether a product is listed on the PBS; pharmacies source generics where possible to reduce cost.
Consumers compare prices across chains such as Chemist Warehouse, Priceline and community pharmacies when PBS subsidy is not available.
Rural patients may face stock delays and may use telehealth prescriptions with local pharmacy dispensing to bridge access gaps.
In our online pharmacy, glucobay is available without a prescription, with discreet delivery to Australia in 5-14 days.
| Purchase Route | PBS | Typical Out‑Of‑Pocket |
|---|---|---|
| Community Pharmacy (Chain) | Varies | Often lower with generics |
| Independent Pharmacy | Varies | May be higher; stock dependent |
| Online Pharmacy / Telehealth | Varies | Compare product and shipping costs |
Checklist For Online Buyers: confirm ARTG/TGA registration, check PBS status and verify brand versus generic packaging.
Comparable Medicines And Preferences
How does acarbose stack up against other diabetes medicines in Australia?
Acarbose is an alpha‑glucosidase inhibitor and its closest class alternatives are miglitol and voglibose.
Other diabetes classes such as metformin, DPP‑4 inhibitors, SGLT2 inhibitors and GLP‑1 receptor agonists offer different advantages in HbA1c lowering, weight impact and cardiorenal outcomes.
Acarbose’s niche remains focused on postprandial glucose control with a low intrinsic hypoglycaemia risk.
- Pros Of Acarbose: Good post‑meal control; weight neutral; low standalone hypoglycaemia risk.
- Cons Of Acarbose: High rates of GI side effects; less potent HbA1c lowering versus some modern agents; limited cardiorenal outcome data.
| Comparator | Key Benefit | Trade‑Off |
|---|---|---|
| Miglitol (Glyset) | Same class, similar PPG effect | Similar GI tolerability issues |
| Metformin | First‑line, good fasting and weight profile | Less specific postprandial action |
| SGLT2 / GLP‑1 | Cardiorenal benefits and weight loss | Higher cost; different side‑effect profiles |
Frequently Asked Questions
How quickly does acarbose start to work?
Postprandial glucose is reduced from the first dose, though measurable HbA1c improvements usually appear over weeks.
Will acarbose cause low blood sugar?
Acarbose alone has a low hypoglycaemia risk, but combining it with insulin or sulfonylureas increases that risk.
Important: If hypoglycaemia occurs do not treat with ordinary sugar (sucrose); use glucose (dextrose) such as glucose tablets instead.
What are the common side effects?
The most common issues are flatulence, abdominal pain and diarrhoea; transient increases in liver transaminases have also been reported.
Practical Advice For Remote Or Workplace Settings: carry glucose tablets, plan follow‑ups via telehealth and discuss tolerability before starting if your job is safety critical.
Guidelines For Proper Use
How should pharmacists and prescribers set patients up for success with acarbose?
Start at 25 mg three times daily with meals and titrate slowly as tolerated, monitoring glycaemic response and adverse effects.
Consider baseline liver function tests and renal function if risk factors are present and avoid use in significant renal or hepatic disease.
Pharmacist Counselling Points: emphasise taking tablets with the first bite, warn that flatulence and diarrhoea are common but often transient, and provide a hypoglycaemia plan (glucose tablets, not ordinary sugar).
- Initiation: 25 mg TDS with first bite of main meals.
- Monitoring: HbA1c and PPG response; LFTs if symptomatic or high risk.
- Follow‑Up: early phone check for tolerability in the first 2–4 weeks, especially for remote patients.
Patient Handout Template (One Page): dose and timing, common side effects and how to manage them, hypoglycaemia steps, and contact numbers for telehealth follow‑up.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Bendigo | Victoria | 5-9 days |