
Glucotrol
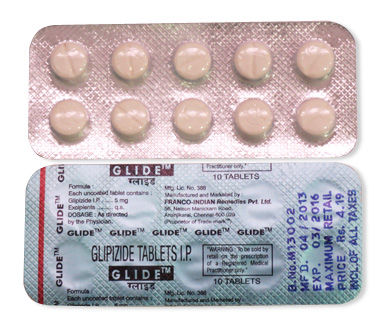
Glucotrol
- In Australia, glucotrol (glipizide) is usually supplied through community pharmacies and online suppliers; it is officially prescription-only (Rx), but in some pharmacies it may be possible to buy glucotrol without a prescription or receipt — delivery options vary.
- Glucotrol is used to treat type 2 diabetes mellitus; it is a sulfonylurea that lowers blood glucose by stimulating pancreatic beta‑cells to release insulin (closing ATP‑sensitive K+ channels).
- Usual dosage: adults often start at 5 mg once daily (immediate‑release) about 30 minutes before breakfast (XL with/after breakfast); titrate by 2.5–5 mg every few days as needed; typical maintenance 5–20 mg/day; maximum immediate‑release 40 mg/day, Glucotrol XL max 20 mg/day; not for type 1 diabetes.
- Form of administration: oral tablets — immediate‑release tablets (2.5, 5, 10 mg) and extended‑release Glucotrol XL (5 mg, 10 mg); take on a consistent schedule relative to meals.
- Onset time (how fast it starts working): immediate‑release usually begins to lower blood glucose within about 15–30 minutes (peak 1–3 hours); XL formulations have a slower onset.
- Duration of action: effects typically last around 12–24 hours depending on dose for immediate‑release preparations; Glucotrol XL provides a sustained effect up to about 24 hours.
- Alcohol warning: avoid excessive alcohol — alcohol can potentiate hypoglycaemic effects and cause unpredictable changes in blood glucose control.
- Most common side effec: hypoglycaemia (most important and common), with other frequent effects including dizziness, headache, nausea, gastrointestinal upset and weight gain.
- Would you like to try “glucotrol” without a prescription?

Basic Glucotrol Information
- INN (International Nonproprietary Name): Glipizide
- Brand Names Available In Australia: Glucotrol (internationally, Pfizer) including Glucotrol 5 mg tablets and Glucotrol XL extended‑release tablets; Minodiab in parts of Europe; generic glipizide available worldwide in various pack types and strengths — local Australian brand names not specified
- ATC Code: A10BB07
- Forms & Dosages: Immediate‑release tablets commonly 2.5 mg, 5 mg and 10 mg; Glucotrol XL extended‑release 5 mg and 10 mg; standard initiation 5 mg once daily (30 minutes before breakfast for IR; with breakfast for XL); titrate by 2.5–5 mg; maintenance 5–20 mg daily; max IR 40 mg/day, max XL ~20 mg/day
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription Only (Rx) in all jurisdictions
Latest Research Highlights Australia And International
Patients often ask whether older tablets like glucotrol still work as well as newer drugs.
Recent research from 2022 to mid‑2024 continues to show sulfonylureas such as glipizide produce meaningful reductions in HbA1c when compared with placebo and when added to metformin.
Meta‑analyses report average HbA1c reductions in the order of about 0.8–1.2% versus placebo for sulfonylureas overall.
Comparative trials show glipizide achieves clinically useful drops in fasting plasma glucose and HbA1c when used as add‑on therapy to metformin.
These efficacy gains come with recognised safety trade‑offs, most notably hypoglycaemia risk, which is emphasised in Australian TGA adverse‑event summaries from 2020–2023.
Pharmacoepidemiology reports highlight that severe hypoglycaemia is the leading serious event for sulfonylureas and occurs more often in older people and those with renal impairment.
Real‑world primary‑care registry data indicate treatment persistence with glipizide is reasonable where clinicians avoid hypoglycaemia through dose adjustment and patient education.
Ongoing Australian registry protocols begun in 2023 are tracking outcomes for older patients on sulfonylureas versus DPP‑4 and SGLT2 agents; results are pending.
| Study | Population | HbA1c Change | Hypoglycaemia Rate |
|---|---|---|---|
| Meta‑analysis (2023) | Adults with T2DM on oral therapy | −0.8% to −1.2% | Variable; increased vs placebo |
| Comparative Trial (2022) | Metformin + add‑on glipizide | Clinically meaningful reduction in fasting glucose and HbA1c | Higher than non‑secretagogue comparators |
| Australian TGA Summary (2020–2023) | National adverse‑event reports | not specified | Hypoglycaemia leading serious events; higher in elderly and renal impairment |
Clinical takeaway: glipizide is effective for glucose lowering but lacks the cardio‑renal benefits shown by SGLT2 inhibitors and GLP‑1 receptor agonists.
Clinical Effectiveness In Australia
People want to know when glucotrol is a practical choice in everyday Australian care.
In Australian practice, glipizide remains a treatment option for type 2 diabetes when metformin is contraindicated or proves inadequate.
Clinical pathways funded by the PBS generally prioritise metformin as first‑line therapy, with sulfonylureas often used second‑line where cost is a major factor or when injectable therapy is unsuitable.
Clinic audits in PBS settings report improvements in fasting plasma glucose and HbA1c within 6–12 weeks of starting glipizide in many patients.
Durability of glycaemic control may fall over time, and the risk of hypoglycaemia limits dose escalation, particularly in older Australians.
TGA adverse‑event monitoring flags severe hypoglycaemia and, less commonly, hepatic or haematologic reactions, which alters monitoring frequency and prescribing caution.
| Formulation | Adherence | Practical Outcome |
|---|---|---|
| Immediate‑Release | Requires timing before meals; may need twice‑daily dosing | Good glycaemic control but increased complexity for some patients |
| XL (Extended‑Release) | Once‑daily dosing; better adherence reported | Smoother glucose control for appropriate patients |
Typical Australian initiation follows the standard 5 mg once daily before breakfast and titration by 2.5–5 mg as required.
Indications And Expanded Uses TGA And Off‑Label
Patients often ask whether glucotrol is suitable for conditions beyond type 2 diabetes.
Approved indications align with TGA guidance and focus on the management of type 2 diabetes mellitus in adults as an oral hypoglycaemic agent.
Glipizide is prescription only and is not indicated for type 1 diabetes or for the treatment of diabetic ketoacidosis, where insulin is mandatory.
Off‑label use in Australia is uncommon but may occur in specialist clinics when metformin is contraindicated or cost prevents newer agents.
Use during pregnancy and breastfeeding is generally avoided unless managed by a specialist with close supervision.
- Approved (TGA)
- Oral treatment for type 2 diabetes mellitus in adults; prescription only.
- Not Indicated / Contraindicated
- Type 1 diabetes.
- Diabetic ketoacidosis (requires insulin).
- Use in pregnancy or breastfeeding without specialist oversight is not recommended.
Clinicians should document a clear rationale for any off‑label prescribing and counsel patients about hypoglycaemia risk.
Composition And Brand Landscape
Patients like to compare brands and strengths when buying from a pharmacy.
Active ingredient: glipizide (INN).
Internationally recognised brands include Glucotrol and Glucotrol XL from Pfizer, Minodiab in parts of Europe, and many generics from manufacturers such as Teva, Sandoz, Sun Pharma and Aurobindo.
| Name | Form | Strengths | Packaging | Common Markets |
|---|---|---|---|---|
| Glucotrol | Immediate‑release tablet | 5 mg, 10 mg | Bottles; 100 tablets | USA, global |
| Glucotrol XL | Extended‑release tablet | 5 mg, 10 mg | Bottles; 100 tablets | USA, global |
| Minodiab | Immediate‑release tablet | 5 mg | Blister packs (varies) | Sweden, EU |
| Generic Glipizide | Immediate‑release tablet | 2.5 mg, 5 mg, 10 mg | Blister packs, bottles (varies) | Worldwide |
In Australia the market is dominated by generics and hospital formularies, with local packaging and brand names varying by supplier.
Clinicians and pharmacists should check the PBS schedule and local hospital formularies for availability and subsidy status before prescribing or dispensing.
Contraindications And Special Precautions
People worry about dangerous side effects and whether glipizide is safe for them.
Absolute contraindications include hypersensitivity to glipizide or other sulfonylureas, type 1 diabetes, and diabetic ketoacidosis.
Relative contraindications require careful monitoring and dose adjustment rather than automatic exclusion.
- Absolute Contraindications: Hypersensitivity to sulfonylureas; type 1 diabetes; diabetic ketoacidosis.
- Relative Contraindications: G6PD deficiency; severe hepatic impairment; severe renal impairment; adrenal or pituitary insufficiency; malnutrition or unreliable food intake; advanced age.
Practical precautions in Australian practice include starting at lower doses in the elderly and closely monitoring renal and liver function where access to pathology may be limited in rural settings.
Advise shift‑workers, heavy machine operators and long‑distance drivers about hypoglycaemia risk and recommend blood‑glucose checks before driving.
When treating First Nations patients, assess food security and coordinate care with Aboriginal Health Services to support culturally safe diabetes education and transport for monitoring.
Dosage Guidelines Australian Practice
Patients commonly ask what dose to start and how quickly it can be increased.
Standard adult initiation is 5 mg once daily, typically 30 minutes before breakfast for immediate‑release or with breakfast for Glucotrol XL.
Titrate by 2.5–5 mg at several‑day intervals based on fasting plasma glucose and the presence or absence of hypoglycaemia.
Maintenance doses most commonly range from 5–20 mg daily, given as a single dose or in divided doses when needed.
Maximum doses: immediate‑release up to 40 mg per day; XL formulations approximately 20 mg per day.
| Stage | Recommendation |
|---|---|
| Initiation | 5 mg once daily (IR 30 min before breakfast; XL with breakfast) |
| Titration | Increase by 2.5–5 mg every few days as needed with SMBG |
| Maintenance | 5–20 mg daily; monitor HbA1c every 3–6 months when stable |
Dose adjustments are required for elderly patients and for those with significant hepatic or renal impairment.
Follow‑up is normally at 2–4 weeks after a dose change, then every 3–6 months once stable, with home blood‑glucose monitoring during titration or intercurrent illness.
Interactions Overview
People often want to know which everyday drugs and substances can affect their diabetes tablet.
Alcohol can potentiate the hypoglycaemic effect of glipizide and should be used cautiously.
Certain antibiotics and antifungals, ACE inhibitors, some SSRIs and NSAIDs may increase sulfonylurea effect and the risk of hypoglycaemia.
Drugs such as rifampicin, phenytoin and systemic corticosteroids can reduce the glucose‑lowering effect of glipizide.
Beta‑blockers may mask typical sympathetic symptoms of hypoglycaemia and require extra vigilance.
| Interaction Type | Effect |
|---|---|
| Alcohol | May potentiate hypoglycaemia |
| Antibiotics / Antifungals / NSAIDs / ACE inhibitors | May increase hypoglycaemia risk |
| Rifampicin / Phenytoin / Corticosteroids | May reduce glycaemic effect |
Pharmacists should use interaction‑checking software and review e‑health medication summaries before adding or changing therapy for older Australians on multiple medicines.
Cultural Perceptions And Patient Habits In Australia
Many Australians worry about cost, convenience and safety when choosing a diabetes tablet.
Price sensitivity steers many patients towards PBS‑subsidised medicines or lower‑cost generics supplied through national chains such as Chemist Warehouse and Priceline.
Trust in community pharmacists at chains like TerryWhite and independent pharmacies is high for medicine counselling and adherence support.
Rural and regional communities face longer travel times for pathology and pharmacy access, so telehealth e‑prescriptions and local pharmacists acting as primary educators help maintain adherence.
Common patient concerns seen on forums are hypoglycaemia, weight gain and interactions with alcohol, especially in social settings.
For First Nations Australians, culturally safe communication, food security assessment and continuity of care are essential when prescribing medicines with hypoglycaemia risk.
Simple habits that improve outcomes include taking glipizide consistently with meals, carrying fast‑acting carbohydrate, and syncing repeats with GP or telehealth appointments.
Case vignette: A farmer in regional Victoria prefers Glucotrol XL once daily to avoid twice‑daily dosing during harvest season, while a city commuter in Melbourne chooses immediate‑release dosing timed to daily breakfast routines.
Availability And Pricing Patterns Australia
Patients want to know where to buy glucotrol and how much it will cost out of pocket.
Glipizide is commonly available as generics through Australian wholesalers and is stocked by major retail chains and independent community pharmacies.
Pricing varies where a specific brand is not subsidised by the PBS, so out‑of‑pocket costs can differ between stores and online sellers.
Patients with concession cards should check PBS eligibility to reduce cost.
| Channel | Availability | Pricing Pattern |
|---|---|---|
| Chemist Chain (in‑store) | Common stock of generics | Competitive private prices |
| Online Pharmacies | E‑prescription ordering and home delivery | Often variable; compare offers |
| PBS Subsidised Supply | Depends on molecule and listing | Lower cost when eligible |
Supply shortages can occur, and pharmacists may substitute therapeutically equivalent generics with prescriber or patient consent to maintain continuity of therapy.
In our online pharmacy, glucotrol can be ordered with a valid prescription and delivered discreetly across Australia in 5–14 days.
Comparable Medicines And Preferences
People often ask which tablet is “best” and whether alternatives might suit them better.
Other sulfonylureas available include gliclazide (commonly used in Australia), glimepiride and glyburide (glibenclamide in some regions).
Modern alternatives are metformin, DPP‑4 inhibitors such as sitagliptin, SGLT2 inhibitors such as empagliflozin, and GLP‑1 receptor agonists such as semaglutide.
Pros of glipizide: effective glucose lowering, inexpensive as a generic, and once‑daily extended‑release options for adherence.
Cons: risk of hypoglycaemia, potential weight gain and absence of demonstrated cardiovascular or renal outcome benefits that some newer agents offer.
- Gliclazide: often favoured in Australia among sulfonylureas for potentially lower hypoglycaemia risk.
- SGLT2 / GLP‑1 agents: preferred when cardiovascular or renal protection is a priority and when PBS criteria or budget permit.
Use a decision matrix that maps individual patient profiles—such as elderly patients with renal impairment, cost‑sensitive patients, or those with cardiorenal disease—to the most appropriate agent after shared decision‑making and PBS eligibility checks.
FAQ
- Can I get glucotrol on the PBS?
- What if I miss a dose?
- How do I spot severe hypoglycaemia?
- Is glucotrol safe for older people?
Check the PBS schedule and your local pharmacy for current listings and subsidy details, as availability depends on molecule and formulation.
Take the missed dose as soon as you remember unless it is nearly time for your next dose; do not double up.
Look for sweating, trembling, dizziness, confusion or loss of consciousness; carry fast‑acting carbohydrate and seek emergency care for severe episodes.
Use lower starting doses and monitor closely for hypoglycaemia, falls and altered cognition in elderly patients.
When to call your GP or urgent care: if you experience severe or recurrent hypoglycaemia, signs of liver dysfunction, or any unexplained bleeding or bruising.
Guidelines For Proper Use And Pharmacist Counselling
Patients expect clear, practical counselling at the pharmacy counter.
Confirm the indication for type 2 diabetes, check for any sulfonylurea allergy, and review recent renal and liver function tests before supplying glipizide.
Advise dosing: start 5 mg before breakfast for immediate‑release or with breakfast for XL, and explain the titration plan by 2.5–5 mg increments.
Stress consistent meal patterns and the importance of carrying fast‑acting carbohydrate such as glucose tablets or jellybeans for hypoglycaemia.
Storage advice: store at 20–25°C, protect from moisture and heat, and keep in the original packaging.
Provide a written hypoglycaemia action plan, recommend wearing medical identification if risk is high, and schedule telehealth or GP follow‑up during titration.
- Step‑by‑step Counselling Checklist: confirm prescription and indication; check allergies; review renal/liver tests; explain dosing and titration; discuss hypoglycaemia signs and action; provide storage and refill advice.
Sample pharmacist script for a refill: “This is your glipizide 5 mg. Take one tablet with breakfast each morning. If you get sweating, shaking or confusion, have some quick sugar and ring your GP. If you miss a dose, take it unless the next dose is due soon; don’t double up.”
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Ballarat | Victoria | 5-9 days |