
Tolvaptan
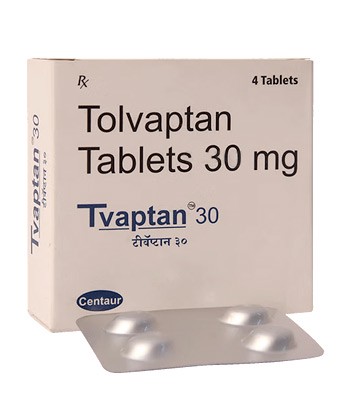
Tolvaptan
- Tolvaptan is supplied through hospital and community pharmacies in Australia (brands include Samsca and Jinarc) and elsewhere; it is a prescription-only (Rx) medicine and should only be obtained with a valid prescription and under medical supervision.
- Tolvaptan is used to treat hyponatremia (eg, SIADH, CHF, cirrhosis) and to slow progression of autosomal dominant polycystic kidney disease (ADPKD). It is a selective vasopressin V2‑receptor antagonist that increases free water excretion (aquaresis) and raises serum sodium.
- Typical dosing: for ADPKD an initial regimen often starts 45 mg in the morning plus 15 mg in the afternoon with titration up to 90/30 mg daily as tolerated; for hyponatraemia start at 15 mg once daily and titrate as needed up to 60 mg/day (maximum).
- Administered orally as film‑coated tablets (available in 15 mg, 30 mg, 45 mg and 60 mg strengths depending on region).
- Onset: increased urine output typically begins within 2–4 hours; changes in serum sodium are often seen within the first 24 hours (commonly within 6–24 hours).
- Duration of action: diuretic/aquaresis effects commonly persist for several hours and clinical effects can last up to about 24 hours; chronic effects on ADPKD require long‑term therapy and monitoring.
- Alcohol warning: avoid excessive alcohol—alcohol can worsen dehydration and may increase liver risk; tolvaptan carries a known risk of serious liver injury so avoid alcohol and report any liver‑related symptoms promptly.
- Most common side effec is thirst and increased urination; other frequent adverse effects include dry mouth, nausea, diarrhoea and fatigue.
- Would you like to try tolvaptan without a prescription?
Latest Research Highlights
Basic Tolvaptan Information
- INN (International Nonproprietary Name): Tolvaptan.
- Brand Names Available In Australia: Samsca, Jinarc.
- ATC Code: C03XA01.
- Forms & Dosages: Tablet (oral) available in 15mg, 30mg, 45mg, 60mg strengths; typical packaging in blister packs of 10–30 tablets.
- Manufacturers In Australia: Otsuka Australia (originator); Accord Healthcare appears as supplier in some regions.
- Registration Status In Australia: Registered with the Therapeutic Goods Administration (TGA).
- OTC / Rx Classification: Prescription-only (Rx).
Patients and clinicians ask whether recent studies change how tolvaptan is used in Australia.
Randomised placebo-controlled trials from the 2010s such as TEMPO and REPRISE underpin regulatory approval for autosomal dominant polycystic kidney disease, and remain central to the evidence base for disease modification.
More recent cohort and registry analyses from 2022–2024 continue to show a disease‑modifying signal for tolvaptan in selected adults, with slowed total kidney volume growth and attenuated eGFR decline compared with untreated cohorts.
Post‑marketing surveillance identified rare but serious hepatic injury, which led to stricter monitoring recommendations in many regions.
Australian pharmacovigilance through the TGA and the Database of Adverse Event Notifications has reported liver enzyme elevations and dehydration-related events consistent with global safety data.
For hyponatraemia, hospital case series reproduce short‑term correction of serum sodium using tolvaptan when fluid restriction fails, but these data consistently stress daily fluid balance and frequent sodium checks to avoid rapid correction.
Extrapolation of trial results to under‑represented groups such as Indigenous Australians or very elderly patients should be cautious because they were not well represented in major trials.
Preferred quick summary of main trials and safety events:
| Trial Name | Population | Primary Outcome | Effect | Notable Safety Events |
|---|---|---|---|---|
| TEMPO (summary) | ADPKD adults | Total kidney volume growth | Slower TKV increase versus placebo | Liver enzyme elevations reported; monitoring reinforced |
| REPRISE (summary) | ADPKD adults with reduced eGFR | eGFR decline | Slower eGFR loss versus placebo | Rare hepatic injury signals; LFT follow-up advised |
| Hospital Series | Inpatients with hyponatraemia | Serum sodium correction | Predictable rises in serum Na with monitoring | Risk of overly rapid correction without daily checks |
Key safety highlights from registries and pharmacovigilance focus on liver enzyme rises that are uncommon but clinically important.
Monitoring intervals recommended in practice include baseline liver function tests and frequent checks during early titration.
Clinical Effectiveness In Australia
Patients frequently want to know whether tolvaptan changes long‑term outcomes here in Australia.
Tolvaptan is TGA‑registered and used in specialist nephrology clinics and hospital services across the country.
When initiated early in eligible ADPKD patients and titrated per specialist protocol, tolvaptan shows clinically meaningful slowing of kidney growth and decline in eGFR.
Australian real‑world case series echo international results but also emphasise adherence challenges driven by polyuria and increased thirst.
In the inpatient setting, tolvaptan for hyponatraemia delivers predictable serum sodium rises when accompanied by daily sodium checks and fluid management.
Access to specialist prescribing and monitoring capacity — especially timely liver function tests and serum sodium measurements — strongly affects health outcomes.
TGA and DAEN adverse‑event reports are commonly referenced in local risk–benefit discussions and electronic medical records are used to document baseline LFTs and follow‑up.
Measurable outcomes clinicians track include:
- eGFR slope over months to years.
- Total kidney volume (TKV) change on imaging.
- Serum sodium correction speed and target attainment in hyponatraemia.
| Monitoring Item | Typical Cadence |
|---|---|
| Baseline LFTs and electrolytes | Before initiation |
| LFTs during titration | Weekly for 4 weeks, then monthly or per specialist |
| Serum Na (hyponatraemia) | Daily while correcting; then as advised |
Indications & Expanded Uses
Patients often ask what tolvaptan is approved for in Australia.
Approved indications follow global labels and include adult ADPKD to slow kidney volume growth and eGFR decline, and management of clinically significant hyponatraemia (SIADH, heart failure, cirrhosis) where fluid restriction fails.
Typical ADPKD initiation and titration strategies start at 45mg in the morning plus 15mg in the afternoon and escalate to 90mg/30mg if tolerated.
For hyponatraemia the usual starting dose is 15mg once daily with titration up to 60mg per day as needed for short courses.
Off‑label use in Australia is uncommon and reserved for specialist decisions or clinical trials, and paediatric use is not approved.
Any expanded or off‑label use requires informed consent, specialist oversight, and structured monitoring of liver function, electrolytes and volume status.
- ADPKD
- Typical Regimen: Start 45mg morning + 15mg afternoon; monitor LFTs frequently during titration.
- Hyponatraemia
- Typical Regimen: Start 15mg once daily; titrate up to 60mg/day; monitor serum sodium daily while correcting.
- Expanded/Off‑Label
- Approach: Specialist oversight, informed consent, and structured LFT/electrolyte monitoring.
Composition & Brand Landscape
People commonly ask which brand to look for and what strengths are available in Australia.
The active ingredient is the International Nonproprietary Name tolvaptan, ATC C03XA01.
In Australia the brands recorded are Samsca and Jinarc supplied by Otsuka Australia, with tablet strengths commonly listed at 15mg, 30mg and 60mg depending on local packaging.
Tablets are the only dosage form available; there are no injectable or topical forms.
Packaging is typically blister packs of 10–30 tablets per carton and labels display INN and brand name together.
Clinicians typically use INN or brand name interchangeably but must note strengths when titrating ADPKD regimens.
Community pharmacists source stock from Otsuka or specialty wholesalers and national chains provide dispensing and counselling.
| Brand | Strengths | Manufacturer | Packaging Notes |
|---|---|---|---|
| Jinarc | 15mg, 30mg, 60mg (regional packaging varies) | Otsuka Australia | Blister packs, 10–30 tablets per carton |
| Samsca | 15mg, 30mg, 60mg (regional packaging varies) | Otsuka Australia | Blister packs, 10–30 tablets per carton |
Contraindications & Special Precautions
Patients want to know when tolvaptan must not be used.
Absolute contraindications include severe liver impairment, hypovolaemia, anuria and known hypersensitivity to tolvaptan or excipients.
Relative precautions include moderate hepatic or renal impairment, dehydration risk, and concurrent use of strong CYP3A4 inhibitors which can increase exposure.
Elderly patients often need lower starting doses and closer monitoring of hydration and sodium shifts.
Pregnancy and breastfeeding are contraindications and contraception discussion is needed for people of childbearing potential.
Indigenous Australians with higher comorbidity burdens and remote access limitations require culturally safe counselling and accessible monitoring pathways.
Workplace safety should be discussed because polyuria and nocturia can disrupt sleep or affect tasks such as long‑haul driving.
- Absolute Contraindications: Severe liver impairment; hypovolaemia; anuria; hypersensitivity to tolvaptan or excipients.
- Relative Precautions: Moderate hepatic/renal impairment; risk of dehydration; strong CYP3A4 inhibitors.
| Risk | Recommended Monitoring Action |
|---|---|
| Potential hepatic injury | Baseline LFTs and frequent LFT checks during early therapy |
| Dehydration/hypernatraemia | Daily fluid balance and electrolyte checks when correcting sodium |
Dosage Guidelines
Many patients ask, "What dose will I start on and how often will I need tests?"
For ADPKD the usual starting regimen is 45mg in the morning plus 15mg in the afternoon, with specialist‑led titration up to 90mg/30mg if tolerated.
Chronic therapy is typical for ADPKD under specialist supervision.
For hyponatraemia the initial dose is usually 15mg once daily with titration to effect up to a maximum of 60mg per day for short courses, usually no longer than 30 days.
Children are not approved for tolvaptan and severe renal failure is a contraindication.
Elderly patients should start at lower doses and be monitored closely for hydration and sodium shifts.
If a dose is missed, take it the same day if remembered; skip if it is close to the next dose and do not double up.
In case of overdose seek immediate medical attention because of risk of dehydration and hypernatraemia.
- ADPKD Regimen
- Start 45mg morning + 15mg afternoon; escalate to 90mg/30mg as tolerated.
- Hyponatraemia Regimen
- Start 15mg once daily; titrate up to 60mg/day for short courses; monitor serum Na daily while correcting.
| Monitoring Point | Recommended Timing |
|---|---|
| Baseline LFTs and electrolytes | Before starting |
| Early titration checks | Weekly for first 1–4 weeks |
| Maintenance LFTs | Monthly or per specialist plan |
Interactions Overview
Patients commonly ask what medicines interact with tolvaptan.
Tolvaptan is metabolised mainly via CYP3A4 and strong CYP3A4 inhibitors can increase tolvaptan exposure and the risk of liver injury.
Examples of interacting classes include some azole antifungals, macrolide antibiotics and certain antiviral agents; specialist advice is required before co‑prescribing.
CYP3A4 inducers may reduce tolvaptan levels and efficacy.
Concurrent diuretics increase the risk of dehydration and hypernatraemia and require careful fluid and electrolyte monitoring.
There is no formal contraindication with coffee, but caffeine and other diuretics may worsen polyuria and alcohol should be minimised due to dehydration risk.
Australian e‑health systems and My Health Record help prescribers and pharmacists identify potential interactions during dispensing.
| Interacting Drug/Class | Interaction Effect | Recommended Action |
|---|---|---|
| Strong CYP3A4 inhibitors (e.g. ketoconazole) | Increased tolvaptan exposure; higher hepatotoxicity risk | Avoid co‑administration or seek specialist dosing advice |
| CYP3A4 inducers | Reduced tolvaptan levels; possible loss of effect | Review necessity; adjust therapy under specialist guidance |
| Loop/Thiazide diuretics | Increased dehydration and sodium shift risk | Close fluid/electrolyte monitoring; consider dose changes |
Cultural Perceptions & Patient Habits
Patients often worry about the quality‑of‑life trade‑offs from tolvaptan such as polyuria and thirst.
Online forums and patient groups report price sensitivity and high trust in pharmacists as frontline educators in Australia.
Many patients prefer face‑to‑face counselling at community pharmacies such as Chemist Warehouse, Priceline or TerryWhite Chemmart.
Rural and remote patients face access barriers, including less frequent lab monitoring and longer travel times to specialists.
Telehealth with local pathology collection is commonly used to bridge gaps in monitoring and follow‑up.
Indigenous health services emphasise culturally safe communication, community engagement and flexible monitoring arrangements for long‑term therapies.
Australian patients also rely on PBS subsidies where available, and out‑of‑pocket costs influence adherence when subsidies do not apply.
- Common Patient Concerns: polyuria, thirst, frequency of blood tests, and cost.
- Rural Access Solutions: telehealth consults, local pathology collections, coordinated specialist outreach.
- Pharmacist Counselling Points: expected side effects, importance of LFTs, signs of liver injury, fluid advice, and interaction checks.
Availability & Pricing Patterns
Where patients can obtain tolvaptan and what it might cost are frequent questions.
Tolvaptan is prescription-only and TGA‑registered in Australia, with brands including Samsca and Jinarc supplied by Otsuka Australia.
Supply routes include hospital pharmacies for inpatient initiation, community pharmacies for ongoing dispensing, and online pharmacies or telehealth providers for repeat supplies when monitoring is current.
PBS subsidisation varies and clinicians should verify eligibility for any patient who asks about cost support.
Private prescriptions can be costly, particularly for chronic ADPKD dosing, and some patients contact manufacturer support programmes or compassionate supply routes.
In our online pharmacy, tolvaptan is supplied on prescription with discreet delivery to Australia in 5-14 days.
| Supply Route | Likely Cost Bracket | Required Documentation |
|---|---|---|
| Hospital Pharmacy | Variable (usually public supply during admission) | Specialist prescription and inpatient chart |
| Community Pharmacy / Chains | Private purchase or subsidised if eligible | Current prescription and recent pathology for monitoring |
| Online Pharmacy / Telehealth | Private purchase; delivery fees may apply | E‑prescription and confirmation of monitoring tests |
Comparable Medicines And Preferences
Patients ask what alternatives exist to tolvaptan.
There are no oral medicines with the same disease‑modifying evidence in ADPKD as tolvaptan.
Conivaptan is an intravenous vaptan used in inpatient hyponatraemia but is not an ADPKD treatment option.
Lixivaptan has been investigational and should be considered only within trials or specialist pathways after checking current trial status.
Older diuretics such as furosemide and spironolactone treat volume but do not target V2 receptors or slow cyst growth in ADPKD.
For hyponatraemia, options include fluid restriction, hypertonic saline in acute settings, and agents like demeclocycline depending on clinical context.
- Pros of Tolvaptan: disease‑modifying evidence for ADPKD and effective sodium correction in hyponatraemia.
- Cons of Tolvaptan: need for liver monitoring, tolerability issues (thirst, polyuria), and cost.
| Indication | Preferred Agent | Monitoring Burden |
|---|---|---|
| ADPKD | Tolvaptan | High — baseline and frequent LFTs |
| Inpatient Hyponatraemia | Conivaptan (IV) or Tolvaptan (oral) | Moderate to high — daily Na checks |
| Volume Management | Loop diuretics | Lower — routine renal monitoring |
FAQ Section
Is tolvaptan on the PBS?
Tolvaptan is TGA‑registered, but PBS subsidisation can vary; check the PBS Schedule and discuss eligibility with your specialist and pharmacist.
How often will I need blood tests?
Baseline LFTs and electrolytes are required, followed by frequent monitoring early (often weekly for 1–4 weeks) and then periodic LFTs as per the specialist plan.
Can I drink alcohol or continue caffeine?
Avoid excess alcohol because of dehydration risk; caffeine may worsen polyuria and moderate intake should be discussed with your clinician.
What if I miss a dose?
Take the missed dose the same day if remembered; if it is close to the next scheduled dose, skip it and do not double up.
Guidelines For Proper Use
People commonly want a clear checklist to take to their pharmacy.
Pharmacist counselling should cover indication, expected benefits, common adverse effects such as thirst and polyuria, and urgent liver‑injury signs like jaundice or dark urine.
Advise on fluid strategy — do not restrict fluids unless specifically instructed by the treating team — and discuss contraception for those of childbearing potential.
Document baseline LFTs and electrolytes and confirm monitoring arrangements before dispensing.
Storage instructions are to keep below 25°C in the original container away from moisture.
For dispensing, verify recent pathology and check for interacting medicines, particularly strong CYP3A4 inhibitors.
- Pre‑Dispense Checks: current prescription, recent LFTs/electrolytes, full medication list.
- Monitoring Schedule (Pharmacy Handout): baseline, weekly LFTs for 1–4 weeks, then monthly or per specialist.
- Red‑Flag Symptoms To Escalate: yellowing of skin/eyes, severe abdominal pain, persistent nausea or fatigue.
Delivery Across Australia
| City | Region | Delivery time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Wollongong | New South Wales | 5-7 days |
| Geelong | Victoria | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Albury | New South Wales / Victoria | 5-9 days |
| Bunbury | Western Australia | 5-9 days |
| Gladstone | Queensland | 5-9 days |