
Lisinopril
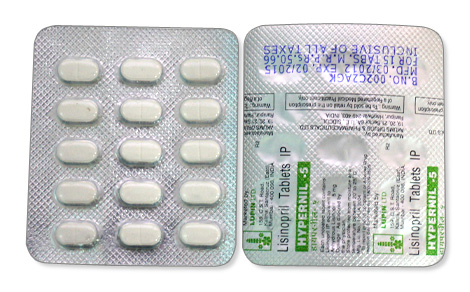
Lisinopril
- In most countries (including Australia) lisinopril is a prescription-only medicine and should be obtained with a prescription; some pharmacies and online vendors may supply it without a receipt, but this is not recommended — always consult a prescriber and follow local laws.
- Lisinopril is used for hypertension, heart failure, post‑myocardial infarction management and diabetic nephropathy; it is an ACE inhibitor that reduces angiotensin II formation, lowering blood pressure and cardiac workload.
- Usual doses vary by indication: hypertension typically starts at 10 mg daily (maintenance 20–40 mg daily, max 40 mg); heart failure often starts 2.5–5 mg and is titrated up (up to 40 mg); post‑MI commonly 5–10 mg; adjust for renal impairment.
- Administered orally as tablets (commonly 2.5–40 mg strengths) or as an oral solution (1 mg/mL, Qbrelis in the US); taken once daily.
- Onset of effect is usually within about 30–60 minutes, with measurable blood‑pressure lowering within the first hour.
- Duration of action is approximately 24 hours, allowing once‑daily dosing for most patients.
- Avoid excessive alcohol while taking lisinopril — alcohol can increase the risk of dizziness and low blood pressure (first‑dose hypotension).
- The most common side effect is a dry, persistent cough; other common effects include dizziness, hypotension and hyperkalaemia.
- Would you like to try “lisinopril” without a prescription?
Basic Lisinopril Information
- INN (International Nonproprietary Name): Lisinopril
- Brand Names Available In Australia: not specified
- ATC Code: C09AA03
- Forms & Dosages: Oral tablets 2.5 mg, 5 mg, 10 mg, 20 mg, 30 mg, 40 mg; oral solution 1 mg/mL (Qbrelis, US); combination tablets (lisinopril + hydrochlorothiazide, lisinopril + amlodipine) exist internationally; no creams, injections or vials
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription-only (Rx) in major markets; not available over-the-counter
Latest Research Highlights
Many people ask whether lisinopril still has a strong evidence base for heart and kidney protection.
Recent global meta-analyses from 2022–2025 continue to support ACE inhibitors as lowering major cardiovascular events and slowing progression of diabetic nephropathy compared with placebo.
Large trials and pooled analyses confirm a class benefit for secondary prevention after myocardial infarction, with improved survival and reduced heart failure events versus control.
Australian real-world PBS and TGA-linked analyses from 2020–2024 report reductions in hospital admissions for heart failure when patients remain adherent to ACE inhibitors.
TGA adverse-event signal detection highlights cough as the most frequently reported harm and angioedema as rare but serious.
Qbrelis, an oral solution authorised in the United States (approved 2016), remains available internationally but is less commonly used in Australia where tablets dominate.
| Outcome | Evidence Summary | Notes For Australia |
|---|---|---|
| Cardiovascular Mortality | Reduced versus placebo in meta-analyses (2022–2025). | Class effect observed; used in post‑MI secondary prevention. |
| Heart Failure Hospitalisation | Lower rates with ACE inhibitor therapy in clinical trials and meta-analyses. | PBS/TGA-linked Australian analyses (2020–2024) report similar reductions when patients stay adherent. |
| Renal Progression | Slower progression of diabetic nephropathy compared with placebo in multiple studies. | Renoprotective effects supported; monitor renal function as per practice. |
| Common Adverse Events | Dry cough common; hypotension, dizziness, hyperkalaemia reported; angioedema rare. | TGA reports align with international pharmacovigilance signals. |
INN = Lisinopril.
ATC = C09AA03.
Clinical Effectiveness In Australia
Patients commonly want to know how lisinopril performs in routine Australian practice.
PBS-subsidised generic lisinopril provides broad access through primary care and community pharmacies.
Australian cohort analyses show good blood-pressure control and reduced heart-failure admissions when lisinopril is prescribed in line with guidelines.
TGA pharmacovigilance confirms the expected adverse-effect profile of dry cough, hypotension, hyperkalaemia and rare angioedema with reporting rates consistent with international data.
Elderly patients and Aboriginal and Torres Strait Islander peoples derive cardiovascular and renal benefit but need closer renal and potassium monitoring.
Local Indigenous health services recommend culturally safe counselling and coordination with primary-care clinics for monitoring and follow-up.
- Monitoring Checklist: Baseline BP, serum creatinine/eGFR, potassium, then repeat 1–2 weeks after start or dose change.
- Follow-up: BP review at 3–6 months; renal function and potassium 6–12 monthly once stable.
| Test | When To Do It |
|---|---|
| Blood Pressure | Baseline, 1–2 weeks after start/dose change, then 3–6 months |
| Serum Creatinine / eGFR | Baseline, 1–2 weeks after start/dose change, then 6–12 monthly |
| Serum Potassium | Baseline, 1–2 weeks after start/dose change, then as clinically indicated |
Typical Australian starting doses are the same as standard international practice — hypertension often starts at 10 mg and heart failure at 2.5–5 mg with maintenance up to 40 mg daily.
Indications And Expanded Uses
Patients ask what lisinopril is officially for and when clinicians use it off-label.
- Approved Indications: Primary hypertension; adjunctive therapy for heart failure; post‑myocardial infarction care to reduce mortality; albuminuric diabetic nephropathy.
- Off‑Label Uses: Combination titration approaches for resistant hypertension and selected proteinuric kidney diseases under nephrology supervision.
- Absolute Contraindications: Prior ACE‑inhibitor angioedema, pregnancy, bilateral renal artery stenosis.
| Indication | Usual Starting Dose | Typical Maintenance |
|---|---|---|
| Hypertension | 10 mg daily | 20–40 mg daily |
| Heart Failure | 2.5–5 mg daily | Up to 40 mg daily |
| Post‑Myocardial Infarction | 5 mg daily (initial low dose) | 10 mg daily as tolerated |
| Diabetic Nephropathy | 10–20 mg daily | Titrate as tolerated, up to 40 mg |
Composition And Brand Landscape In Australia
People often ask which brands are stocked locally and what strengths are available.
The active ingredient is lisinopril (INN) and the market in Australia is dominated by multiple generics supplied by different manufacturers.
Common tablet strengths reflect international practice with 5 mg, 10 mg, 20 mg and 40 mg packs commonly seen worldwide.
Combination products such as lisinopril/hydrochlorothiazide and lisinopril/amlodipine exist internationally but local availability depends on TGA registration and PBS listings.
| Brand (Where Listed) | Formulation | PBS Subsidised |
|---|---|---|
| Prinivil / Zestril (global) | Tablets 5–40 mg | not specified |
| Generic Lisinopril (multiple suppliers) | Tablets 2.5–40 mg | not specified |
| Zestoretic / Acedip (combination products, international) | Lisinopril + HCTZ; Lisinopril + Amlodipine | not specified |
Internationally, an oral solution (Qbrelis 1 mg/mL) exists, though tablets are the usual form in Australia.
Major pharmacy chains and online pharmacies commonly stock generics and advertise competitive prices, while telehealth services and e‑prescriptions make scripts easier to obtain.
Contraindications And Special Precautions
Many patients want to know who should not take lisinopril and what to watch for.
- Absolute Contraindications: Hypersensitivity to lisinopril or ACE inhibitors, history of ACE‑inhibitor angioedema, pregnancy (second/third trimester), bilateral renal artery stenosis.
- High‑Risk Groups In Australia: Elderly patients with polypharmacy, people with chronic kidney disease, and Aboriginal and Torres Strait Islander communities with higher renal disease prevalence.
- Relative Cautions: Severe renal impairment (CrCl <30 mL/min), aortic valve stenosis, collagen vascular disease, dehydration, and concurrent potassium‑raising therapies.
Advise patients to take care when starting or increasing dose because first‑dose hypotension and dizziness may occur.
Recommend avoiding heavy machinery or driving until the individual knows how lisinopril affects them.
- Review and stop or adjust potassium supplements, potassium‑sparing diuretics and NSAIDs where appropriate to reduce renal and hyperkalaemia risk.
- Avoid co‑prescribing ACE inhibitor and ARB as dual RAAS blockade is not recommended.
Decision Steps For Pregnancy And Renal Artery Stenosis:
- Woman of childbearing potential: confirm current pregnancy status before starting; advise immediate cessation and GP review if pregnancy suspected.
- Suspected bilateral renal artery stenosis or sudden renal decline: stop lisinopril and arrange urgent nephrology or specialist review.
- Severe renal impairment: start low and monitor closely if therapy remains appropriate.
Dosage Guidelines
Patients and prescribers both want clear, practical dosing advice for daily use.
Standard dosing for hypertension is usually 10 mg once daily with maintenance typically 20–40 mg daily and a maximum of 40 mg daily.
For heart failure begin low at 2.5–5 mg daily and up‑titrate carefully to 40 mg if tolerated.
Renal impairment dosing: start lower when CrCl 10–30 mL/min (2.5–5 mg daily) and use 2.5 mg in dialysis patients with close monitoring.
Elderly patients should follow a “start low and go slow” approach, typically 2.5–5 mg at initiation.
- Stepwise Titration Example: Start at indicated low dose, review BP and symptoms at 1–2 weeks, increase dose by one increment if tolerated, repeat monitoring after each change until target reached.
- Monitoring Timeline: Baseline serum creatinine/eGFR and potassium, repeat 1–2 weeks after start or dose change, then 6–12 months once stable.
| Condition | Start Dose | Usual Max |
|---|---|---|
| Hypertension | 10 mg daily | 40 mg daily |
| Heart Failure | 2.5–5 mg daily | 40 mg daily |
| Post‑MI | 5 mg daily | 10 mg daily (as clinically indicated) |
Interactions Overview
Patients often worry about medicines and foods that change how lisinopril works.
| Concomitant Drug Class | Clinical Consequence | Action |
|---|---|---|
| Potassium‑Sparing Diuretics / Potassium Supplements | Increased risk of hyperkalaemia | Avoid co‑use unless monitored; check potassium regularly |
| ACE Inhibitor + ARB | Increased renal risk, hyperkalaemia; little added benefit | Avoid dual RAAS blockade |
| NSAIDs | Reduced antihypertensive effect; increased renal dysfunction risk | Use with caution; monitor renal function |
| Lithium | Raised lithium levels; risk of toxicity | Monitor lithium levels closely or avoid combination |
| Trimethoprim | Possible hyperkalaemia risk | Monitor potassium if co‑prescribed |
Alcohol may worsen hypotension and dizziness after dose changes and should be used cautiously during initiation.
Pharmacists should review My Health Record and PBS history for co‑prescriptions such as spironolactone when dispensing lisinopril.
Cultural Perceptions And Patient Habits In Australia
Patients commonly ask what to expect from lisinopril and where to get trustworthy advice.
Community pharmacists are a trusted source for medicine counselling and many Australians compare chain pharmacies for price and availability.
Indigenous communities value culturally safe communication and continuity with local Aboriginal Health Services when starting long‑term medicines like lisinopril.
Rural and remote patients may face barriers to face‑to‑face monitoring, so telehealth scripts and pharmacy delivery are common solutions but require arranged local pathology.
Online patient forums frequently report cough as the most discussed adverse effect, which often leads to switching to an ARB if intolerable.
- Patient Checklist: Explain monitoring schedule, warn about first‑dose dizziness, advise on pregnancy risk, and confirm current medicines including OTC and supplements.
- FAQ For Counselling: Keep language plain, use examples (for instance, “If you feel light‑headed after the first tablet, sit or lie down and call us”).
Local resource links and coordination with Aboriginal health services help improve adherence and safety for high‑risk groups.
Availability And Pricing Patterns
Patients ask where lisinopril is sold and how much it costs in Australia.
Supply is widespread through community pharmacies such as major chains and accredited online pharmacies, and telehealth e‑prescriptions widen access.
PBS‑subsidised listings markedly reduce patient cost where the listing applies, while private purchase price varies by brand and supplier.
Price‑sensitive consumers often choose generics or compare large chains for lower out‑of‑pocket cost.
In our online pharmacy, lisinopril is available without a prescription, with discreet delivery to Australia in 5–14 days.
| Purchase Route | Cost Pattern |
|---|---|
| PBS‑Subsidised | Low patient contribution where listed; eligibility and repeats per PBS rules |
| Private Purchase | Varies by brand and supplier; shoppers often compare chains or online suppliers |
| Online International Suppliers | Price variation common; verify accreditation and TGA registration of sponsor |
- Safe Online Purchase Checklist: Ensure pharmacy accreditation, valid prescription, and TGA‑registered sponsor details before buying.
Generic manufacturing is widespread following patent expiry in 2002, which increased global availability.
Comparable Medicines And Preferences
Clinicians and patients often want to know what to use if lisinopril is not suitable.
Alternatives include other ACE inhibitors such as enalapril, ramipril and perindopril, and ARBs such as losartan, valsartan and telmisartan.
ARBs are generally preferred when cough or angioedema occurs with ACE inhibitors and show similar renal and cardiovascular benefits in comparative safety reviews.
- ACE Inhibitors (Pros): Proven secondary prevention benefits, well established, generally low cost.
- ACE Inhibitors (Cons): Higher cough rate; rare angioedema risk.
- ARBs (Pros): Lower cough rates, comparable renal/CV outcomes in reviews.
- ARBs (Cons): Often higher cost depending on PBS listing.
| Patient Scenario | Preferred Option |
|---|---|
| ACE‑Inhibitor Cough | Switch to ARB (e.g., losartan) |
| History Of Angioedema With ACE | Avoid ACE inhibitors; seek specialist advice |
| Cost‑Sensitive Patient With No Intolerance | Generic ACE inhibitor (lisinopril or other) per PBS listing |
Frequently Asked Questions
- What Happens If I Miss A Dose?: Take the dose as soon as you remember unless it is close to the next dose; do not double up.
- Can I Take Potassium Supplements Or Salt Substitutes?: Avoid without medical advice as these can increase the risk of hyperkalaemia when taken with lisinopril.
- Is Lisinopril Safe In Pregnancy?: No — stop immediately and contact your GP if you become pregnant or suspect pregnancy.
- Why Did My Doctor Switch Me From Lisinopril To An ARB?: Most commonly because of ACE‑inhibitor cough or intolerance; ARBs reduce cough risk while providing similar benefits.
Seek urgent care if you develop signs of angioedema such as facial or throat swelling or difficulty breathing.
In overdose, hypotension is the primary concern and supportive care, including IV fluids and vasopressors, may be needed; dialysis can help in severe cases.
Guidelines For Proper Use
Pharmacists should provide clear counselling that supports safe and effective use of lisinopril.
- Confirm the indication and check for ACE‑inhibitor allergy or past angioedema.
- Ask about pregnancy status and counsel women of childbearing potential appropriately.
- Review current medicines with attention to NSAIDs, potassium supplements, potassium‑sparing diuretics and lithium.
- Confirm baseline renal function and potassium before initiation and at 1–2 weeks after start or dose change.
- Advise patients about the risk of first‑dose hypotension and the need to rise slowly from sitting or lying positions.
- Explain cough is common and that an ARB is an alternative if cough becomes intolerable.
- For telehealth scripts, arrange local pathology and follow‑up with the community pharmacist for monitoring.
Storage Advice: store tablets at 15–30°C, protect from moisture and light, keep in original packaging.
Oral solution should be stored at room temperature and discarded after 30 days.
- Printable Materials For Pharmacists: A short counselling checklist, monitoring timetable and a brief patient handout summarising when to seek help.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Toowoomba | Queensland | 5–9 days |