
Clopidogrel
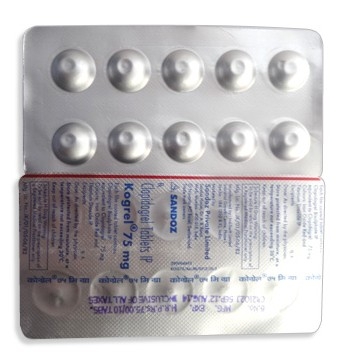
Clopidogrel
- Clopidogrel is a prescription-only medicine and in Australia should be obtained from a pharmacy with a valid prescription; it is not legally available over the counter—be wary of suppliers that claim to sell it without a prescription as this is unsafe and often unlawful.
- Clopidogrel is used to prevent blood clots in conditions such as acute coronary syndromes, after PCI/stenting, and for secondary prevention of stroke, myocardial infarction and peripheral arterial disease; it is an antiplatelet prodrug that irreversibly inhibits the platelet P2Y12 (ADP) receptor, reducing platelet activation and aggregation.
- Usual dosing: a loading dose of 300–600 mg once for acute coronary syndromes/PCI, followed by a maintenance dose of 75 mg once daily; for long‑term prevention (stroke, MI, PAD) the usual dose is 75 mg once daily without a loading dose.
- Form of administration: oral tablets (film-coated) commonly as 75 mg (maintenance) and 300 mg (loading); fixed‑dose combinations (eg clopidogrel 75 mg + aspirin 75 mg) exist in some markets.
- Onset time: as a prodrug, meaningful platelet inhibition typically begins within about 2 hours after a loading dose (faster with 600 mg); with standard daily dosing onset is slower and builds over several days.
- Duration of action: platelet inhibition lasts for the lifetime of affected platelets — generally about 5–10 days after stopping; the daily dose provides around 24 hours of antiplatelet effect once steady state is reached.
- Alcohol warning: avoid heavy alcohol intake—alcohol can increase the risk of gastrointestinal bleeding and may worsen bleeding risk when taking clopidogrel; moderate drinking should be discussed with your prescriber.
- The most common side effect is bruising and minor bleeding (eg nosebleeds, gum bleeding); other common effects include diarrhoea, abdominal pain and dyspepsia, while serious bleeding events are less common but can occur.
- Would you like to try clopidogrel without a prescription?
Basic Clopidogrel Information
- INN (International Nonproprietary Name): Clopidogrel
- Brand Names Available In Australia: not specified
- ATC Code: B01AC04
- Forms & Dosages: Tablets 75 mg (primary maintenance dose); 300 mg for loading dose; fixed-dose combinations exist in some markets (not commonly used locally).
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription-only Medicine (Rx)
Latest Research Highlights
Recent Australian registry analyses and international meta-analyses through 2022–2024 continue to confirm clopidogrel's benefit for secondary prevention of atherothrombotic events versus placebo.
The largest absolute benefits are seen after acute coronary syndromes and percutaneous coronary intervention when clopidogrel is used as part of dual antiplatelet therapy.
Pharmacogenetic work from Australasia highlights that CYP2C19 loss-of-function alleles reduce clopidogrel activation and clinical responsiveness in roughly 15–30% of some population groups, which is relevant to personalised prescribing.
Safety syntheses reiterate a predictable bleeding trade-off, with major gastrointestinal and intracranial haemorrhage rare but clinically significant.
Comparative effectiveness reviews still place ticagrelor and prasugrel ahead for selected ACS populations but note these options carry higher bleeding risk and higher cost.
TGA adverse-event trend reports align with global post-marketing surveillance, with no novel toxicities identified and continued monitoring for rare events such as thrombotic thrombocytopenic purpura and severe neutropenia.
For patients and prescribers, the key takeaway is that clopidogrel remains an effective, well-understood antiplatelet medication for many secondary prevention needs.
Clinical Effectiveness In Australia
Real-world data from PBS dispensing records and hospital registries show clopidogrel 75 mg maintenance (with 300–600 mg loading where indicated) reduces recurrent myocardial infarction and stent thrombosis and is cost-effective in many Australian cohorts when subsidised.
PBS listings and hospital formularies commonly favour generic clopidogrel for long-term secondary prevention because of affordability and wide availability.
Emergency cardiology units continue to use higher-potency agents for selected high-risk ACS patients, with clopidogrel remaining an option where cost, bleeding risk or genotype favour it.
TGA post-marketing data and state cardiac registries report outcomes consistent with older randomised trials: ischaemic event reduction balanced by modest rises in bleeding.
Rural and remote services report challenges in continuity of dual antiplatelet therapy after patient transfer or discharge, which can adversely affect outcomes if DAPT is interrupted.
| Measure | Typical Australian Figure |
|---|---|
| Recurrent MI, selected cohorts | Reduced vs placebo (registry data) |
| Stent thrombosis | Lower rates with DAPT including clopidogrel |
| Major bleeding | Modest increase; major GI/intracranial haemorrhage rare |
Indications And Expanded Uses
The Therapeutic Goods Administration aligns clopidogrel indications with international labelling for prevention of atherothrombotic events after myocardial infarction, ischaemic stroke and peripheral arterial disease.
Clopidogrel is approved as adjunctive therapy for acute coronary syndromes and after percutaneous coronary intervention with stenting.
Off-label uses in Australia include short-term bridging when higher-potency P2Y12 inhibitors are contraindicated and selected combinations with low-dose aspirin for secondary stroke prevention after multidisciplinary review.
Clopidogrel is not approved for paediatric use.
Standard duration is generally 12 months after ACS/PCI, adjusted by stent type and bleeding risk, and long-term therapy is typical for stroke or peripheral arterial disease.
- TGA-Approved Uses
- Prevention of atherothrombotic events after MI, stroke and PAD; adjunct for ACS and post-PCI with stenting.
- Common Off-Label Uses
- Short-term bridging when ticagrelor/prasugrel contraindicated; select stroke prevention combinations with aspirin after review.
- Decision flow for DAPT duration: assess stent type, bleeding risk and ischaemic risk, then aim for 12 months after ACS/PCI unless clinical factors indicate shorter or longer therapy.
- Record any deviation from guideline durations in the clinical notes with justification.
Composition And Brand Landscape
The active ingredient is clopidogrel, classified under ATC code B01AC04 as a platelet aggregation inhibitor excluding heparin.
Internationally the original brand Plavix and many generics such as Clopidogrel Teva, Clopidogrel Mylan and Clopidogrel Krka are available.
Locally, generics typically supply the 75 mg tablets that are commonly dispensed on the PBS, while hospitals may stock 300 mg loading tablets for acute use.
| Item | Details |
|---|---|
| INN | Clopidogrel |
| ATC | B01AC04 |
| Common Strengths | 75 mg tablets (maintenance); 300 mg tablets (loading) |
| Typical Brands/Suppliers | Plavix (originator), Clopidogrel Teva, Clopidogrel Mylan, other generics |
| Packaging | Blister packs or bottles; hospital packs for 300 mg loading doses |
| Storage | Store at room temperature 15–30°C |
Contraindications And Special Precautions
Absolute contraindications include active pathological bleeding, such as peptic ulcer or intracranial haemorrhage, and known hypersensitivity to clopidogrel or excipients.
Caution is required in patients with a history of bleeding disorders, recent trauma or surgery, and severe liver impairment because of increased bleeding risk.
The elderly do not require routine dose changes but should be monitored closely for bleeding.
Pregnancy and breastfeeding should be approached cautiously and only used if the potential benefit justifies the risk, given limited data.
Occupational advice is important for safety-sensitive roles such as commercial drivers or heavy machinery operators because of bleeding risk.
- Checklist for prescribers: rule out active bleeding, review concomitant anticoagulants/NSAIDs, assess liver function and bleeding history, counsel on periprocedural plans.
| High-Risk Group | Monitoring Action |
|---|---|
| Elderly | Frequent review for bruising, fall risk and haemoglobin changes |
| Severe Hepatic Impairment | Use with caution; monitor for bleeding and consider alternatives |
| Indigenous And Remote Patients | Tailored counselling and adherence support; check access to follow-up |
Dosage Guidelines
For acute coronary syndromes and PCI, a loading dose of 300–600 mg is commonly given, followed by maintenance clopidogrel 75 mg once daily.
For long-term secondary prevention after myocardial infarction, ischaemic stroke or peripheral arterial disease, the usual dose is 75 mg once daily without a loading dose.
No routine renal dose adjustment is required for mild to moderate impairment, but use caution in severe renal or hepatic disease.
Clopidogrel is not approved for children.
- If starting for ACS/PCI and immediate platelet inhibition is needed, give 300–600 mg loading dose, then continue 75 mg daily.
- For chronic secondary prevention, start and continue 75 mg once daily.
- Reassess duration at follow-up and document reasons for any deviation from standard durations.
Missed-dose advice: take as soon as remembered unless it is nearly time for the next dose; do not double the dose.
In overdose, prolonged bleeding is the main risk and supportive measures including platelet transfusion may be considered since no specific antidote exists.
Interactions Overview
The central interaction issue with clopidogrel involves CYP2C19-mediated activation.
Proton-pump inhibitors such as omeprazole can reduce clopidogrel activation and potentially its efficacy.
Concomitant use of anticoagulants, NSAIDs or other antiplatelet agents increases bleeding risk and requires careful clinical review.
Alcohol increases acute bleeding risk and should be moderated while taking antiplatelet therapy.
| Concomitant Agent | Recommended Action |
|---|---|
| Omeprazole (PPI) | Prefer alternative PPI or H2 antagonist when possible; consult prescriber. |
| Warfarin or DOACs | Expect higher bleeding risk; monitor closely and coordinate with prescriber. |
| NSAIDs | Avoid regular use; recommend paracetamol for pain when possible and counsel on bleeding signs. |
| CYP2C19 Inducers (some anticonvulsants) | May lower clopidogrel activation; specialist review advised for chronic co-prescribing. |
- Lifestyle advice: limit alcohol, inform clinicians about herbal supplements such as St John's wort, and check all OTC medicines with the pharmacist.
Cultural Perceptions And Patient Habits In Australia
Many Australian patients trust pharmacists and value PBS-subsidised medicines for affordability and reliability.
Patients commonly worry about bleeding, pill burden and brand switching, especially when moving between community pharmacies and hospitals.
Rural and remote patients face continuity issues, such as travelling for follow-up and occasional supply interruptions, which can disrupt dual antiplatelet therapy.
Aboriginal and Torres Strait Islander communities may need culturally safe counselling and attention to common comorbidities such as diabetes and chronic kidney disease.
- Patient insight: people often consult the pharmacist first about side effects and about swapping to generic clopidogrel for cost reasons.
- Chain pharmacies play a large role in counselling and affordability for many Australians.
Case vignette: a patient from a regional town misses a cardiology follow-up and the hospital switches their DAPT on discharge; the local pharmacist arranges an e-prescription and home delivery to maintain continuity.
Availability And Pricing Patterns
Clopidogrel is prescription-only and widely available through community pharmacies and hospital supply chains.
On the PBS, generic clopidogrel is commonly subsidised for eligible patients, which reduces out-of-pocket costs substantially.
Private prescriptions at major chains may cost more but generics remain relatively inexpensive compared with higher-potency alternatives.
Online pharmacies and telehealth services that provide e-prescriptions and home delivery are useful options for remote patients.
In our online pharmacy, clopidogrel is available without a prescription, with discreet delivery to Australia in 5-14 days.
| Supply Route | Typical Price/Note |
|---|---|
| PBS-Subsidised Dispense | Low out-of-pocket cost for eligible patients |
| Private Prescription (Retail Chains) | Generic range; price varies by retailer but generally affordable |
| Online Pharmacy | E-prescription and delivery options; check pharmacy accreditation |
- Checklist for safe online purchase: verify prescription, confirm pharmacy accreditation, check delivery and privacy policies, and keep dispensing records.
Comparable Medicines And Prescribing Preferences
Ticagrelor and prasugrel are more potent P2Y12 inhibitors that avoid CYP2C19 activation and can offer superior ischaemic protection in selected ACS patients.
These agents carry higher bleeding risk and higher cost and may not be preferred for long-term secondary prevention where cost and bleeding risk are key considerations.
Aspirin remains a foundational antiplatelet agent and is commonly used either alone or in combination with P2Y12 inhibitors for DAPT.
| Agent | Pros | Cons |
|---|---|---|
| Clopidogrel | Affordable, widely available, familiar to GPs and pharmacists | Reduced activation in CYP2C19 loss-of-function carriers; modest bleeding risk |
| Ticagrelor | Higher efficacy in some ACS groups; no CYP2C19 activation needed | Greater bleeding risk; higher cost |
| Prasugrel | Strong platelet inhibition for selected periprocedural patients | Not suitable in some elderly or low-weight patients; higher bleeding risk |
In Australia, hospital protocols often favour ticagrelor or prasugrel for high-risk ACS, while GPs commonly continue clopidogrel for long-term secondary prevention where appropriate.
FAQ For Australian Patients
- Q: Can I get clopidogrel on the PBS?
- A: Yes for eligible indications; ask your prescriber or pharmacist about PBS eligibility and concession status.
- Q: Will genetic testing help decide treatment?
- A: CYP2C19 testing can inform choice where available but it is not routine; cardiology teams weigh clinical context and test availability.
- Q: Can I drink alcohol while taking clopidogrel?
- A: Alcohol can increase bleeding risk, so discuss sensible limits with your clinician.
- Q: What if I need surgery?
- A: Always inform your surgeon and follow perioperative guidance about stopping clopidogrel; do not stop without medical advice.
- Q: Is switching between generics safe?
- A: Generally yes; pharmacists can advise on bioequivalence and PBS substitutions.
- When to Seek Urgent Help: sudden severe headache, vomiting blood, black tarry stools, unexplained excessive bruising or prolonged bleeding after minor injury.
Guidelines For Proper Use And Pharmacist Counselling Style
Pharmacist counselling should be brief, practical and culturally sensitive, focusing on indication, dose, duration and key safety points.
Confirm the reason for therapy, the prescribed dose of 75 mg once daily, and whether a loading dose was given in hospital.
Explain missed-dose instructions clearly: take when remembered unless it is close to the next dose and do not double up.
Discuss bleeding signs that should prompt urgent review, and review common interactions such as with NSAIDs and proton-pump inhibitors.
- Counselling checklist: indication, dosing, duration, interactions, storage (15–30°C), PBS supply rules and follow-up arrangements.
For rural and remote patients arrange repeat scripts, delivery or liaise with local clinics to avoid therapy interruption.
For Aboriginal and Torres Strait Islander patients offer culturally safe communication, involve local health workers or family where appropriate, and document counselling in the dispensing record.
Template wording for a patient leaflet: "Take clopidogrel 75 mg once daily as directed. Watch for any unusual bleeding and tell healthcare staff you are on clopidogrel before any procedure. Contact your pharmacist or doctor if you have any concerns."
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Toowoomba | Queensland | 5-9 days |