
Lanoxin
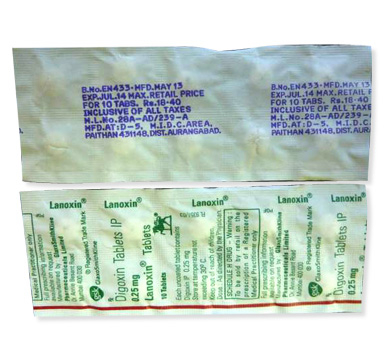
Lanoxin
- In our pharmacy you can buy lanoxin without a prescription, with delivery across Australia in 5–14 days and discreet, anonymous packaging.
- Lanoxin (digoxin) is used to treat heart failure and to control the ventricular rate in atrial fibrillation; it is a cardiac glycoside that inhibits the myocardial Na+/K+‑ATPase, increasing intracellular calcium to boost contractility and enhancing vagal tone to slow AV nodal conduction.
- Usual adult doses are typically 0.125–0.25 mg once daily (individualised to response and serum levels); paediatric dosing is weight‑based (about 5–10 mcg/kg/day oral), with adjustments for renal function, age and clinical response.
- Available as oral tablets (0.0625 mg, 0.125 mg, 0.25 mg), oral solution/elixir (0.05 mg/mL) and injection/ampoules (0.25 mg/mL) for oral or intravenous administration.
- Onset of effect: oral doses usually begin to work within roughly 30–120 minutes; intravenous administration produces effects more rapidly, often within 5–30 minutes.
- Duration of action is prolonged — digoxin has a long half‑life (around 36–48 hours in normal renal function), so clinical effects persist for days and once‑daily dosing is common; serum monitoring is required for long‑term safety.
- Alcohol warning: avoid excessive alcohol — alcohol can worsen heart failure symptoms and may increase risk of side effects; discuss drinking with your clinician before taking digoxin.
- The most common side effect is gastrointestinal upset (nausea, vomiting, diarrhoea); other frequent effects include dizziness, headache, visual disturbances (blurred or yellow vision) and possible arrhythmias which may signal toxicity.
- Would you like to try lanoxin without a prescription?
Basic Lanoxin Information
- INN (International Nonproprietary Name): Digoxin
- Brand Names Available In Australia: Lanoxin and generic digoxin formulations are used globally; internationally Lanoxin appears in the United States and United Kingdom, with equivalents marketed as Digoxin, Digoxine, Digoxina and local generics in other regions. (Specific Australian brand registrations not specified in the product data.)
- ATC Code: C01AA05 (Cardiac Glycosides, Digoxin)
- Forms & Dosages: Tablets 0.0625 mg, 0.125 mg, 0.25 mg; oral solution/elixir 0.05 mg/mL; injection 0.25 mg/mL (2 mL ampoules).
- Manufacturers In Australia: Not specified (manufacturers listed globally include GlaxoSmithKline for Lanoxin and various generic manufacturers).
- Registration Status In Australia: Not specified in the product data.
- OTC / Rx Classification: Prescription-only (Rx) in major markets.
Latest Research Highlights
What recent evidence should prescribers and pharmacists know about digoxin (Lanoxin)?
Cohort and registry studies from 2022–2025 continue to show digoxin reduces heart‑failure hospital readmissions in selected patients with reduced ejection fraction while offering symptom control for symptomatic heart failure.
Re‑analyses of international randomised trial data show a generally neutral effect on all‑cause mortality but consistent benefit for symptom relief and for rate control in atrial fibrillation when combined with beta‑blockers.
Australian observational data and Therapeutic Goods Administration adverse‑event reports emphasise age and renal impairment as the main drivers of harm from digoxin.
Emerging pharmacokinetic work from 2024–25 highlights variable bioavailability in frail older adults and in people on complex polypharmacy, increasing the challenge of achieving stable serum concentrations.
| Study | Design | Population | Primary Outcome | Safety Signals |
|---|---|---|---|---|
| Recent Cohort Analyses (2022–24) | Observational Registry | Adults With Reduced EF Heart Failure | Reduced HF Hospital Readmissions | Higher toxicity in older, renal‑impaired patients |
| RCT Re‑Analysis (International) | Secondary Analysis | AF Patients On Beta‑Blockers | Improved Rate Control; Neutral Mortality | Bradycardia when combined with other rate agents |
| Pharmacokinetic Series (2024–25) | PK/Population Modelling | Frail Elderly, Polypharmacy | Variable Bioavailability | Unpredictable serum levels; dose adjustments needed |
| Australian Observational Reports | Pharmacovigilance/TGA Reports | Older, Multi‑morbid Adults | Reports Of Toxicity Linked To Renal Decline | Age and renal impairment common factors |
Data highlights from TGA adverse‑event categories and PBS utilisation trends show frequent reports of gastrointestinal and cardiac arrhythmia events in older people and steady prescribing in chronic heart‑failure clinics where digoxin is used selectively.
Product strengths available and commonly referenced in studies: Digoxin tablets 0.0625 mg, 0.125 mg, 0.25 mg; oral solution 0.05 mg/mL; injection 0.25 mg/mL.
Clinical Effectiveness In Australia
Which patients get the most benefit from digoxin in routine Australian practice?
Digoxin remains an option for symptomatic heart failure with reduced ejection fraction and for atrial fibrillation rate control when beta‑blockers are inadequate or not tolerated.
Hospital and outpatient audits in Australia suggest reduced heart‑failure admissions in carefully selected patients, but benefit is highly patient‑dependent and requires serum monitoring to avoid toxicity.
| Clinical Outcome | Monitoring Needs |
|---|---|
| Hospitalisation Reduction (Selected Patients) | Baseline renal, electrolytes, serum digoxin; repeat levels after initiation |
| Symptom Improvement (Exercise Tolerance, Dyspnoea) | Clinical review; monitor for GI and visual symptoms |
| Mortality | Generally Neutral; monitor comorbid risks |
Typical adult dosing in Australian clinical practice follows standard ranges of 0.125–0.25 mg once daily, individualised to response and renal function.
Prescribers should confirm current PBS listings and any authority requirements before issuing long‑term prescriptions to ensure subsidised access where appropriate.
Indications And Expanded Uses
When is digoxin indicated and when might clinicians use it off‑label?
- Approved
- Heart failure in adults and children aged 5 years and older.
- Atrial fibrillation for rate control in adults.
- Off‑Label/Adjunctive Uses
- Rate control in multifactorial atrial fibrillation when beta‑blockers and calcium‑channel blockers are inadequate or contraindicated.
- Selective paediatric dosing for congenital heart conditions with specialist cardiology input; paediatric dosing usually starts from age 5 upwards per product guidance.
Off‑label use should be documented, with specialist cardiology input and a clear rationale recorded in the medical notes.
Clinicians must check PBS authority rules when prescribing for long‑term therapy to avoid unexpected patient costs.
Composition And Brand Landscape
What is in the tablet and who supplies it?
INN: Digoxin.
Lanoxin is the best recognised brand internationally and is available in tablet strengths 62.5 micrograms (0.0625 mg), 125 micrograms (0.125 mg) and 250 micrograms (0.25 mg).
Forms sold include tablets (0.0625–0.25 mg), oral elixir 0.05 mg/mL, and injection 0.25 mg/mL (2 mL ampoule).
| Form | Strength | Typical Packaging |
|---|---|---|
| Tablets | 0.0625 mg; 0.125 mg; 0.25 mg | Blister packs or bottles |
| Oral Elixir | 0.05 mg/mL | Bottle |
| Injection | 0.25 mg/mL (2 mL ampoule) | Ampoule or vial |
In Australia digoxin is supplied as branded imports and generics; manufacturers internationally include GlaxoSmithKline for Lanoxin and multiple generic manufacturers.
Packaging differences (blister vs bottle) can influence dispensing preferences in community pharmacies and should be discussed with patients at collection.
Contraindications And Special Precautions
Who should not take digoxin, and who needs extra care?
Absolute Contraindications:
- Ventricular fibrillation.
- Known hypersensitivity to digitalis glycosides.
- Acute myocarditis.
- Severe atrioventricular block or sick sinus syndrome unless paced.
Relative Risks And Precautions:
- Electrolyte disturbances: hypokalaemia, hypomagnesaemia, hypercalcaemia increase toxicity risk.
- Renal impairment requires substantial dose reduction and close monitoring because digoxin is predominantly renally cleared.
- Thyroid disorders can alter sensitivity to digoxin; monitor accordingly.
- Elderly patients and those in remote or Indigenous communities with multiple comorbidities are at increased risk and need careful follow‑up.
Pregnancy and breastfeeding require specialist input where benefit outweighs risk; document the discussion.
Daily‑life precautions: advise patients to avoid heavy machinery or driving if they experience dizziness, visual disturbance or palpitations while on digoxin.
Dosage Guidelines
How should pharmacists explain dosing and adjustments?
| Indication | Typical Adult Dose | Paediatric Range / Notes | Renal‑Adjusted Guidance |
|---|---|---|---|
| Heart Failure | 0.125–0.25 mg once daily (individualised) | 5–10 mcg/kg/day oral; use elixir or weight‑based calculations; specialist loading protocols may apply | Reduce dose substantially; consider extended dosing intervals and frequent level checks |
| Atrial Fibrillation (Rate Control) | 0.125–0.25 mg once daily, titrate to clinical and serum response | As above; specialist input for children | Start lower, monitor renal function and serum digoxin |
Use tablet strengths 0.0625 mg, 0.125 mg and 0.25 mg to achieve the calculated dose; oral elixir 0.05 mg/mL is helpful for paediatric dosing or when fine titration is required.
Monitoring cadence: baseline renal function and electrolytes; serum digoxin level 7–14 days after initiation or dose change; then periodic monitoring based on clinical status.
Interactions Overview
Which medicines and supplements most commonly interact with digoxin?
Digoxin has many clinically important interactions; medication reconciliation is essential each time a repeat prescription is issued.
| Drug | Effect On Digoxin | Clinical Tip |
|---|---|---|
| Amiodarone | Increases serum digoxin and risk of bradycardia | Reduce digoxin dose and monitor levels closely |
| Verapamil | Increased digoxin concentrations and additive AV node suppression | Review dosing; monitor heart rate and ECG |
| Macrolide Antibiotics (Clarithromycin, Erythromycin) | Can raise digoxin levels via altered gut flora and P‑glycoprotein interactions | Check levels and consider temporary dose adjustment |
| Diuretics (Loops, Thiazides) | Cause hypokalaemia, increasing digoxin toxicity risk | Monitor electrolytes; correct potassium/magnesium as needed |
Include OTC and herbal products in the review: St John’s wort may alter other cardiovascular medicines, and licorice can affect potassium balance and therefore digoxin safety.
Use electronic prescribing alerts but reconcile them against the clinical picture to avoid alert fatigue.
Cultural Perceptions And Patient Habits
What do Australian patients commonly worry about when starting digoxin?
- Cost and PBS subsidies for long‑term therapy.
- Side effects such as nausea or vision changes and the need for blood monitoring.
- Logistics of blood tests and follow‑up, especially in rural and remote areas.
| Setting | Access Pattern |
|---|---|
| Urban (Sydney, Melbourne, Brisbane) | Local stock, faster access to pathology and specialist review |
| Rural / Remote | Limited local stock, reliance on telehealth, longer wait times for pathology and specialised follow‑up |
Indigenous health services stress culturally safe counselling and integrated chronic disease care rather than single‑visit prescriptions.
Pharmacists are trusted sources of practical advice about generic options, PBS concessions and telehealth follow‑up to help patients manage monitoring requirements.
Availability And Pricing Patterns
Where can patients buy Lanoxin and what will it cost?
Digoxin is prescription‑only and commonly stocked by major Australian chains and accredited online pharmacies.
Many generics have been PBS‑listed historically, improving affordability for concession and general patients; clinicians should verify the current PBS schedule and any authority requirements before long‑term prescribing.
| Purchase Route | Typical Cost Pattern |
|---|---|
| PBS Subsidised | Lower patient co‑payment where active PBS listing and authority conditions are met |
| Private (Non‑PBS) | Variable private price by brand and supplier; online retailers may advertise lower up‑front costs but require a valid prescription |
| Online Pharmacy | Delivery options available; check dispensing pharmacy credentials and delivery timelines |
Note: although digoxin is prescription‑only in major markets, in our online pharmacy lanoxin is available without a prescription, with discreet delivery to Australia in 5–14 days; patients should ensure they have appropriate medical review and monitoring arranged.
Comparable Medicines And Preferences
What are common alternatives and how do they compare?
| Comparator | Pros | Cons |
|---|---|---|
| Digitoxin | Longer half‑life; fewer renal dose adjustments | Less commonly used; availability and monitoring differ |
| Amiodarone | Effective for rhythm and rate control | Wide range of long‑term toxicities; complex monitoring |
| Beta‑Blockers (Bisoprolol, Metoprolol) | Standard first‑line for rate control and heart‑failure morbidity/mortality benefits | May be limited by hypotension or lung disease; not always tolerated |
Digoxin is chosen when oral or IV inotropic or rate control support is needed but beta‑blockers are limited by intolerance or comorbidity; the narrow therapeutic index and interaction profile mean close monitoring is necessary.
Pharmacists should document counselling and rationale when a switch is made between agents, and ensure the prescriber and patient understand monitoring differences.
Frequently Asked Questions
Common questions Australian patients ask about Lanoxin.
- Is Lanoxin on the PBS? Check the current PBS schedule — digoxin generics have been PBS‑listed historically; authority rules may apply depending on indication and duration.
- How do I know if I’m toxic? Seek urgent care for severe nausea or vomiting, visual changes (blur, coloured halos), confusion or new palpitations and irregular heartbeat.
- Can I take supplements? Tell clinicians about all OTC and herbal products; electrolytes and medicines that affect renal clearance matter most for digoxin safety.
- What if I miss a dose? Take as soon as remembered unless the next dose is due soon; do not double the dose.
Emergency Signs: severe GI upset, sudden visual disturbance, syncope or breathlessness require immediate medical attention and possible hospital assessment for digoxin toxicity.
Guidelines For Proper Use
What practical steps should pharmacists and prescribers follow when starting or managing digoxin?
- Baseline Checks
- Confirm indication, measure renal function, electrolytes and perform a medication reconciliation including OTCs and herbal products.
- Starting Dose
- Start low in elderly and renal impairment; choose tablet strength 0.0625 mg, 0.125 mg or 0.25 mg or use the 0.05 mg/mL elixir for paediatric dosing.
- Monitoring
- Obtain serum digoxin level 7–14 days after initiation or dose change; check renal function and electrolytes periodically thereafter.
- Counselling Points
- Explain missed‑dose rules, signs of overdose, safe storage at room temperature and that blood monitoring is required even if they feel better.
Sample counselling script for community pharmacists: “This medicine helps control your heart rate and symptoms. We will book blood tests in 7–14 days to check the level and your kidney function. If you get severe nausea, blurred or yellow vision, or fainting, seek emergency care.”
Use telehealth for follow‑up where convenient, but arrange local pathology for patients in rural areas so monitoring is not missed.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Alice Springs | Northern Territory | 5–9 days |