
Marevan
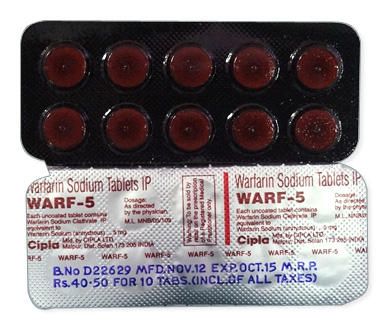
Marevan
- In our pharmacy, you can buy marevan without a prescription, with delivery throughout Australia. Discreet and anonymous packaging.
- Marevan is used to prevent and treat venous thromboembolism, reduce stroke risk in atrial fibrillation and prevent thrombosis in prosthetic heart valves; it is a vitamin K antagonist that inhibits the gamma‑carboxylation of clotting factors II, VII, IX and X (and proteins C and S), reducing blood clotting.
- The usual dose is an initial 2–5 mg once daily, with a maintenance range typically 2–10 mg per day individualized to INR monitoring; target INR is usually 2.0–3.0 (2.5–3.5 for some mechanical valves).
- The form of administration is oral tablets (commonly 1 mg, 3 mg and 5 mg tablets; other strengths are available).
- The effect begins within 24–72 hours; warfarin is not immediate and full anticoagulant effect may take 3–5 days due to existing clotting factor turnover.
- The duration of action is prolonged — anticoagulant effect can persist for 2–5 days after a dose (half‑life is variable, roughly 36–42 hours), so regular INR monitoring is required.
- Do not consume excessive alcohol — alcohol can increase bleeding risk and cause unpredictable changes in INR; discuss alcohol use with your clinician and avoid binge drinking.
- The most common side effect is minor bleeding (gum bleeding, nosebleeds) and easy bruising; other effects include hair loss, rash and, rarely, serious bleeding or skin necrosis.
- Would you like to try marevan without a prescription?
Basic Marevan Information
- INN (International Nonproprietary Name): Warfarin.
- Brand Names Available In Australia: Marevan (GlaxoSmithKline / Aspen Pharmacare) and Coumadin (Bristol‑Myers Squibb / Aspen / Mylan) are listed for Australia, with Marevan commonly supplied in 1 mg, 3 mg and 5 mg blister packs or bottles and Coumadin available in multiple scored tablet strengths.
- ATC Code: B01AA03 (Vitamin K Antagonists).
- Forms & Dosages: Oral tablets only in strengths including 1 mg, 2 mg, 2.5 mg, 3 mg, 4 mg, 5 mg, 6 mg, 7.5 mg and 10 mg; no standard injectable or liquid oral forms for human use.
- Manufacturers In Australia: Aspen Pharmacare / Boots Healthcare / Mylan and Bristol‑Myers Squibb are named suppliers for Australian market brands; generics and other international manufacturers also supply product to local distributors.
- Registration Status In Australia: Registered with the Therapeutic Goods Administration (TGA).
- OTC / Rx Classification: Prescription only (Rx).
Latest Research Highlights (Australian And International Studies 2022–2025)
Patients and clinicians ask whether warfarin still has a place alongside direct oral anticoagulants.
Large international meta‑analyses and registry reviews published to 2024–2025 confirm that DOACs such as rivaroxaban, apixaban, dabigatran and edoxaban generally match or exceed warfarin for stroke prevention in non‑valvular atrial fibrillation, with lower rates of intracranial haemorrhage.
Australian anticoagulation service audits from 2022–2025 show many rural INR‑managed clinics maintain stable control when point‑of‑care testing and telehealth are used, supporting continued warfarin use in selected settings.
Clinical trial evidence still supports warfarin for mechanical heart valves and severe mitral stenosis, and specialist guidance retains warfarin for some antiphospholipid syndrome phenotypes.
TGA pharmacovigilance and adverse‑event reporting remain important; major bleeding and drug interactions continue to be leading harms reported locally.
Pharmacogenomics (VKORC1 / CYP2C9) appears promising for dose individualisation, but routine PBS‑funded genotyping is not yet standard practice in Australia.
Readers should note evidence levels: randomised controlled trials and large cohort registries form the strongest basis of the DOAC vs warfarin comparisons, while Australian audits and TGA reports add pragmatic, real‑world context.
Clinical Effectiveness In Australia
Patients often want to know how well Marevan works in everyday Australian care compared with trial results.
TGA registration and PBS monitoring show consistent effectiveness for stroke prevention in atrial fibrillation when INR is maintained within target ranges, typically 2.0–3.0.
Anticoagulation clinics report time‑in‑therapeutic‑range (TTR) commonly between 55% and 70% in urban centres, and slightly lower where point‑of‑care testing is unavailable.
Real‑world PBS dispensing and TGA monitoring data combine with international RCT results to show that warfarin remains effective where close INR monitoring is feasible.
Clinical effectiveness depends strongly on monitoring, diet counselling and medication reconciliation to reduce bleeding and thrombotic events.
TGA adverse‑event summaries highlight major bleeding and interactions as principal causes for hospital presentation among patients on warfarin.
For many Australians with mechanical valves or DOAC contraindications, Marevan remains the evidence‑supported anticoagulant of choice.
Indications And Expanded Uses (TGA‑Approved And Off‑Label)
People ask: "When is Marevan the right medicine?"
TGA‑approved indications reflect global practice: prophylaxis and treatment of venous thromboembolism, stroke prevention in atrial fibrillation, and prevention of thromboembolism in prosthetic heart valves.
Australian practice extends to long‑term anticoagulation where DOACs are unsuitable — for example mechanical valves and significant mitral stenosis.
Specialist haematologists may use warfarin for certain antiphospholipid syndrome subtypes and complex thrombophilias as off‑label or specialist‑driven therapy.
Common INR targets are 2.0–3.0 for AF and VTE, and 2.5–3.5 for some mechanical valve prostheses.
Pregnancy is an important safety note: warfarin is generally contraindicated due to teratogenicity, except in rare, specialist‑managed mechanical valve cases with clear risk–benefit discussion.
Composition And Brand Landscape (Active Ingredient, Australian Brands)
Many patients search for brand names and tablet strengths when filling a prescription.
The active ingredient is warfarin (INN), classified under ATC B01AA03 as a vitamin K antagonist.
Marevan is a commonly recognised Australian brand supplied in 1 mg, 3 mg and 5 mg tablets in blister packs or bottles.
Coumadin is another brand present in Australia and generics are available in a wide range of strengths from 1 mg to 10 mg.
All available forms are oral tablets; there are no standard injectable or liquid human formulations.
Patients who are price conscious often pick generics or PBS‑subsidised brands at community pharmacies or large chains, while some prefer continuity with a trusted pharmacy.
Contraindications And Special Precautions (Australian High‑Risk Groups)
People understandably worry about who should not take warfarin.
Absolute contraindications include pregnancy, active major bleeding, severe uncontrolled hypertension, recent high‑bleed‑risk surgery, severe liver impairment and known hypersensitivity.
Relative contraindications or high‑monitoring groups include the elderly (start lower doses), frequent fallers, severe renal impairment, alcohol use disorder, poor adherence and concurrent antiplatelet therapy.
Indigenous and remote communities require special attention because higher comorbidity burdens and limited INR access increase safety risks; telehealth and local pharmacy point‑of‑care testing help mitigate these factors.
Counselling points for daily life cover activity risk assessment (contact sports), workplace safety with heavy machinery and driving considerations if there is bleeding risk or sudden incapacitation risk.
Dosage Guidelines (Standard Regimens And Australian Practice)
Common practical questions are "How much do I start with?" and "What if I miss a dose?"
Typical initiation in adults is 2–5 mg daily with prompt titration based on INR; elderly patients often start around 2 mg daily due to increased sensitivity.
Maintenance doses typically range from 2–10 mg per day and must be individualised by INR monitoring.
INR targets are generally 2.0–3.0 for atrial fibrillation and VTE, and 2.5–3.5 for select mechanical valve patients.
Children require specialist weight‑based dosing and frequent INR checks, while liver impairment calls for lower starting doses and careful monitoring.
Missed‑dose instructions: take as soon as remembered on the same day; do not double the next day; skip if near the next scheduled dose.
Overdose or major bleeding requires urgent vitamin K and possible prothrombin complex concentrate in hospital.
Interactions Overview (Food, Drink, Medicines; TGA And E‑Health Reports)
Patients often ask which foods and medicines will affect their INR.
Vitamin K–rich foods such as green leafy vegetables reduce warfarin effect and sudden dietary changes can destabilise INR control.
Alcohol can unpredictably increase bleeding risk and heavy drinking alters warfarin metabolism.
Drug interactions reported in Australian TGA summaries and e‑health systems include antibiotics (metronidazole, trimethoprim–sulfamethoxazole and some cephalosporins), azole antifungals, amiodarone, certain SSRIs/SNRIs, anticonvulsants (phenytoin, carbamazepine), NSAIDs and aspirin, and herbal supplements such as St John’s wort and ginkgo biloba.
Medication reconciliation at every dispensing, and active use of My Health Record or an e‑medication list, helps flag interactions before harm occurs.
- Action Points: Monitor INR, adjust dose, avoid combinations where advised by clinician.
Cultural Perceptions And Patient Habits (Australian Patient Behaviour)
Many Australians describe warfarin as effective but inconvenient due to monitoring and diet limits.
Patients report trust in pharmacists and anticoagulation nurses, with rural clinics and local pharmacies playing a key role in access and adherence.
Price sensitivity encourages PBS‑subsidised or generic choices at national chains or community pharmacies, but continuity of care with a known pharmacist is often prioritised.
Urban patients commonly switch to DOACs for convenience when clinically suitable, while rural patients may remain on warfarin due to cost, comorbidities or specialist advice.
Indigenous and remote communities cite travel for INR testing, cultural safety and competing health priorities as barriers that need tailored services.
- Common Concerns: Monitoring burden, dietary limits, bleeding fears, cost.
- Common Enablers: Point‑of‑care INR testing, telehealth, pharmacist counselling.
Availability And Pricing Patterns (Pharmacies, Online, PBS Vs Private)
Where and how patients obtain Marevan is a frequent question.
Marevan and generic warfarin are prescription‑only and stocked widely by national chains and community pharmacies across Australia.
PBS subsidies significantly reduce out‑of‑pocket costs for many eligible patients; private prices vary and chains often advertise competitive generic pricing.
Online pharmacies and telehealth e‑prescriptions are increasingly used, with dispensing still requiring a valid prescription and pharmacist counselling prior to supply.
In our online pharmacy, marevan is available without a prescription, with discreet delivery to Australia in 5‑14 days.
Multiple manufacturers supplying different brand packaging reduce the risk of national shortages, but regional strength availability can vary.
Comparable Medicines And Preferences (Alternatives In Australia)
Patients want to know the alternatives and why one might be chosen over another.
DOACs — rivaroxaban (Xarelto), apixaban (Eliquis), dabigatran (Pradaxa) and edoxaban (Lixiana) — are preferred in many non‑valvular AF and VTE settings for fixed dosing and no routine INR monitoring.
Other VKAs such as acenocoumarol and phenprocoumon are less commonly used in Australia.
Key pros for warfarin include proven efficacy in mechanical valves, cost advantages via PBS/generics and established reversal strategies with vitamin K and prothrombin complex concentrate.
Key cons include frequent INR monitoring, dietary and drug interactions and teratogenicity in pregnancy.
Shared decision‑making should balance indication, renal function, adherence ability, pregnancy plans and cost/PBS status.
FAQ — Common Australian Patient Questions
Q: Can I drink alcohol on warfarin?
A: Small, consistent amounts are usually tolerated, but avoid binge drinking and tell your clinician about any change in drinking patterns.
Q: What if I miss a dose?
A: Take the dose as soon as you remember on the same day; do not double up the next day and seek advice if multiple doses were missed.
Q: Can I switch from warfarin to a DOAC?
A: Many people with non‑valvular AF or VTE can switch, but this requires clinician review, renal function checks and a stop/start protocol.
Q: Is Marevan on the PBS?
A: Warfarin preparations are prescription‑only and are commonly PBS‑subsidised; confirm subsidy status with a pharmacist or the PBS schedule.
When To Seek Urgent Care: Major bleeding, sudden severe headache, haematuria, significant bruising or any sign of uncontrolled bleeding.
Guidelines For Proper Use And Pharmacist Counselling (Australian Practice)
Patients expect clear counselling at each supply.
Pharmacists should confirm indication, baseline INR and target range, and provide counselling on consistent vitamin K intake, interactions, missed‑dose rules and bleeding signs.
Use of My Health Record and up‑to‑date e‑medication lists at every dispensing reduces interaction risk.
For rural patients, pharmacists can arrange point‑of‑care INR testing or coordinate telehealth with a local anticoagulation clinic.
- Counselling Checklist: Indication, dosing, INR schedule, interactions, emergency actions, travel and pregnancy warnings.
Provide a written dosing card and encourage enrolment in an anticoagulation clinic or pharmacist‑managed monitoring programme where available.
Report adverse events to the TGA and ensure prescriptions meet any PBS authority requirements.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |