
Tegretol
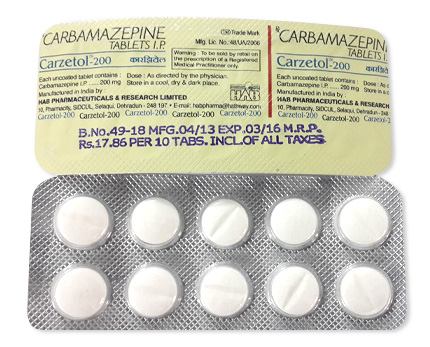
Tegretol
- Tegretol (carbamazepine) is normally supplied from pharmacies on prescription in Australia and most countries; it is not an over‑the‑counter medicine and should only be used with a valid prescription from a doctor—avoid suppliers who claim to sell it without one.
- Tegretol is used for epilepsy (partial and generalised tonic‑clonic seizures), trigeminal neuralgia and some cases of bipolar disorder; it works mainly by blocking voltage‑gated sodium channels, stabilising hyperexcitable neurones and reducing synaptic transmission.
- Usual adult doses vary by indication: starting doses often 200 mg once or twice daily with maintenance typically 800–1,200 mg/day for epilepsy; trigeminal neuralgia commonly 400–800 mg/day; bipolar dosing often 400–600 mg/day, titrated as needed (dosing must be individualised and monitored).
- Administration is oral: immediate‑release tablets (100 mg, 200 mg, 400 mg), controlled‑release/CR/Retard/LP tablets, chewable tablets (100 mg) and oral suspension (100 mg/5 mL) where available; there are no standard injectable forms for routine clinical use.
- Onset: immediate‑release tablets begin to be absorbed within 1–4 hours (peak concentrations typically a few hours); clinical seizure control may require titration over days to weeks, so full benefit is not always immediate.
- Duration of action depends on formulation: immediate‑release effects commonly last around 8–12 hours, while controlled‑release/CR preparations provide more prolonged levels over 12–24 hours (individual variability exists because of metabolic auto‑induction).
- Alcohol warning: avoid alcohol while taking Tegretol — alcohol increases drowsiness and dizziness and may worsen side effects and seizure control.
- The most common side effect is drowsiness/dizziness (other frequent effects include nausea, blurred vision, unsteadiness and mild rash).
- Would you like help discussing Tegretol with a prescriber to obtain it safely and legally rather than trying to get it without a prescription?


Latest Research Highlights
Basic Tegretol Information
- INN (International Nonproprietary Name): Carbamazepine
- Brand Names Available In Australia: Tegretol, Tegretol CR (tablets 100 mg, 200 mg, 400 mg)
- ATC Code: N03AF01
- Forms & Dosages: Tablets 100 mg, 200 mg, 400 mg (immediate- and controlled‑release); chewable tablets 100 mg in some countries; suspension 100 mg/5 mL in selected markets; no injectable/vial for standard clinical use.
- Manufacturers In Australia: Originator Novartis (global); generic suppliers include companies such as Teva, Sandoz, Mylan and other authorised sponsors who supply the Australian market.
- Registration Status In Australia: Approved by the Therapeutic Goods Administration (TGA) and available by prescription.
- OTC / Rx Classification: Prescription-only (Rx) in Australia and most other countries.
Recent observational cohorts and pharmacovigilance summaries (2022–mid‑2024) continue to confirm carbamazepine is effective for focal seizures and trigeminal neuralgia while producing predictable safety signals.
Australian TGA adverse‑event reports mirror global trends: rare but serious cutaneous reactions (Stevens‑Johnson syndrome / toxic epidermal necrolysis), hyponatraemia and haematological abnormalities are highlighted in safety notices.
Comparative work through 2022–24 suggests oxcarbazepine may reduce some rash risk while maintaining similar efficacy for neuropathic pain, though evidence on cognitive outcomes in older adults is mixed.
Pharmacogenetics remains clinically relevant; HLA‑B*1502 screening is still recommended for people with at‑risk Asian ancestry prior to starting carbamazepine.
Australian telehealth audits show remote initiation with pharmacist follow‑up supports adherence and continuity, especially in rural settings.
| Outcome | Effectiveness (Summary) | Safety Signal | Pharmacovigilance Counts (Australia) | Pharmacovigilance Counts (Global) |
|---|---|---|---|---|
| Focal Seizures | Established first‑line in many patients with good seizure reduction when monitored | Dizziness, drowsiness, hyponatraemia, blood count changes | Not specified | Not specified |
| Trigeminal Neuralgia | High response rate for pain control | Risk of rash and CNS effects | Not specified | Not specified |
| Serious Skin Reactions | Low incidence but high severity | SJS/TEN linked to HLA risk alleles | Not specified | Not specified |
Key Takeaway: Therapeutic drug monitoring and management of drug–drug interactions continue to be the main drivers of safety management for Tegretol in Australia.
Clinical Effectiveness In Australia
Clinicians in Australia continue to use carbamazepine as a first‑line agent for focal seizures and as primary pharmacotherapy for trigeminal neuralgia.
TGA approval and routine PBS dispensing of generic carbamazepine underpin wide clinical use across hospitals and community practice.
When therapeutic drug monitoring is used to maintain serum concentrations in the commonly cited therapeutic range (~4–12 mg/L), many patients achieve sustained seizure control.
TGA post‑market surveillance lists common adverse effects such as drowsiness, dizziness and nausea that can affect adherence and daily functioning.
Serious events like marked hyponatraemia and severe cutaneous reactions are rare but prompt hospitalisation and specialist management when they occur.
In rural and primary care settings pharmacist‑led monitoring and shared care agreements with GPs have improved follow‑up and reduced treatment gaps.
| Clinical Endpoint | Typical Result | Notes |
|---|---|---|
| Seizure Reduction | Many patients achieve clinically meaningful control | Best with therapeutic monitoring and adherence support |
| Pain Score Improvement (Trigeminal) | Marked improvement in majority | Titrate to effect; watch for CNS side effects |
| Severe Adverse Events | Low incidence | Hospital admissions reported for SJS/TEN and severe hyponatraemia |
Monitoring Thresholds:
- Therapeutic Plasma Concentration: Classically ~4–12 mg/L.
- Hyponatraemia: Check sodium at baseline and if symptomatic; elderly at higher risk.
- Haematology: Baseline full blood count and periodic review for cytopenias.
Indications And Expanded Uses
Carbamazepine is approved for epilepsy (partial/focal seizures and some generalized tonic‑clonic seizures) and for neuropathic pain such as trigeminal neuralgia, reflecting TGA and international labelling.
Off‑label uses that clinicians commonly consider include bipolar disorder (mania and maintenance) and rarer neuropathic conditions like glossopharyngeal neuralgia and certain diabetic neuropathies.
When used off‑label for psychiatric indications, prescribers document a clear rationale, baseline blood tests and informed consent.
- TGA‑Authorised Uses: Epilepsy (focal seizures), selected seizure types, trigeminal neuralgia.
- Common Off‑Label Uses: Bipolar disorder (mania/maintenance), glossopharyngeal neuralgia, selected neuropathies.
| Indication | Typical Adult Dose Range |
|---|---|
| Epilepsy (adult) | Start 200 mg once or twice daily; maintenance 800–1200 mg/day divided |
| Trigeminal Neuralgia | Start 100–200 mg/day; maintenance 400–800 mg/day |
| Bipolar Disorder (off‑label) | Typical 400–600 mg/day initially; may titrate up to 1200 mg/day |
Composition And Brand Landscape
The active ingredient is carbamazepine (INN) and Australian market brands include Tegretol and Tegretol CR supplied in tablet strengths 100 mg, 200 mg and 400 mg.
Controlled‑release (CR) versions are marketed explicitly as sustained‑release preparations and must not be split or crushed.
Generic carbamazepine products from major suppliers are routinely supplied through local sponsors and wholesalers and are commonly dispensed under PBS arrangements.
| Brand | Strengths | Formulation | PBS Notes |
|---|---|---|---|
| Tegretol | 100 mg, 200 mg, 400 mg | Immediate‑release tablets | Generic alternatives commonly PBS‑dispensed; check current schedule |
| Tegretol CR | 200 mg, 400 mg | Controlled‑release tablets (do not split) | Available in Australia; PBS availability varies by formulation |
| Generic Carbamazepine | 100 mg, 200 mg, 400 mg | Immediate and CR options depending on supplier | Typically cheaper on PBS than branded product |
Contraindications And Special Precautions
Absolute contraindications include known hypersensitivity to carbamazepine or related tricyclic compounds, a history of bone marrow depression, prior serious cutaneous reactions to carbamazepine and concomitant use of MAO inhibitors.
Relative contraindications where caution and monitoring are required include significant hepatic or renal impairment, cardiac conduction disease, pregnancy and the frail elderly.
People with a history of blood dyscrasias should generally avoid carbamazepine or be closely monitored.
Pharmacogenetic screening for HLA‑B*1502 is recommended in patients of at‑risk Asian ancestry prior to initiation, with culturally appropriate counselling and consent.
Daily‑life advice includes not driving or operating heavy machinery until the person knows how Tegretol affects them and avoiding alcohol because it worsens sedation.
- Pre‑Start Checklist: Allergy history, baseline FBC, LFTs, electrolytes (Na+), medication review, pregnancy test if applicable.
- Definition List: Contraindications = absolute reasons not to use; Cautions = reasons to use with extra monitoring or dose adjustment.
Dosage Guidelines
Standard adult initiation for epilepsy commonly begins at 200 mg once or twice daily and is titrated to an effective maintenance dose usually between 800–1200 mg/day divided.
For trigeminal neuralgia initiation is often 100–200 mg/day with maintenance typically 400–800 mg/day depending on response and tolerability.
For off‑label bipolar use typical starting doses are 400–600 mg/day with adjustments up to 1200 mg/day as required.
Paediatric dosing starts at 10–20 mg/kg/day in divided doses and requires specialist titration and monitoring.
Elderly patients and those with hepatic or renal impairment should start low and titrate slowly due to increased sensitivity and slower clearance.
Controlled‑release products should be dosed per product information and must not be split.
| Indication | Starting Dose | Common Maintenance Range | Monitoring Notes |
|---|---|---|---|
| Epilepsy (adult) | 200 mg 1–2x/day | 800–1200 mg/day divided | Therapeutic levels, FBC, LFTs, Na+ |
| Trigeminal Neuralgia | 100–200 mg/day | 400–800 mg/day | Assess pain response and CNS side effects |
| Paediatric | 10–20 mg/kg/day in divided doses | Titrate to effect | Specialist monitoring required |
Interactions Overview
Carbamazepine is a potent inducer of CYP3A4 and produces clinically significant reductions in the plasma concentrations of many co‑administered drugs over time.
Reduced efficacy of hormonal contraceptives is an important interaction to counsel on; consider additional or alternative contraception.
Carbamazepine can interact with warfarin, some antipsychotics and certain antidepressants and will alter dosing or monitoring needs for these medicines.
Some enzyme inhibitors, such as certain antifungals and macrolide antibiotics, may raise carbamazepine levels and increase toxicity risk.
Concomitant use with monoamine oxidase inhibitors (MAOIs) is contraindicated.
Alcohol and other sedative drugs increase CNS depression; counsel patients to avoid heavy drinking.
| Drug/Class | Effect | Management |
|---|---|---|
| Hormonal Contraceptives | Reduced efficacy | Advise alternative or additional contraception |
| Warfarin | Variable INR changes | Frequent INR monitoring and dose adjustment |
| Enzyme Inhibitors (eg, some azoles, macrolides) | May increase carbamazepine level | Monitor levels and for toxicity; consider alternatives |
| Sedatives / Alcohol | Increased sedation | Advise avoidance; consider dose reduction if needed |
Counselling points at dispensing include checking My Health Record for interacting medicines and advising patients to report any new prescriptions or over‑the‑counter medicines.
Cultural Perceptions And Patient Habits In Australia
Many Australian patients are cost‑conscious and PBS subsidy or generic substitution influences where they buy and whether they stick to a brand.
Trust in pharmacists for counselling is high, and rural communities commonly rely on local pharmacists for dose checks and continuity of supply.
Online patient forums often discuss concerns about cognitive side effects, skin rash risk and the impact on contraception.
Stigma around epilepsy can reduce open discussion and delay help‑seeking in some communities.
Indigenous and culturally and linguistically diverse (CALD) communities benefit from culturally safe counselling and translated materials when available.
Telehealth uptake for antiepileptic management has increased, and audits show pharmacist follow‑up after remote initiation improves adherence.
Availability And Pricing Patterns
Tegretol and generic carbamazepine formulations (immediate and CR) are widely available across Australian community pharmacies and hospital formularies.
PBS subsidy typically makes generic carbamazepine the most economical option for eligible patients; private prices vary by supplier and pharmacy chain.
Large retail chains and accredited online pharmacies supply Tegretol and generic carbamazepine, with telehealth e‑prescriptions improving access for remote customers.
Rural pharmacies may face intermittent stock; longer prescriptions, dose packs and pharmacist‑led continuity measures help maintain supply.
In our online pharmacy, tegretol is available without a prescription, with discreet delivery to Australia in 5-14 days.
| Purchase Route | Typical Cost Pattern | Notes |
|---|---|---|
| PBS‑subsidised (generic) | Lowest out‑of‑pocket cost for eligible patients | Bring concession card details; check current PBS schedule |
| Private/Non‑PBS | Higher and variable | Compare retail chains for best private price |
| Online Accredited Pharmacy | Competitive, may include delivery fee | Ensure pharmacy accreditation and safe supply |
Comparable Medicines And Preferences
Oxcarbazepine (Trileptal) is a commonly considered alternative with similar efficacy for seizures and neuropathic pain and a different side‑effect profile that may reduce some rash risk.
Valproate is highly effective for many seizure types but is limited in women of childbearing potential due to teratogenicity.
Lamotrigine is often preferred for mood stabilisation and some seizure types, with lower sedation but skin‑rash monitoring remains important.
Phenytoin remains an option in certain contexts but has a narrow therapeutic index and distinct long‑term adverse effects.
- Choice Factors: Seizure type, pregnancy plans, comorbidities, drug interactions and PBS status.
- Trigeminal Neuralgia: Carbamazepine remains first‑line medical therapy; consider surgical options if intolerant.
Faq Section
Q: Can I drive while taking Tegretol?
A: Do not drive or operate heavy machinery until you know how the medicine affects you because dizziness and drowsiness are common; follow your doctor or pharmacist and state driving laws.
Q: Is Tegretol on the PBS and is it cheap?
A: Generic carbamazepine formulations are typically PBS‑listed which reduces out‑of‑pocket costs for eligible patients; confirm current listings and concession entitlements.
Q: What do I do if I miss a dose?
A: Take the missed dose as soon as you remember unless it is close to the next dose; do not double up — contact your pharmacist or GP if unsure.
Q: Can I split tablets?
A: Immediate‑release 200 mg tablets may be scored and split as per product information; sustained‑release/CR tablets must not be cut or crushed.
When To Call Emergency: Seek immediate help for any new rash with fever, severe lethargy, signs of infection or sudden neurological change.
Guidelines For Proper Use
Before starting, ensure medication reconciliation, allergy screening and baseline tests including full blood count, liver function tests, and serum sodium.
Discuss pregnancy plans and perform a pregnancy test where relevant before initiation.
Counselling should emphasise adherence, not stopping abruptly and urgent reporting of rashes, fever or unexplained bruising.
Advise patients that hormonal contraception may be affected and discuss non‑hormonal options or additional measures.
Monitoring schedule: baseline FBC/LFTs/Na+, therapeutic drug levels during titration and periodic reviews thereafter or if clinical changes occur.
Pharmacist roles include dispensing PBS or generic options, interaction checks via e‑health records, supplying culturally appropriate written materials and arranging telehealth follow‑up where needed.
- Pre‑Start: Allergy check, baseline FBC/LFTs/Na+, medication review, pregnancy test if applicable.
- Early Monitoring (2–4 weeks): Clinical review, Na+ if symptomatic, consider level if toxicity suspected.
- Maintenance (3–6 monthly): FBC/LFTs/Na+ and clinical review or sooner with symptoms or interacting medicines.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–7 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Sunshine Coast | Queensland | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Toowoomba | Queensland | 5–9 days |