
Eldepryl
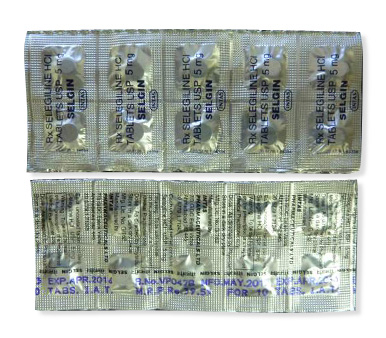
Eldepryl
- In pharmacies, Eldepryl is generally prescription-only in most jurisdictions (including the US, UK, EU and Australia); it is supplied through licensed pharmacies and wholesalers, although some pharmacies or online vendors may offer it without a receipt — this is not recommended and may be illegal in your area.
- Eldepryl (selegiline) is used mainly as an adjunct treatment for Parkinson’s disease to boost dopaminergic activity by irreversibly inhibiting monoamine oxidase B (MAO‑B); transdermal selegiline (Emsam) is also used for major depressive disorder in some formulations.
- The usual dose for Parkinson’s disease is 5–10 mg daily (often 5 mg twice daily) for tablets/capsules; orally disintegrating tablets (Zelapar) are typically 1.25–2.5 mg once daily; dosing may be adjusted when given with levodopa/carbidopa.
- Administration is oral (tablets or capsules), orally disintegrating tablet, or transdermal patch (Emsam); the Eldepryl brand is usually given as 5 mg tablets or capsules.
- Onset time: MAO‑B inhibition begins within hours of dosing, but meaningful symptomatic improvement may take days to weeks of continuous treatment.
- Duration of action: pharmacological MAO‑B inhibition can persist for 24 hours or longer due to irreversible enzyme inhibition; clinical effects are maintained with daily dosing.
- Alcohol warning: avoid excessive alcohol — it can worsen dizziness, orthostatic hypotension and other side effects; additionally take care with tyramine‑rich foods (and follow medical advice) to reduce risk of hypertensive reactions, especially with transdermal formulations.
- The most common side effect is nausea (other frequent effects include dry mouth, dizziness, insomnia, headache and increased sweating; more serious risks such as hallucinations or hypertensive crises can occur, especially with interacting drugs).
- Would you like to try eldepryl without a prescription?

Basic Eldepryl Information
- INN (International Nonproprietary Name): Selegiline (also known as Selegilina, Selegilinum, L‑Deprenalin).
- Brand Names Available In Australia: Brand listings from international markets include Eldepryl and Zelapar (capsules 5 mg; orally disintegrating tablets Zelapar), Emsam transdermal patch, and various generic labels such as Selegilina.
- ATC Code: N04BD01 — Monoamine Oxidase B Inhibitors, classified for use in anti‑parkinson drugs.
- Forms & Dosages: Tablets 5 mg and 10 mg (blisters of 28 or 100), Capsules 5 mg, Orally Disintegrating Tablet (Zelapar) 1.25 mg, Transdermal Patch (Emsam) 6 mg, 9 mg, 12 mg per 24 hr.
- Manufacturers In Australia: Not specified in the source data for Australia specifically; international suppliers include Somerset Pharmaceuticals, Valeant, Mylan, Sun Pharma, Teva, Sandoz, Intas and Abbott — verify TGA sponsor for Australian registration.
- Registration Status In Australia: Not specified in the source data for Australia; internationally selegiline is prescription‑only and approved by major regulators such as FDA, EMA and MHRA — check the TGA register for current Australian listings.
- OTC / Rx Classification: Prescription only (Rx) in most jurisdictions per the source data; confirm current TGA and PBS classification for local dispensing.
Latest Research Highlights — Australian & International (2022–2025)
Are you wondering what recent studies mean for people taking selegiline for Parkinson’s disease?
Recent meta‑analyses and long‑term observational cohorts from 2022 to 2025 refine the role of MAO‑B inhibitors such as selegiline in Parkinson’s management.
Overall evidence shows modest motor benefit and suggests MAO‑B inhibitors can delay escalation of levodopa in early disease, but effect sizes vary between studies.
Australian observational cohorts from movement‑disorder clinics and state health datasets reported improved time‑to‑first‑levodopa‑increase while stressing heterogeneous outcomes and clinician prescribing differences.
Regulatory pharmacovigilance summaries (FDA, EMA, TGA public reports) maintain orthostatic hypotension, insomnia and drug interactions as the most reported adverse events in older, polypharmacy populations.
Comparative work since 2022 highlights rasagiline and safinamide as alternative MAO‑B strategies with different dosing and convenience profiles.
Transdermal selegiline (Emsam) remains relevant for depression in some markets, but it is not a direct substitute for oral Parkinson’s formulations like Eldepryl.
Data trends point toward earlier adjunctive MAO‑B use in some clinics, while long‑term disease‑modifying claims remain uncertain.
Study Summary Table (2022–2025)
| Study Type | Population | Main Outcome | Safety Signals | Level Of Evidence |
|---|---|---|---|---|
| Meta‑analysis | Early Parkinson’s (multiple RCTs) | Modest motor score improvement | Insomnia, dizziness reported | Moderate |
| Observational Cohort (Australia) | Clinic and state datasets | Delayed levodopa escalation | Orthostatic hypotension in elderly | Low‑Moderate |
| Comparative Trial | MAO‑B agents | Similar motor benefit; differing dosing | Drug interactions noted | Moderate |
Use the INN and ATC anchors when discussing pharmacology: selegiline (ATC N04BD01) is available as tablets, capsules and an orally disintegrating tablet according to product information.
Clinical Effectiveness In Australia
Patients and clinicians ask: Does selegiline actually help with motor symptoms in everyday practice?
In Australian clinical practice, selegiline (Eldepryl and generic selegiline) is primarily used as adjunctive therapy in early‑to‑moderate Parkinson’s disease to smooth motor fluctuations and potentially delay levodopa escalation.
TGA classifies selegiline as a prescription‑only MAO‑B inhibitor with ATC code N04BD01.
State clinic audits and hospital pharmacy data indicate modest symptomatic gains measured by UPDRS motor subsections and fewer wearing‑off episodes when combined with levodopa/carbidopa.
PBS impact influences prescribing; where selegiline is not fully subsidised clinicians often prefer PBS‑listed alternatives.
TGA adverse‑event reports in Australia mirror international findings: orthostatic hypotension, insomnia and hallucinations are more common in elderly patients with polypharmacy.
Measured Outcomes
- Motor Scores (UPDRS Motor Subscale): modest improvement in selected cohorts.
- Levodopa Dose Change: delayed need for dose escalation in some observational samples.
- Quality Of Life: mixed results, small positive signals in early adjunctive use.
Outcome → Level Of Evidence
| Outcome | Level Of Evidence |
|---|---|
| Motor symptom smoothing | Moderate (RCTs + cohorts) |
| Delay in levodopa escalation | Low‑Moderate (observational) |
| Long‑term disease modification | Insufficient evidence |
Prescribers and pharmacists should note available dosing options from product data: tablets 5 mg and 10 mg, capsule 5 mg, and Zelapar ODT 1.25 mg, so dosing counselling reflects formulation differences.
Indications & Expanded Uses (TGA + Off‑Label)
What is selegiline approved for, and when is off‑label use considered?
TGA‑aligned approvals mirror international licences: selegiline is indicated as an antiparkinsonian MAO‑B inhibitor (ATC N04BD01) and is used primarily as adjunctive therapy with levodopa/carbidopa for Parkinson’s disease symptom control.
Off‑label uses observed in Australian neurology clinics include strategies to reduce levodopa wearing‑off and occasional experimental adjunctive approaches for refractory motor fluctuations.
Transdermal selegiline (Emsam) is licensed for depression in some jurisdictions but is not a direct substitute for oral Parkinson’s dosing such as Eldepryl.
Contraindicated combinations include other MAOIs, certain opioids (for example meperidine) and serotonergic polypharmacy; tyramine cautions also apply.
Definitions
- Approved Indication: Adjunctive therapy in Parkinson’s disease with levodopa/carbidopa per product summaries.
- Common Off‑Label Use: Reducing wearing‑off periods and clinician‑led adjunctive strategies in complex cases.
- Contraindicated Combinations: Concurrent use with other MAOIs, certain opioids (eg. meperidine), and highly serotonergic agents.
Always cross‑check current TGA product information and PBS listings before prescribing or dispensing.
Use formulation data (tablets, capsule, ODT, patch) to match indication and patient needs when advising prescribers or patients.
Composition & Brand Landscape
Which brands and formulations should pharmacists expect to see when sourcing selegiline for patients?
The active ingredient is selegiline (INN).
International brand landscape includes Eldepryl (tablets/capsules), Zelapar (orally disintegrating tablet) and Emsam transdermal patch in some markets.
Available formulations per product data: tablets 5 mg and 10 mg, capsules 5 mg, ODT 1.25 mg (Zelapar), and transdermal patches 6/9/12 mg per 24 hr (Emsam).
Suppliers and manufacturers vary by region; examples from the source data include Somerset Pharmaceuticals, Valeant, Mylan, Sun Pharma, Teva and Sandoz.
Brand → Form → Typical Packaging → Likely Supplier Region
| Brand | Form | Typical Packaging | Supplier Region |
|---|---|---|---|
| Eldepryl | Capsule / Tablet | Capsules 5 mg; tablets 5/10 mg (blisters) | United States / United Kingdom |
| Zelapar | Orally Disintegrating Tablet | ODT 1.25 mg (blisters) | United States / Global |
| Emsam | Transdermal Patch | Patches 6/9/12 mg per 24 hr | Global |
| Generic Selegilina | Tablet / Capsule | Variable blisters | India / EU |
Pharmacist Checklist
- Confirm TGA sponsor and Australian registration before ordering.
- Check PBS authority criteria and potential substitution rules.
- Verify interchangeability between ODT (Zelapar) and standard tablets—formulation differences can affect dosing and administration.
Contraindications & Special Precautions
Which patients should avoid selegiline, and who needs careful monitoring?
Absolute contraindications from product data include known hypersensitivity to selegiline, concurrent use with other MAOIs, certain opioids such as meperidine, serotonergic agents and pheochromocytoma due to hypertensive crisis risk.
Relative contraindications requiring monitoring include peptic ulcer disease, severe cardiovascular disease, and mental status disorders such as psychosis or mania.
Elderly patients with polypharmacy are at higher risk of orthostatic hypotension, falls and hallucinations, so start low and monitor closely.
Selegiline safety in pregnancy and breastfeeding is not established; avoid unless benefit outweighs risk and consult specialist guidance.
Special attention is needed for Indigenous and remote populations where comorbidity burden and access barriers can magnify adverse outcomes; involve local Aboriginal Medical Services and culturally safe counselling.
When To Avoid Vs Monitor
| Situation | Action |
|---|---|
| Concurrent MAOI or meperidine | Avoid — contraindicated |
| Age >75 with multiple meds | Use lower start dose, monitor BP and cognition |
| Pheochromocytoma | Avoid — hypertensive crisis risk |
Counsel patients on lifestyle and work restrictions: avoid driving or operating machinery until they know how selegiline affects them due to possible dizziness or insomnia.
Dosage Guidelines (Australian Practice & PBS References)
How should selegiline be started and adjusted in everyday clinical care?
Standard adult dosing per product information is 5–10 mg daily, commonly given as 5 mg twice daily for tablets/capsules.
Orally disintegrating tablets such as Zelapar are available in 1.25 mg and often used once daily with 1.25–2.5 mg options noted in product data.
In Australian practice, start at the low end for elderly patients and titrate according to motor response and adverse effects.
When combined with levodopa/carbidopa, monitor for additive dopaminergic effects and consider reducing levodopa if dyskinesia occurs.
Renal or hepatic impairment requires caution and consideration of dose reduction and clinical monitoring.
Common Regimens
| Use | Typical Regimen |
|---|---|
| Monotherapy / Adjunct | 5 mg twice daily (tablets/capsules) |
| ODT Option | Zelapar 1.25–2.5 mg once daily |
| Elderly Start | 5 mg once daily, titrate as tolerated |
Missed dose advice: take as soon as remembered unless near next dose; do not double up.
Overdose can cause severe hypertension, agitation, convulsions or hallucinations — seek immediate medical attention.
Interactions Overview (Drugs, Food & Alcohol)
What to check for when a patient is on selegiline?
Major drug interactions include other MAO inhibitors, certain opioids such as meperidine, and strong serotonergic agents which can precipitate serotonin syndrome or hypertensive crises.
Sympathomimetics and some decongestants can provoke hypertensive responses when combined with selegiline.
Tricyclic antidepressants, SSRIs, SNRIs and certain analgesics require careful washout periods and specialist consultation if combined.
Although selective MAO‑B inhibition at therapeutic doses reduces tyramine risk versus non‑selective MAOIs, counsel patients about large amounts of aged cheese, cured meats and other high‑tyramine foods.
Alcohol may worsen hypotension or orthostatic symptoms.
Interaction Table
| Interacting Agent | Clinical Risk / Action |
|---|---|
| Other MAOIs | Hypertensive crisis — do not combine |
| Meperidine and certain opioids | Severe reactions — contraindicated |
| SSRIs / SNRIs / TCAs | Risk of serotonin syndrome — allow washout per guidance |
| Sympathomimetics (eg. pseudoephedrine) | Hypertensive response — avoid or monitor |
Pharmacist dispensing checklist: review full med list for serotonergic agents and opioids, ask about OTC decongestants, advise dietary caution and document counselling in the patient record.
Cultural Perceptions & Patient Habits In Australia
What do Australian patients worry about when starting selegiline?
Cost, side‑effects and ease of dosing top patient priorities across urban and regional Australia.
Many patients rely on PBS subsidies and trust pharmacists at chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart for advice about access and substitution.
Online forums and local support groups report mixed experiences: some value symptom smoothing and reduced levodopa needs while others stop because of sleep disturbance or dizziness.
Rural and remote communities face access barriers including stockouts and longer travel to specialists, so telehealth e‑prescriptions and pharmacy delivery are commonly used.
Indigenous patients often prefer community‑controlled health services and culturally adapted counselling; involve Aboriginal Health Workers and local services for shared decision‑making.
Patient Priorities
- Cost and PBS subsidy status.
- Side‑effect risk (insomnia, dizziness).
- Ease of dosing and formulation (ODT vs tablet).
Access Pathways: Urban Vs Rural
| Urban | Rural |
|---|---|
| Multiple pharmacy chains, walk‑in specialist clinics | Telehealth prescribing, pharmacy home delivery, longer waits for neurology review |
Pharmacists remain a trusted source for PBS enquiries, substitution and local availability checks.
Availability & Pricing Patterns (Pharmacies, PBS & Online)
How easy is it to get eldepryl in Australia and what will it cost?
Availability across Australian pharmacy chains varies by brand and supplier agreements; generics are often easier to source than brand names like Eldepryl or Zelapar.
Chemist Warehouse, Priceline and TerryWhite Chemmart can often order stock, and online pharmacies and telehealth services provide home delivery — useful for rural patients.
PBS status affects uptake; if selegiline is not fully PBS‑listed for a patient’s indication, private prescribing leads to out‑of‑pocket costs and drives patients toward generics or alternative MAO‑B agents.
In our online pharmacy, eldepryl is available without a prescription, with discreet delivery to Australia in 5‑14 days.
Availability & Pricing Comparison (Indicative)
| Source | PBS Price | Private Price (Approx) | Notes |
|---|---|---|---|
| Large Chain Pharmacy | Check PBS Schedule | Variable by brand | Generics often cheaper; confirm stock |
| Online Pharmacy | Depends on subsidy | Delivery fees may apply | Home delivery for rural areas |
| Specialist Clinic Supply | Depends on authority script | Higher private cost | May have limited brand choice |
Pharmacists should confirm TGA sponsor details and storage guidance: store below 25°C and keep in original packaging per product data.
Check wholesalers such as Sun Pharma, Teva and Sandoz for lead times when ordering stock.
Comparable Medicines & Prescriber Preferences
Which alternatives do prescribers choose instead of selegiline?
Common alternatives within the MAO‑B and adjunct spectrum include rasagiline and safinamide, and COMT inhibitors like entacapone and tolcapone when levodopa wearing‑off is the main problem.
Rasagiline is often favoured for once‑daily dosing and perceived convenience.
Safinamide offers reversible MAO‑B inhibition and additional glutamatergic modulation, which some prescribers use when exploring different mechanisms.
Choice depends on clinical features, comorbidities, PBS availability and patient preference.
Agent → Dosing → Pros/Cons → PBS Note
| Agent | Dosing | Pros | Cons / PBS Note |
|---|---|---|---|
| Selegiline | 5–10 mg/day; Zelapar ODT 1.25–2.5 mg | Long clinical history; multiple formulations | More interaction potential; dosing frequency |
| Rasagiline | Once daily | Convenient dosing | May be preferred if PBS‑listed |
| Safinamide | Once daily | Reversible MAO‑B, additional modulation | Different mechanism; check subsidy |
Discuss formulation preferences with patients: ODTs may suit those with swallowing difficulties, while tablets and capsules provide standard dosing options.
Frequently Asked Questions (Australian Patient Focus)
What do Australians most often ask about eldepryl and selegiline?
- Is Eldepryl on the PBS? — Check the current PBS Schedule; prescribers should confirm authority requirements and discuss co‑payments with patients.
- Can I take selegiline with my antidepressant? — Generally avoid combining with SSRIs or SNRIs without a safe washout; contact the prescriber or pharmacist for advice.
- Will selegiline make me sleepy or dizzy? — Insomnia and orthostatic hypotension are reported; monitor and avoid driving until effects are known.
- Can I get selegiline in a patch? — A transdermal patch (Emsam) exists for depression in some markets but is not the typical Parkinson’s formulation; check TGA registration and indication.
If experiencing severe headache, chest pain or signs of hypertensive crisis seek emergency care immediately.
Typical dosing reference for context: 5–10 mg/day for tablets; Zelapar ODT 1.25–2.5 mg once daily.
Contact local pharmacy chains or telehealth services for availability and PBS queries.
Guidelines For Proper Use — Counselling & Pharmacy Practice
How should pharmacists counsel patients starting selegiline?
Verify the indication and TGA‑approved product when accepting a prescription or providing telehealth advice.
Confirm a full medication list with special attention to serotonergic agents, opioids and sympathomimetics.
Explain dosing clearly: common tablet regimen is 5 mg twice daily while Zelapar ODT is usually 1.25–2.5 mg once daily per product data.
Advise storage below 25°C and encourage patients to keep medicines in original packaging.
Monitor side effects: recommend orthostatic blood pressure checks, watch for sleep disturbances and hallucinations, particularly in older adults with polypharmacy.
Use culturally safe communication for Indigenous patients and engage Aboriginal Medical Services or interpreters when appropriate.
Stepwise Counselling Checklist
- Confirm indication and check for contraindicated medicines (MAOIs, meperidine, strong serotonergics).
- Explain dosing and missed‑dose rules; demonstrate ODT administration if needed.
- Advise on dietary caution with high‑tyramine foods and alcohol moderation.
- Discuss PBS authority requirements and assist with substitution or cost‑saving options.
- Set referral triggers: severe hypertension, signs of serotonin syndrome, severe agitation or suspected overdose.
Pharmacist Scripting Template For Telehealth Dispensing
“I see this script is for selegiline for Parkinson’s symptoms. Can you confirm all other medicines you take, especially antidepressants or strong pain medicines? Start at the lower dose and report dizziness, sleep problems or any new confusion. If you have chest pain, severe headache or rapid heartbeat, seek emergency care.”
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Gold Coast | Queensland | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |