Ranexa
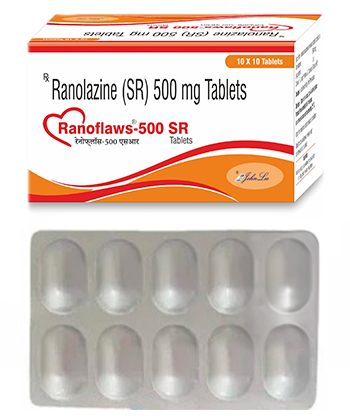
Ranexa
- Officially Ranexa (ranolazine) is prescription-only in Australia and most countries; however, some pharmacies may in practice supply ranexa without a prescription—this is not recommended and use should be under specialist supervision.
- Ranexa is used to treat chronic stable angina; ranolazine works mainly by inhibiting the late inward sodium current (late INa) in cardiac muscle, reducing intracellular sodium and calcium overload, lowering diastolic wall tension and myocardial oxygen consumption (it does not significantly lower heart rate or blood pressure but may prolong the QT interval).
- The usual adult dose for chronic stable angina is ranolazine 500 mg extended‑release twice daily, with possible titration to 1000 mg twice daily based on response and tolerability (do not exceed 2000 mg/day).
- Ranexa is supplied as an oral extended‑release tablet (ER tablets: commonly 375 mg, 500 mg, 750 mg and in some markets 1000 mg) taken by mouth twice daily.
- Onset of symptomatic improvement is not immediate — plasma levels peak around 2–6 hours after a dose, and patients often notice angina improvement over days to a couple of weeks rather than within minutes.
- The ER formulation has a duration of action supporting twice‑daily dosing (roughly ~12 hours of clinical effect per dose; total daily effect depends on the twice‑daily regimen).
- Avoid excessive alcohol while taking ranexa — alcohol may worsen dizziness or nausea, can interact with liver metabolism and increase the risk of adverse effects including QT prolongation.
- The most common side effect is constipation; other frequent adverse effects include nausea, headache and dizziness, with occasional palpitations or QT prolongation at higher exposures.
- Would you like to try “ranexa” without a prescription?

Latest Research Highlights
Basic Ranexa Information
- INN (International Nonproprietary Name): Ranolazine.
- Brand Names Available In Australia: Ranexa (500 mg, 1000 mg) distributed by iNova and Menarini.
- ATC Code: C01EB18.
- Forms & Dosages: Extended‑release (ER) oral tablets in strengths listed internationally as 375 mg, 500 mg, 750 mg and 1000 mg (1000 mg is more commonly available in Australia and North America).
- Manufacturers In Australia: iNova and Menarini are the named distributors for Ranexa in Australia.
- Registration Status In Australia: Prescription‑only medicine approved for chronic stable angina under specialist supervision (refer to the TGA for up‑to‑date records).
- OTC / Rx Classification: Prescription only (Rx).
Do patients still ask whether new studies change how ranolazine is used?
Randomised trials and meta‑analyses from 2022–2025 continue to support ranolazine as a second‑line antianginal for chronic stable angina when first‑line therapy leaves persistent symptoms.
Clinical data repeatedly show modest reductions in angina frequency and measurable improvement in exercise tolerance versus placebo when ranolazine is added to standard therapy such as β‑blockers or calcium‑channel blockers.
Safety signals are consistent across trials and real‑world series, with dose‑dependent QT prolongation as the principal cardiac concern.
Common adverse effects reported are gastrointestinal (constipation, nausea) and neurological (dizziness, headache), which are usually mild.
Australian pharmacovigilance via the TGA reports adverse events similar to international experience, and registries note adherence barriers linked to cost and polypharmacy in older patients.
Emerging mechanistic and early clinical work through 2022–25 explores ranolazine’s antiarrhythmic potential in atrial fibrillation prevention, but evidence remains exploratory and not for routine practice.
| Setting | Typical Sample Size | Key Endpoints | QT Findings |
|---|---|---|---|
| Randomised Controlled Trials | Hundreds to low thousands | Angina frequency, exercise tolerance, functional class | Small dose‑dependent increase in QT interval; monitored and rarely clinically significant |
| Meta‑analyses | Aggregated across multiple trials | Overall symptom reduction vs placebo, pooled safety | Reinforce QT signal but low incidence of torsades de pointes in trial populations |
| Real‑World Registries (Incl. Australia) | Variable; from hundreds to registries with larger cohorts | Adherence, adverse events reporting, effectiveness in comorbid patients | TGA data consistent with trials; monitoring challenges in elderly patients on polypharmacy |
Clinical Effectiveness In Australia
What should patients expect if a cardiologist prescribes ranexa in Australia?
TGA approvals for ranolazine ER tablets align with international indications for symptomatic chronic stable angina as add‑on therapy when other agents are insufficient.
Australian clinical practice mirrors trial outcomes: many patients experience fewer angina episodes and improved exertional capacity when ranolazine is added to conventional therapy.
Where ranolazine is PBS‑subsidised, cost barriers fall and adherence improves; where subsidy does not apply, cost sensitivity lowers uptake especially among pensioners and those on multiple medicines.
TGA adverse‑event reporting and specialist clinics in metropolitan centres report cautious use in older and multimorbid patients because of QT risks and potential interactions.
Typical Australian prescribing pathways see cardiologists initiate ranolazine with GPs and community pharmacists providing follow‑up and adherence support.
Telehealth has increased access for rural patients but ECG follow‑up remains necessary where QT risk exists, and limited ECG access can be a barrier.
| TGA Label | Observed Real‑World Effect |
|---|---|
| Symptomatic Chronic Stable Angina (Add‑On) | Reduced angina frequency and improved exercise tolerance in patients with persistent symptoms on standard agents |
| Specialist Supervision Suggested | Cardiologist initiation with GP and pharmacist follow‑up is common practice |
Indications And Expanded Uses
Who is ranolazine licensed for, and when do clinicians consider off‑label use?
- Approved Use: Symptomatic chronic stable angina in adults as add‑on therapy when conventional agents are insufficient.
- Paediatric Use: Not approved for children; safety and efficacy not established.
- Off‑Label / Investigational: Adjunctive therapy for refractory angina in specialist centres and investigational studies looking at atrial fibrillation prevention.
Clinicians generally reserve ranolazine for patients who cannot tolerate higher doses of nitrates, β‑blockers or calcium‑channel blockers or who have persistent symptoms despite these treatments.
Regulatory and product labelling guide cautious use in hepatic impairment, notable QT prolongation, or when patients are on strong CYP3A inhibitors.
Composition And Brand Landscape
What exactly is in a Ranexa tablet, and who supplies it in Australia?
The active ingredient is ranolazine (INN) formulated as modified/extended‑release (ER) oral tablets.
Globally the product is most commonly marketed as Ranexa, with regional strengths varying between 375 mg, 500 mg, 750 mg and 1000 mg.
In Australia Ranexa is available as 500 mg and 1000 mg ER tablets distributed by iNova and Menarini.
| Brand | Strengths | Manufacturer / Distributor | Typical Pack Size (Australia / EU / NA) |
|---|---|---|---|
| Ranexa | 500 mg, 1000 mg | iNova / Menarini | Box/blister (Australia); blister packs common in EU; bottle/blister in North America |
| Ranexa (EU) | 375 mg, 500 mg, 750 mg | Menarini, generics (Accord, Sandoz) | Blister packs (EU) |
| Corzyna / Ranexa (Canada) | 500 mg, 1000 mg | Bausch Health | Bottle or blister (Canada) |
Pharmacists should reference TGA labelling and current local stock information when counselling patients about Ranexa tablets and ranolazine ER formulations.
Contraindications And Special Precautions
Who should definitely not take ranolazine, and what precautions are essential?
- Absolute Contraindications: Known hypersensitivity to ranolazine or any component; severe hepatic impairment; concurrent use of strong CYP3A inhibitors (for example ketoconazole, clarithromycin); existing congenital or acquired QT prolongation.
- Relative Cautions: Moderate hepatic impairment (dose adjust/avoid), severe renal impairment (not recommended), patients over 75 years with polypharmacy, and patients with prior arrhythmias—ECG monitoring advised.
- Pregnancy/Breastfeeding: Insufficient data; generally avoided unless benefit clearly outweighs risk.
Practical everyday advice for patients includes avoiding grapefruit juice (CYP3A interaction), limiting alcohol if dizziness occurs, and not driving or using heavy machinery if faintness or profound dizziness develops.
Special focus for Aboriginal and Torres Strait Islander patients is needed because higher cardiometabolic comorbidity rates increase the need for careful review of interactions and renal/hepatic status.
| Decision Step | Action |
|---|---|
| Severe Hepatic Impairment | Contraindicated |
| On Strong CYP3A Inhibitor | Do not co‑prescribe |
| QT Prolongation On Baseline ECG | Avoid ranolazine; seek cardiology advice |
Dosage Guidelines
How is ranolazine started and adjusted in practice?
The standard adult regimen for chronic stable angina is ranolazine ER 500 mg twice daily to start.
If symptoms persist and the medicine is tolerated, the dose may be increased to 1000 mg twice daily, not exceeding 2000 mg per day.
Severe hepatic impairment is a contraindication; dose reduction or avoidance applies in moderate hepatic disease.
Mild to moderate renal impairment requires caution; severe renal impairment is not recommended.
| Situation | Dosing Guidance |
|---|---|
| Starting Dose (Adults) | 500 mg twice daily |
| Titration | Increase to 1000 mg twice daily if needed and tolerated |
| Max Dose | 2000 mg/day |
| Missed Dose | Take next scheduled dose; do not double up |
In Australia, cardiologists often request a baseline ECG and periodic QT monitoring, particularly after dose escalation or when adding interacting drugs.
Interactions Overview
Which medicines and foods should patients and pharmacists watch for?
Ranolazine is metabolised primarily by CYP3A, so strong CYP3A inhibitors such as ketoconazole and clarithromycin are contraindicated.
Moderate or weak CYP3A inhibitors require caution and may necessitate dose reduction or closer monitoring.
CYP3A inducers can reduce ranolazine exposure and potentially decrease efficacy.
Because ranolazine can prolong the QT interval, additive QT‑prolonging agents (certain antiarrhythmics, some antipsychotics, macrolide antibiotics) increase arrhythmia risk.
Grapefruit and grapefruit juice should be avoided due to CYP3A interactions.
| Interaction Category | Examples / Advice |
|---|---|
| Contraindicated | Strong CYP3A inhibitors (e.g., ketoconazole, clarithromycin) |
| Avoid / Use With Caution | Concurrent QT‑prolonging drugs; grapefruit juice; strong CYP3A inducers |
| Monitor | Moderate CYP3A inhibitors; SSRIs/macrolides commonly co‑prescribed in primary care |
Pharmacists should use real‑time interaction databases when dispensing and counsel patients about foods and drinks that alter ranolazine levels.
Cultural Perceptions And Patient Habits
How do Australian patients view ranolazine and what practical barriers do they face?
Price sensitivity is common, with many patients asking about PBS subsidy, generics and cheaper alternatives when Ranexa is recommended.
Community trust in pharmacists for practical counselling is strong, and patients rely on pharmacies for price comparisons and advice on substitution.
Telehealth prescriptions have increased access for rural patients, yet access to ECG monitoring can be a practical barrier for safe follow‑up.
Patient forums and social media commonly report relief from persistent angina but also concerns about dizziness and medication cost.
In Aboriginal and Torres Strait Islander communities, culturally safe care, medication reconciliation and outreach ECG access are particularly important because of higher cardiometabolic disease burdens.
Case vignette — Urban Patient: A 68‑year‑old pensioner in Melbourne started ranolazine after persistent angina despite a β‑blocker, noticed fewer chest pain episodes but mentioned mild constipation; community pharmacy arranged a follow‑up call and TGA‑adverse event reporting information.
Case vignette — Rural Patient: A 72‑year‑old in rural Queensland used telehealth to obtain a prescription; delayed ECG access meant the cardiologist arranged a local clinic ECG before dose escalation.
Availability And Pricing Patterns
Where can Australians buy Ranexa and how much might it cost out of pocket?
Ranexa 500 mg and 1000 mg are distributed in Australia by iNova and Menarini, and major retail chains can usually stock or order the product.
Retail outlets such as Chemist Warehouse, Priceline and TerryWhite Chemmart commonly supply Ranexa or can arrange order‑in stock.
PBS listing for ranolazine varies over time; clinicians and pharmacists should check the current PBS Schedule to determine subsidy status and patient co‑payments.
Where unsubsidised, patients frequently compare prices across bricks‑and‑mortar and online pharmacies to manage costs.
Note on online purchasing: in this pharmacy Ranexa is available without a prescription, with discreet delivery to Australia in 5‑14 days.
| Pharmacy Type | Likely Price Range | PBS Status Check |
|---|---|---|
| Major Chains (In‑Store) | Moderate to higher if unsubsidised | Check PBS Schedule at point of sale |
| Independent Pharmacies | Variable; may negotiate or special‑order | Check PBS Schedule |
| Online Pharmacies | Competitive pricing; watch shipping times | Check PBS Schedule and ECG follow‑up arrangements |
Supply interruptions for certain strengths have occurred internationally; Australian wholesalers may vary stock, so pharmacists should confirm availability when prescribing or dispensing.
Comparable Medicines And Preferences
When is ranolazine chosen over other antianginals?
First‑line options for chronic angina in Australia include nitrates (isosorbide mononitrate/dinitrate), β‑blockers (metoprolol, bisoprolol) and calcium‑channel blockers (amlodipine, diltiazem, verapamil).
Ranolazine differs by having little to no effect on heart rate or blood pressure, which is useful when bradycardia or hypotension are concerns.
It is commonly used as an additive therapy when symptoms persist on conventional agents, or when patients cannot tolerate dose increases of other drugs.
| Medicine Class | Efficacy | HR/BP Effect | Monitoring / Interaction Notes |
|---|---|---|---|
| β‑Blockers | Good post‑MI benefit | Reduce heart rate | Well established; monitor bradycardia |
| Calcium‑Channel Blockers | Effective in vasospastic angina | May lower BP | Monitor for oedema and hypotension |
| Ranolazine | Modest additive antianginal effect | Minimal impact on HR/BP | QT and CYP3A interactions; ECG monitoring advised |
Frequently Asked Questions
- Is Ranexa on the PBS and cheap? Check the current PBS Schedule; listing and subsidy status vary by strength and indication.
- Will ranolazine slow my heart rate? Ranolazine generally does not significantly change heart rate or blood pressure.
- Do I need ECG monitoring? A baseline ECG is recommended to assess the QT interval and monitoring after dose escalation or when adding interacting drugs is advised.
- What if I miss a dose or feel faint? Take the next scheduled dose and do not double up; if fainting or severe dizziness occurs, seek immediate medical care.
- What are common side effects? Constipation, nausea, headache and dizziness are common and usually mild; palpitations and QT prolongation are less common but monitored.
Guidelines For Proper Use
What should pharmacists tell patients starting ranolazine?
- Confirm the TGA‑label indication: chronic stable angina as add‑on therapy.
- Review the full medication list for CYP3A inhibitors/inducers and QT‑prolonging agents.
- Advise baseline ECG and periodic QT monitoring, especially after dose changes.
- Counsel on missed doses: skip doubling doses and take the next scheduled dose.
- Storage: keep at 20–25°C in a dry place and protect from moisture and heat.
- Avoid grapefruit juice and limit alcohol if dizziness occurs.
- Report suspected adverse reactions to the TGA and escalate syncope, palpitations or severe dizziness immediately.
For Indigenous and rural patients provide culturally safe adherence strategies and coordinate ECG access or outreach cardiology where needed.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Alice Springs | Northern Territory | 5-9 days |