
Revia
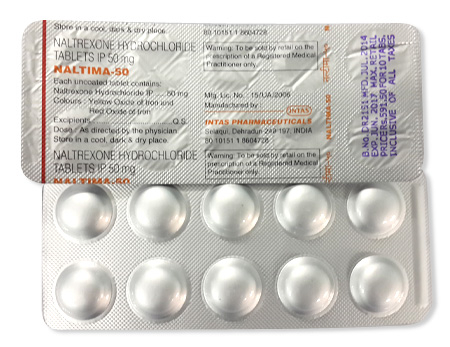
Revia
- In many pharmacies you can buy Revia (naltrexone) — legally it is a prescription‑only medicine in Australia and most countries, but some pharmacies or online suppliers may supply it without a prescription or receipt; this is not recommended and you should consult a healthcare professional before use.
- Revia is used for relapse prevention in opioid use disorder and to reduce craving in alcohol dependence; it is an opioid receptor antagonist (primarily a competitive mu‑opioid receptor antagonist) that blocks the effects of opioids and reduces the rewarding effects of alcohol.
- The usual adult dose is 50 mg orally once daily for tablets; the extended‑release injectable formulation is 380 mg intramuscularly every 4 weeks; treatment durations vary (minimum 3–6 months for alcohol dependence, often longer for opioid relapse prevention) and initiation requires the patient to be opioid‑free for 7–10 days to avoid precipitated withdrawal.
- Forms of administration: oral film‑coated, scored 50 mg tablets (tablets in blister packs or bottles) and a prolonged‑release 380 mg vial for intramuscular injection (single‑use, powder for reconstitution).
- Onset time: oral tablets start to block opioid effects within about 30–60 minutes (clinical effects on alcohol craving may take days); the injectable depot achieves therapeutic plasma levels within hours with full effect developing over 1–3 days.
- Duration of action: a single oral dose has an effect lasting roughly 24 hours (hence once‑daily dosing); the extended‑release intramuscular injection provides approximately four weeks of opioid blockade.
- Alcohol warning: although naltrexone is used to treat alcohol dependence, it can cause or worsen liver injury; avoid excessive alcohol consumption, have liver function monitored regularly and discuss alcohol use with your prescriber before and during treatment.
- The most common side effects are nausea and headache; other frequent effects include insomnia, joint or muscle pain, anxiety, tiredness and loss of appetite—most adverse effects are dose‑related and often settle with continued therapy.
- Would you like to try revia without a prescription?
Basic Revia Information
- INN (International Nonproprietary Name): Naltrexone hydrochloride
- Brand Names Available In Australia: Revia (50 mg tablets) — brand discontinued in many regions, generics available; Vivitrol (380 mg IM) — available; Depade — discontinued; Naltrexona (generic) — generic presentations exist. Exact Australian sponsor listings not specified.
- ATC Code: N07BB04
- Forms & Dosages: Tablet 50 mg oral (film-coated, scored; blisters or bottles); Prolonged‑release injection 380 mg/vial IM (powder for reconstitution, single‑use vial).
- Manufacturers In Australia: Not specified. Global suppliers include Alkermes (Vivitrol), Teva, Sandoz, Accord and various regional generic manufacturers; check TGA sponsor registration for local supply.
- Registration Status In Australia: Not specified. International approval includes FDA (USA) and EMA (EU); local TGA registration/sponsor should be verified.
- OTC / Rx Classification: Prescription Only (Rx).
Latest Research Highlights
Worried whether the latest studies back up naltrexone use for alcohol or opioid problems?
Randomised controlled trials from 2022–2025 continue to show that oral naltrexone reduces heavy‑drinking days and craving compared with placebo in people with alcohol use disorder.
Extended‑release injectable naltrexone (Vivitrol, 380 mg IM) shows improved adherence in selected opioid‑use cohorts but mixed long‑term abstinence results, often limited by retention in care.
Observational pharmacovigilance and TGA/DAEN‑style reports reinforce low‑frequency hepatotoxicity signals at high cumulative exposures, prompting routine liver monitoring.
Recent meta‑analyses confirm most adverse events are mild and dose‑related, with nausea and headache the commonest complaints.
Real‑world Australian clinic audits highlight that adherence and integration with psychosocial care are the key determinants of outcome.
Urban patients tend to access clinic‑based MAT more easily, while rural patients report stigma and access barriers; culturally safe care models and telehealth help close that gap.
| Study Type | Population | Key Outcome |
|---|---|---|
| Randomised Controlled Trials (2022–2025) | Alcohol use disorder | Reduced heavy‑drinking days and craving vs placebo |
| RCTs / Cohort Studies (Injectable) | Opioid‑use cohorts (selected, opioid‑free at initiation) | Improved adherence; mixed long‑term abstinence due to retention issues |
| Observational / Pharmacovigilance | Real‑world users | Low‑frequency hepatotoxicity signals at high exposures; most AEs mild |
- Safety Signals: Hepatotoxicity reported rarely with high cumulative exposure; baseline and periodic LFTs recommended.
- Dosing Highlight: Tablet 50 mg oral once daily; prolonged‑release injection 380 mg IM monthly.
- Research Terms To Note: naltrexone research 2023; Vivitrol adherence; hepatotoxicity naltrexone.
Clinical Effectiveness In Australia
Want to know how naltrexone performs in Australian clinics compared with trials?
State‑based MAT services and clinic audits from 2020–2025 align with international findings that naltrexone reduces relapse risk in alcohol dependence when used with psychosocial support.
For opioid dependence, naltrexone supports relapse prevention when patients are opioid‑free at initiation.
TGA product information and post‑market monitoring support prescription use alongside counselling and psychosocial therapies.
Real‑world effectiveness is often limited by adherence to daily oral dosing, and injectable 380 mg IM addresses this but needs clinic infrastructure for administration.
| Formulation | Typical Clinical Outcome | Practical Consideration |
|---|---|---|
| Oral Naltrexone 50 mg | Reduces relapse risk; effectiveness depends on adherence | Daily dosing can limit real‑world benefit; common choice for privacy |
| Extended‑Release IM 380 mg | Improves adherence in selected cohorts; retention affects long‑term outcomes | Requires clinic visits and cold‑chain handling |
Monitor liver function tests as standard clinical practice in Australia.
Funding and PBS subsidy status, and out‑of‑pocket co‑payments, shape treatment uptake and adherence.
Pharmacies including Chemist Warehouse and TerryWhite Chemmart commonly collaborate with clinics to supply oral tablets and support follow‑up.
Indications And Expanded Uses
Wondering what naltrexone is approved for, and whether other uses are supported?
Approved primary indications include alcohol dependence and relapse prevention in opioid dependence when opioid‑free at initiation.
Off‑label uses trialled in Australian practice include binge‑eating disorder, some impulse‑control disorders and adjunctive pain management, but evidence is mixed and guideline endorsement is limited.
Recent Australian pilot studies (2022–2024) are exploratory signal‑generation only and do not support routine off‑label use without further RCT evidence.
- Approved Uses: Alcohol dependence — oral 50 mg daily; Opioid relapse prevention — oral 50 mg daily or 380 mg IM monthly.
- Off‑Label/Investigational: Binge‑eating disorder, impulse control disorders, adjunctive pain therapy — evidence scorecard: low/insufficient.
Clinicians should discuss evidence uncertainty, obtain informed consent for off‑label prescribing, and document shared decision‑making.
Patients may prefer oral 50 mg tablets for privacy, or monthly injections to avoid daily reminders and improve adherence.
PBS listing may not cover off‑label uses, which affects affordability and uptake.
Composition And Brand Landscape
Curious which brands and formulations you might see in pharmacy shelves or clinic fridges?
| Brand Name | Form | Status |
|---|---|---|
| Revia | 50 mg tablets | Brand discontinued in many regions; generics available |
| Depade | 50 mg tablets | Discontinued |
| Vivitrol | 380 mg IM injection | Available |
| Naltrexona (generic) | 50 mg tablets | Generic (various markets) |
INN: Naltrexone hydrochloride.
Storage and transport: tablets at 20–25°C; injections refrigerated and used after reconstitution within label timeframes.
Generics from Teva, Sandoz and Accord are common internationally; local Australian suppliers and sponsors should be verified via the TGA.
Australian patients frequently ask about cost and PBS‑listed brands; pharmacists at Chemist Warehouse, Priceline and TerryWhite Chemmart often advise on generics and savings.
Contraindications And Special Precautions
Worried about the risk of sudden withdrawal or liver problems?
Absolute contraindications include current opioid use or recent opioid withdrawal, acute hepatitis or severe hepatic impairment, and known hypersensitivity to naltrexone or excipients.
Relative precautions include moderate hepatic or renal impairment and a history of depression or suicidal ideation; close monitoring is required.
- Absolute Contraindications: Current opioid use or recent opioid withdrawal; acute hepatitis; severe hepatic impairment; known hypersensitivity.
- Relative Precautions: Moderate hepatic/renal impairment; history of depression/suicidality; pregnancy risks must be considered per region.
Data highlights recommend baseline liver function tests and periodic LFT monitoring during therapy due to hepatotoxicity signals in pharmacovigilance reports.
Advise patients that opioid analgesia will be blocked while on naltrexone and arrange emergency analgesia strategies before elective surgery.
Pharmacist screening in community pharmacies is helpful to identify contraindications and ensure safe supply.
Dosage Guidelines
How is naltrexone started and what should patients expect about dosing?
| Indication | Route | Dose | Notes |
|---|---|---|---|
| Alcohol Dependence | Oral | 50 mg once daily | Minimum 3–6 months; with psychosocial support |
| Opioid Relapse Prevention | Oral | 50 mg once daily | Initiate when opioid‑free 7–10 days; duration individualised |
| Opioid Relapse Prevention | IM Extended‑Release | 380 mg every 4 weeks | Clinic administration; refrigerate prior to use |
- Initiation Criteria: Patient must be opioid‑free for 7–10 days before starting to avoid precipitated withdrawal.
- Missed Dose: Take as soon as remembered unless close to next dose; do not double up.
- Elderly/Impairment: Use with caution; monitor LFTs in hepatic impairment.
Discuss adherence plans such as daily alarms for tablets versus monthly injections for those with adherence challenges.
Consider PBS implications for long‑term therapy and use telehealth or local clinics for injections in rural areas.
Interactions Overview
Wondering which medicines clash with naltrexone?
The primary interaction is pharmacodynamic antagonism with opioids which risks precipitated withdrawal and blocks opioid analgesia.
Concomitant use with other hepatotoxic drugs or heavy alcohol intake increases hepatotoxic risk and needs closer LFT monitoring.
Naltrexone is not a major CYP inducer or inhibitor, so classic pharmacokinetic interactions are fewer, but clinical caution remains prudent.
| Interaction | Clinical Effect | Action |
|---|---|---|
| Opioids | Precipitated withdrawal; blockade of analgesia | Do not co‑prescribe; ensure opioid abstinence 7–10 days before initiation |
| Hepatotoxic Agents / Alcohol | Increased hepatotoxic risk | Monitor LFTs; avoid in acute hepatitis |
| Other Medications | Few CYP interactions known | Review analgesia plans; counsel on OTC products |
Advise patients to carry a treatment card stating they are on naltrexone for analgesia planning during surgery or injury.
Pharmacies should document interactions in dispensing software and counsel patients receiving telehealth prescriptions.
Cultural Perceptions And Patient Habits
Are people comfortable starting naltrexone, and what influences their choices?
Stigma around addiction treatment persists in Australia, and many patients prefer framing naltrexone as relapse prevention rather than “replacement therapy.”
Rural patients often cite confidentiality concerns and limited clinic access, while urban patients access specialist services more readily.
Price sensitivity and PBS reliance strongly influence acceptance and ongoing adherence.
- Stigma & Privacy: Monthly injections can help people avoid daily reminders and protect privacy.
- Rural Access: Telehealth, local pharmacy collaboration and chilled transport for injections are crucial for remote patients.
- Cultural Safety: Culturally safe models and partnerships with Aboriginal Community Controlled Health Services improve acceptance for Indigenous Australians.
Pharmacists are trusted sources of information and can provide discreet counselling and advice on PBS options and generics.
Availability And Pricing Patterns
How easy is it to obtain naltrexone in Australia, and what will it cost?
Oral naltrexone 50 mg tablets are widely available as generics internationally, while Revia is discontinued in many regions and Vivitrol remains available as the branded extended‑release injectable.
In Australia availability depends on TGA registration, sponsor supply and local pharmacy stock; clinicians should verify current PBS schedules and sponsors.
| Source | What To Expect | Price/Notes |
|---|---|---|
| PBS | Listing varies by formulation and indication | Check current PBS schedules; coverage not guaranteed for all uses |
| Private Script | Available via prescription | Out‑of‑pocket cost varies by brand and supplier (not specified) |
| Clinic‑Funded Program | Injectable programs may fund Vivitrol for selected patients | Costs may be reduced or covered via clinic funding |
Cold‑chain requirements for Vivitrol mean injections are usually clinic‑based or dispensed from refrigerated pharmacies for same‑day administration.
In our online pharmacy, revia is available without a prescription, with discreet delivery to Australia in 5‑14 days.
Always confirm the brand is TGA‑registered and the sponsor is legitimate when ordering online or via telepharmacy.
Comparable Medicines And Preferences
How does naltrexone compare with other medicines used for alcohol or opioid dependence?
| Drug | Pros | Cons | Suitability |
|---|---|---|---|
| Disulfiram | Deterrent effect when alcohol consumed | Requires abstinence and commitment; adverse reactions with alcohol | Suitable for motivated patients seeking aversive therapy |
| Acamprosate | Supports long‑term abstinence, well tolerated | Requires multiple daily dosing; renal considerations | Good for maintenance when not suitable for naltrexone |
| Methadone | Effective for opioid dependence with supervised dosing | Opioid agonist; daily clinic visits often required | Suitable when opioid substitution is the goal |
| Buprenorphine/Suboxone | Partial agonist with safety advantages | Needs induction and monitoring; some diversion risk | Common MAT option for opioid dependence |
| Nalmefene | Opioid receptor antagonist for alcohol dependence | Different licensing and accessibility; may not suit all patients | Alternative to naltrexone in selected patients |
Choice depends on patient preference, clinical comorbidities such as liver disease, PBS coverage and access to clinics.
Long‑acting injectables may be preferred for rural and Indigenous patients where adherence and clinic access are the main barriers.
Frequently Asked Questions
Can I take naltrexone while on opioid painkillers?
No. Naltrexone is an absolute contraindication with current opioid use and can precipitate acute withdrawal.
Is naltrexone on the PBS?
PBS coverage varies by formulation and indication; clinicians and pharmacists should check the current PBS schedule for up‑to‑date listings.
What are common side effects?
Common side effects include nausea, headache, insomnia, joint or muscle pain, anxiety and tiredness; most are dose‑dependent and often subside.
What should I do about liver monitoring?
Baseline LFTs and periodic monitoring are recommended because hepatotoxicity has been reported, especially at high cumulative exposures.
How should I store it?
Store tablets at 20–25°C and protect from moisture and excess heat; store injections refrigerated per product label and use reconstituted vial within the recommended timeframe.
- When To Seek Help: Severe abdominal pain, jaundice, signs of liver dysfunction, or suicidal ideation — seek urgent medical care.
- Practical Tip: Carry a treatment card stating you are on naltrexone for analgesia planning and emergency care.
Guidelines For Proper Use
How should pharmacists and clinicians manage safe initiation and follow‑up?
Key checklist items include screening for current opioid use, baseline LFTs, informed consent, integrated psychosocial support and ongoing monitoring.
- Ensure opioid abstinence for 7–10 days before initiation to avoid precipitated withdrawal.
- Prescribe oral 50 mg once daily for alcohol or opioid relapse prevention, or 380 mg IM every 4 weeks for extended‑release injection where appropriate.
- Baseline LFTs and periodic checks during therapy; avoid in acute hepatitis.
- Use motivational interviewing and culturally appropriate materials for Indigenous clients.
- Arrange telehealth follow‑up for rural patients and liaise with local pharmacies for supply and refrigerated transport for injections.
Pharmacist counselling checklist for dispensing includes screening questions about opioid use, current LFTs, mental health history, planned surgeries and analgesia needs.
Missed doses should be taken when remembered unless close to next dose; do not double up.
Document PBS or private prescribing, obtain injection consent forms where required, and provide an emergency analgesia plan for patients on naltrexone.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–7 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Cairns | Queensland | 5–9 days |