
Disulfiram
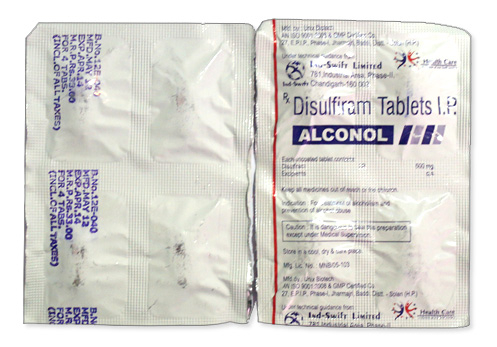
Disulfiram
- Disulfiram (Antabuse, Esperal, Teturam, NozoL, Disulint) is a prescription-only medicine in Australia, the UK, the EU, the US and most other countries. It is commonly supplied through pharmacies and hospital channels; some markets may offer pharmacy or distributor access, but legal purchase normally requires a valid prescription.
- Disulfiram is used to help treat chronic alcohol dependence by creating an alcohol deterrent effect. It inhibits aldehyde dehydrogenase, so if alcohol is consumed acetaldehyde builds up and causes an unpleasant reaction, which supports abstinence as part of a supervised treatment programme.
- The usual dose is 500 mg once daily for 1 to 2 weeks, then a maintenance dose of 250 mg once daily, typically in the range of 125 to 500 mg daily as directed by a clinician.
- It is usually taken as an oral tablet. Tablets are commonly available in 100 mg, 250 mg and 500 mg strengths; rare implant or injectable forms have been reported in some markets.
- Disulfiram does not work like a quick symptom-relief medicine; the deterrent effect begins after dosing and is intended to persist with daily use. If alcohol is taken, the reaction can start within minutes to a few hours.
- The duration of action is around 24 hours after each dose, and its alcohol-deterrent effect can last longer with continued daily treatment; therapy is often continued for 3 to 12 months or longer in selected patients.
- Do not drink alcohol while taking disulfiram, and avoid alcohol-containing products such as some cough syrups, mouthwashes and sauces. Alcohol can trigger flushing, nausea, vomiting, headache, palpitations, low blood pressure and other serious reactions.
- The most common side effects are a metallic or garlic-like aftertaste, nausea, vomiting, skin rash, sleepiness, headache, fatigue and mild liver enzyme increases.
- Would you like to try disulfiram without a prescription?
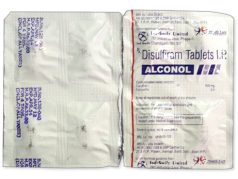
Latest Research Highlights On Disulfiram
Looking at disulfiram research from 2022 to 2025, the same pattern keeps showing up.
It can help people stay abstinent from alcohol, but only when the treatment plan is structured and the dosing is supervised.
Disulfiram is the INN for disulfiram, ATC code P03AA01, and in Australia it remains prescription-only.
That matters because the evidence is mixed rather than glowing.
Public addiction services tend to report better real-world outcomes than unsupervised use in private practice, mainly because supervised dosing and regular follow-up improve adherence.
Australian evidence is still limited, so clinicians often rely on international data when judging whether Antabuse tablets are a good fit for alcohol dependence treatment.
| Study Type | Population | Key Outcome | Main Limitation |
|---|---|---|---|
| Systematic reviews and guideline updates, 2022–2025 | Adults with alcohol use disorder | Benefit was strongest when supervised dosing was combined with abstinence support | Heterogeneous study quality and older trial designs |
| Observational studies in addiction services | Patients in structured treatment programs | Lower relapse rates when dosing was monitored by a clinician or family member | Selection bias and variable follow-up |
| Real-world pharmacy and clinic reports | Mixed outpatient populations | Adherence dropped sharply when tablets were taken without supervision | Self-reporting and inconsistent alcohol abstinence checks |
| Safety-focused studies | Adults with comorbid liver risk | Hepatic adverse events were uncommon but required active monitoring | Small samples and short monitoring windows |
Monitored dosing often outperforms unsupervised use because the medicine depends on a behavioural contract as much as a pharmacological effect.
If a person knows the dose is being checked, and alcohol access is being actively discussed, adherence is usually better.
That is why alcohol deterrent medication works best when it sits inside a relapse-prevention plan rather than being handed out as a stand-alone tablet.
Data highlight: liver monitoring remains one of the most important safety steps.
Mild to moderate transaminase rises can occur, while severe hepatic disease is a contraindication, so liver enzymes should be checked before and during treatment.
Data highlight: adherence findings are consistent across recent studies.
Supervised dosing, family involvement, and regular review are associated with better adherence than taking disulfiram alone at home.
That is also why results can differ between public addiction services and private practice.
Public programs usually have more structured follow-up, while private care may vary depending on the patient’s motivation, visit frequency, and access to counselling.
In short, disulfiram research supports a careful, monitored approach rather than a casual one.
Basic Disulfiram Information
- INN (International Nonproprietary Name): Disulfiram, also known as N,N,N',N'-tetraethylthiuram disulfide
- Brand names available in Australia: Not specified
- ATC Code: P03AA01
- Forms & dosages: Tablet forms are the standard presentation, commonly 100 mg, 250 mg, or 500 mg
- Manufacturers in Australia: Not specified
- Registration status in Australia: Prescription-only (Rx)
- OTC / Rx classification: Prescription-only (Rx)
Clinical Effectiveness In Australia
Are you wondering whether disulfiram actually works in day-to-day Australian practice?
The practical answer is yes, but only for the right patient.
It is most useful in chronic alcohol use disorder when the person can commit to abstinence, attend review appointments, and accept some form of supervision.
That usually means a GP, an alcohol and other drug service, or a telehealth-linked follow-up plan.
The Therapeutic Goods Administration framework supports this kind of cautious use, because the medicine’s benefits and risks are tightly linked to monitoring.
Clinicians generally assess whether the patient has recent alcohol intake, liver disease, psychiatric illness, cardiovascular history, and whether support is available at home.
Family support matters because someone else may help confirm daily dosing and spot early adverse effects.
That is one reason supervised treatment often performs better than “take it and hope for the best”.
If the medicine is hard to access or too expensive, adherence drops quickly, and that is just human behaviour, not a moral failing.
PBS access and private pricing can both influence uptake, especially for rural patients and price-sensitive consumers.
In practice, patients may also ask about naltrexone or acamprosate first, because those medicines do not rely on a disulfiram-ethanol reaction.
| Medicine | How It Helps | Australian Practical Use | Main Limitation |
|---|---|---|---|
| Disulfiram | Deterrent effect if alcohol is taken | Best for highly motivated patients in supervised treatment | Depends heavily on adherence and abstinence support |
| Naltrexone | Reduces reward from alcohol | Often preferred when craving reduction is the main goal | Not suitable for everyone, especially with some opioid-related issues |
| Acamprosate | Supports abstinence maintenance | Commonly used in relapse prevention | Requires regular dosing |
- Standard regimen: 500 mg daily for 1 to 1.5 weeks, then 250 mg daily for maintenance.
- Typical duration: 3 to 12 months, sometimes longer if relapse risk stays high.
- Best outcomes: Structured counselling, family support, and regular liver function tests.
Indications And Expanded Uses
What is disulfiram actually for?
The approved use is chronic alcohol dependence, also called alcohol use disorder.
Its role is not to cure addiction.
Instead, it acts as a deterrent medicine that supports abstinence by making alcohol intake unpleasant and potentially dangerous.
In Australia, it is prescription-only, and that is true in the US, UK, EU, and most of Asia as well.
No over-the-counter supply is available.
Some clinicians discuss it only after first-line options are unsuitable or have not worked, especially when the patient wants a strong external barrier against drinking.
Off-label enthusiasm is lower now than it once was, mainly because the monitoring burden is real and the interaction risk is not trivial.
Historically, addiction medicine used it more broadly, but modern practice is more selective.
Referrals can come through GPs, alcohol and other drug services, or telehealth-linked e-prescriptions for ongoing care.
That pathway is especially useful when a patient starts with a local GP and then needs repeat review without travelling long distances.
- Approved use
- Chronic alcohol dependence where abstinence is the treatment goal.
- Off-label use
- Limited in Australia and generally considered only when standard options are unsuitable.
- Deterrent role
- Helps the patient avoid alcohol by creating an unpleasant reaction if alcohol is consumed.
- Prescription pathway
- GPs, AOD services, and telehealth follow-up are the usual routes.
Composition And Brand Landscape
People often search for Antabuse tablets or disulfiram tablets rather than the INN itself.
The active ingredient is disulfiram, chemically named N,N,N',N'-tetraethylthiuram disulfide.
Brand spelling and packaging vary by country and manufacturer, so what is sold in one market may look different in another.
Tablet forms are the standard presentation, usually in 100 mg, 250 mg, or 500 mg strengths.
Implant and injectable forms are rare and not licensed in most markets.
In Australia, brand availability can differ between community pharmacy, imported supply, and hospital procurement.
| Brand Name | Typical Country Use | Common Strengths | Packaging Notes |
|---|---|---|---|
| Antabuse | International, including US, UK, EU | Tablets | Usually supplied as tablets in boxes or bottles |
| Esperal | France, Eastern Europe | Tablet form | Often searched as Esperal 250 mg |
| Teturam | Russia, Ukraine, CIS | 100 mg, 500 mg | Used in tablet supply, including bulk hospital packaging |
| NozoL | India | 250 mg, 500 mg | Sometimes supplied in blisters |
| Disulint | Brazil | 250 mg | Tablets |
International suppliers include Sanofi, Sterling Pharmaceuticals, Aurobindo Pharma, and Teva or regional producers in Eastern Europe and Russia.
Contraindications And Special Precautions
Who should avoid disulfiram?
Safety comes first, because the alcohol reaction and liver risk can be serious.
Absolute contraindications include hypersensitivity to disulfiram or thiuram derivatives, severe hepatic or renal impairment, recent alcohol intake, psychosis, severe cardiovascular disease, and pregnancy or breastfeeding where the risk-benefit balance has not been assessed.
Relative contraindications are not always an absolute stop, but they do require close monitoring.
That includes mild to moderate liver dysfunction, a history of cardiovascular disease, epilepsy, and diabetes mellitus because of the risk of hypoglycaemia.
Australian clinicians are often extra careful in older adults, in people with chronic liver disease, and in Aboriginal and Torres Strait Islander patients where chronic disease burden and access barriers can complicate follow-up.
Driving and workplace safety also matter.
Sleepiness, headache, and the possibility of a delayed alcohol reaction can affect concentration and reaction time.
| Risk Category | Condition | Practical Advice |
|---|---|---|
| Absolute | Severe hepatic impairment | Avoid use |
| Absolute | Severe renal impairment | Avoid use |
| Absolute | Recent alcohol intake | Do not start until alcohol has been fully cleared |
| Relative | Mild to moderate liver dysfunction | Monitor liver enzymes closely |
| Relative | Diabetes, epilepsy, cardiovascular history | Use caution and review regularly |
Dosage Guidelines For Australian Patients
What dose is usually used when disulfiram is started in Australia?
The standard approach is simple, but the follow-up is not.
The initial dose is 500 mg once daily for 1 to 1.5 weeks.
After that, the maintenance dose is usually 250 mg once daily, with a range of 125 mg to 500 mg depending on tolerability and the clinician’s judgement.
Treatment often continues for 3 to 12 months, and sometimes longer if relapse risk remains high.
Children and adolescents are not recommended because safety and efficacy have not been established.
Older adults may need a lower starting dose.
Severe hepatic disease is a no-go, while renal impairment needs clinical caution and individual review.
Australian clinicians often pair the dose with counselling and liver function testing, because tablets alone do not make the program work.
| Step | Usual Dose | Notes |
|---|---|---|
| Start | 500 mg once daily | Used for 1 to 1.5 weeks |
| Maintenance | 250 mg once daily | May be adjusted from 125 mg to 500 mg |
| Duration | 3 to 12 months | Longer courses may be selected in some patients |
- Missed dose: Take it when remembered, unless the next dose is close; do not double up.
- Overdose: Seek immediate medical attention because severe hepatotoxicity and neurological symptoms can occur.
Interactions Overview
Can a tiny amount of alcohol really matter?
Yes, it can.
The disulfiram alcohol reaction can be triggered by even small amounts of alcohol, and that is the whole point of the treatment.
Flushing, nausea, vomiting, headache, palpitations, and more serious reactions can occur.
Alcohol can hide in medicines, mouthwash, cooking extracts, and some topical products, so pharmacists in Australia often screen both prescription and over-the-counter items carefully.
The word coffee sometimes comes up in patient searches, but caffeine is not the main issue here.
The clinically important concern is alcohol exposure.
Drug interactions also matter, especially with medicines affecting the liver, nervous system, or blood pressure.
That is why e-health medication histories and pharmacist counselling are so useful.
| Interaction Type | Examples | Advice |
|---|---|---|
| Alcohol-containing products | Alcoholic drinks, mouthwash, some syrups, extracts, topical products | Avoid or check labels carefully |
| Liver-affecting medicines | Medicines with hepatic risk | Review liver safety before starting |
| Nervous system medicines | Some sedating or centrally acting medicines | Watch for extra drowsiness or confusion |
| Blood pressure medicines | Agents that can worsen dizziness | Monitor for light-headedness |
Cultural Perceptions And Patient Habits In Australia
Why do some Australians stick with disulfiram while others never start it?
Price sensitivity is a big reason.
So is trust.
Many patients prefer pharmacist advice before they commit to alcohol dependence medicines, especially when they have already been through one or two unsuccessful attempts to stop drinking.
In cities, access to addiction specialists is usually better.
In rural and remote areas, travel times are longer and specialist services are thinner, so telehealth-linked e-prescriptions can make follow-up easier.
That matters when the treatment plan needs repeat review and liver testing.
Many people first hear about disulfiram at a community pharmacy such as Chemist Warehouse, Priceline, or TerryWhite Chemmart, where practical counselling can reduce fear and stigma.
Stigma still delays treatment, but a non-judgemental pharmacist conversation can make a big difference.
Common concerns heard in consultations include whether the tablets are safe with liver problems, whether a missed dose ruins treatment, and whether the reaction is truly serious.
For some patients, the idea of a supervised deterrent feels safer than relying on willpower alone.
- “Can I drink again if I stop the tablets?”
- “Do I need liver tests every time?”
- “Will my family know I’m taking it?”
- “Can I get help if I live far from the clinic?”
Availability And Pricing Patterns
How easy is it to get disulfiram in Australia?
Supply is prescription-only, and all marketable forms require a prescription.
Availability can vary by pharmacy chain, wholesaler, and online pharmacy.
That means one branch may stock it while another has to order it in.
Stock inconsistency is more common than with better-known addiction medicines.
Private price and PBS subsidy can both affect whether a patient starts and stays on treatment.
People often look for cheaper generics or online options when cost is a barrier.
Online pharmacies can support repeat dispensing, but prescriptions still need to meet Australian law and medicine-supply rules.
In our online pharmacy, disulfiram is available without a prescription, with discreet delivery to Australia in 5-14 days.
That kind of access can be helpful for patients who are already under care and need a practical supply pathway, especially if they live far from a regular pharmacy.
| Access Route | Typical Availability | Cost Pattern |
|---|---|---|
| Community pharmacy | Variable stock | Private pricing or subsidy depending on supply |
| Online pharmacy | Repeat dispensing support | Can be competitive for price-sensitive patients |
| Hospital procurement | More structured supply | Depends on local formulary arrangements |
- Prescription required for every marketable form.
- Check whether the pharmacy can source the brand or strength you need.
- Confirm whether PBS or private pricing applies.
- Ask about ordering time if you need ongoing supply.
Comparable Medicines And Patient Preferences
Should disulfiram be compared with naltrexone, acamprosate, baclofen, and topiramate?
Yes, because patients usually choose between medicines based on goals, tolerability, and access.
Naltrexone and acamprosate are often preferred in Australia because they do not depend on the disulfiram-ethanol reaction.
That makes them easier for many people to live with.
Disulfiram is better suited to highly motivated patients who want a strong deterrent, especially when supervised treatment is available.
Baclofen and topiramate may come up in specialist conversations, but their use can be more selective.
The main decision points are liver status, adherence, stigma, past treatment response, and whether supervised or unsupervised therapy is realistic.
| Medicine | Strength | Weakness | Best Fit |
|---|---|---|---|
| Disulfiram | Strong deterrent if alcohol is taken | Requires abstinence and adherence | Motivated patients in structured programs |
| Naltrexone | Craving reduction | Not a deterrent medicine | Patients wanting a non-deterrent option |
| Acamprosate | Supports abstinence maintenance | Requires ongoing dosing | Relapse prevention after stopping alcohol |
| Baclofen | May be considered off-label | Less straightforward use | Selected specialist cases |
| Topiramate | May help some patients | Not approved everywhere for this use | Specialist-led treatment discussions |
- Liver status and past liver test results.
- Ability to take medicine every day.
- Preference for supervised treatment.
- Previous response to alcohol dependence medicines.
- Comfort with a deterrent approach.
Frequently Asked Questions
How long before I can drink alcohol again?
Alcohol should be avoided during treatment and for at least 12 hours after the last dose, but the safest answer is to follow your prescriber’s advice because the reaction can still be dangerous.
Can I buy disulfiram without a prescription?
No, not in Australia or in most other major markets.
It is prescription-only, and that includes all marketable forms.
Is it safe if I have liver problems?
Severe hepatic disease is a contraindication.
Mild to moderate liver dysfunction needs close monitoring and possible dose reduction, so your GP or specialist should review liver tests first.
What if I miss a dose?
Take it when remembered if the next dose is not close, but do not double the dose.
Store tablets at room temperature, protected from moisture and light.
If you get severe nausea, jaundice, rash, confusion, or feel very unwell, seek medical advice promptly.
Guidelines For Proper Use
What does good use of disulfiram look like in real life?
It starts before the first tablet.
Abstinence should be confirmed, hidden alcohol sources should be avoided, and liver tests should be arranged.
That is the standard counselling Australian pharmacists and clinicians usually give.
Patients should report rash, jaundice, confusion, severe nausea, or unusual fatigue promptly.
Storage is straightforward: keep the tablets at 15 to 30°C, protected from moisture and light.
Successful treatment depends on a structured plan, not on tablets alone.
Pharmacists are often the first trusted contact, while telehealth can help with follow-up for people in rural areas.
| Counselling Point | What To Do | Why It Matters |
|---|---|---|
| Confirm abstinence | Do not start if alcohol has been used recently | Prevents a dangerous early reaction |
| Check liver tests | Attend baseline and follow-up monitoring | Helps detect liver injury early |
| Avoid hidden alcohol | Read labels on medicines and mouth products | Reduces unplanned reactions |
| Report side effects | Tell the prescriber about rash, jaundice, confusion, or severe nausea | Allows early review |
- Take the tablet exactly as prescribed.
- Avoid alcohol in all forms, including hidden sources.
- Attend liver function monitoring.
- Use supervised support where possible.
- Keep storage conditions within room temperature.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Toowoomba | Queensland | 5-9 days |