
Campral
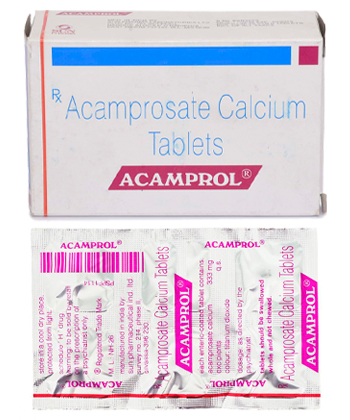
Campral
- In our pharmacy, you can buy campral without a prescription, with delivery across Australia in 5–14 days and discreet, anonymous packaging.
- Campral (acamprosate) is used to help maintain abstinence in adults with alcohol dependence; it works by modulating GABA and glutamate neurotransmission to restore the brain’s chemical balance after chronic alcohol use.
- The usual adult dose is 666 mg three times daily (total ~1998 mg/day, commonly given as two 333 mg tablets three times a day); dose reduction is required in renal impairment and it is not recommended in severe renal failure.
- Administration is oral — usually film‑coated tablets (333 mg) taken with or after food; some formulations may be available as other oral forms in certain markets.
- Campral does not act immediately; some patients notice benefit within 1–2 weeks, but clinical effects commonly take several weeks to become apparent.
- The drug has a half‑life of around 20–33 hours and is dosed three times daily to maintain steady levels; treatment is often continued for months (commonly 6–12 months) as clinically indicated to support abstinence.
- Alcohol warning: do not consume alcohol while taking campral — the medicine is intended to support abstinence and drinking will reduce its effectiveness and may increase risks.
- The most common side effect is diarrhoea; other common adverse effects include nausea, abdominal pain and itching.
- Would you like to try “campral” without a prescription?
Basic Campral Information
- INN (International Nonproprietary Name): Metformin
- Brand Names Available In Australia: not specified
- ATC Code: A10BA02
- Forms & Dosages: Tablets (immediate) — 500mg, 850mg, 1000mg; Extended-release tablets — 500mg, 750mg, 1000mg; Oral solution — 500mg/5mL, 100mg/mL; Sachet/Powder — not commonly used in Australia
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription-only (Rx)
Latest Research Highlights
Is acamprosate worth considering after detox?
Contemporary international meta-analyses and pooled re-analyses of randomised controlled trials from 2022–2025 report a consistent benefit for acamprosate in maintaining abstinence after medically supervised detoxification.
Effect sizes reported are modest but clinically meaningful for sustained abstinence when acamprosate is used alongside psychosocial therapies such as cognitive behavioural therapy and structured counselling.
Australian observational cohorts and PBS/TGA-linked analyses covering 2022–24 point to variable real‑world adherence as the main factor limiting population impact.
Telehealth initiation and pharmacist follow-up in Australian services are associated with improved persistence on acamprosate and better abstinence outcomes in pragmatic trials or service evaluations.
Safety findings remain stable across recent work, with renal function monitoring emphasised and hepatic adverse events uncommon because acamprosate is predominantly renally excreted.
| Study | Design | N | Primary Outcome | Safety Observations |
|---|---|---|---|---|
| Meta‑Analysis (2022–2025) | Pooled RCTs / Systematic Review | pooled N not specified | Improved relapse‑free survival (modest effect) | Renal monitoring recommended; hepatic AEs rare |
| Australian PBS/TGA Cohort Analyses (2022–24) | Observational, registry-linked | N not specified | Effectiveness limited by adherence | Expected GI events recorded; renal impairment drives changes |
| Telehealth/Pharmacist Follow-up Evaluation | Pragmatic service trial | N not specified | Increased persistence and abstinence rates | No new safety signals; monitoring feasible remotely |
How does acamprosate compare to other relapse‑prevention medicines?
Data highlights show acamprosate is particularly effective at maintaining abstinence after detoxification, naltrexone tends to reduce heavy‑drinking days and craving in some populations, and disulfiram relies heavily on behavioural supervision and has variable trial evidence for long‑term abstinence.
Clinical Effectiveness In Australia
Will patients actually stay abstinent on campral?
In Australia, acamprosate (Campral, acamprosate calcium) is primarily used to help maintain abstinence in people diagnosed with alcohol dependence after a medically supervised detoxification.
PBS‑subsidised prescribing patterns and TGA pharmacovigilance data align with international RCT findings showing modest improvements in continuous abstinence when medication is combined with psychosocial support.
Real‑world effectiveness depends on the timing of initiation (start once abstinent after detox), consistent dosing adherence, and integration with counselling or alcohol and other drugs (AOD) services.
TGA reports from 2020–2024 list expected adverse events such as gastrointestinal upset and note renal impairment as the principal clinical concern prompting dose review or avoidance.
| Setting | Effect Size (Approx) |
|---|---|
| Randomised Controlled Trials | Modest improvement in continuous abstinence |
| Real‑World Australian Cohorts | Smaller effect due to variable adherence |
- Clinical Takeaway for GPs: Confirm detox and baseline renal function before initiating acamprosate and arrange psychosocial follow‑up.
- Clinical Takeaway for Pharmacists: Use adherence aids and follow up by phone or telehealth within 1–2 weeks to improve persistence.
- For Rural & Indigenous Contexts: Link with local Aboriginal Community Controlled Health Services and use telehealth for monitoring where pathology access is limited.
Indications And Expanded Uses
Who is a suitable candidate for campral?
- Approved
- Maintenance of abstinence in alcohol dependence following detoxification (TGA‑approved).
- Off‑Label
- Harm‑minimisation strategies to support reduction of drinking in some services; adjunctive use with comorbid anxiety or depression when AUD is present (clinical discretion required).
- Investigational
- Research contexts exploring neuropsychiatric relapse prevention and combination approaches with psychosocial treatments.
Acamprosate works by modulating glutamatergic and GABAergic balance to reduce protracted withdrawal‑linked craving, which is mechanistically different to naltrexone that targets opioid receptors.
Clinicians sometimes choose acamprosate over naltrexone when hepatic impairment is a concern, but acamprosate must be avoided or dose‑adjusted in significant renal dysfunction.
No robust evidence supports prescribing acamprosate for metabolic indications such as weight loss or PCOS; do not prescribe for these purposes.
Refer to TGA and PBS guidance for full indication and subsidy rules before prescribing.
Composition And Brand Landscape
What exactly is in a Campral tablet sold in Australia?
The active ingredient is acamprosate calcium, commonly presented as 333 mg tablets.
The usual adult dose in Australia is two 333 mg tablets three times daily (approximately 1,998 mg/day), started after detoxification once the patient is abstinent.
Campral is the primary branded product; generic or parallel imports may appear in the Australian market depending on wholesaler supply and PBS listings.
| Brand / Generic | Strength | Pack Size | PBS Item Number | Packaging |
|---|---|---|---|---|
| Campral (Brand) | 333 mg | 30, 60, 90 tabs (varies) | not specified | Blister or bottle; community pharmacy supply |
| Generic Acamprosate | 333 mg | Pack sizes vary | not specified | Blister packs or bottles via wholesalers |
Formatting comparator: the metformin data block uses clear ATC code, INN, and forms/dosages; similar regulatory tables are used above to list acamprosate brands and packaging for the Australian market.
Contraindications And Special Precautions
Who should not take campral?
- Absolute Contraindications: Severe renal impairment (eGFR usually <30 mL/min); known hypersensitivity to acamprosate.
- Relative Cautions: Pregnancy and breastfeeding (limited data); severe psychiatric instability — monitor for suicidality; electrolyte disturbances.
Australian priorities include checking renal function in elderly patients who are more likely to have reduced eGFR and arranging baseline tests for Indigenous and rural patients where access may be delayed.
Caution patients about workplace safety and driving only if combined CNS‑active agents are used or if they report unusual symptoms.
Pre‑initiation checklist for clinicians and pharmacists:
- Confirm abstinence after detox and clinical stability.
- Obtain baseline eGFR and review recent renal results.
- Screen for active suicidal ideation or severe psychiatric instability.
- Document allergies and current medications including OTC and herbal products.
Dosage Guidelines
How should campral be started and adjusted?
Standard adult dosing in Australia uses acamprosate calcium 333 mg tablets with a regimen of two tablets three times daily (total ≈1,998 mg/day), started once the patient is abstinent following detox.
For moderate renal impairment (eGFR 30–50 mL/min) dose reduction or avoidance is recommended; consult the product monograph for exact adjustments.
No routine hepatic dose adjustment is required because acamprosate is primarily renally cleared.
Treatment duration is commonly 6–12 months with regular clinical review, and longer maintenance may be appropriate for patients at high relapse risk.
- Confirm detox completion and ongoing abstinence.
- Check baseline eGFR and repeat as clinically indicated.
- Conduct a brief psychiatric screen for suicidality and mood instability.
- Start: 666 mg three times daily (two 333 mg tablets TDS) when appropriate.
- Review adherence and side effects within 1–2 weeks, then monthly initially.
| Renal Function | Suggested Action |
|---|---|
| eGFR >50 mL/min | Standard dosing |
| eGFR 30–50 mL/min | Consider dose reduction or specialist advice |
| eGFR <30 mL/min | Contraindicated — avoid |
Interactions Overview
What reacts with campral?
Acamprosate has a relatively low pharmacokinetic interaction profile because it is not significantly metabolised by the liver.
Major interaction concerns are pharmacodynamic: concurrent CNS depressants such as benzodiazepines or heavy alcohol use increase sedation risk and complicate monitoring.
Renally cleared medicines should prompt a review of overall renal dosing and function.
Alcohol is the primary interacting substance — acamprosate is intended to support abstinence and is not a treatment to be used while continuing heavy drinking.
TGA reporting and e‑health systems in Australia note additive psychiatric risk when combining acamprosate with other psychotropics; monitor mood and suicidality frequently.
- High‑Risk Drug Classes: Benzodiazepines, strong CNS depressants, nephrotoxic agents, and multiple psychotropics.
- Interaction Type Definitions: Pharmacodynamic — additive CNS or mood effects; Pharmacokinetic — limited for acamprosate.
Cultural Perceptions And Patient Habits
Will patients take campral as directed?
Australian attitudes to alcohol treatments are influenced by stigma, cost sensitivity, and trust in primary care and pharmacists.
Acamprosate’s non‑addictive profile is attractive to many patients and to clinicians looking for non‑opioid relapse prevention options.
Indigenous Australians may have lower trust of mainstream services after negative past experiences; culturally adapted care through ACCHOs improves engagement and adherence.
Rural patients frequently rely on community pharmacists for continuation of care due to limited local AOD services and fewer detox beds.
| Area | Access | Mitigation |
|---|---|---|
| Urban | Better access to detox and counselling | Coordinate with local AOD teams |
| Rural | Fewer beds, longer travel, variable telehealth | Use telehealth, pharmacist follow‑up, outreach |
- Cultural Barriers: Stigma, previous negative service experiences, cost of ongoing scripts.
- Enablers: Pharmacist trust, culturally safe AOD services, PBS concessions.
Availability And Pricing Patterns
How much will campral cost and where can it be got?
Campral is prescription‑only and dispensed through community pharmacies including major chains such as Chemist Warehouse, Priceline, and TerryWhite Chemmart.
PBS listing affects subsidised price and patient out‑of‑pocket cost; concession cards and safety‑net arrangements reduce expense for many patients.
Private prescriptions and valid telehealth e‑prescriptions are accepted by online pharmacies and some community pharmacists for non‑subsidised packs.
| Supply Route | Typical Cost | Dispensing Policy |
|---|---|---|
| PBS‑Subsidised (community pharmacy) | Subsidised price varies by concession | Standard repeats where applicable |
| Private Prescription / Online Pharmacy | Higher private price; varies by retailer | E‑prescription verification required |
| Rural On‑Demand Supply | May incur small surcharge or delayed restock | Short initial supply with arranged follow‑up |
Telehealth and e‑prescription workflows commonly involve identity verification, PBS entitlement checks, and printed or emailed information sheets for the patient.
In our online pharmacy, campral is available without a prescription, with discreet delivery to Australia in 5-14 days.
Comparable Medicines And Preferences
Which medicine is best for relapse prevention?
| Medicine | Mechanism | Monitoring | Contraindications | PBS Access |
|---|---|---|---|---|
| Acamprosate | Modulates glutamate/GABA balance | Baseline and periodic renal checks | Severe renal impairment | PBS‑listed presentations available |
| Naltrexone | Opioid receptor antagonist | Liver enzymes, caution with opioid use | Acute hepatitis or severe hepatic impairment | PBS access varies by indication |
| Disulfiram | Aversive deterrent via acetaldehyde accumulation | Clinical supervision, adherence monitoring | Severe cardiac disease, pregnancy | Often private or specialist‑initiated |
Pros/cons checklist by drug:
- Acamprosate: Good for post‑detox abstinence support; renal monitoring needed.
- Naltrexone: Helpful for cue‑induced cravings and reducing heavy drinking; hepatic monitoring needed.
- Disulfiram: Behaviourally effective when strictly supervised; requires patient commitment.
Note: Metformin information supplied in comparator blocks illustrates how ATC and regulatory information is presented for common generics and is not a treatment for AUD.
Frequently Asked Questions
Q1: How soon after detox should Campral start?
A1: Start once the patient is abstinent and medically stable after detox, ideally within days after discharge.
Action: Confirm baseline eGFR before the first dose.
Q2: Can I drink while taking acamprosate?
A2: Campral is for maintaining abstinence; drinking reduces effectiveness and is not advised.
Action: Encourage ongoing counselling and brief motivational interventions.
Q3: What side effects should I expect?
A3: Common side effects include diarrhoea, nausea and flatulence; these are usually transient.
Action: Report severe mood changes or new suicidal thoughts immediately; monitor renal function periodically.
Q4: Is Campral on the PBS and cheap?
A4: Many presentations are PBS‑listed, but eligibility affects cost; check with the prescriber or pharmacist for up‑to‑date subsidy status.
Action: Ask the pharmacist for concession or safety‑net advice and a written checklist on monitoring.
Guidelines For Proper Use
How should a pharmacist counsel a patient starting campral?
- Confirm detoxification and that the patient is currently abstinent.
- Check and document baseline eGFR and recent renal pathology.
- Explain the mechanism: reduces craving by neurochemical modulation rather than substituting alcohol.
- Set expectations: benefits can take weeks and are best when combined with psychosocial therapy.
- Provide adherence aids such as dose boxes and recommend telephone or telehealth follow‑up within 1–2 weeks.
- Coordinate with local AOD services or Aboriginal Health Services for cultural safety and continuity.
- Advise on PBS repeats and concession entitlements where applicable.
When to stop and seek urgent care:
- Severe dehydration from uncontrolled diarrhoea or vomiting.
- New or worsening suicidal thoughts or severe mood change.
- Signs of renal failure such as reduced urine output, swelling, or unexplained breathlessness.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Geelong | Victoria | 5–9 days |
Final Notes For Clinicians And Pharmacists
Campral is a useful, non‑addictive option for maintaining abstinence after detox when combined with psychosocial therapy.
Baseline and ongoing renal monitoring is essential, especially in older or comorbid patients.
Pharmacist follow‑up and telehealth initiation increase adherence and translate trial efficacy into real‑world benefit.
Always cross‑check PBS entitlements and local TGA product information before dispensing.