
Metoclopramide
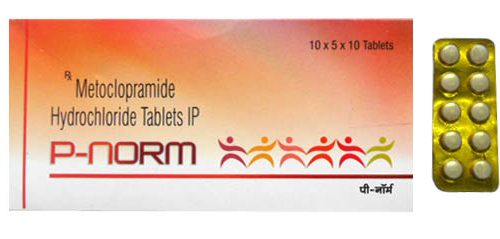
Metoclopramide
- Available from community pharmacies and hospitals; metoclopramide is prescription-only (Rx) in most countries including Australia, but availability varies and some local pharmacies or online sellers may supply it without a prescription — check local regulations and pharmacy policy.
- Metoclopramide is used as an antiemetic and prokinetic for nausea and vomiting, diabetic gastroparesis, prevention of chemotherapy-induced nausea and as an adjunct in migraine; it is a dopamine D2 receptor antagonist, 5‑HT3 receptor antagonist and 5‑HT4 receptor agonist that increases gastric motility and raises the threshold of the chemoreceptor trigger zone.
- Usual adult dosage is 10 mg orally, IM or IV three times daily for nausea; for gastroparesis 10 mg 30 minutes before meals (up to four times daily); typical maximum 30 mg/day (short-term supervised use may be up to 40 mg); paediatric and elderly dose adjustments apply.
- Forms and routes: oral tablets (5 mg, 10 mg), orally dispersible tablets (ODT), oral solution/syrup, and IM/IV ampoules.
- Onset of action: oral 20–60 minutes, IM 10–30 minutes, IV within minutes (often 1–3 minutes for antiemetic effect).
- Duration of action: effects typically last around 4–6 hours, depending on dose and route of administration.
- Alcohol warning: avoid alcohol while taking metoclopramide as it can increase drowsiness, sedation and the risk of central nervous system side effects.
- The most common side effect is drowsiness; other frequent effects include fatigue, restlessness/akathisia, diarrhoea and dizziness — long-term use can cause serious risks such as tardive dyskinesia.
- Would you like to try metoclopramide without a prescription?

Metoclopramide: What Australians Need To Know
Basic Metoclopramide Information
- INN (International Nonproprietary Name): Metoclopramide.
- Brand Names Available In Australia: not specified.
- ATC Code: A03FA01 — Metoclopramide (A03F Propulsives; A03 Drugs For Functional Gastrointestinal Disorders).
- Forms & Dosages: Tablets 5 mg and 10 mg; Orally dispersible tablets 5 mg and 10 mg; Oral solution 5 mg/5 mL and 10 mg/10 mL; Ampoule 10 mg/2 mL for IM/IV.
- Manufacturers In Australia: not specified.
- Registration Status In Australia: not specified.
- OTC / Rx Classification: Prescription Only (Rx) in most markets; not an OTC medicine due to risks with chronic use and extrapyramidal effects.
Latest Research Highlights
Clinicians often ask whether metoclopramide is still recommended for acute nausea and how long it is safe to use.
Recent Australian and international analyses between 2022 and 2025 emphasise metoclopramide’s reliable short‑term efficacy as an antiemetic and prokinetic and highlight safety limits for longer use.
Randomised controlled trials continue to show clear benefit for acute postoperative nausea and vomiting (PONV), chemotherapy‑related nausea when combined with 5‑HT3 antagonists, and migraine‑associated vomiting.
Pharmacoepidemiology and meta‑analyses report limited long‑term benefit for chronic gastroparesis because of accumulating safety signals, especially tardive dyskinesia with prolonged exposure.
Australian post‑marketing surveillance and hospital audits have continued to flag extrapyramidal events and tardive dyskinesia with cumulative exposure.
Recent safety reviews recommend limiting courses to short periods (commonly ≤5–12 days) and using the lowest effective dose, with dose reductions in hepatic or renal impairment and in the elderly.
| Study Type | Efficacy Endpoints | Safety Observations |
|---|---|---|
| Randomised Controlled Trials (RCTs) | Rapid control of acute PONV, migraine vomiting, adjunctive chemo control with 5‑HT3 agents. | Short‑term tolerability good; lower extrapyramidal risk with single/short courses. |
| Observational Studies | Fast symptom relief in emergency and ward settings; oral 10 mg effective for ambulatory nausea. | Reports of akathisia, dystonic reactions; greater risk with repeated dosing. |
| Surveillance / Hospital Audits | Supports routine short‑term use IV/IM for acute nausea. | Continued signals of tardive dyskinesia with cumulative exposure; calls for duration limits. |
Clinical Effectiveness In Australia
People commonly ask how quickly metoclopramide works in an emergency or after surgery.
Australian clinical practice treats metoclopramide as a dependable short‑term antiemetic across emergency departments, surgical wards and primary care.
Hospitals routinely supply IV and IM ampoules for rapid control of acute nausea, and community prescribers use oral tablets and orally dispersible tablets for ambulatory cases.
State health audits from 2022–25 show IV/IM administration relieves symptoms within 30–60 minutes in most patients with PONV or migraine vomiting.
Oral metoclopramide 10 mg three times daily produces good relief for mild to moderate ambulatory nausea, but severe chemotherapy nausea is often treated with combinations that favour ondansetron or other 5‑HT3 antagonists.
For diabetic gastroparesis, short courses timed before meals can help symptoms but long‑term use is discouraged because of tardive dyskinesia risk.
Common adverse events reported to the TGA include drowsiness, akathisia and prolactin‑related effects, reinforcing guidance to avoid prolonged courses.
- Time To Relief: IV/IM 30–60 minutes; oral 10–60 minutes depending on severity.
- Common Adverse Events: Drowsiness, restlessness (akathisia), diarrhoea.
- TGA Reporting Themes: Extrapyramidal reactions and tardive dyskinesia with cumulative exposure.
Indications And Expanded Uses
Patients often want to know what metoclopramide is officially approved to treat in Australia.
TGA‑aligned indications and common international uses include acute nausea and vomiting, adjunctive treatment in migraine, and short‑term management of diabetic gastroparesis.
Clinicians also use metoclopramide off‑label for refractory nausea in palliative care and as a bridging antiemetic in emergency settings.
Chemotherapy regimens sometimes incorporate IV metoclopramide as an adjunct to 5‑HT3 antagonists for particular protocols.
Off‑label prescribing should weigh benefit against risk, particularly when considering courses beyond five days because of tardive dyskinesia risk.
- Approved Uses: Acute nausea and vomiting; adjunct for migraine; short‑term diabetic gastroparesis.
- Common Off‑Label Uses: Palliative refractory nausea; emergency bridging; adjunct in some chemo regimens.
| Indication | Typical Australian Route/Dose |
|---|---|
| Nausea/Vomiting | Oral/IV/IM 10 mg three times daily (max 30 mg/day). |
| Diabetic Gastroparesis | 10 mg orally 30 minutes before meals and at bedtime (short‑term, up to 4 times daily; short‑term max 40 mg/day). |
| Chemotherapy‑Related Nausea | IV 10–20 mg prior to chemotherapy as adjunct per regimen. |
| Paediatric Use | Weight‑based 0.1–0.15 mg/kg q8h (max 10 mg/dose). |
Composition And Brand Landscape
Customers often ask whether metoclopramide tablets are branded or generic in Australia.
The active ingredient is metoclopramide hydrochloride, listed by INN as metoclopramide.
Globally the drug appears under brand names such as Primperan, Reglan and Maxolon as well as many generics.
In Australia generic metoclopramide formulations and hospital injectables are commonly used, with retail brand names varying by supplier.
Available formulations include 5 mg and 10 mg tablets, orally dispersible tablets, oral solutions (5 mg/5 mL) and 10 mg/2 mL ampoules for IM/IV use.
| Form | Strength | Common Pack Sizes |
|---|---|---|
| Tablet | 5 mg, 10 mg | Blisters of 10–50 tablets |
| Orally Dispersible Tablet | 5 mg, 10 mg | Blisters/Boxes |
| Oral Solution | 5 mg/5 mL, 10 mg/10 mL | Bottles 100–200 mL |
| Ampoule/Vial | 10 mg/2 mL | Boxes of 5 or 10 ampoules |
Note: Metoclopramide is prescription‑only and not widely subsidised for many indications, so patients often pay privately for metoclopramide 10mg tablets.
Contraindications And Special Precautions
Many patients ask whether metoclopramide is safe for people with Parkinson’s or seizure disorders.
Absolute contraindications include hypersensitivity to metoclopramide, pheochromocytoma, seizure disorders and mechanical gastrointestinal obstruction, haemorrhage or perforation.
A prior history of tardive dyskinesia is a firm contra‑indicator to any metoclopramide use.
Relative cautions include Parkinson’s disease, mood disorders, hepatic or renal impairment, pregnancy and breastfeeding, and advanced age where extrapyramidal effects are more likely.
People should be warned about drowsiness and akathisia and advised not to drive or operate heavy machinery until they know how metoclopramide affects them.
For Indigenous and remote communities, heightened vigilance is recommended because of higher rates of comorbidity and challenges with follow‑up care.
| Population Group | Special Precautions |
|---|---|
| Elderly | Prefer reduced starting dose; monitor for extrapyramidal reactions. |
| Hepatic/Renal Impairment | Consider 50% dose reduction. |
| Pregnancy/Breastfeeding | Cautious use; short courses may be considered with informed consent. |
Dosage Guidelines
People often ask how much metoclopramide they can safely take each day.
Standard adult dosing in Australia is 10 mg orally, IM or IV three times daily for nausea with a maximum of 30 mg per day.
For diabetic gastroparesis clinicians may give 10 mg 30 minutes before meals and at bedtime, up to four times daily for short‑term use with a short‑term maximum of 40 mg per day.
Paediatric dosing is weight‑based at 0.1–0.15 mg/kg per dose every eight hours, with a maximum of 0.5 mg/kg/day and up to 10 mg per dose.
Dose reductions of about 50% are recommended for significant hepatic or renal impairment (for example GFR <40 mL/min).
Elderly patients should start at a lower dose and be monitored closely for extrapyramidal effects.
Treatment duration should typically be a single dose or a short course of ≤5 days, and should not exceed 12 weeks for any indication because of tardive dyskinesia risk.
| Group | Typical Dose | Max Daily Dose |
|---|---|---|
| Adults | 10 mg PO/IV/IM tds | 30 mg/day |
| Diabetic Gastroparesis | 10 mg 30 min before meals and at bedtime | 40 mg/day (short term) |
| Children | 0.1–0.15 mg/kg q8h | Max 0.5 mg/kg/day (up to 10 mg/dose) |
Missed Dose: Take when remembered unless close to the next dose; do not double up.
Overdose Signs: Drowsiness, disorientation and extrapyramidal reactions warrant urgent care.
Interactions Overview
Patients commonly ask whether metoclopramide is safe to take with antipsychotics or opioids.
Major interaction risks come from additive extrapyramidal effects when metoclopramide is combined with antipsychotics and other dopamine antagonists.
CNS depression increases when metoclopramide is used with opioids, alcohol and sedative medicines.
Concomitant antipsychotics may potentiate prolactin‑mediated effects and increase risk of movement disorders.
Concurrent use with QT‑prolonging drugs should prompt a careful review in polypharmacy settings.
| Drug/Class | Clinical Effect |
|---|---|
| Antipsychotics (Dopamine Antagonists) | Increased risk of extrapyramidal symptoms and tardive dyskinesia. |
| Opioids, Alcohol, Sedatives | Enhanced CNS depression and drowsiness; increased fall risk. |
| QT‑Prolonging Agents | Require review when on multiple QT‑prolonging medicines. |
Pharmacists should check My Health Record and eScripts for antipsychotic co‑prescribing and flag elderly patients in aged care for interaction review.
Cultural Perceptions And Patient Habits
Many Australians value fast relief and clear advice when they seek an antiemetic from a local pharmacy.
Online forums and community pharmacy feedback show people appreciate rapid symptom relief from metoclopramide but worry about movement disorders and long‑term harms.
Rural patients tend to rely on local pharmacies for immediate access and advice and may face longer waits for specialist review.
Telehealth and e‑prescriptions have improved access but can limit face‑to‑face assessment for side‑effect screening.
Indigenous health services stress the need for culturally tailored counselling because of higher comorbidity rates and concerns about side effects.
Price sensitivity means many consumers favour generics or discount pharmacy chains and may request shorter courses or alternatives.
- Theme: Rapid relief valued but fears about tardive dyskinesia are common.
- Theme: Rural access relies on trusted community pharmacists for follow‑up.
Availability And Pricing Patterns
People want to know where they can buy metoclopramide and how much it will cost.
In Australia metoclopramide is prescription‑only and available through community pharmacies and hospital supply chains.
When not PBS‑subsidised, patients typically pay privately for generics, while inpatient hospital use is generally covered.
Injectable metoclopramide is usually reserved for hospital administration, with oral forms dispensed in community pharmacies.
Price competition among chains can make generic metoclopramide tablets affordable, but out‑of‑pocket cost sometimes influences choice of duration or alternative agents.
Stock levels can vary in regional centres and pharmacists should flag supply issues and suggest alternatives like ondansetron or domperidone where appropriate.
| Channel | Typical Pricing Pattern |
|---|---|
| PBS | Not widely subsidised for many indications; hospital supply common. |
| Private Retail | Patients pay privately for generics; pricing varies by chain. |
| Hospital | Inpatient use generally covered; injectables hospital‑administered. |
Our online pharmacy offers discreet delivery across Australia and can supply metoclopramide without a prescription, with delivery in 5–14 days.
Comparable Medicines And Preferences
Clinicians and patients ask which antiemetic is best for their situation.
Alternatives available in Australia include domperidone, ondansetron and other 5‑HT3 antagonists, prochlorperazine and promethazine.
Domperidone is often preferred where a peripheral prokinetic is needed and central side effects must be minimised, but it carries QT‑related cardiac considerations.
Ondansetron is favoured for chemotherapy and severe PONV because it has minimal extrapyramidal risk, though it can be costlier or off‑PBS for some uses.
Metoclopramide remains valuable for rapid central antiemetic effect and for IV use in acute care settings.
| Medicine | Pros | Cons |
|---|---|---|
| Metoclopramide | Rapid central antiemetic; IV/IM option; prokinetic effect. | Extrapyramidal risk with prolonged use; tardive dyskinesia concern. |
| Domperidone | Less CNS penetration; useful for peripheral prokinetic need. | QT prolongation risk; cardiac monitoring may be required. |
| Ondansetron | Low extrapyramidal risk; effective for chemo and PONV. | Can be more expensive; may be off‑PBS for some indications. |
Choice depends on setting: ED and wards often use IV metoclopramide, oncology prefers 5‑HT3 antagonists, and palliative care uses tailored combinations.
Frequently Asked Questions
Q: Is metoclopramide on the PBS?
A: Generally prescription‑only and not widely PBS‑subsidised for all indications; hospital supply covers many inpatient uses.
Q: How long can I take it safely?
A: Short courses (≤5 days) are standard; avoid use beyond 12 weeks due to tardive dyskinesia risk.
Q: Can I drive after taking it?
A: Avoid driving if you experience drowsiness, dizziness or akathisia; test your response before driving.
Q: What are signs of serious side‑effects?
A: New involuntary movements, sustained muscle spasms or high fever with rigidity require urgent medical assessment.
When To Seek Medical Help: Stop the medicine and seek urgent care for acute dystonia, new involuntary movements or severe sedation.
For official patient information consult TGA and PBS resources or ask your pharmacist for printed advice.
Guidelines For Proper Use
Pharmacists should counsel patients to confirm the indication and screen for contraindications before dispensing metoclopramide.
Check history of neuroleptic exposure, Parkinson’s disease, pheochromocytoma and seizure disorders.
Review concomitant medicines and advise on the correct dose, timing and maximum duration — emphasise short‑course use.
Explain common side‑effects such as drowsiness, diarrhoea and akathisia and instruct patients to stop therapy and seek help if they notice involuntary movements.
For diabetic patients explain the importance of taking metoclopramide 30 minutes before meals for gastroparesis dosing.
Advise on storage at 15–30°C and protecting tablets from moisture and light.
Provide written action plans for rural patients and offer telehealth follow‑up or referral to Aboriginal Health Services for Indigenous patients as preferred.
- Screening Checklist: Contraindications, co‑medications, pregnancy/breastfeeding, elderly status.
- Patient Handout Template: Dose, duration, red‑flag symptoms, missed dose instructions.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Sunshine Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |