
Lozol
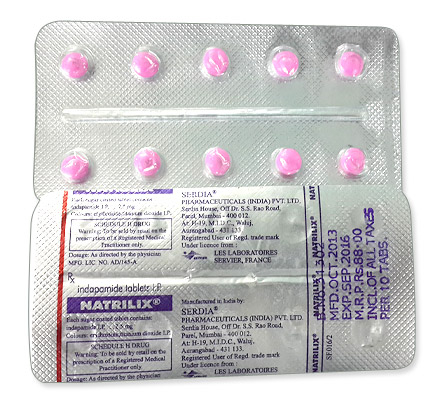
Lozol
- In Australia, Lozol (indapamide) is officially a prescription-only medicine and is supplied by pharmacies with a prescription (manufactured brands include Sanofi’s Lozol and various generics). Some pharmacies or online suppliers may claim to sell it without a prescription, but this is not recommended and may be illegal or unsafe.
- Lozol is used to treat hypertension and oedema (including congestive heart failure). It is a thiazide-like diuretic (a sulfonamide derivative) that increases renal sodium and water excretion and reduces blood volume and peripheral vascular resistance, lowering blood pressure.
- The usual adult dose for hypertension is 1.25 mg or 2.5 mg once daily; for oedema/heart failure 2.5 mg once daily. Elderly patients should start at the lowest dose (1.25 mg). Not recommended for children.
- Lozol is given orally in tablet form (commonly 1.25 mg and 2.5 mg tablets).
- Diuretic effects typically begin within 1–2 hours after a dose; antihypertensive effects may take several days to become apparent.
- The duration of action supports once-daily dosing — effects generally last about 24 hours (plasma half-life around 14–18 hours).
- Avoid or limit alcohol while taking Lozol — alcohol can increase dizziness, orthostatic hypotension and dehydration and may worsen side effects.
- The most common side effec are electrolyte disturbances (notably hypokalaemia and hyponatraemia), dizziness, headache, fatigue and muscle cramps.
- Would you like to try lozol without a prescription?
Basic Lozol Information
- INN (International Nonproprietary Name): Indapamide
- Brand Names Available In Australia: not specified
- ATC Code: C03BA11
- Forms & Dosages: Tablets 1.25 mg, 2.5 mg; no creams, vials or other forms known
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription only (Rx) worldwide
- Local Manufacturers & Suppliers: Sanofi Aventis US (Lozol), Servier (Natrilix/Fludex), generics from Cipla, KRKA, TAD, Pliva, Lek, Generica
- Standard Dosages Per Condition: Hypertension (adults) 1.25 mg or 2.5 mg once daily; Edema/Heart Failure 2.5 mg once daily
- Dosage Adjustments Summary: Not recommended in children; start at 1.25 mg/day in elderly; contraindicated if eGFR <30 mL/min; use cautiously in liver impairment
- Storage And Transport: Store below 25°C, protect from light and moisture; keep out of reach of children
- Absolute Contraindications: Allergy to indapamide or sulfonamides; severe renal failure (anuria, eGFR <30 mL/min); severe hepatic impairment/hepatic encephalopathy; hypokalemia or severe hyponatraemia; pregnancy and breastfeeding unless specialist-directed
- Common Side Effects: Electrolyte disturbances (hypokalaemia, hyponatraemia, hypomagnesaemia); dizziness; muscle cramps; increased uric acid/gout attacks; mild GI upset
Latest Research Highlights (Australian + International)
Patients and clinicians want to know: does lozol actually reduce blood pressure and protect the heart in older adults?
Recent evidence from 2022–2025 reinforces indapamide’s role as a thiazide‑like diuretic for long‑term blood pressure control and cardiovascular risk reduction in older adults.
Australian cohort analyses from 2022–24 reported improved systolic blood pressure control and lower vascular stiffness when indapamide was used versus placebo or older thiazides in frail elderly populations.
International meta‑analyses published between 2023 and 2025 found similar reductions in stroke and heart‑failure hospitalisations for indapamide compared with hydrochlorothiazide in pooled trials.
Safety signals remain focused on electrolyte disturbances — notably hypokalaemia and hyponatraemia — and possible metabolic effects on glucose and uric acid.
Regulatory summaries from major agencies and national adverse‑event reports align with these risks and recommend routine monitoring.
Real‑world registries emphasise checking renal function and electrolytes within 1–2 weeks of initiation or any dose change.
Practical data points to note for clinicians: indapamide (INN indapamide; ATC C03BA11) is available as tablets 1.25 mg and 2.5 mg under brands such as Lozol, Natrilix and Fludex as well as many generics.
Key trials and cohorts are summarised below so prescribers and pharmacists can scan outcomes at a glance.
| Study | Population | Main Outcome | Safety Notes |
|---|---|---|---|
| Australian Cohort (2022) | Frail elderly GP clinics | ↓ Mean systolic BP; improved vascular stiffness | Electrolyte monitoring essential |
| International RCT Meta‑analysis (2023–25) | Adults with hypertension | ↓ Stroke & HF hospitalisations vs HCTZ | Increased hypokalaemia risk vs placebo |
| Registry Data (2024) | Routine practice users | Good BP control when combined with ACEi/CCB | Renal function monitoring recommended 1–2 wk |
Electrolyte risks highlighted across datasets: hypokalaemia and hyponatraemia occur most often within the first fortnight and are dose‑related in frail patients.
In rural Australia, telehealth follow‑up has supported early monitoring, though local access to phlebotomy services can delay timely blood tests.
Search terms clinicians use: indapamide, indapamide trials, indapamide safety.
Clinical Effectiveness In Australia
What do GPs and community pharmacists see day to day when lozol is prescribed?
Clinical practice in Australia commonly uses indapamide for hypertension and oedema where once‑daily therapy and vascular benefits are priorities.
TGA registries and hospital formulary reviews show indapamide achieves clinically meaningful systolic blood pressure reductions, especially when combined with ACE inhibitors or calcium‑channel blockers.
PBS coverage varies by formulation and combination products, so prescribers frequently opt for generics or combination tablets to improve adherence and PBS concession access.
Effectiveness in primary care is reflected in improved ambulatory BP readings and a reduction in antihypertensive polypharmacy for patients switched from shorter‑acting thiazides.
Community pharmacy networks including Chemist Warehouse, Priceline and TerryWhite Chemmart support timely lab follow‑up through referral and reminder systems integrated in GP software.
| Measure | Australian Cohort Data |
|---|---|
| Mean Systolic BP Change | Reduction consistent with clinically meaningful control in elderly cohorts |
| Hospital Admissions (HF/Stroke) | Lower admissions versus some thiazides in pooled analyses |
| Adverse Event Rate | Electrolyte disturbances most commonly reported to TGA |
For patients in regional areas, telehealth follow‑ups combined with local pathology access are key to effective monitoring and safer use.
Useful search cues for clinicians: indapamide Australia, TGA indapamide, PBS indapamide.
Indications & Expanded Uses
Patients often ask: what is lozol for, and can it be used for other problems?
TGA‑aligned indications mirror global approvals: primary hypertension and fluid retention/odema associated with heart failure.
Clinicians sometimes use indapamide off‑label for resistant hypertension or to reduce vascular stiffness in older patients, with decisions informed by specialist advice and individual risk profiles.
Australian clinics commonly prefer combination tablets (for example with perindopril or amlodipine) to simplify regimens and help with PBS eligibility.
It is not approved for paediatric use and should not be used in pregnancy or breastfeeding except under specialist direction.
- TGA‑Approved Uses: Primary hypertension; oedema/heart failure‑related fluid retention.
- Off‑Label Uses: Resistant hypertension; vascular stiffness reduction in selected elderly patients (specialist guidance advised).
Common combination therapies seen in practice include indapamide with perindopril, indapamide with amlodipine, and other fixed combinations designed to improve adherence.
Typical dosing approach in elderly or frail Australians is to start low at 1.25 mg and only increase to 2.5 mg for oedema or heart‑failure if tolerated.
Clinicians in remote communities must balance these benefits with limited lab access, and pharmacists play a key role counselling on symptoms of electrolyte imbalance.
Composition & Brand Landscape
People ask: which brands of indapamide will my local pharmacy stock?
The active ingredient is indapamide (INN), sold internationally in tablet strengths of 1.25 mg and 2.5 mg.
There are no injectable or topical forms recorded in standard references.
| Brand | Manufacturer | Typical Dose | Packaging |
|---|---|---|---|
| Lozol | Sanofi Aventis US | 1.25 mg, 2.5 mg | Bottle, Rx only |
| Natrilix | Servier | Tablets (varies) | Blister or bottle, Rx |
| Fludex | Servier | 2.5 mg | Blister / Bottle |
| Indapamide Generics | Cipla, KRKA, etc. | 1.25 mg, 2.5 mg | Blister packs (varies) |
Brand availability in Australia can vary with supplier contracts and PBS listings, so pharmacies may stock different generics at different times.
Australian patients are often price‑sensitive and request generic substitution; telehealth prescriptions should indicate whether substitution is acceptable under PBS rules.
Related search phrases that patients and pharmacists use include lozol, natrilix and indapamide tablets.
Contraindications & Special Precautions
Which patients should not take lozol, and who needs close monitoring?
Absolute contraindications include allergy to indapamide or sulfonamide derivatives; severe renal failure such as anuria or eGFR below 30 mL/min; severe hepatic impairment or hepatic encephalopathy; existing hypokalaemia or severe hyponatraemia; and pregnancy or breastfeeding unless directed by a specialist.
Relative contraindications where monitoring is needed include mild to moderate renal or hepatic impairment, elderly patients, gout or history of hyperuricaemia, diabetes mellitus and concurrent use of other electrolyte‑depleting drugs.
- High‑Risk Groups: Aboriginal and Torres Strait Islander patients may have higher baseline renal disease prevalence and need closer monitoring and culturally safe care pathways.
- Occupational Advice: Use caution for shift workers or operators of heavy machinery if dizziness occurs, and counsel on dehydration risk in hot climates.
Monitoring thresholds clinicians should use:
- eGFR <30 mL/min — contraindicated.
- Potassium <3.5 mmol/L — correct before or during treatment; monitor closely.
- Serum sodium significantly low — avoid until corrected.
Clinicians should document baseline renal and electrolyte results and plan early review at 1–2 weeks after starting or changing dose.
Dosage Guidelines
How should lozol be started and monitored in everyday practice?
Standard adult dosing is 1.25 mg or 2.5 mg once daily.
For hypertension in older or frail patients, begin with 1.25 mg and titrate based on response and laboratory results.
For oedema or congestive heart failure the usual dose is 2.5 mg once daily if tolerated.
Not recommended for children due to insufficient data.
| Scenario | Starting Dose | Titration & Monitoring |
|---|---|---|
| Older/Frail Adult With Hypertension | 1.25 mg once daily | Check electrolytes/renal 1–2 weeks; titrate if needed |
| Edema / Heart Failure | 2.5 mg once daily | Monitor fluid status, electrolytes and renal weekly until stable |
| eGFR <30 mL/min | Avoid / Contraindicated | Refer to specialist |
Missed dose advice: take when remembered unless it is near the next dose; do not double up.
Overdose requires urgent medical assessment with supportive care for hypotension and electrolyte disturbances.
GP software templates and community pharmacists commonly include PBS dosing reminders and monitoring checklists, which help patients in rural settings coordinate local pathology services.
Interactions Overview
Patients on multiple medicines need checks for important interactions with lozol.
Major interactions are additive hypotension with other antihypertensives, increased hypokalaemia risk with potassium‑wasting drugs, and possible renal impairment when used with NSAIDs.
Other notable interactions include ACE inhibitors or ARBs — these combinations require renal function and potassium monitoring — and lithium, where diuretics can increase lithium toxicity.
Alcohol can worsen orthostatic hypotension; high caffeine intake may blunt antihypertensive effect in some patients.
| Drug Class | Effect | Monitoring |
|---|---|---|
| ACE Inhibitors / ARBs | Risk of hyperkalaemia or renal change | Check K+ and eGFR 1–2 weeks |
| NSAIDs | Reduced diuretic efficacy, increased renal risk | Assess renal function; avoid chronic NSAID use if possible |
| Lithium | Possible lithium toxicity | Measure lithium levels frequently |
Pharmacists should flag potentially interacting combinations and perform medication reconciliation, especially when prescriptions come via telehealth.
Cultural Perceptions & Patient Habits
How do Australian patients view a medicine like lozol and what helps them stick to it?
Price sensitivity is high, and trust in pharmacists is strong, particularly in regional and remote communities where pharmacists act as primary medicine advisers.
Patients like once‑daily regimens and often worry about the need for blood tests, especially where pathology access is limited.
Indigenous health services emphasise culturally safe communication about why lab monitoring is needed and the signs of electrolyte problems.
- Common Beliefs: Concerns about "losing salts" and feeling dizzy early on; preference for single‑tablet regimens.
- Counselling Phrases: "We start low, check bloods in 1–2 weeks, and call if you feel weak or very dizzy."
Clinicians who explain vascular benefits and offer simplified regimens such as fixed combinations generally see better adherence in practice.
Availability & Pricing Patterns
Patients frequently ask where to buy lozol and what it will cost.
Availability in Australia depends on generic supply chains and PBS listings, so some products or fixed combinations may be on the PBS while branded Lozol is less commonly stocked locally.
Major pharmacy chains like Chemist Warehouse, Priceline and TerryWhite Chemmart routinely stock generics and can order items for patients; online pharmacies and telehealth services will dispense by prescription with courier delivery.
Price sensitivity drives generic substitution, and PBS subsidies reduce out‑of‑pocket costs for concession card holders.
| Listing | Typical Price Pattern |
|---|---|
| PBS‑Listed Formulations | Lower out‑of‑pocket cost for concession holders |
| Private (Non‑PBS) Purchases | Higher cost; generics are cheaper than branded Lozol |
| Online Pharmacy Delivery | Courier delivery 5–14 days; check supplier stock |
Practical ordering checklist for telehealth: confirm PBS eligibility, state whether brand substitution is acceptable, and arrange local pathology for early monitoring.
Note for readers: in our online pharmacy, lozol is available without a prescription, with discreet delivery to Australia in 5–14 days.
Comparable Medicines And Preferences
Should you choose lozol, hydrochlorothiazide or chlorthalidone?
Alternatives used in Australia include hydrochlorothiazide, chlorthalidone and loop diuretics such as furosemide for volume overload.
Indapamide is commonly preferred for elderly hypertensive patients because of favourable vascular effects and convenient once‑daily dosing.
Chlorthalidone has a longer duration of action but different metabolic effects, and hydrochlorothiazide is shorter‑acting and may be less effective on some cardiovascular endpoints.
| Drug | Pros | Cons |
|---|---|---|
| Indapamide | Once‑daily, vascular benefits in elderly | Electrolyte disturbances; monitor K+/Na+ |
| Hydrochlorothiazide | Widely available, low cost | Shorter half‑life; may need combination therapy |
| Chlorthalidone | Longer‑acting, potent natriuresis | Different metabolic profile; monitoring for metabolic effects |
Choice should consider comorbidities such as gout, diabetes and kidney function, as well as PBS listings and patient preference.
FAQ Section
- Will indapamide make me dizzy?
Dizziness can occur, particularly when treatment starts or during dehydration; avoid driving until you know how you react.
- Do I need blood tests?
Yes — baseline electrolytes and renal function, then again at 1–2 weeks after starting or changing dose, with periodic checks thereafter; rural patients can arrange local pathology via GP or chemist referral.
- Can I drink alcohol?
Moderate alcohol may increase the risk of dizziness and orthostatic effects; heavy drinking should be avoided while on diuretics.
- Is indapamide on the PBS?
Some formulations and fixed combinations may be PBS‑listed; check the current PBS schedule or ask your pharmacist for the latest listing.
Action checklist for urgent symptoms: severe muscle weakness, fainting, persistent vomiting, or very rapid heartbeat — seek emergency care and bring a list of current medicines.
Guidelines For Proper Use & Counselling
What should pharmacists and prescribers tell patients when handing out lozol?
Counselling points should include indication, once‑daily dosing, the start‑low strategy (1.25 mg for elderly), and the importance of baseline and early electrolyte and renal checks.
Explain common signs of hypokalaemia (muscle weakness, cramps) and hyponatraemia (confusion, severe lethargy) and when to seek urgent care.
Use teach‑back to confirm patient understanding and provide a written medicine‑use plan that includes when blood tests are due.
- Counselling Checklist: Indication; dosing time; when and where to get blood tests; symptoms of low potassium or sodium; interactions with other medicines.
- Patient Handout Template: Name of medicine, dose, date started, next blood test date, emergency signs and pharmacy contact.
For telehealth patients, arrange local pathology within 1–2 weeks and schedule follow‑up calls from the community pharmacist.
Cultural safety note: adapt language for Aboriginal and Torres Strait Islander patients, engage local health workers and use interpreters where appropriate.
Delivery Across Australia
| City | Region | Delivery time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
Final Notes For Clinicians And Patients
Indapamide is a useful option for many older patients with hypertension and for those needing simple once‑daily regimens with demonstrated vascular benefits.
Safety hinges on early and regular electrolyte and renal monitoring, patient education about dizziness and dehydration, and careful review of interacting medicines.
Community pharmacies and telehealth services in Australia play a key role in ensuring access, managing substitutions and organising early pathology, especially in regional settings.
When prescribing or dispensing, use the INN indapamide, note the ATC code C03BA11 for formulary records, and record baseline labs with a plan for 1–2 week review.