
Calan
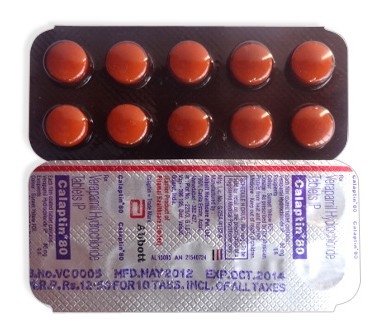
Calan
- In our pharmacy, you can buy Calan without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging; note that Calan (verapamil) is prescription‑only in many countries, so local regulations may differ.
- Calan (verapamil) is used for hypertension, angina (including variant/Prinzmetal’s angina) and certain arrhythmias (atrial fibrillation/flutter, paroxysmal supraventricular tachycardia). It is a phenylalkylamine calcium‑channel blocker that inhibits L‑type calcium channels, reducing cardiac contractility, slowing AV nodal conduction and causing peripheral vasodilation.
- The usual dose for adults is 80–120 mg orally three times daily for immediate‑release formulations, or 180–240 mg once or twice daily for extended‑release/sustained‑release products; for IV use typical bolus doses are 5–10 mg (may be repeated per medical protocol). Dosing should be reduced in the elderly and in renal/hepatic impairment; paediatric use requires specialist guidance.
- Administration forms include immediate‑release tablets (40, 80, 120 mg), extended‑release tablets and capsules (100–240 mg, common ER strengths 120, 180, 240 mg) and an intravenous solution (e.g. 2.5 mg/mL; 5 mg/2 mL ampoules).
- Onset: oral immediate‑release preparations typically begin to work within 30–60 minutes (extended‑release formulations have a slower onset of 1–3 hours); IV verapamil acts within 1–5 minutes.
- Duration of action: immediate‑release oral effects generally last about 4–8 hours; extended‑release preparations provide control for approximately 12–24 hours; IV effects are shorter and require monitoring.
- Alcohol warning: avoid or limit alcohol while taking Calan as alcohol can increase dizziness, low blood pressure and other adverse effects and may worsen heart‑rate and conduction changes.
- The most common side effect is constipation; other frequent effects include dizziness, headache, ankle oedema and nausea, with more serious risks of bradycardia, AV block and hypotension in some patients.
- Would you like to try calan without a prescription?
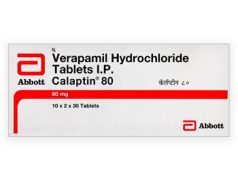
Basic Calan Information
- INN (International Nonproprietary Name): Verapamil.
- Brand Names Available In Australia: Calan (US discontinued), Calan SR, Isoptin SR, Covera‑HS, Verelan, Verelan PM and generic Verapamil products are used worldwide and may appear in Australia as generics.
- ATC Code: C08DA01.
- Forms & Dosages: Tablets 40 mg, 80 mg, 120 mg.
- Forms & Dosages (continued): Extended‑release tablets 120 mg, 180 mg, 240 mg, and extended‑release capsules 100–240 mg.
- Forms & Dosages (IV): Intravenous solution 2.5 mg/mL (5 mg/2 mL ampoules).
- Manufacturers In Australia: Local suppliers vary; global manufacturers include Abbott, Pfizer, Mylan, Teva and Sandoz, with generics commonly supplied to Australian wholesalers.
- Registration Status In Australia: Prescription-only in most regions per international registries; local PBS and TGA listings should be checked for current subsidy and registration details.
- OTC / Rx Classification: Rx (prescription-only) in most jurisdictions, though supply and subsidy depend on formulation and indication.
- Indications: Hypertension, angina pectoris (including variant angina), and arrhythmias such as atrial fibrillation/flutter and paroxysmal supraventricular tachycardia.
- Dosage Guidelines: Hypertension—80–120 mg PO three times daily (immediate‑release) or 180–240 mg once or twice daily (extended‑release).
- Dosage Guidelines (Arrhythmia): IV for acute arrhythmia 5–10 mg IV bolus; may repeat once after 30 minutes under monitoring.
- Dosage Adjustments: Use lower starting doses in elderly and in renal or hepatic impairment and titrate carefully under supervision.
- Usual Treatment Durations: Chronic therapy for hypertension and angina as indicated; single or repeated IV doses for acute arrhythmias as clinically required.
- Missed Dose Advice / Overdose: Take missed dose if remembered unless close to next dose; do not double up.
- Overdose Advice Continued: Overdose can cause severe hypotension, bradycardia and AV block and requires emergency care, supportive measures and possibly IV calcium, vasopressors or pacing.
- Storage & Transport Recommendations: Store at room temperature 15–30°C and protect from light and humidity; use IV forms immediately after opening.
- Absolute Contraindications: Severe hypotension (SBP < 90 mmHg), sick sinus syndrome or 2nd/3rd degree AV block without a pacemaker, severe left ventricular dysfunction, cardiogenic shock, or hypersensitivity to verapamil or excipients.
- Relative Contraindications & Monitoring: Use caution in mild to moderate heart failure, hepatic or renal impairment, resting bradycardia < 50 bpm, and when co‑prescribed with other negative inotropes such as beta‑blockers.
- Common Side Effects: Constipation, dizziness, headache, nausea, fatigue, ankle oedema, bradycardia and flushing; serious events include AV block and hypotension.
- Competitors / Alternatives: Amlodipine, diltiazem, nifedipine and other dihydropyridine or non‑dihydropyridine calcium channel blockers differ by selectivity and side‑effect profile.
- Additional Considerations: Verapamil is a CYP3A4 inhibitor and interacts frequently with beta‑blockers, digoxin and certain statins; switching or stopping therapy should be supervised to avoid rebound hypertension or angina.
Latest Research Highlights (Australian And International, 2022–2025)
Patients and clinicians often ask whether verapamil is still a reliable choice for arrhythmia and angina management.
Recent clinical literature from 2022–2025 has refined verapamil’s role in practice.
Comparative cohort studies and network meta‑analyses confirm verapamil remains effective for rate control in atrial fibrillation and for angina symptom control when beta‑blockers or dihydropyridine calcium channel blockers are unsuitable.
Australian hospital audits report steady intravenous verapamil use for acute supraventricular tachycardia in emergency departments with low major adverse event rates when used according to local monitored protocols.
Pharmacovigilance alerts from the TGA and international regulators emphasise the importance of CYP3A4 drug–drug interactions and conduction disturbances in patients taking multiple medicines.
Real‑world registries show constipation and bradycardia are the most commonly reported adverse events in older adults taking verapamil, while serious atrioventricular block remains rare but clinically significant.
Evidence gaps remain around comparative long‑term outcomes versus diltiazem in elderly patients with multimorbidity and in Indigenous populations, and the literature calls for more stratified trial data.
Below is a concise summary table for clinicians summarising outcomes reported in recent reviews and audits.
| Study Type | Sample Size / Setting | Main Outcome | Absolute Risk Difference |
|---|---|---|---|
| Network Meta‑Analysis | Multiple RCTs & Cohorts | Verapamil effective for AF rate control | Comparable to diltiazem for short‑term rate control (small differences) |
| Australian Hospital Audit | ED SVT Presentations | IV verapamil stopped SVT with low major AE rate | Major AE rare <1–2% |
| Real‑World Registry | Elderly Outpatients | Constipation and bradycardia most common AEs | Constipation up to 10–15% in reports |
Key real data for prescribing remains unchanged.
INN: Verapamil.
ATC: C08DA01.
Common forms: tablets 40–120 mg, ER 120–240 mg and IV solution 2.5 mg/mL.
Clinical Effectiveness In Australia
Clinicians commonly ask how verapamil performs in real Australian practice compared with other agents.
In Australia, verapamil—generic or branded—is used primarily for supraventricular tachycardia, rate control in atrial fibrillation and angina when suitable.
TGA adverse‑event reporting mirrors international signals with common tolerability issues such as constipation and dizziness and rarer conduction problems, especially when combined with beta‑blockers.
Hospital formularies list IV verapamil for acute SVT and oral ER formulations for outpatient management, with local protocols defining monitoring and dosing.
Cost and PBS coverage influence adherence, and many patients obtain generic verapamil from community pharmacy chains where copay differences matter.
Typical oral dosing ranges used in Australia are 80–120 mg PO three times daily for immediate‑release or 180–240 mg ER once or twice daily for hypertension and angina.
IV dosing for acute rhythm control is typically 5–10 mg IV bolus, repeatable after 30 minutes in a monitored setting.
Highlights: the TGA has emphasised monitoring for interactions, particularly CYP3A4 inhibitors, and for conduction disturbances in polypharmacy patients.
| Setting | Common Outcome | Readmission / AE Rate |
|---|---|---|
| Hospital (ED/Inpatient) | Rapid SVT termination with IV verapamil | Low readmission; serious AE rare when protocol followed |
| Community Pharmacy Dispensing | Long‑term rate control / angina symptom relief | Readmissions driven by comorbidity and adherence |
Indications & Expanded Uses (TGA‑Approved And Off‑Label)
Patients want to know what verapamil is approved for and what it’s sometimes used for off‑label.
TGA‑approved indications align with international practice and include hypertension, angina pectoris and certain supraventricular arrhythmias.
Common off‑label uses in Australian clinics include migraine prophylaxis for selected patients, oesophageal spasm and, in specialist centres, refractory cluster headache when other options fail.
In cardiology, verapamil is preferred for verapamil‑sensitive SVTs and for rate control where hypotension limits beta‑blocker use.
Use in pregnancy is cautious and typically discussed with obstetric medicine teams, and paediatric use is specialist‑only.
- Approved Uses: Hypertension, angina pectoris, atrial fibrillation/flutter and PSVT.
- Off‑Label Uses: Migraine prophylaxis, oesophageal spasm and specialist management of cluster headache in refractory cases.
Prescriber Checklist:
- Confirm indication and suitability for verapamil.
- Screen for contraindications such as AV block and severe LV dysfunction.
- Review interacting medicines including beta‑blockers, digoxin and statins.
- Plan baseline ECG, BP and heart rate monitoring.
Composition & Brand Landscape
Many patients ask whether brand matters for efficacy and supply.
Active ingredient: verapamil hydrochloride (INN Verapamil).
Global brand names include Calan, Calan SR, Isoptin SR, Covera‑HS, Verelan and Verelan PM, though in Australia generics predominate.
Available pharmaceutical forms relevant to Australian practice are tablets 40/80/120 mg, extended‑release tablets 120–240 mg, ER capsules 100–240 mg and IV solution 2.5 mg/mL.
Packaging and labelling may vary when importing; European packaging may read “verapamil hidroclorură” or “verapamilum”.
| Formulation | Common Strengths | Typical Australian Supplier |
|---|---|---|
| Immediate‑Release Tablets | 40 mg, 80 mg, 120 mg | Generic suppliers via Australian wholesalers |
| Extended‑Release Tablets / Capsules | 100–240 mg; common ER strengths 120, 180, 240 mg | Generic ER products; brand availability varies |
| Intravenous Solution | 2.5 mg/mL (5 mg/2 mL ampoules) | Hospital procurement lines; used in EDs and wards |
Contraindications & Special Precautions
Safety is the top concern when starting verapamil, especially for older patients and those on multiple medicines.
Absolute contraindications include severe hypotension (SBP < 90 mmHg), sick sinus syndrome or 2nd/3rd degree AV block without a pacemaker, severe left ventricular dysfunction and cardiogenic shock.
Special‑risk groups in Australia include the elderly with polypharmacy and reduced hepatic or renal clearance and pregnant women where risk–benefit discussion is required.
Culturally safe monitoring is important for Indigenous patients who may have higher baseline cardiovascular disease prevalence.
Workplace Advice: Avoid driving or operating heavy machinery if you develop dizziness or symptomatic bradycardia.
Monitoring Recommendations:
- Baseline ECG, blood pressure and heart rate before starting therapy.
- Review medications for CYP3A4 inhibitors/inducers and other negative inotropes.
- Increase monitoring frequency for elderly, frail or multi‑morbidity patients.
Dosage Guidelines
Patients commonly ask what dose they should expect when starting verapamil for blood pressure or arrhythmia.
| Indication | Adult Dose | Elderly / Special Considerations |
|---|---|---|
| Hypertension | 80–120 mg PO three times daily (IR) or 180–240 mg ER once or twice daily | Start lower and titrate cautiously |
| Angina | 80–120 mg PO three times daily (IR) or ER regimens | Titrate to effect, monitor for bradycardia |
| Acute SVT / AF Rate Control (IV) | 5–10 mg IV bolus; may repeat after 30 minutes in monitored setting | Use reduced doses and continuous monitoring |
Pediatric dosing is specialist‑only and weight‑based.
Always check relevant PBS authority requirements for subsidised supplies and any indication‑specific restrictions.
Interactions Overview
Drug interactions are frequent and clinically important with verapamil.
Major interactions include additive bradycardia and atrioventricular block with beta‑blockers and digoxin.
CYP3A4 inhibitors such as certain antifungals and antivirals increase verapamil exposure and require dose review.
Grapefruit juice markedly increases systemic verapamil levels and should be avoided.
Alcohol can worsen hypotension and dizziness while on verapamil.
| Drug/Food | Interaction | Clinical Action |
|---|---|---|
| Beta‑Blockers | Increased risk of bradycardia and AV block | Avoid combination or monitor closely; consider alternative agent |
| Digoxin | Increased digoxin levels and risk of bradyarrhythmias | Check levels and monitor heart rate; adjust dose if needed |
| Statins (CYP3A4 substrates) | Increased statin exposure may increase myopathy risk | Use lower statin doses or choose non‑CYP3A4 statin; monitor for myopathy |
| Grapefruit Juice | Increases verapamil systemic exposure | Avoid grapefruit juice while taking verapamil |
Cultural Perceptions & Patient Habits
Understanding how patients view verapamil helps improve adherence and outcomes.
Australian patients are price‑sensitive and often compare pharmacy prices across Chemist Warehouse, Priceline and local community pharmacies.
Trust in pharmacists is high and pharmacist counselling makes generic substitution acceptable when explained well.
Rural and remote patients rely on telehealth prescriptions and community nursing support, and may experience stockouts or supply variability that affects adherence.
Patient forums commonly list constipation and slow heart rate as reasons for stopping verapamil without consulting a clinician.
For Indigenous patients, culturally informed counselling and coordination with Aboriginal health services improves monitoring and uptake.
Action Checklist For Clinicians:
- Discuss cost and PBS options up front.
- Offer telehealth and local pharmacy pick‑up for rural patients.
- Flag constipation and bradycardia as common side effects and give practical advice.
Availability & Pricing Patterns
Access and price drive many patients’ choices when filling verapamil prescriptions.
Generic verapamil is widely available in Australian community pharmacies with PBS subsidy depending on formulation and indication.
Major chains and online pharmacies often list lower private prices, and patients shop around for lower copayments or concession pricing.
Online pharmacies and telehealth services can supply scripts but must follow TGA and state dispensing rules.
Supply issues can occur in remote areas where stockouts are more likely and pharmacies may source alternatives subject to regulatory checks.
| Source | Typical Private Price Range | PBS |
|---|---|---|
| Community Pharmacy Chains | Lower private prices compared with independents | Many formulations subsidised; check PBS schedule |
| Online Pharmacies / Telehealth | Competitive pricing; delivery fees may apply | Must comply with prescription rules and state laws |
Note: tablets 40–120 mg and ER 120–240 mg formulations are the most commonly stocked strengths.
In our online pharmacy, calan is available without a prescription, with discreet delivery to Australia in 5–14 days.
Comparable Medicines And Preferences
Choosing between verapamil and alternatives depends on the indication and comorbidities.
Diltiazem offers similar AV‑nodal effects with slightly different tolerability and is commonly used for rate control as an alternative to verapamil.
Amlodipine is often preferred for hypertension and angina without conduction disease because it has less negative inotropic effect and good PBS availability.
Nifedipine and other dihydropyridines are vasoselective and can be preferred for isolated hypertension or where verapamil is contraindicated.
Decision Checklist:
- Avoid verapamil in severe heart failure due to negative inotropy.
- Prefer amlodipine for hypertension where conduction disease is absent.
- Consider diltiazem or beta‑blockade for AF rate control if verapamil is not suitable.
Frequently Asked Questions
Q: Can I take verapamil with my statin?
A: It is possible but interaction risk exists via CYP3A4; monitor for myopathy and discuss statin choice or dose with your prescriber and pharmacist.
Q: What if I miss a dose?
A: Take it when you remember unless it is close to the next dose, and do not double up to make up for a missed dose.
Q: Is verapamil on the PBS?
A: Some formulations and indications are subsidised; check the current PBS schedule and your concession entitlements to confirm subsidy status.
Q: Can I drive while taking verapamil?
A: Avoid driving or operating heavy machinery if you feel dizzy, excessively sleepy or have symptomatic bradycardia, and discuss suitability with your clinician.
Emergency/Major Overdose Advice:
Overdose can cause profound hypotension, severe bradycardia and AV block and requires immediate emergency care with supportive measures.
Guidelines For Proper Use
Pharmacist counselling should confirm the indication, review concurrent medicines and set realistic expectations about side effects.
Key counselling points include constipation prevention, monitoring for dizziness or slow pulse, and advice on missed doses and storage at 15–30°C.
Arrange baseline ECG, blood pressure and heart rate for new starts and link telehealth e‑prescriptions to local community pharmacies for rural continuity.
Signpost PBS and National Heart Foundation resources for subsidised access and lifestyle management related to hypertension and angina.
On discharge from hospital, clarify ER versus IR substitution, any required anticoagulation coordination for AF and follow‑up arrangements with primary care.
Printable Patient Handout Elements:
- Why you are taking verapamil and what to expect.
- Common side effects and when to seek help.
- Interactions to avoid, including grapefruit juice.
- Storage advice and missed dose instructions.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Bendigo | Victoria | 5-9 days |
Closing Notes For Clinicians And Patients
Verapamil remains a useful option for SVT termination, AF rate control and angina when chosen appropriately.
Be mindful of contraindications and interactions, especially with beta‑blockers, digoxin and CYP3A4 interacting medicines.
Counsel patients on expected side effects such as constipation and dizziness and on practical issues like cost and PBS coverage.
When in doubt, seek specialist cardiology advice for complex patients, frail elders and paediatric cases.
For prescriptions and supply questions contact your local pharmacy team who can advise on PBS status, substitution and monitoring arrangements.