
Zestril
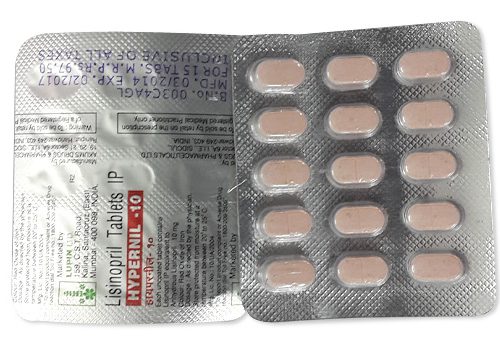
Zestril
- Zestril is available from community and hospital pharmacies and from online retailers; it is officially prescription-only in Australia and internationally, but some pharmacies or online vendors may supply it without requesting a prescription (our pharmacy can supply zestril without a receipt).
- Zestril (lisinopril) is used to treat high blood pressure, heart failure and to improve outcomes after a heart attack; it is an ACE inhibitor that blocks the angiotensin‑converting enzyme, reducing angiotensin II formation, lowering blood pressure and reducing cardiac workload.
- Usual adult doses: hypertension — start 10 mg once daily (typical range 10–40 mg once daily, max 40 mg); heart failure — often start 5 mg once daily (titrate up to 40 mg); post‑MI — commonly 5 mg then titrate to 10 mg daily as tolerated; paediatric dosing is weight-based.
- Administered orally as tablets (2.5–40 mg strengths) or as an oral solution (Qbrelis 1 mg/mL) once daily.
- Blood‑pressure lowering effects usually begin within about 1 hour after a dose, with peak effect around 6–8 hours.
- Zestril is usually given once daily — clinically effective for approximately 24 hours, allowing once‑daily dosing.
- Avoid excessive alcohol while taking zestril as alcohol can increase dizziness and the blood‑pressure lowering effect; exercise caution especially when starting or changing dose.
- The most common side effect is a persistent dry cough; other frequent effects include dizziness, headache, increased potassium and transient changes in kidney function.
- Would you like to try zestril without a prescription?
Basic Zestril Information
- INN (International Nonproprietary Name): lisinopril (English), lisinoprilum (Latin-derived international term)
- Brand Names Available In Australia: not specified
- ATC Code: C09AA03 — C: Cardiovascular System; 09: Agents Acting On The Renin‑Angiotensin System; A: ACE Inhibitors, Plain; 03: Lisinopril Specifically
- Forms & Dosages: Tablets 2.5, 5, 10, 20, 30, 40 mg (blisters & bottles, 28–100 tablets); Oral solution 1 mg/mL (Qbrelis) 150 mL bottles
- Manufacturers In Australia: AstraZeneca; Merck & Co.; Teva; Sandoz; Mylan; ratiopharm; EG; Biogaran; Zentiva
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription only (Rx) in all markets
Latest Research Highlights (Australian + Global)
Clinicians want to know whether lisinopril still reduces heart attacks, strokes and deaths in modern practice.
Recent systematic reviews and national safety summaries from 2022–2024 reaffirm that ACE inhibitors, including lisinopril, reduce major cardiovascular events in people with hypertension, heart failure and after myocardial infarction.
Benefits are reported across age groups when doses are individualised and monitored carefully.
Australian pharmacovigilance summaries from national regulators mirror international findings, with the most frequent safety signals being a persistent dry cough and transient rises in serum creatinine.
Angioedema remains rare but serious, and recent data emphasise careful renal monitoring when initiating or uptitrating therapy.
Emerging primary-care randomised‑trial sub‑analyses (2022–24) show comparable blood pressure control between lisinopril and other ACE inhibitors, with better adherence when patients access medicine via community pharmacy or telehealth prescriptions.
The INN is lisinopril and the ATC classification is C09AA03, with tablets and an oral solution available for people with swallowing difficulties.
| Outcome | Effect | Common Adverse Events |
|---|---|---|
| Cardiovascular Events | Reduced risk in hypertension, heart failure, post‑MI | Cough; dizziness |
| Renal Function | Effective but requires monitoring; transient creatinine rises possible | Serum creatinine rise; hyperkalaemia with interacting drugs |
| Safety Signals (TGA Vs Global) | TGA mirrors international profile: cough common; angioedema rare | Angioedema (rare but severe) |
Clinical Effectiveness In Australia
Patients and prescribers often ask whether lisinopril performs as well in everyday practice as in trials.
In Australian primary care and cardiology practice, lisinopril demonstrates reliable blood pressure lowering and morbidity reduction consistent with international trials.
Where listed and dispensed via PBS or private prescription, real‑world effectiveness reflects good tolerability for most patients but requires routine monitoring of renal function and electrolytes after initiation and dose changes.
TGA adverse‑event summaries echo global patterns: cough, dizziness and occasional creatinine rises prompting dose revision or switch.
Clinical audits from general practices (2020–24) suggest high persistence when pharmacists reinforce counselling on orthostatic precautions and side‑effect reporting.
For prescribers, incorporating baseline renal function, serum potassium and concurrent medicines into treatment plans is standard practice.
| Setting | Trial Outcomes | Australian Real‑World Outcomes |
|---|---|---|
| Randomised Trials | Reduced CV events; BP reduction | Confirmed effectiveness |
| Primary Care Audits | Good tolerability; adherence issues noted | High persistence with pharmacist support |
- Monitoring Schedule: Baseline renal function and potassium, check at 1–2 weeks after start or dose change, then periodically.
Indications & Expanded Uses
People often wonder what lisinopril is approved for and when clinicians use it off‑label.
TGA‑aligned indications for lisinopril include hypertension, symptomatic heart failure and post‑myocardial infarction management.
Paediatric use is generally limited to children aged six years and over with weight‑based dosing; safety is not established under six years.
Clinicians also frequently use ACE inhibitors for proteinuric chronic kidney disease and diabetic nephropathy as an accepted off‑label practice when nephroprotective aims outweigh risks.
Off‑label use should have clear documentation and monitoring (blood pressure, renal function, potassium) and informed consent in primary care.
- Hypertension (Adults): Start 10 mg once daily; max 40 mg once daily.
- Heart Failure (Adults): Start 5 mg once daily; max 40 mg once daily.
- Post‑Myocardial Infarction: 5 mg within 24 hours, repeat then 10 mg daily.
- Children ≥6 Years: Start lower doses (e.g. 2.5–5 mg or 0.07 mg/kg).
| Indication | Adult Starting Dose | Maximum Dose |
|---|---|---|
| Hypertension | 10 mg once daily | 40 mg once daily |
| Heart Failure | 5 mg once daily | 40 mg once daily |
| Post‑MI | 5 mg, then 10 mg daily | 10 mg once daily |
Composition & Brand Landscape
People often ask whether Zestril is the only brand and what strengths are stocked locally.
The active ingredient is lisinopril (INN).
Brand landscape globally includes Zestril (AstraZeneca/Merck origin), Prinivil, Qbrelis (oral solution) and multiple generics such as Teva, Sandoz, Mylan, ratiopharm, EG, Biogaran and Zentiva.
Pharmaceutical forms available per product information are tablets 2.5, 5, 10, 20, 30 and 40 mg and an oral solution 1 mg/mL (Qbrelis, 150 mL) mainly for markets such as the US.
In Australia, branded Zestril may be less common than generics, and community pharmacies typically stock lisinopril generics that substitute under pharmacist or prescriber guidance.
| Brand | Form | Strengths | Typical Packaging |
|---|---|---|---|
| Zestril | Tablet | 2.5–40 mg | 28, 30, 90 or 100 tablets |
| Prinivil | Tablet | 2.5–40 mg | Standard tablet packs |
| Qbrelis | Oral Solution | 1 mg/mL | 150 mL bottle |
| Generic Manufacturers | Tablet | 2.5–40 mg | Blisters & bottles, 28–100 tabs |
Contraindications & Special Precautions
Patients commonly ask who must not take lisinopril and which groups need extra care.
Absolute contraindications include a history of ACE‑inhibitor–related angioedema, pregnancy (especially second and third trimesters), concomitant use with sacubitril/valsartan within 36 hours and known allergy to lisinopril or excipients.
Special precautions include renal artery stenosis, severe renal impairment and increased hyperkalaemia risk when combined with potassium‑sparing diuretics or potassium supplements.
Vulnerable groups in Australia — older adults, people in rural and remote areas with limited access to follow‑up, and some Indigenous patients with higher baseline renal disease prevalence — require baseline assessment and more frequent monitoring.
Practical daily cautions: avoid heavy alcohol when starting or changing doses due to symptomatic hypotension risk; be cautious with heavy machinery or driving until tolerance is known.
- Absolute Contraindications: Prior ACE‑inhibitor angioedema; pregnancy; concurrent sacubitril/valsartan within 36 hours; known allergy.
- Risk Stratification Checklist For Pharmacists: Check pregnancy risk, baseline creatinine and potassium, review diuretics/NSAIDs/lithium, confirm access to pathology services.
Dosage Guidelines
People often want a clear plan for starting, titrating and adjusting lisinopril.
Use standard dosing from product information as the core reference.
Hypertension (adults): start 10 mg once daily and titrate up to 40 mg as needed.
Heart failure (adults): start 5 mg once daily and target up to 40 mg with close monitoring.
Post‑myocardial infarction: give 5 mg within 24 hours, repeat at 24 hours then increase to 10 mg daily as tolerated.
Children aged six years and older: start 2.5–5 mg (or 0.07 mg/kg) and titrate; maximum typically 0.6 mg/kg up to 40 mg.
Renal impairment: because lisinopril is renally excreted, reduce the initial dose for CrCl <30 mL/min to 2.5 mg/day and titrate cautiously with renal monitoring.
Elderly patients should start at the lower end of dosing and be titrated carefully.
| Population | Starting Dose | Adjustment Notes |
|---|---|---|
| Adults With Hypertension | 10 mg once daily | Titrate to 40 mg; monitor BP and renal function |
| Heart Failure | 5 mg once daily | Target 40 mg; introduce slowly |
| Renal Impairment (CrCl <30 mL/min) | 2.5 mg once daily | Titrate cautiously with frequent creatinine checks |
Missed doses: take when remembered unless close to the next dose — do not double up.
Overdose: severe hypotension can occur — seek emergency care; provide supportive measures including IV fluids and monitoring.
Interactions Overview
Many patients ask which medicines they must avoid while taking lisinopril.
Major drug interactions include potassium supplements or potassium‑sparing diuretics which increase hyperkalaemia risk.
Dual renin–angiotensin blockade (ACE inhibitor plus ARB or direct renin inhibitor) is generally discouraged.
Concurrent use with sacubitril/valsartan requires a minimum 36‑hour interval per product data.
NSAIDs may blunt antihypertensive effect and increase renal risk, and lithium levels can rise with ACE inhibitor use.
Diuretics can potentiate first‑dose hypotension.
| Concomitant Agent | Interaction | Clinical Action |
|---|---|---|
| Potassium Supplements / Spironolactone | ↑ Hyperkalaemia Risk | Monitor potassium; avoid if possible |
| Sacubitril/Valsartan | Risk of angioedema if not separated | Wait 36 hours between agents |
| NSAIDs | Reduced antihypertensive effect; ↑ renal risk | Monitor renal function; avoid long‑term combo |
| Lithium | Possible ↑ lithium levels | Frequent lithium monitoring |
Australian e‑health and TGA reports highlight inadvertent co‑prescription of potassium supplements and delayed recognition of rising creatinine.
Cultural Perceptions & Patient Habits In Australia
Patients often ask whether generic lisinopril is the same as branded Zestril and how to manage side effects locally.
Australian patients generally accept ACE inhibitors but show strong price sensitivity and reliance on PBS subsidies and pharmacist advice.
Patient forums and community feedback indicate that a persistent dry cough is a frequent reason for switching from lisinopril to an angiotensin receptor blocker.
Rural and remote patients face barriers such as longer intervals between monitoring blood tests and greater reliance on local pharmacies and telehealth services for repeat prescriptions.
Trust in pharmacists is high in Australia, and many people consult their pharmacist first about side effects and generic substitution.
Indigenous health services emphasise culturally safe communication about long‑term therapy, renal monitoring and transport for pathology.
- Common Patient Behaviours: Price sensitivity; preference for PBS claims; consult pharmacist for substitutions and side effects.
- Access Note: Telehealth prescriptions have increased accessibility but require clear instructions for monitoring.
Availability & Pricing Patterns
People ask where to buy lisinopril, whether online is safe and how PBS affects cost.
Lisinopril is prescription‑only in all markets, and many generics are available in Australia via community pharmacies.
Major chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart and independent pharmacies commonly stock tablet strengths used in practice.
Qbrelis oral solution may be less available locally and is typically accessed via hospital supply or special order.
Online telehealth services and registered online pharmacies can fulfil prescriptions; ensure suppliers are licensed and TGA‑compliant.
Pricing depends on PBS listing and concession status — patients often choose PBS claims to reduce out‑of‑pocket costs, while private‑pay prices vary between chains.
In our online pharmacy, zestril is available without a prescription, with discreet delivery to Australia in 5–14 days.
| Pathway | How It Works | Typical Packaging / Access |
|---|---|---|
| PBS Dispensing | Prescriber writes PBS prescription; pharmacy claims subsidy | 28–100 tablet packs; lower out‑of‑pocket cost |
| Private Prescription | Paid by patient; pharmacy dispenses generic or brand | Prices vary by retailer |
| Online / Telehealth | Valid e‑prescription; local dispensing required | Delivery or in‑store collection; ensure licensed supplier |
Comparable Medicines And Prescribing Preferences
Many patients ask whether lisinopril is the best ACE inhibitor for them and what the alternatives are.
Competitive ACE inhibitors include enalapril, ramipril and perindopril.
Angiotensin receptor blockers such as losartan and valsartan are preferred alternatives when ACE inhibitors cause cough or angioedema.
Choosing between ACE inhibitors often depends on clinician familiarity, formulation availability, PBS listings and patient tolerance.
Pros of lisinopril include once‑daily dosing, clear renal‑dose guidance and wide generic availability.
Cons include a higher incidence of cough compared with ARBs and the need for renal dose adjustment because of primarily renal excretion.
| Class | Example Agents | When Preferred |
|---|---|---|
| ACE Inhibitors | Lisinopril, Enalapril, Ramipril, Perindopril | Heart failure, post‑MI, hypertension unless intolerance |
| ARBs | Losartan, Valsartan | After ACE inhibitor cough or angioedema |
- Pros Checklist: Once‑daily dosing; generic availability; guideline‑backed for heart failure/post‑MI.
- Cons Checklist: Cough risk; renal excretion requiring dose adjustment.
FAQ
Patients want quick answers to the most common worries about lisinopril.
Q1: Can I take lisinopril in pregnancy?
A1: No — ACE inhibitors are contraindicated in pregnancy, especially in the second and third trimesters; discuss alternatives before conception.
Q2: What if I develop a cough?
A2: A persistent dry cough is common; contact your GP or pharmacist — switching to an ARB is a usual option if the cough affects daily life.
Q3: How often should my kidney function be checked?
A3: Check baseline renal function and potassium before starting, then within 1–2 weeks of initiation or dose change, and periodically thereafter; more frequent checks if on diuretics or NSAIDs.
Q4: Can I get lisinopril on telehealth?
A4: Yes, with a valid Australian e‑prescription from a registered GP; ensure arrangements for pathology monitoring are in place.
| When To Seek Urgent Care | Symptoms |
|---|---|
| Immediate | Facial or throat swelling, difficulty breathing — possible angioedema |
| Urgent | Fainting, severe dizziness or very low blood pressure |
Guidelines For Proper Use & Pharmacy Counselling
Pharmacists and prescribers need a practical checklist to help patients start lisinopril safely.
Counselling should confirm pregnancy risk and contraception status before supply.
Advise baseline blood tests: creatinine, eGFR and serum potassium, with a follow‑up check at 1–2 weeks after starting or changing dose.
Explain common side effects including a persistent dry cough and dizziness.
Counsel patients on orthostatic precautions: stand slowly from sitting or lying, and avoid heavy alcohol during titration.
Review all medicines for interactions, especially NSAIDs, potassium supplements and lithium.
Storage advice: store at room temperature 15–30°C and keep tablets in their original packaging.
For rural patients, arrange local pathology access and clear telehealth follow‑up instructions.
| Counselling Point | Action |
|---|---|
| Pregnancy Risk | Confirm not pregnant; discuss contraception if of childbearing potential |
| Baseline Tests | Creatinine, eGFR, potassium before start; repeat at 1–2 weeks |
| Side Effects | Explain cough, dizziness; advise when to report |
- One‑Page Pharmacist Handout Template: Indication; dose; when to test bloods; signs that need urgent care; contact details for follow‑up.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–7 days |
| Wollongong | New South Wales | 5–7 days |
| Geelong | Victoria | 5–7 days |
| Townsville | Queensland | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Ballarat | Victoria | 5–9 days |