
Minipress
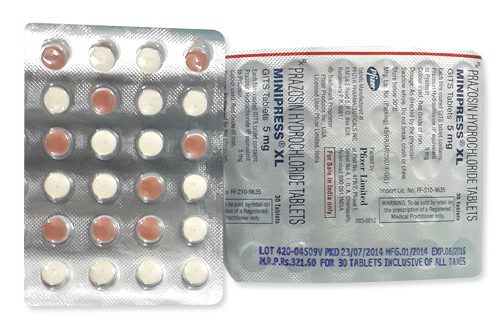
Minipress
- Minipress (prazosin) is normally supplied from pharmacies and is a prescription-only medicine; it should be obtained with a valid prescription. While some online or unregulated sellers may offer it without a prescription, this is not recommended or lawful and may be unsafe.
- Minipress is used primarily to treat hypertension and works as an alpha-1 adrenergic blocker, causing vasodilation and lowering blood pressure; it is also used off‑label for PTSD‑related nightmares in some settings.
- The usual dosing starts at 1 mg orally two to three times a day, with typical maintenance doses of 6–15 mg per day in divided doses and occasional maximum doses up to about 20 mg/day in specialist care.
- Minipress is given orally as capsules or tablets (common strengths include 1, 2 and 5 mg capsules; tablets of 0.5–5 mg may be available depending on country).
- The effect usually begins within about 30–60 minutes of an oral dose, with the marked “first‑dose” fall in blood pressure most likely shortly after initial dosing.
- The duration of action is relatively short—typically around 6–8 hours—so dosing is often required multiple times per day.
- Do not drink alcohol or limit alcohol intake while taking Minipress, as alcohol can increase drowsiness and substantially raise the risk of dizziness and hypotension.
- The most common side effect is dizziness, especially on standing (postural hypotension/first‑dose effect); other frequent effects include headache, drowsiness, nasal congestion, nausea and palpitations.
- Would you like to try minipress without a prescription?

Basic Minipress Information
- INN (International Nonproprietary Name): Prazosin
- Brand Names Available In Australia: not specified
- ATC Code: C02CA01
- Forms & Dosages: Capsules 1 mg, 2 mg, 5 mg; tablets reported in some markets 0.5 mg, 1 mg, 2 mg, 5 mg (availability varies by country)
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription (Rx) Only in all territories
Latest Research Highlights
What Does Recent Evidence Say About Minipress And Modern Uses?
Australian and international summaries through 2024 position prazosin as a legacy alpha‑1 blocker with well‑characterised antihypertensive effects.
Older randomised trials consistently show blood‑pressure lowering versus placebo and other alpha‑blockers, but there are limited large contemporary RCTs assessing long‑term cardiovascular outcomes.
For PTSD‑related nightmares, meta‑analyses report a small to moderate symptomatic benefit in selected cohorts, with significant heterogeneity across trials and mixed results across populations.
Safety signals are predictable and repeatedly noted: a pronounced first‑dose or postural hypotension and dizziness appear across pooled adverse‑event reports.
Australian pharmacovigilance commentary echoes global patterns: postural syncope in older people and interactions with polypharmacy are common themes.
| Outcome | Summary | Study Quality |
|---|---|---|
| Efficacy Vs Placebo | Consistent BP lowering in older trials; mixed evidence for PTSD symptoms | Mostly small to moderate RCTs; few large contemporary outcome trials |
| Safety Events Frequency | Frequent dizziness/orthostatic events; syncope reported in elderly | Pooled safety data; observational/pharmacovigilance reports supplement RCTs |
| Regulatory Signals | TGA trends mirror global reports of falls and interactions in polypharmacy | Case reports and adverse‑event databases; limited population trials |
Key Data Highlights: prazosin (Minipress) is INN C02CA01 and has been manufactured by Pfizer as the reference brand.
Clinical Effectiveness In Australia
Who Gets Minipress In Practice And How Well Does It Work?
Prazosin lowers peripheral vascular resistance and reduces blood pressure in typical dosing ranges.
On the PBS, prazosin is prescribed less often than first‑line ACE inhibitors, ARBs or calcium‑channel blockers for hypertension.
It remains useful for patients intolerant of those first‑line classes, or where clinician preference or comorbidity favour an alpha‑blocker.
Real‑world PBS and TGA signals are used in Australia to monitor both use and harms, with TGA reports emphasising first‑dose hypotension and dizziness in elderly patients and those on multiple antihypertensives.
GP audits and telehealth prescribing trends show clinicians typically start prazosin at a low dose and titrate slowly to reduce syncope risk.
Community pharmacies — including major chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart — play a key role in counselling, checking interactions and monitoring adherence.
| Measure | Observation |
|---|---|
| PBS Dispensed Volume (Relative) | Lower than ACE inhibitors/ARBs and CCBs (less commonly prescribed) |
| TGA‑Reported Events By Age Group | Higher reports of postural syncope and falls in elderly; dizziness across adult groups |
Indications And Expanded Uses
What Is Minipress Approved For And When Is It Used Off‑Label?
Approved Indication: prazosin is approved as an antihypertensive agent under the alpha‑1 adrenergic antagonist class.
Common Off‑Label Uses In Australia: management of PTSD‑related nightmares and sleep disturbances, and occasional symptom relief of lower urinary tract symptoms related to BPH when other agents are unsuitable.
In inpatient settings, prazosin has been trialled for acute hypertensive episodes and autonomic hyperactivity states, always with careful monitoring.
Off‑label use should be documented clearly with informed consent and a risk–benefit discussion recorded in clinical notes.
- Approved Indication: Hypertension (alpha‑1 blocker).
- Common Off‑Label Use: PTSD nightmares, sleep disturbance; selective LUTS symptom relief.
Checklist Before Off‑Label Initiation: document consent, record baseline blood pressure, complete a fall risk assessment and plan close follow‑up monitoring.
Composition And Brand Landscape
What Is In Each Tablet Or Capsule And Which Brands Exist?
Active Ingredient: prazosin, formulated as prazosin hydrochloride in marketed products.
The original reference brand is Minipress (Pfizer), with other international names such as Hypovase and numerous generics in other markets.
Dosage Forms Commonly Encountered: capsules in 1 mg, 2 mg and 5 mg strengths; tablets in 0.5–5 mg ranges vary by country and supplier.
| Brand/Region | Packaging/Strengths | Manufacturer |
|---|---|---|
| United States | Minipress capsules 1 mg, 2 mg, 5 mg | Pfizer |
| UK / Europe | Hypovase tablets (various strengths) | Pfizer |
| India / Other Generics | Multiple tablets and capsules varying strengths | Multiple manufacturers, incl. Pfizer |
Packaging strength highlights to note: 1 mg, 2 mg and 5 mg capsules are the most commonly referenced formats in product information.
Contraindications And Special Precautions
Who Should Be Careful Or Avoid Minipress?
Absolute Contraindications: known hypersensitivity to prazosin or related quinazolines, and prior prazosin‑related syncope or severe postural hypotension.
Use Caution In The Elderly Because Of Increased Fall Risk And Higher Reports Of Syncope.
Exercise Caution In Patients With Angina Or Heart Failure Since Hypotension may precipitate ischaemia.
Severe hepatic impairment warrants dose reduction and careful titration.
Pregnancy And Breastfeeding: avoid unless benefits clearly outweigh risks and specialist input is obtained.
Driving And Work: advise patients about dizziness and drowsiness and recommend avoiding heavy machinery or driving until individual tolerance is established.
- Clinician Checklist: review fall risk, check current antihypertensives, assess liver function, document contraindications.
- Patient Counselling Points: stand up slowly, report dizziness or fainting, avoid alcohol, keep follow‑up BP checks.
Dosage Guidelines
How Is Minipress Usually Dosed For Hypertension And Off‑Label Use?
Standard Initial Dose For Hypertension: 1 mg orally two to three times daily, with cautious titration.
Usual Maintenance Dose Range: approximately 6–15 mg per day in divided doses; rare reports of doses up to 20 mg/day.
Off‑Label PTSD Use: clinicians commonly start at a lower single nightly dose and titrate slowly based on response and tolerability.
| Population | Starting Dose | Titration / Maintenance |
|---|---|---|
| Adults (Hypertension) | 1 mg 2–3×/day | Increase slowly toward 6–15 mg/day divided |
| Elderly | Lower starting dose; consider single daily or split small doses | Titrate slowly with close orthostatic monitoring |
| Hepatic Impairment | Consider lower starting dose | Careful titration and monitoring |
Missed Dose Advice: take when remembered unless close to the next dose; do not double up.
Overdose Management: supportive care for severe hypotension with monitoring of vital signs.
Interactions Overview
Which Medicines And Substances Increase Risk When Taken With Minipress?
Major Interaction Risks Include Additive Hypotension With ACE Inhibitors, ARBs, Diuretics, Beta‑Blockers And Other Vasodilators.
Caution With Nitrates And Other Potent Vasodilators Because Of Risk Of Marked Hypotension.
Alcohol Potentiates Orthostatic Hypotension And Dizziness; CNS Depressants May Enhance Drowsiness.
Food Interactions Are Limited, But High Alcohol Intake Raises Safety Concerns And Large Caffeine Intake Can Mask Symptoms.
E‑health Medication‑Interaction Checks Often Flag Polypharmacy In Older Australians As A High‑Priority Trigger For Review.
| Interaction Class | Practical Advice |
|---|---|
| Other Antihypertensives | Avoid abrupt combined up‑titration; monitor BP closely |
| Nitrates / Potent Vasodilators | Use with caution; consider alternative strategies |
| Alcohol | Advise against or limit due to increased dizziness and orthostatic risk |
Cultural Perceptions And Patient Habits
What Do Australian Patients Usually Ask About Minipress?
Many Australians are price‑sensitive and look to the PBS and trusted community pharmacists for advice, which influences acceptance of older generics such as Minipress.
Rural and remote patients may face access barriers for monitoring, with telehealth e‑prescriptions and local pharmacies helping to bridge gaps.
Patient forums often mention dizziness and fear of falls, which can lead to hesitancy among older people.
Culturally Safe Prescribing For Indigenous Australians Includes Attention To Comorbidities, Access Issues And Family Involvement In Counselling.
- Common Patient Concerns: dizziness on standing, cost, monitoring needs, and interaction with other medicines.
- Urban Vs Rural Access: urban centres typically have faster dispensing and clinic access; rural areas rely more on telehealth and local pharmacy support.
Availability And Pricing Patterns
Where Can You Get Minipress In Australia And What Does It Cost?
Availability: minipress and generic prazosin are prescription‑only and are stocked through authorised wholesalers and community pharmacy chains.
Major retailers such as Chemist Warehouse, Priceline and TerryWhite Chemmart usually stock generics or can order product lines by prescription.
Online pharmacies and telehealth services commonly supply prazosin on e‑prescription, and pharmacists may substitute generics under PBS rules.
Pricing: PBS subsidy status determines patient co‑payment levels; private prescriptions are typically more expensive, with variation by brand and pack size.
In our online pharmacy, minipress is available without a prescription, with discreet delivery to Australia in 5–14 days.
| Prescription Type | Typical Cost Pattern |
|---|---|
| PBS‑Subsidised Script | Lower co‑payment depending on patient status and concession |
| Private Script | Higher out‑of‑pocket cost; varies by brand and pack size |
Comparable Medicines And Preferences
Which Alternatives Should Clinicians Consider Instead Of Minipress?
Comparable Alpha‑Blockers Include Doxazosin (longer‑acting, once‑daily) And Terazosin (also used for BPH).
Alfuzosin is more BPH‑focused and is not typically used for hypertension.
Compared With ACE Inhibitors, ARBs Or Calcium‑Channel Blockers, prazosin is less often chosen first‑line due to orthostatic effects and less robust outcome data.
| Agent | Pros | Cons |
|---|---|---|
| Doxazosin | Once daily dosing | Alpha‑blocker orthostatic risk remains |
| Terazosin | Useful if BPH symptoms coexist | Requires monitoring for hypotension |
| ACE/ARB/CCB | Evidence for CV outcomes and often first‑line | Not suitable for all patients due to tolerability or contraindications |
Choice Considerations: dosing frequency preference, BPH symptom benefit, fall risk in elderly and interaction profile with current medicines.
Frequently Asked Questions
Will Minipress Make Me Dizzy?
Dizziness, particularly on standing or after the first dose, is common.
Start low and rise slowly to reduce risk.
Can I Drink Alcohol On Minipress?
Alcohol can potentiate hypotension and dizziness and should be avoided or minimised while stabilising on prazosin.
Is Minipress On The PBS?
Check current PBS listings for subsidy status, as this affects out‑of‑pocket costs and dispensing choices.
Can Minipress Help PTSD Nightmares?
Some patients report benefit off‑label, but evidence is mixed and specialist review, informed consent and monitoring are advised.
Definitions:
- First‑Dose Phenomenon: a marked drop in blood pressure that can occur with the first dose or when restarting therapy after interruption.
- Off‑Label: use outside the product's approved indications; it requires explicit documentation and consent.
Guidelines For Proper Use
How Should Pharmacists And GPs Counsel Patients Starting Minipress?
Measure baseline supine and standing blood pressure before initiation and during titration.
Emphasise starting low and titrating slowly, with orthostatic precautions such as rising slowly from sitting or lying.
Review the full medication list for additive hypotensive agents and update e‑health medication records.
Schedule follow‑up BP checks in the clinic or community pharmacy and document monitoring plans.
For remote patients, use telehealth plus local pharmacy or nurse monitoring and involve family or carers when fall risk exists.
| Risk Group | Monitoring Interval |
|---|---|
| Low Risk Adults | BP check 1–2 weeks after initiation, then as needed |
| Elderly / Polypharmacy | BP check within 48–72 hours of dose change, then weekly during titration |
| Hepatic Impairment | Frequent clinical review and cautious titration |
Counselling Script (Brief): "Start at 1 mg two or three times a day and rise slowly from sitting or lying. Avoid alcohol while getting used to it, and come back for a BP check within a week or sooner if you feel faint."
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–7 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Albury | New South Wales | 5–9 days |