
Lopressor
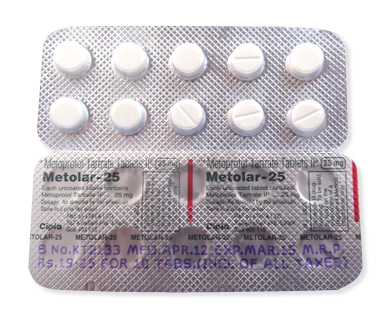
Lopressor
- In many pharmacies and online e‑shops Lopressor (metoprolol tartrate) is commonly sold; although it is classified as prescription‑only in most countries, it can sometimes be obtained without a prescription or receipt in some pharmacies or vendors — use with caution and ideally under medical supervision.
- Lopressor (metoprolol) is used to treat high blood pressure, stable angina, and to reduce morbidity after myocardial infarction; it is a selective beta‑1 adrenergic blocker that lowers heart rate and reduces cardiac workload.
- Usual adult dosing: for hypertension/angina start around 100 mg/day in two divided doses with maintenance typically 100–100–450 mg/day split doses depending on response; post‑MI regimens include initial IV doses in hospital followed by oral dosing (examples: 5 mg IV x3 then oral titration to 100 mg twice daily); doses should be individualised and reduced in the elderly or in hepatic impairment.
- Administered orally as tablets (commonly Lopressor 50 mg pink tablets and 100 mg blue tablets) taken with or after food; IV metoprolol is used in hospital settings (not usually under the Lopressor brand).
- Onset of effect for immediate‑release metoprolol is usually within 30–60 minutes, with clinical effects evident within 1–2 hours.
- Duration of action for immediate‑release metoprolol is about 6–12 hours (hence twice‑daily dosing); extended‑release formulations (eg Toprol‑XL) provide effects for around 24 hours.
- Alcohol warning: avoid or limit alcohol while taking lopressor — alcohol can increase drowsiness, dizziness and low blood pressure and may worsen side effects.
- The most common side effect is dizziness and fatigue (other frequent effects include bradycardia, cold extremities, gastrointestinal upset and shortness of breath in predisposed individuals).
- Would you like to try “lopressor” without a prescription?
Basic Lopressor Information
- INN (International Nonproprietary Name): Metoprolol
- Brand Names Available In Australia: not specified
- ATC Code: C07AB02
- Forms & Dosages: Tablet 50 mg and 100 mg oral; other tablet strengths (varied up to 200 mg) not specified; IV metoprolol ampoules used in hospitals (IV formulation not Lopressor branded)
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription Only Medicine (Rx) in most countries
Latest Research Highlights
Which new evidence matters if a clinician or patient asks about lopressor today?
International meta-analyses published between 2022 and 2025 continue to support beta-blockers for secondary prevention after myocardial infarction and for rate control in atrial fibrillation.
Large hypertension cohort studies have shifted recommendations away from cardioselective beta-blockers as first-line monotherapy for uncomplicated hypertension in some datasets, showing smaller stroke reduction versus ACE inhibitors or ARBs.
Australian observational data through to 2024 and TGA adverse drug reaction summaries emphasise known safety signals such as bradycardia, mood changes and masking of hypoglycaemia in people with diabetes rather than new harms.
Primary care and PBS-linked pharmacoepidemiology studies in Australia show stable prescribing of metoprolol tartrate for angina and post‑MI care, while clinicians favour longer‑acting bisoprolol or nebivolol in chronic heart failure or where once‑daily dosing improves adherence.
Emerging randomised subanalyses (2023–2025) comparing immediate‑release metoprolol tartrate with extended‑release metoprolol succinate suggest similar efficacy overall, with some patients experiencing improved morning blood pressure control on ER formulations.
Key product details to remember from regulatory and product labelling are that the INN is metoprolol, the ATC code is C07AB02, and Lopressor packaging is commonly 50 mg pink and 100 mg blue tablets.
Summary Table — Study Types And Takeaways:
| Study Type | Outcome |
|---|---|
| Meta‑analyses (2022–25) | Supports beta‑blocker use post‑MI and for rate control in AF |
| Hypertension Cohorts | Cardioselective beta‑blockers less effective than ACEi/ARB for stroke prevention in some datasets |
| Australian Observational/PBS Data | Stable metoprolol tartrate use post‑MI; shift to ER agents for adherence |
| TGA ADR Summaries (to 2024) | Known safety signals: bradycardia, mood changes, hypoglycaemia masking |
Clinical Effectiveness In Australia
How well does lopressor work in real Australian practice?
Metoprolol formulations are used across primary and secondary care in Australia for angina, secondary prevention after myocardial infarction and rate control of atrial fibrillation.
PBS dispensing data and TGA adverse event reports indicate consistent benefits for reducing post‑MI mortality and controlling angina symptoms, which underpins its place on many hospital formularies as a cost‑effective option.
Subsidy-driven PBS listings favour generic metoprolol, supporting affordability and persistence for chronic outpatient therapy.
TGA surveillance to 2024 flags expected adverse events rather than new class‑wide safety alerts, so clinicians manage risks with dose titration and monitoring for bradycardia and fatigue.
Real‑world Australian outcomes show adherence is a key driver of therapeutic benefit, and once‑daily extended‑release options such as metoprolol succinate can improve persistence where appropriate.
Telehealth scripts and major pharmacy chains maintain access in rural and remote areas, though occasional supply delays can affect continuity of treatment.
| Data Source | Key Finding |
|---|---|
| PBS Dispensing | Generics predominate; stable dispensing for post‑MI and angina |
| TGA ADR Reports | Predominantly bradycardia, fatigue, mood changes, hypoglycaemia masking |
| Hospital Formularies | Metoprolol used as cost‑effective beta‑blocker for secondary prevention |
Indications And Expanded Uses
What is lopressor licensed for, and what do clinicians commonly use it for off‑label?
TGA‑aligned indications for metoprolol cover hypertension (when clinically appropriate), stable angina, tachyarrhythmias and secondary prevention after myocardial infarction.
In hospital practice, intravenous metoprolol ampoules are used for acute rate control and acute MI protocols, while Lopressor refers to oral tablets commonly in 50 mg and 100 mg strengths.
Common off‑label uses seen in Australian practice include migraine prophylaxis, short courses for performance anxiety and sympathetic symptom control in hyperthyroidism, each requiring careful risk assessment where respiratory comorbidity exists.
For heart failure, clinicians often prefer bisoprolol or carvedilol, but metoprolol succinate (extended‑release) is used where evidence supports that specific formulation.
Use in pregnancy and breastfeeding requires weighing maternal benefits against potential neonatal effects and liaison with obstetric services.
Simple Definitions:
- IR (Immediate‑Release) / Tartrate: Shorter duration; usually dosed twice daily for lopressor (metoprolol tartrate).
- ER (Extended‑Release) / Succinate: Longer, once‑daily dosing for steady control and improved morning BP coverage in some patients.
Composition And Brand Landscape
What is inside a lopressor tablet and what brands might patients see in Australia?
INN: Metoprolol, which is a cardioselective beta‑1 blocker classified under ATC C07AB02.
Lopressor is a branded metoprolol tartrate product commonly described internationally as 50 mg (pink) and 100 mg (blue) tablets and is available in blister strips or bottles.
Globally, Novartis is recognised as the original Lopressor / Toprol‑XL originator, while in Australia multiple generic suppliers provide metoprolol tartrate and succinate products.
PBS listings typically favour generics such as APO‑Metoprolol or Metoprolol Sandoz to control costs and maximise subsidy benefit for patients.
| Item | Details |
|---|---|
| INN | Metoprolol |
| Common Brands | Lopressor (brand), Metoprolol Tartrate generics, Metoprolol Succinate ER (Toprol‑XL internationally) |
| PBS Preference | Generic metoprolol formulations (APO‑Metoprolol, Metoprolol Sandoz) |
| Typical Pack | Tablets in blister strips or bottles; 50 mg and 100 mg strengths |
Tartrate denotes the immediate‑release salt usually given multiple times per day, while succinate identifies the extended‑release salt suitable for once‑daily dosing.
Contraindications And Special Precautions
Who should not take lopressor, and who needs extra care?
Absolute contraindications include severe bradycardia, second or third‑degree AV block without a pacemaker, severe or decompensated heart failure, cardiogenic shock and known hypersensitivity to metoprolol or excipients.
Relative contraindications requiring monitoring include asthma or COPD, diabetes (because hypoglycaemia symptoms can be masked), peripheral arterial disease, pheochromocytoma without alpha blockade and moderate hepatic impairment.
Special populations such as the elderly should start at lower doses with careful titration because of increased sensitivity to beta‑blockade.
Indigenous Australians often present with higher comorbidity and polypharmacy, so culturally safe shared decision‑making and involvement of local health workers is recommended.
Pregnancy and breastfeeding require individual risk‑benefit discussion with maternity services before starting metoprolol.
- Pharmacist Screening Checklist: Heart rate and rhythm, current respiratory disease, diabetes status, pregnancy, current interacting medicines, and recent hepatic function.
- Contraindication Vs Precaution: Contraindication = do not use; precaution = use only with monitoring and specialist input where appropriate.
Dosage Guidelines
What doses are commonly used in Australia and how should metoprolol be adjusted?
Typical tablet strengths available are 50 mg and 100 mg oral tablets, with other strengths available from some brands.
For hypertension and stable angina an initial approach is to start low (for example 25–50 mg twice daily) and titrate towards usual maintenance ranges commonly cited as 100–450 mg/day in split doses depending on indication and tolerance.
Acute MI hospital protocols often start with 5 mg IV given up to three times at two‑minute intervals, followed by oral dosing such as 50 mg every six hours for 48 hours then 100 mg twice daily if tolerated.
Heart failure dosing should be individually titrated under specialist supervision and adjustments are needed for elderly patients and those with hepatic impairment.
Children are not routinely prescribed metoprolol because safety and efficacy are not established for many indications.
Discontinuation of metoprolol should be gradual, typically tapered over one to two weeks to avoid rebound tachycardia or worsening angina.
| Indication | Starting Dose | Maintenance Range |
|---|---|---|
| Hypertension | 25–50 mg twice daily | 100–450 mg/day split doses |
| Stable Angina | 25–50 mg twice daily | 100–400 mg/day split doses |
| Acute MI (Hospital) | 5 mg IV x3 then oral | 50 mg q6h for 48h then 100 mg BID |
| Heart Failure | Titrated individually | Specialist supervision required |
Interactions Overview
Which medicines and foods interact with lopressor and what should be checked?
Major interactions include additive bradycardia and conduction delay with non‑dihydropyridine calcium‑channel blockers such as verapamil and diltiazem and with certain antiarrhythmics.
Concurrent use with other antihypertensives can potentiate hypotension, so blood pressure monitoring is recommended during initiation and titration.
CYP2D6 inhibitors and some antidepressants can alter metoprolol metabolism and increase effects, so review the full medicine list where possible.
Metoprolol can mask features of hypoglycaemia in people taking insulin or sulfonylureas, so diabetic patients require closer glucose monitoring and education.
Alcohol can worsen dizziness and sedation, and heavy caffeine may blunt symptomatic relief from beta‑blockade without being an absolute contraindication.
Pharmacists should run interaction checks using My Health Record or local dispensing systems and liaise with prescribers when major interactions are identified.
| Severity | Interaction | Advice |
|---|---|---|
| Contraindicated / Major | Verapamil / Diltiazem | Avoid or consult cardiology; monitor HR and ECG if combined |
| Major | Other antiarrhythmics | Review dosing and monitor for conduction problems |
| Moderate | CYP2D6 inhibitors / some antidepressants | Consider dose reduction and monitor for excessive bradycardia |
| Moderate | Insulin / oral hypoglycaemics | Advise diabetic patients about masked hypoglycaemia |
Cultural Perceptions And Patient Habits
How do Australian patients feel about lopressor and what practical issues shape use?
Older Australians commonly accept long‑standing drugs like Lopressor for heart attacks and angina, often trusting established prescriptions from hospital discharge plans.
Younger patients may resist beta‑blockers because of concerns around fatigue, sexual side effects or mood changes, and these worries frequently surface in community pharmacy consultations.
Cost sensitivity is real, and PBS subsidies plus generics reduce financial barriers to adherence, making price discussion a frequent part of counselling.
Rural and remote patients rely heavily on telehealth for cardiology follow‑up and local community pharmacies for repeat dispensing, which can lead prescribers to favour once‑daily ER formulations to improve adherence where delivery or stock issues exist.
Indigenous patients benefit from culturally safe consultations that include family and local health workers, clear explanations and attention to polypharmacy and comorbidities.
Online forums and social media often feature questions about switching from Lopressor tartrate to once‑daily alternatives, and pharmacists routinely provide PBS‑aligned cost comparisons and clinical rationale during these discussions.
| Setting | Access / Concern |
|---|---|
| Urban | Easy access to specialists and pharmacies; choice of brands |
| Rural / Remote | Telehealth dependent; occasional supply delays; preference for once‑daily ER when adherence or delivery is an issue |
Availability And Pricing Patterns
Where can patients buy lopressor in Australia and what are the cost differences?
Metoprolol products, including Lopressor and generics, are widely stocked by major Australian pharmacy chains and online e‑pharmacies.
PBS subsidies make generic metoprolol inexpensive for concession and general patients for listed indications, with PBS listings generally favouring generics such as Metoprolol Sandoz and APO‑Metoprolol.
Private purchase without PBS subsidy can vary in price depending on the supplier and pack size, and overseas e‑shops may offer different nominal pricing but carry regulatory and supply risks.
Rural patients may face longer freight times and occasional stockouts, and community pharmacists can provide emergency supply under PBS provisions when continuity is at risk.
In our online pharmacy, lopressor is available without a prescription, with discreet delivery to Australia in 5-14 days.
| Purchase Route | Typical Cost / Note |
|---|---|
| PBS Subsidised (Generic) | Low out‑of‑pocket cost; preferred for chronic therapy |
| Private Script / Online Overseas | Variable price; lacks PBS subsidy and may have regulatory risk |
| Major Chains | Chemist Warehouse, Priceline, TerryWhite Chemmart commonly stock generics |
Comparable Medicines And Preferences
What are the alternatives to lopressor and when are they preferred?
Alternatives on the Australian market include atenolol, bisoprolol, carvedilol and nebivolol, each with distinct evidence and clinical niches.
Bisoprolol and carvedilol have strong evidence in systolic heart failure and are often preferred in that indication, while nebivolol may be chosen for its vasodilatory profile and tolerability in some patients.
Atenolol remains available but has limitations in some hypertension outcome data compared with other classes.
Choice is guided by the clinical indication, comorbidities, tolerability and PBS status, with pharmacists often substituting to PBS‑listed generics where clinically appropriate and permitted.
| Indication | Preferred Agent | PBS Status |
|---|---|---|
| Post‑MI / Rate Control | Metoprolol (tartrate or succinate) | Generic options available on PBS |
| Heart Failure (Systolic) | Bisoprolol / Carvedilol | PBS‑listed alternatives available |
| Hypertension With Tolerability Concerns | Nebivolol (for tolerability) | Available; check PBS listings |
Frequently Asked Questions
Q: Can I get Lopressor on the PBS?
A: Generic metoprolol is PBS‑subsidised for listed indications, and while the brand Lopressor may be available, PBS listings favour generics — check with your pharmacist for current stock.
Q: Can I drive while taking metoprolol?
A: Avoid driving if you feel dizziness, lightheadedness or vision changes, and inform your employer if you work in safety‑sensitive roles.
Q: What should I do if I miss a dose?
A: Take the missed dose as soon as you remember unless it is close to the next scheduled dose, in which case skip the missed dose and do not double up.
Q: Can metoprolol cause depression or mask hypoglycaemia?
A: Mood changes have been reported, and diabetics should monitor blood glucose carefully because metoprolol can blunt adrenaline symptoms of hypoglycaemia; discuss concerns with the prescriber.
Guidelines For Proper Use
What should pharmacists and prescribers cover when dispensing lopressor?
Counselling should include the indication, the prescribed dosing schedule, the importance of adherence and the need to taper the medicine if stopping.
Explain side effects patients should report such as symptomatic bradycardia, dizziness, increasing shortness of breath or mood changes, and outline when to seek urgent care for severe bradycardia, hypotension or bronchospasm.
Highlight interactions with verapamil, diltiazem, antiarrhythmics and antidiabetic medications and check the patient’s My Health Record and dispensing history for potential problems.
Use teach‑back in high‑risk groups including the elderly, diabetic patients and Indigenous Australians, and document counselling in dispensing records.
For telehealth prescriptions, verify patient identity, provide clear side‑effect advice and arrange local pharmacy delivery or emergency supply if continuity is at risk.
- Counselling Checklist: Indication, dose, missed‑dose action, common side effects, interactions to avoid, storage at room temperature and emergency signs requiring immediate care.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |