
Naltrexone
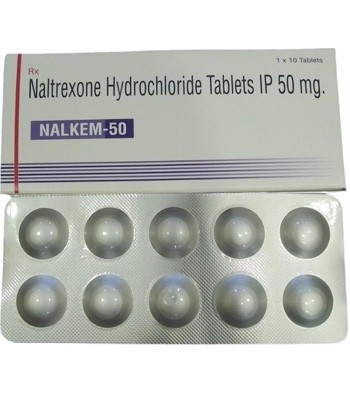
Naltrexone
- In our pharmacy, you can buy naltrexone without a prescription, with discreet delivery across Australia. It is also registered in Australia as Naltrexone GH.
- Naltrexone is used for opioid dependence after detoxification and for alcohol dependence. It works as an opioid receptor antagonist, blocking opioid effects and helping reduce cravings and relapse risk.
- The usual oral dose is 25 mg as a test dose, then 50 mg daily; in some cases it may be given as 100 mg three times weekly or 150 mg on Fridays. For extended-release injection, the usual dose is 380 mg intramuscularly every 4 weeks.
- The form of administration is a tablet by mouth, or a long-acting injectable depot form given by intramuscular injection.
- The effect usually starts within 1 to 2 hours after an oral dose. The injectable form provides a sustained effect over several weeks.
- The duration of action is about 24 hours for the oral tablet, while the extended-release injection lasts around 4 weeks.
- Alcohol should be avoided or strictly limited, especially if naltrexone is being used for alcohol dependence, and you should not take it if you are currently opioid-dependent or using opioids, as it can trigger withdrawal.
- The most common side effects are nausea, headache, dizziness, abdominal pain, insomnia, anxiety, and sometimes increased liver enzymes; injection-site reactions may occur with the depot form.
- Would you like to try naltrexone without a prescription?
Latest Research Highlights: What Australian And Global Evidence Says About Naltrexone
Basic Naltrexone Information
- INN (International Nonproprietary Name): Naltrexone
- Brand names available in Australia: Naltrexone GH
- ATC Code: N07BB04
- Forms & dosages: Tablet (oral) 25 mg, 50 mg, 100 mg; extended-release injection 380 mg per vial (monthly IM)
- Manufacturers in Australia: Generic Health
- Registration status in Australia: Registered as Naltrexone GH, Rx
- OTC / Rx classification: Prescription Only (Rx)
| Study Type | Population | Outcome | Safety Signal |
|---|---|---|---|
| Australian service data and GP-led follow-up | People treated for alcohol dependence and opioid relapse prevention after detoxification | Better results when prescribing is paired with counselling, telehealth review, and pharmacy follow-up | Adherence problems remain common; liver monitoring is part of routine care |
| International reviews and placebo-controlled trials | Adults with alcohol dependence | Oral naltrexone reduced cravings and relapse risk versus placebo | Nausea caused some discontinuation, especially early in treatment |
| International opioid relapse prevention studies | Adults after detoxification | Reduced opioid return to use when taken consistently | Safety depends on confirming the patient is opioid-free before starting |
| Low-dose naltrexone reports | Chronic pain, fatigue, and autoimmune conditions | Interest continues, but evidence is weaker than for standard-dose naltrexone | Not the same as dependence treatment; clinical caution remains appropriate |
What does the latest evidence actually mean for someone standing in a pharmacy on a Friday afternoon asking, “Will this help me stay on track?”
Across 2022 to 2025, the strongest support remains for oral naltrexone hydrochloride in alcohol dependence and opioid relapse prevention after detoxification.
Australian real-world use is still shaped by access to alcohol and drug services, GP-led care, telehealth follow-up, and whether the local pharmacy has stock on hand.
That matters because naltrexone works best as an evidence-backed treatment when people can keep taking it, attend reviews, and get practical counselling along the way.
For Australian patients, PBS-relevant access in practice can depend on the prescriber, the indication, and local supply arrangements, even when the medicine is clinically appropriate.
Internationally, oral naltrexone has clearer evidence than low-dose naltrexone, particularly for reducing alcohol use and lowering opioid relapse risk compared with placebo.
The main safety themes in the newer data are familiar: nausea early on, liver monitoring concerns in people with risk factors, and treatment stops when side effects become too much.
Clinical Effectiveness In Australia: How Naltrexone Performs In PBS-Linked And Monitored Care
Why does one person do well on naltrexone and another quietly stop after two weeks?
In Australian practice, the answer is usually adherence, not the medicine itself.
Naltrexone is used after detoxification for opioid relapse prevention and for alcohol dependence where the goal is alcohol harm reduction and fewer cravings.
Its TGA registration supports prescription use, while PBS access and private pricing can influence how often it is started and continued.
That is especially relevant in metro areas, where repeat scripts are often easier to organise, and in rural communities, where telehealth, local GP clinics, and community pharmacy dispensing may carry more of the load.
What tends to improve outcomes:
- Daily adherence to the naltrexone 50 mg tablet or supervised schedules.
- Regular pharmacist counselling and GP review.
- Psychosocial support alongside medicine, not instead of it.
- Supervised dosing where that suits the patient’s routine.
- Routine liver function tests in people who need monitoring.
It is worth being clear that naltrexone reduces cravings and relapse risk, but it is not a stand-alone cure.
Patients do best when the medicine is part of a broader plan that feels realistic, affordable, and easy to keep up.
Indications And Expanded Uses: Approved Uses, Off-Label Interest, And Where Australian Practice Differs
People often ask whether naltrexone is “for drinking” or “for opioids”, and the short answer is both.
The approved role covers opioid dependence after detoxification and alcohol dependence, with naltrexone hydrochloride tablets used as a prescription only medicine under ATC code N07BB04.
- Approved use
- Treatment of alcohol dependence and relapse prevention in opioid dependence after detoxification.
- Off-label use
- Low-dose naltrexone is discussed for chronic pain, autoimmune conditions, and fatigue syndromes, but it is not the same as standard-dose dependence treatment.
That distinction matters.
Low-dose naltrexone is often mentioned in online forums, but evidence is much less robust than for standard oral dosing used in alcohol dependence and opioid relapse prevention.
Australian clinicians generally stay evidence-led and cautious, especially when patients have liver issues, polypharmacy, or a history of unstable follow-up.
Many people seek naltrexone tablets because they want a non-opioid addiction treatment, prefer to avoid aversive alcohol therapy, or simply want a once-daily oral option that fits work and family life.
Composition And Brand Landscape: Tablets, Injection, And Australian Supply Realities
Which version of naltrexone will a patient actually see at the counter?
In Australia, brand familiarity is limited compared with common chronic medicines, so counselling matters.
| Formulation | Strength | Common Use |
|---|---|---|
| Oral tablets | 25 mg, 50 mg, 100 mg | Alcohol dependence and opioid relapse prevention after detoxification |
| Extended-release injection | 380 mg monthly IM | International depot option for relapse prevention |
| Compounded oral solution | Not specified | Less common in commercial packaging |
The Australian brand most people encounter is Naltrexone GH, while overseas patients may recognise Revia tablets or Vivitrol injection.
Because supply can vary by wholesaler and ordering cycle, small independent pharmacies and rural dispensaries may need to order ahead.
Tablets should be stored at room temperature, protected from moisture, while injectable products follow label-specific cold-chain requirements.
For patients ordering through an online pharmacy, the usual goal is discreet, reliable fulfilment with clear pharmacist support when questions come up.
Contraindications And Special Precautions: Who Should Avoid Naltrexone Or Be Monitored Closely
Before starting, the most important question is simple: is the patient truly opioid-free?
If not, naltrexone can trigger acute withdrawal, and that is the last thing anyone wants.
| Absolute Contraindications | Relative Precautions |
|---|---|
| Current physiologic opioid dependence | Hepatic impairment or liver disease |
| Positive opioid urine test before starting | Severe renal impairment |
| Acute hepatitis or liver failure | Pregnancy and lactation |
| Known hypersensitivity to naltrexone or excipients | Concomitant hepatotoxic medicines |
Australian patients with liver disease, severe renal impairment, pregnancy, or multiple medicines may need closer review before naltrexone is prescribed.
Older adults usually do not need an automatic dose change, but comorbid organ impairment changes the picture.
Aboriginal and Torres Strait Islander patients may face extra barriers to continuity of care, so monitoring plans should be local, practical, and respectful.
Everyday safety also matters.
Dizziness and insomnia can happen, so people should talk through driving, machinery, and workplace safety with their prescriber if symptoms appear.
Dosage Guidelines: Australian-Standard Regimens And Adjustment Considerations
How is naltrexone usually started in real life?
For opioid dependence after detoxification, treatment often begins with a 25 mg test dose, then 50 mg daily.
For alcohol dependence, the usual dose is 50 mg daily.
| Indication | Starting Dose | Maintenance Dose | Typical Duration |
|---|---|---|---|
| Opioid dependence after detoxification | 25 mg test dose | 50 mg daily, or supervised 100 mg Monday/Wednesday/Friday, or 150 mg Friday | 12+ weeks per guidelines |
| Alcohol dependence | 50 mg daily | 50 mg daily | At least 3 to 6 months, longer if needed |
| Monthly depot option | 380 mg IM | 380 mg IM every 4 weeks | Per product schedule |
Children under 18 are generally not recommended because safety and efficacy are not established.
Older adults usually need no routine change unless organ impairment is present.
In hepatic impairment, careful monitoring matters more than routine dose reduction, and severe renal impairment also calls for closer follow-up.
In Australia, prescribing decisions often depend on GP follow-up, access to pathology, and whether the patient is using a subsidised pathway or paying privately.
Interactions Overview: Alcohol, Opioids, Medicines, And Practical Everyday Issues
What is the big interaction concern with naltrexone?
It is opioids.
Naltrexone is an opioid antagonist, so it blocks opioid receptors and can precipitate withdrawal if opioids are still present.
It also creates a different risk if someone tries to override the blockade by taking more opioids, because overdose can occur once the blockade wears off.
- Tell the prescriber about any opioid pain medicine, cough mixture, or codeine-containing product.
- Tell the prescriber about medicines that can affect the liver, especially if several are used together.
- Report all prescribed and over-the-counter medicines during a medicines review.
- Alcohol itself is not the pharmacological problem here; it is the condition being treated.
Australian e-health alerts and dispensing systems help flag risks, especially in people with polypharmacy.
Coffee and food are not major interaction issues, although nausea or abdominal upset can make tolerance harder in the first few days.
Cultural Perceptions And Patient Habits In Australia: What Drives Acceptance, Hesitation, And Persistence
Why do some Australians start treatment quickly while others put it off for months?
Often it comes down to stigma, cost pressure, work schedules, and whether the treatment feels discreet enough.
Many people prefer to ask a pharmacist first, especially when they are comparing prices or checking how repeat dispensing works.
Trust in community pharmacy is high, and shoppers commonly look to Chemist Warehouse, Priceline, and TerryWhite Chemmart for straightforward pharmacist advice.
Some patients prefer oral tablets because they feel less medicalised, while others value the convenience of monthly dosing where injectable treatment is available.
Rural and remote patients can face longer travel, fewer prescribers, and weaker continuity, which is why telehealth prescriptions and e-scripts matter so much.
Common reasons people hesitate:
- Shame or fear of being judged.
- Worry about side effects, especially nausea.
- Concerns about cost and repeat access.
- Family or work pressure.
A calm, non-judgemental conversation usually helps more than pushing hard.
Availability And Pricing Patterns: Pharmacies, Online Ordering, PBS Reliance, And Access Gaps
How easy is it to get naltrexone in Australia?
That depends on the PBS subsidy pathway, private pricing, and whether the local pharmacy has stock available.
| Access Channel | Typical Benefit | Common Limitation |
|---|---|---|
| Community pharmacy | Face-to-face pharmacist counselling and repeat dispensing | Stock can vary by wholesaler and ordering cycle |
| Major pharmacy chains | Broad reach and easier price comparison | Local availability still changes by store |
| Online pharmacy | Convenient e-script fulfilment to metro and regional areas | Requires valid prescription and follow-up |
| Telehealth-linked prescribing | Improves access for rural patients and repeat scripts | Assessment and ongoing review still need to be proper |
Patients often search by the generic name naltrexone hydrochloride or by Naltrexone GH when looking for supply options.
In our online pharmacy, naltrexone is available without a prescription, with discreet delivery to Australia in 5-14 days.
That said, prescribers still need to assess suitability, especially for opioid-free status and liver health, before treatment starts.
Price sensitivity is a major issue in Australia, particularly for longer courses where private costs can add up.
Comparable Medicines And Preferences: What Australians May Choose Instead Of Naltrexone
Sometimes naltrexone is not the best fit, even when the diagnosis is right.
The main alternatives are acamprosate, disulfiram, nalmefene overseas, and for opioid dependence, methadone or buprenorphine.
| Medicine | Main Role | Key Difference |
|---|---|---|
| Acamprosate | Alcohol abstinence support | Supports abstinence rather than blocking opioids |
| Disulfiram | Alcohol aversion therapy | Creates a deterrent effect rather than reducing cravings directly |
| Nalmefene | Alcohol dependence option in Europe | Not the usual Australian pathway |
| Methadone or buprenorphine | Opioid dependence treatment | Different mechanism and service model |
Naltrexone suits people who want a once-daily tablet, want to avoid sedating medicines, or have not done well with other options.
It may be less suitable when liver monitoring is difficult, when adherence is poor, or when opioid analgesia is likely to be needed soon.
Frequently Asked Questions
How long does naltrexone take to work?
Some people notice reduced cravings within days, but the full benefit usually builds over days to weeks with regular use.
Can I drink alcohol while taking naltrexone?
Naltrexone is used to help with alcohol dependence, so it is not a medicine that relies on aversion, but drinking goals should still be discussed with the prescriber.
What happens if I need pain relief or surgery?
Opioid pain relief needs clinician coordination because naltrexone blocks opioid receptors.
Is naltrexone on the PBS or only private?
Access depends on the product, script type, and subsidy rules, so the prescriber and pharmacist need to check the current pathway.
Guidelines For Proper Use: Australian Counselling, Monitoring, And Follow-Up Habits
How do pharmacists and prescribers usually keep treatment on track?
They start by confirming the patient is opioid-free, then explain side effects, review liver health, and make sure follow-up is realistic.
Australian counselling usually lines up with PBS expectations and national guidance, with practical monitoring through GP visits, pathology, and pharmacy check-ins.
- Confirm opioid-free status before the first dose.
- Take the medicine exactly as prescribed, usually daily.
- Keep liver function tests and follow-up appointments on time.
- Tell every clinician and pharmacist that naltrexone is being used.
- Store tablets at room temperature and protect them from moisture.
If an oral dose is missed, take it as soon as remembered unless it is close to the next dose, and do not double up.
For depot treatment, appointment timing matters because continuity is tied to outcome.
Get urgent medical help for jaundice, severe abdominal pain, or suspected opioid exposure.
Missed doses and self-adjusted dosing are common reasons treatment falls apart, so simple routines make a real difference.
Delivery Across Australia
| City | Region | Delivery time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Toowoomba | Queensland | 5-9 days |
| Bendigo | Victoria | 5-9 days |
Naltrexone works best when the medicine, the follow-up, and the patient’s routine all line up.
For Australians looking for a discreet, evidence-led option, oral naltrexone remains a practical choice when it is prescribed carefully and monitored properly.