
Conjugated Estrogens
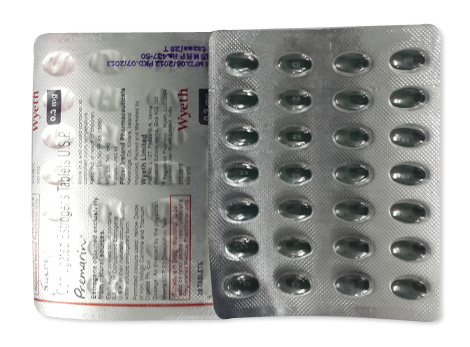
Conjugated Estrogens
- In Australia and most countries conjugated estrogens are a prescription-only medicine (Rx) and are registered (e.g. Premarin®); however, some pharmacies or online suppliers may supply products without asking for a prescription—this is not recommended and you should check local regulations and consult a clinician before purchase.
- Conjugated estrogens are used for menopausal vasomotor symptoms, vulvovaginal atrophy, hypoestrogenism (e.g. ovarian failure) and for postmenopausal osteoporosis prevention; they provide systemic oestrogenic activity by supplying a mixture of oestrogenic sulphate esters (e.g. estrone sulphate, equilin) that are converted to active oestrogens and act at oestrogen receptors (ERα/ERβ) to modulate gene transcription.
- Typical oral starting doses for menopausal symptoms are 0.3–0.625 mg once daily (tablets), with maintenance titration to the lowest effective dose up to 1.25–2.5 mg if needed; vaginal cream is usually 0.5–2 g (≈0.3–1.25 mg equivalent) with common regimens of daily use for up to 21 days then intermittent use or as directed by a clinician.
- Forms of administration include oral tablets (commonly 0.3 mg, 0.625 mg, 1.25 mg), vaginal cream (0.625 mg/g in 27–28 g tubes) and rarely injections; combination products with a progestogen are used when an intact uterus is present.
- Onset of symptomatic relief: vasomotor symptoms often begin to improve within 1–2 weeks with more noticeable benefit by 4–8 weeks; local vaginal symptoms may start to improve within days to a few weeks.
- Duration of action is dependent on daily dosing (once-daily regimens are standard); symptom control persists only while treatment continues and therapy should be reviewed regularly (typically every 3–6 months) to use the lowest effective dose.
- Alcohol warning: avoid excessive alcohol while taking oestrogens — heavy drinking can worsen liver stress and may increase vascular risks; discuss moderate alcohol use with your prescriber and do not combine heavy alcohol intake with oestrogen therapy.
- The most common side effects are breast tenderness or pain, headache, nausea, bloating/abdominal cramps and vaginal spotting or discharge; more serious risks include thromboembolism and, rarely, cholestatic jaundice or severe hypertension.
- Would you like to try conjugated estrogens without a prescription?


Basic Conjugated Estrogens Information
-
INN (International Nonproprietary Name):
Conjugated estrogens.
Also formally referenced as conjugated equine estrogens (CEE) because the product historically contains oestrogens derived from the urine of pregnant mares.
-
Brand Names Available In Australia:
Premarin® and Premia® are listed as brands in Australia.
Premarin is commonly supplied as tablets and a vaginal cream in markets where registered.
-
ATC Code:
G03CA57.
This falls under natural and semisynthetic oestrogens, plain.
-
Forms & Dosages:
Oral tablets: 0.3 mg, 0.625 mg, 0.9 mg, 1.25 mg and 2.5 mg in common markets.
Vaginal cream: 0.625 mg/g, typically in 27–28 g tubes.
Most common packaging includes blister packs of 28 or 84 tablets and 27.5–28 g cream tubes.
-
Manufacturers In Australia:
Pfizer (originally Wyeth) is the major global manufacturer and supplier linked to Premarin®.
Generics and regional suppliers may supply conjugated estrogens to the Australian market under license.
-
Registration Status In Australia:
Conjugated estrogens are registered with the Therapeutic Goods Administration (TGA).
Products such as Premarin® and Premia® are the registered brand entries referenced for Australia.
-
OTC / Rx Classification:
Prescription-only (Rx).
Conjugated estrogens are not available over the counter in the countries surveyed and are supplied by prescription in Australia.
Latest Research Highlights
Worried about whether conjugated oestrogens still work and whether they are safe?
Recent systematic reviews and pooled analyses published between 2022 and 2025 show that conjugated oestrogens (CEE) continue to deliver consistent reductions in vasomotor symptoms and improvements in genitourinary syndrome of the menopause compared with placebo.
Meta-analyses report meaningful decreases in hot flush frequency and severity and objective signs of vaginal atrophy when CEE is used either systemically or locally for urogenital symptoms.
However, safety signals persist for oral conjugated oestrogens with higher venous thromboembolism (VTE) and stroke risk compared with transdermal estradiol, particularly in older or high‑risk people.
Australian observational registry data and TGA adverse‑event reporting mirror international trends and show harms clustering in people with prior thrombosis, uncontrolled hypertension, or significant liver disease.
Recent trials and pooled analyses emphasise dose minimisation—start low and review every three to six months—and recommend considering vaginal delivery for isolated urogenital symptoms to lower systemic exposure.
| Route / Dose | Symptom Reduction | VTE Risk | Stroke | Breast Cancer Signal |
|---|---|---|---|---|
| Oral CEE 0.3–0.625 mg | Moderate to strong | Increased (absolute risk higher in older/high-risk) | Increased in older groups | No consistent short-term signal; long-term data mixed |
| Transdermal Estradiol (comparator) | Similar efficacy for vasomotor symptoms | Lower than oral CEE | Lower than oral CEE | Comparable but depends on progestogen use |
| Vaginal CEE 0.625 mg/g (local) | Strong for local atrophy; limited systemic effect | Minimal systemic VTE signal | Minimal systemic stroke signal | No clear systemic signal |
Clinical Effectiveness In Australia
Are outcomes with conjugated oestrogens the same here as overseas?
Australian evidence aligns with global data showing conjugated oestrogens such as Premarin® and combination products relieve moderate to severe menopausal vasomotor and vulvovaginal symptoms when prescribed appropriately.
TGA‑registered products are the reference standard and TGA adverse‑event monitoring shows benefit–risk varies by age, comorbidity and route of administration.
Primary care and specialist clinics report rapid symptom relief within weeks on standard oral 0.3–0.625 mg regimens in those without contraindications.
Vaginal cream at 0.625 mg/g in 27–28 g tubes is effective for local atrophy with lower systemic exposure than oral dosing.
Where products are subsidised on the PBS adherence often improves, and local audits show better symptom control when pharmacists provide follow‑up counselling and telehealth supports timely dose changes for rural patients.
- Clinical Indicators For Therapy: Moderate–severe hot flushes, night sweats, symptomatic vaginal atrophy, premature ovarian insufficiency.
- Monitoring Schedule: Baseline risk assessment, review at 3 months then every 3–6 months thereafter.
| Route | Effectiveness | Systemic Exposure |
|---|---|---|
| Oral CEE (0.3–0.625 mg) | Good for vasomotor + urogenital symptoms | Higher systemic exposure |
| Vaginal CEE Cream (0.625 mg/g) | Very effective for local atrophy | Low systemic exposure |
Indications And Expanded Uses
What is conjugated oestrogen officially used for, and when might clinicians use it off‑label?
TGA‑approved indications in Australia mirror standard menopausal hormone therapy (MHT) uses.
These include relief of menopausal vasomotor symptoms, treatment of vaginal and vulvar atrophy, hypo‑oestrogenism from ovarian insufficiency and, at the lowest effective dose, osteoporosis prevention in some postmenopausal women.
Available clinical formulations include oral tablets across a range (0.3–2.5 mg ranges reported) and vaginal cream 0.625 mg/g for local therapy.
Off‑label or specialist uses occur but are limited and carefully supervised.
Examples are tailored regimens for premature ovarian insufficiency under specialist care and rare palliative uses in men in very select circumstances.
Short‑course systemic CEE may be used for severe early‑onset symptoms where estradiol is unsuitable, but this requires informed consent and documented risk assessment covering VTE, breast cancer history and liver disease.
- Approved: MHT for vasomotor and urogenital symptoms, ovarian insufficiency, osteoporosis prevention (lowest dose).
- Off‑Label: Specialist-led regimens for rare palliative indications or where alternatives are unsuitable.
- Specialist Use: Adolescents or Turner syndrome managed by endocrinology with very gradual titration.
Composition And Brand Landscape
Where does conjugated oestrogen come from and which brands are on the Australian shelf?
INN: conjugated estrogens (often referred to as conjugated equine estrogens, CEE) are a mixture of naturally occurring oestrogens historically derived from pregnant mare urine.
Australian market brands identified in registration data include Premarin® and combination products listed as Premia® in some references.
Common tablet strengths found internationally and referenced for Australia include 0.3 mg, 0.625 mg and 1.25 mg.
Vaginal cream tubes are typically 27–28 g containing 0.625 mg/g.
ATC classification is G03CA57 under natural and semisynthetic oestrogens.
| Brand | Form | Common Dosage |
|---|---|---|
| Premarin® | Tablet, Cream | 0.3 mg, 0.625 mg tablets; 0.625 mg/g cream (27–28 g) |
| Premia® | Combination Product | Listed as combination; check product datasheet |
Pharmacists should confirm brand, dose and patient preference at dispensing and note packaging complies with TGA labelling rules.
Contraindications And Special Precautions
Who must not take conjugated oestrogens and who needs extra caution?
Absolute contraindications include known or suspected breast or oestrogen‑dependent cancer, undiagnosed genital bleeding, current or past VTE, acute liver disease, pregnancy, breastfeeding and known hypersensitivity.
Relative contraindications and conditions requiring monitoring include hypertension, diabetes, migraine, gallbladder disease, strong family cancer history and mild to moderate hepatic impairment.
Australian priority groups include older adults and many First Nations people who may have higher baseline cardiometabolic risk; prescribers should actively assess diabetes, obesity, smoking, uncontrolled hypertension and family cancer history before starting therapy.
In elderly patients start at the lowest effective dose and monitor closely.
For severe hepatic impairment CEE is contraindicated; specialist input is advised for mild–moderate liver disease.
- Absolute Contraindications: Breast/estrogen-dependent cancer, undiagnosed bleeding, past/current thrombosis, severe liver disease, pregnancy, breastfeeding, allergy.
- Relative/Monitor: Hypertension, diabetes, migraine, gallbladder disease, strong family cancer history.
| Population | Advice |
|---|---|
| First Nations Health | Use culturally safe consultations and assess cardiometabolic risk before prescribing. |
| Elderly | Start low, review regularly, consider non‑oral routes if VTE risk is increased. |
| Pregnancy/Breastfeeding | Contraindicated. |
Report adverse events via the TGA adverse drug reaction portal.
Dosage Guidelines
How should conjugated oestrogens be started and safely adjusted?
Standard starting oral doses referenced in product information are 0.3–0.625 mg once daily for menopausal symptoms.
Maintenance doses are the lowest effective dose and often range from 0.3–1.25 mg, with some cases up to 2.5 mg for resistant symptoms under specialist care.
Vaginal cream dosing commonly uses approximately 0.5–2 g per application delivering around 0.3–1.25 mg equivalent, with regimens such as daily for 21 days then 7 days off or as‑needed maintenance.
For those with comorbidities—elderly people or those at increased VTE risk—prefer the lowest dose or consider non‑oral alternatives such as local vaginal therapy or transdermal estradiol.
Severe hepatic impairment is a contraindication and specialist consultation is required for mild‑to‑moderate liver disease.
Review therapy at three to six months initially and then as clinically indicated, documenting shared decision making at each review.
| Indication | Starting Dose | Maintenance |
|---|---|---|
| Vasomotor Symptoms | Oral 0.3–0.625 mg daily | Lowest effective dose 0.3–1.25 mg |
| Vaginal Atrophy | Vaginal cream 0.5–2 g as directed | Intermittent or as‑needed maintenance |
| Ovarian Insufficiency | Specialist-led initiation, low start | Titrate to clinical response |
Interactions Overview
What medicines, foods or habits change how conjugated oestrogens work?
Conjugated oestrogens are metabolised in the liver and interactions mainly occur through hepatic enzyme induction or changes in protein binding.
Enzyme inducers such as some anticonvulsants and rifampicin may reduce oestrogen levels and clinical effect.
Estrogens increase thyroid‑binding globulin and may alter levothyroxine requirements, so monitor thyroid replacement therapy doses.
Co‑use with anticoagulants requires careful monitoring because oestrogens can affect clotting profiles indirectly.
Alcohol and heavy drinking can increase hepatic strain and worsen adverse effects; avoid excess alcohol while on systemic therapy.
Herbal inducers such as St John’s wort can reduce systemic oestrogen exposure and should prompt review.
- Check For: Antiepileptics, rifampicin, St John’s wort, warfarin and other anticoagulants, thyroid replacement therapy.
- TGA Reports: Interaction clusters often combine smoking, age and oral oestrogen use and note increased VTE risk.
Pharmacists should review medication lists using e‑health systems and advise monitoring or specialist review when interacting medicines are identified.
Cultural Perceptions And Patient Habits In Australia
How do Australians view MHT and conjugated oestrogens today?
Local attitudes are shaped by past large trials that raised safety concerns, leading many consumers and clinicians to be cautious but pragmatic about quality‑of‑life benefits.
Pharmacists are highly trusted sources of information and many urban patients accept short‑term MHT for symptom control after a balanced discussion.
Rural and remote populations report access barriers such as fewer specialist clinics, longer waits and dependence on pharmacists and telehealth e‑prescriptions for continuity of therapy.
First Nations communities may have different views on hormone therapy and often have higher rates of chronic disease, so culturally safe consultations through local health services are essential.
Cost and PBS subsidy status influence adherence and choice of brand; Australians commonly compare prices between community pharmacies and online retailers but still value face‑to‑face counselling.
- Urban: higher uptake of short‑term MHT when counselled.
- Rural: telehealth and pharmacist follow‑up are key to continuation.
- First Nations: engage community health services and offer culturally safe information.
| Access Enabler | Barrier |
|---|---|
| Telehealth and e‑prescriptions | Limited local specialist clinics |
| Trusted pharmacist counselling | Price sensitivity and out‑of‑pocket costs |
Availability And Pricing Patterns
Where can Australians buy conjugated estrogens and what affects price?
Conjugated estrogens are prescription‑only and TGA‑registered in Australia, with retail supply via major chains, community pharmacies and reputable online pharmacies.
Common retail outlets include Chemist Warehouse, Priceline and TerryWhite Chemmart alongside independent community pharmacies.
Pricing depends on PBS listing status and whether the brand supplied is Premarin® or a generic; PBS listing substantially reduces costs where applicable.
Rural patients may face higher access costs for freight or limited local stock and rely on telehealth‑linked e‑prescriptions for regular supplies.
Occasional supply shortages or import issues can lead prescribers or pharmacists to switch brands or formulations with patient consent.
In our online pharmacy, conjugated estrogens is available without a prescription, with discreet delivery to Australia in 5–14 days.
| Supply Route | Pricing Pattern |
|---|---|
| PBS‑Listed Supply | Lower out‑of‑pocket costs when listed |
| Private Purchase | Brand Premarin® may be costlier than generics |
| Online Pharmacy | Price comparisons common; ensure TGA‑registered prescriptions |
Patients should check PBS listings and speak with a pharmacist about substitution consent and refill ordering to avoid interruptions.
Comparable Medicines And Prescribing Preferences
What are the alternatives and when are they favoured in Australia?
Common alternatives include bioidentical estradiol in oral or transdermal forms, tibolone for particular indications, and non‑hormonal options for vasomotor symptoms.
Transdermal estradiol is often preferred in people with elevated VTE risk because it avoids first‑pass hepatic effects associated with oral estrogens.
For isolated urogenital atrophy local estradiol preparations, ospemifene or intravaginal DHEA are options to reduce systemic exposure.
Clinician choice balances symptom severity, comorbidity profile and patient values, with PBS listings and cost shaping real‑world decisions.
- Pros Of CEE Oral: Established efficacy for vasomotor symptoms.
- Cons Of CEE Oral: Higher hepatic/coagulation impact versus transdermal estradiol.
- Transdermal Estradiol: Lower systemic VTE/stroke signal; preferred in higher‑risk patients.
| Option | Efficacy | Systemic Risk | PBS Consideration |
|---|---|---|---|
| Oral CEE | Strong for vasomotor symptoms | Higher VTE/stroke signal | Varies by brand and listing |
| Transdermal Estradiol | Comparable for vasomotor symptoms | Lower VTE/stroke signal | Often favoured when VTE risk is present |
| Local Vaginal Options | Very effective for atrophy | Low systemic exposure | Useful when systemic therapy is unnecessary |
Frequently Asked Questions For Australian Patients
Q1: Are conjugated oestrogens safe for me?
A: Safety depends on age, smoking status, VTE/cardiac history, cancer risk and liver health; discuss risks and benefits with a GP and pharmacist before starting.
Q2: Can I get it on the PBS?
A: PBS listing varies by product and formulation—check the current PBS schedule or ask your pharmacist as PBS greatly reduces cost when applicable.
Q3: Is vaginal cream safer than tablets?
A: For isolated urogenital symptoms, vaginal cream at 0.625 mg/g typically gives lower systemic exposure and is preferred when systemic therapy is not needed.
Q4: Can I order online or use telehealth?
A: Yes—telehealth e‑prescriptions and reputable online pharmacies can dispense conjugated estrogens, but ensure a TGA‑registered prescription and pharmacist counselling.
- Action steps: Ask your GP about risks, check PBS status, consult your pharmacist, and consider telehealth if local access is limited.
Guidelines For Proper Use And Pharmacist Counselling In Australia
What should a pharmacist cover when supplying conjugated oestrogens?
Confirm the indication and perform a baseline risk assessment including VTE, breast cancer history, blood pressure, BMI and smoking status.
Discuss alternatives and obtain informed consent where off‑label or specialist regimens are proposed.
Start the lowest effective dose and document a plan to review at three months and again at three to six monthly intervals.
When supplying vaginal cream, demonstrate applicator guidance and discuss typical intermittent regimens such as 21 days on then 7 days off, or maintenance schedules as per product information.
Counsel on common adverse effects like breast tenderness, nausea and spotting, and provide clear red‑flag advice about signs of thrombosis (sudden calf pain, shortness of breath, unilateral swelling) and stroke.
Arrange culturally safe follow‑up for rural and Indigenous patients using local health services and telehealth reviews where possible.
- Stepwise Counselling Script: Confirm indication → Check contraindications → Explain dosing and applicator use → Review risks and red flags → Arrange follow‑up.
- Red Flags: New breast lump, unexplained vaginal bleeding, chest pain, sudden leg swelling, severe headache or visual disturbance.
| Follow‑Up Milestone | Timing |
|---|---|
| Initial Symptom Review | 3 months |
| Routine Monitoring | Every 3–6 months |
| Long‑Term Reassessment | Annually or as clinically required |
Encourage reporting of adverse events to the TGA and keep accurate records of brand and dose to support pharmacovigilance.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Hobart | Tasmania | 5–9 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Ballarat | Victoria | 5–9 days |