
Prometrium
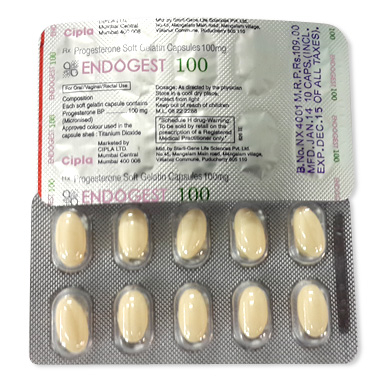
Prometrium
- In many pharmacies and from some online suppliers in Australia you can buy Prometrium without a prescription; however, officially Prometrium (micronised progesterone) is a prescription-only medicine (Rx) in most jurisdictions, so availability without a receipt can vary by supplier and location. Discreet delivery and packaging options are often offered.
- Prometrium (progesterone) is used for secondary amenorrhoea, and for endometrial protection in postmenopausal hormone replacement therapy; it works by activating progesterone receptors to oppose oestrogen-driven endometrial proliferation and to support luteal-phase endometrial changes.
- Usual dosages include 400 mg orally at bedtime once daily for 10 days for secondary amenorrhoea, and 200 mg orally at bedtime for 12 days of a 28‑day cycle for endometrial protection in HRT; capsules are commonly 100 mg or 200 mg so dosing is adjusted accordingly.
- Prometrium is administered orally as micronised progesterone soft capsules (sometimes used vaginally off‑label in some regions); capsules typically come in blister packs or boxes of 15–90 units.
- Onset: systemic effects (including sedative/drowsy effects) often begin within 30–60 minutes after an oral dose, while endometrial/progestogenic changes take days to weeks to develop clinically.
- Duration of action: the sedative/CNS effects commonly last several hours after a dose; the progestogenic effect from a once‑daily dose is generally sufficient to cover a 24‑hour dosing interval for cycle control.
- Alcohol warning: avoid or limit alcohol while taking Prometrium because alcohol can increase drowsiness and CNS depression and worsen side effects like dizziness and sedation.
- The most common side effect is drowsiness/sedation (other frequent effects include headache, breast tenderness, abdominal cramps, dizziness, mood changes and nausea).
- Would you like to try Prometrium without a prescription?

Basic Prometrium Information
- INN (International Nonproprietary Name): Progesterone — common to all international references.
- Brand Names Available In Australia: Prometrium is the principal cited brand for Australia and New Zealand, supplied as micronised progesterone capsules in 100 mg and 200 mg strengths.
- ATC Code: G03DA04 — Genito-urinary system and sex hormones; G03: Sex hormones and modulators; G03D: Progestogens; G03DA: Pregnen-(4)-derivatives.
- Forms & Dosages: Soft capsules 100 mg and 200 mg are the standard commercial forms, typically in blister packs of 30 or 90 units; vaginal capsules/softgels (100 mg, 200 mg) are available in some markets; compounding powders are rare.
- Manufacturers In Australia: AbbVie is the listed manufacturer for Prometrium internationally and for Australia/New Zealand listings; generics and other suppliers (Teva, Mylan and others) are also referenced in global supply chains.
- Registration Status In Australia: Prometrium is referenced for supply in Australia/NZ with prescription-only status (Rx).
- OTC / Rx Classification: Prescription only (Rx) for indicated uses such as secondary amenorrhoea and endometrial protection when used with oestrogen.
Latest Research Highlights
Are you wondering what recent studies say about micronised progesterone and safety?
Randomised trials and large observational cohorts published between 2022 and 2025 continued to evaluate micronised progesterone for endometrial protection during HRT, treatment of secondary amenorrhoea and luteal support in assisted reproduction.
Data show micronised progesterone provides effective endometrial protection when given cyclically with oestrogen and produces withdrawal bleeding where expected in amenorrhoea protocols.
Tolerability in those studies was dominated by CNS effects such as sedation, plus breast tenderness and mood changes.
Comparative observational analyses suggest a lower venous thromboembolism signal for micronised progesterone versus some synthetic progestins, though randomised controlled trial confirmation is limited.
Australian pharmacovigilance reports to the TGA mirror global safety signals with drowsiness, nausea and mood effects reported most often and rare hepatic or thrombotic events flagged for caution.
IVF and luteal-support research supports efficacy for embryo implantation when progesterone is used vaginally or orally, but local clinic practice varies by region and specialist preference.
| Outcome | Indication | Data Highlights |
|---|---|---|
| Endometrial Protection | HRT (with oestrogen) | Micronised progesterone 200 mg nightly for 12 days per 28-day cycle reduces endometrial hyperplasia risk in RCTs/observational cohorts. |
| Menstrual Restoration | Secondary Amenorrhoea | 400 mg nightly for 10 days induces withdrawal bleeding in most patients in cycle therapy studies. |
| Luteal Support | Assisted Reproduction | Vaginal or oral progesterone supports implantation; route choice varies by clinic protocol. |
Clinical Effectiveness In Australia
What can patients in Australia expect from micronised progesterone in real practice?
When prescribed and used according to product information, micronised progesterone reliably induces withdrawal bleeding for secondary amenorrhoea and provides endometrial protection in oestrogen-containing HRT regimens.
Australian prescribers commonly follow labelled regimens such as 400 mg at night for 10 days for amenorrhoea and 200 mg at night for 12 days of a 28-day cycle for endometrial protection.
TGA adverse event reporting aligns with international experience, with headache, dizziness, mood changes and sedation among the common events.
Serious outcomes including thrombosis or significant hepatic dysfunction are uncommon in surveillance data but have been recorded and should prompt immediate review.
Where progesterone is PBS-subsidised for a listed indication adherence and persistence tend to improve, and where scripts are private, cost sensitivity can reduce continuation.
Community pharmacies and specialist clinics report that, in everyday care, labelled regimens deliver outcomes consistent with trial data when screening and monitoring are performed appropriately.
Indications And Expanded Uses
Are there approved uses and other common off-label roles for micronised progesterone?
Regulatory approvals internationally cover secondary amenorrhoea and endometrial protection during oestrogen therapy, and Australian labelling typically mirrors these indications.
Standard regimens include 400 mg nightly for 10 days for secondary amenorrhoea and 200 mg nightly for 12 days of a 28-day cycle for endometrial protection when given with oestrogen.
Common expanded or off-label uses in Australian clinics are luteal-phase support in assisted reproduction, treatment of luteal insufficiency and short-term management of dysfunctional uterine bleeding.
Some fertility centres reference vaginal administration of oral capsules as an off-label route described in parts of Europe and Asia, and Australian practice varies between specialists.
Absolute contraindications include active breast cancer, thrombotic disease history and severe hepatic dysfunction; such patients should not use micronised progesterone.
| Indication | Typical Dose |
|---|---|
| Secondary Amenorrhoea | 400 mg orally at bedtime for 10 days |
| Endometrial Protection (with oestrogen) | 200 mg orally at bedtime for 12 days per 28-day cycle |
| Luteal Support (off‑label) | Clinic-dependent; oral or vaginal routes cited |
Composition And Brand Landscape
Which brands and formulations will your local pharmacy stock?
The active ingredient is progesterone (INN) delivered as micronised progesterone in soft capsules or softgels of 100 mg and 200 mg strengths.
Prometrium is the primary brand referenced for Australia and New Zealand, while Utrogestan and other brand names appear across EU markets.
Key manufacturers include AbbVie (Prometrium) and Besins Healthcare (Utrogestan), with generics produced by companies such as Teva and Mylan.
Packaging commonly includes blister packs of 30 or 90 units, and vaginal softgels or capsules are available in some jurisdictions in boxes of 15 or 30.
Note that some US packaging contains a peanut allergen warning because capsule oil excipients may include peanut oil, a point to check before supply to patients with peanut allergy.
| Brand | Manufacturer | Strengths & Pack Sizes |
|---|---|---|
| Prometrium | AbbVie | 100 mg, 200 mg — blisters 30/90 |
| Utrogestan | Besins Healthcare | 100 mg, 200 mg — softgel/vaginal forms 15/30 |
| Generic Micronised Progesterone | Teva, Mylan, others | 100 mg, 200 mg — variable pack sizes |
Contraindications And Special Precautions
Who should not take micronised progesterone and what should pharmacists screen for?
Absolute contraindications include severe hepatic dysfunction, known or suspected breast or hormone-dependent malignancy, undiagnosed abnormal vaginal bleeding, current or history of thrombosis, pregnancy in certain contexts and allergy to peanuts where applicable.
Relative contraindications requiring monitoring include mild to moderate hepatic or renal impairment, migraine or severe headaches, asthma, depression or other psychiatric disorders and a history of cardiovascular disease.
Australian practice should also consider higher comorbidity burdens in some Indigenous communities and patients in rural areas, with tailored screening and liaison with primary care.
Advise patients that drowsiness, dizziness or impaired concentration may occur and that they should avoid driving or heavy machinery until they know how the medicine affects them.
- Pharmacist Screening Checklist: current liver disease, personal/family thrombosis history, breast symptoms, pregnancy status, peanut allergy, current medications that induce hepatic enzymes.
Dosage Guidelines
What are the standard dosing schedules and what to do if a dose is missed?
For secondary amenorrhoea the standard regimen is 400 mg orally once daily at bedtime for 10 days, repeated as clinically indicated.
For endometrial protection with oestrogen the common regimen is 200 mg orally once daily at bedtime for 12 days of a 28-day cycle.
Commercial strengths are 100 mg and 200 mg soft capsules, and bedtime dosing is often chosen to reduce sedative effects.
No routine dose adjustments are specified for the elderly but monitor for increased sensitivity, and use is contraindicated in severe hepatic impairment.
If a dose is missed take it as soon as remembered unless it is close to the next dose and do not double up.
Overdose may cause nausea, vomiting, withdrawal bleeding and sedation; seek medical review if overdose is suspected.
| Indication | Dose | Monitoring |
|---|---|---|
| Secondary Amenorrhoea | 400 mg nightly x10 days | Bleeding response; rule out pregnancy |
| Endometrial Protection | 200 mg nightly x12 days/28 | Bleeding pattern; periodic endometrial assessment as per local guidelines |
Interactions Overview
Which medicines and substances change progesterone levels or effects?
Enzyme inducers such as rifampicin, carbamazepine, phenytoin and St John’s Wort can reduce progesterone concentrations and lower effectiveness.
Concurrent sedatives, alcohol and some antidepressants may increase drowsiness and additive CNS depression.
Strong CYP inhibitors can alter levels in some contexts, so check interactions when patients take multiple medicines.
Medications that affect coagulation or cardiovascular risk should be reviewed because of the background concern about thrombotic risk in hormone therapy.
| Interacting Drug | Effect | Clinical Action |
|---|---|---|
| Rifampicin, Carbamazepine, Phenytoin | Reduce progesterone levels | Consider alternative therapy or monitor effectiveness; inform prescriber |
| Alcohol, Benzodiazepines, Opioids | Increase sedation | Advise caution with driving; consider dosing at bedtime |
| Strong CYP Inhibitors | May alter plasma levels | Check clinical decision support; adjust monitoring |
Cultural Perceptions And Patient Habits
How do Australians view micronised progesterone and what affects adherence?
Many patients describe micronised progesterone as a “natural” or “bio-identical” option, and that language affects acceptance and choice.
Cost and PBS subsidy strongly influence whether patients persist with therapy, with subsidised access improving adherence.
Rural and remote patients often rely on telehealth and community pharmacies for repeat scripts and counselling, and limited specialist access can delay initiation of HRT or fertility protocols.
Online forums and social media commonly discuss side effects such as drowsiness and mood changes and compare micronised progesterone with synthetics like medroxyprogesterone or dydrogesterone.
Indigenous health services stress culturally safe conversations that consider family and community contexts when discussing HRT or fertility treatments.
Availability And Pricing Patterns
Where can patients in Australia obtain Prometrium and what affects price?
Prometrium and micronised progesterone products are supplied through wholesalers and dispensed at major pharmacy chains and community pharmacies.
Online pharmacies and telehealth services increasingly offer scripted supply, and e-prescriptions have improved access for rural patients.
When a product is PBS-listed for the patient’s indication the out-of-pocket cost falls substantially compared with private scripts.
Private-script patients tend to compare big-chain discounts or consider importing, and pharmacists should remind customers to verify TGA and customs rules for imports.
Check pack size and manufacturer details before dispensing; soft capsules are usually 100 mg or 200 mg in blisters of 30 or 90.
In our online pharmacy, prometrium is available without a prescription, with discreet delivery to Australia in 5-14 days.
Comparable Medicines And Preferences
What are the main alternatives and how do they compare?
Alternatives commonly used in Australia include medroxyprogesterone acetate (Provera), dydrogesterone (Duphaston) and micronised progesterone generics.
Synthetic progestins such as medroxyprogesterone differ structurally and in pharmacology from body-identical progesterone and may have distinct adverse-event profiles.
Dydrogesterone is orally active with a different receptor selectivity and is an option where clinicians prefer a non-sedating progestogen.
Clinician choice balances efficacy for the indication, side-effect profile (sedation is more common with micronised progesterone), thrombotic risk signals, route preferences and patient values about “natural” hormones.
| Drug | Type | Pros | Cons | Common Indications |
|---|---|---|---|---|
| Micronised Progesterone | Body-identical | Well tolerated; HRT endometrial protection | Sedation; peanut oil allergy risk in some brands | HRT, amenorrhoea, luteal support |
| Medroxyprogesterone (Provera) | Synthetic progestin | Widely available; oral/tablet options | Different metabolic/thrombotic profile | Diverse gynaecological uses |
| Dydrogesterone (Duphaston) | Synthetic progestin | Orally active; less sedating | Different receptor action; not body-identical | HRT, luteal support in some protocols |
FAQ — Top Patient Questions
Is Prometrium on the PBS?
Some progesterone indications may be PBS-listed; check the current PBS schedule or ask your pharmacist for the latest subsidy status.
How should I take it?
Take at night to reduce drowsiness; common regimens include 400 mg nightly for 10 days for secondary amenorrhoea and 200 mg nightly for 12 days per 28-day cycle for endometrial protection.
Can I take it if I’m pregnant or trying to conceive?
Use in pregnancy depends on indication and should be directed by a treating specialist; fertility clinics sometimes use progesterone for luteal support under clinic protocols.
What about peanut allergy?
Some capsule formulations contain peanut oil; always check packaging and advise prescribers and pharmacists if there is a known peanut allergy.
Guidelines For Proper Use And Pharmacist Counselling
What should pharmacists cover when counselling a patient starting micronised progesterone?
Confirm the indication, screen for contraindications such as thrombosis history, liver disease and breast cancer, and check for peanut allergy on packaging.
Advise bedtime dosing to limit sedation and provide missed-dose instructions: take as soon as remembered unless near the next dose and do not double up.
Explain storage: keep below 25°C, protect from moisture and light and retain in original packaging.
Instruct patients to monitor for mood changes, unusual bleeding, signs of thrombosis or severe hepatic symptoms and to seek immediate review for severe events.
For rural and remote patients arrange telehealth follow-up, e-prescriptions and coordination with local primary care or Aboriginal Community Controlled Health Services for culturally safe care.
- Pharmacist Counselling Checklist: indication confirmed, pregnancy status, allergy check (peanut), concomitant medicines, driving/work safety advice, adverse-event reporting to the TGA if serious.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Gold Coast | Queensland | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |