
Medrol Active
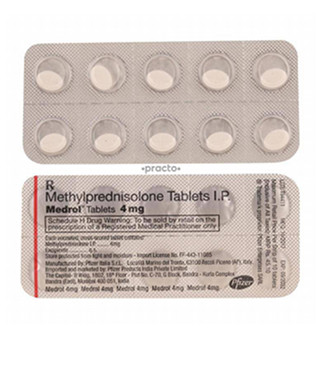
Medrol Active
- In our pharmacy, you can buy medrol active without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
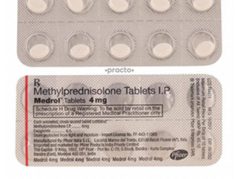
- Medrol active (methylprednisolone) is used to treat inflammatory and immune-mediated conditions such as asthma exacerbations, severe allergic reactions, rheumatoid arthritis, inflammatory bowel disease, lupus and MS relapses; it is a glucocorticoid that suppresses inflammation and the immune response through genomic and non‑genomic effects.
- The usual dose for adults varies by condition: oral 4–48 mg/day (commonly 4–16 mg/day for chronic control; short higher courses for flares); IV pulse dosing for severe exacerbations can be 500–1000 mg/day for 3–5 days; paediatric dosing is typically 0.5–1.7 mg/kg/day — always individualise dosing to the patient and indication.
- Form of administration: oral tablets (2 mg, 4 mg, 8 mg, 16 mg, 32 mg) and injectable formulations (methylprednisolone sodium succinate vials/ampoules for IV/IM, and depot acetate injections for IM use).
- Onset time: oral symptom relief is usually seen within 1–4 hours (with some effects evident within 24 hours); IV/IM administration can produce effects within 30–60 minutes for acute situations.
- Duration of action: a moderate‑acting corticosteroid — clinical effects commonly last about 12–36 hours depending on dose and formulation; high‑dose IV pulses may have prolonged immunosuppressive effects.
- Alcohol warning: avoid excessive alcohol — it can increase risk of gastric irritation and bleeding (especially with NSAIDs), may worsen mood effects and metabolic adverse effects such as hyperglycaemia.
- Most common side effec: increased appetite and weight gain (other frequent effects include insomnia, mood changes, fluid retention, skin thinning and hyperglycaemia).
- Would you like to try medrol active without a prescription?
Latest Research Highlights (Australia + Global, 2022–2025)
- INN (International Nonproprietary Name): Methylprednisolone.
- Brand Names Available In Australia: Medrol; Solu‑Medrol; Dosepak presentations (21‑tablet Dosepak).
- ATC Code: H02AB04.
- Forms & Dosages: Tablets 2 mg, 4 mg, 8 mg, 16 mg, 32 mg; injectables (methylprednisolone sodium succinate) in vials/ampoules 20 mg, 40 mg, 125 mg, 500 mg, 1 g; depot acetate formulations 40 mg, 80 mg in some markets.
- Manufacturers In Australia: Pfizer (including Upjohn/subsidiaries) and a range of generic suppliers and repackagers.
- Registration Status In Australia: Registered with the TGA as prescription‑only medicine.
- OTC / Rx Classification: Prescription Only (Rx) in Australia.
What does the latest evidence say about methylprednisolone and why should clinicians and patients in Australia care?
Recent literature from 2022 to 2025 reinforces methylprednisolone’s established role as a rapid anti‑inflammatory glucocorticoid across specialties.
Australian hospital audits and international randomised controlled trial meta‑analyses continue to support IV methylprednisolone pulses for multiple sclerosis relapses and for severe exacerbations such as acute asthma and COPD flare‑ups.
Short oral tapers are still widely recommended for moderate allergic flares where rapid symptom control is needed.
Safety monitoring from the TGA and international pharmacovigilance databases highlights reversible metabolic effects such as hyperglycaemia and fluid retention as common signals.
Infection risk, psychiatric reactions and bone health impacts with prolonged use remain key safety themes in recent reports.
Comparative studies often contrast methylprednisolone (including methylprednisolone sodium succinate for IV use and acetate depot forms for IM) with prednisolone/prednisone and dexamethasone.
Formulary choice in hospitals is generally driven by potency, IV availability (Solu‑Medrol), and local supply chains.
Observational Australian data note increasing telehealth‑linked prescribing for short oral courses and ongoing rural access challenges where IV administration is required.
Key Study Highlights (2022–2025)
| Study | Population/Setting | Outcome | Safety Notes |
|---|---|---|---|
| IV Pulse RCT Meta‑analysis | MS Exacerbations, multi‑centre | Improved recovery time with 500–1000 mg/day for 3–5 days | Short‑term hyperglycaemia; psychiatric events rare |
| Australian Hospital Audit | Acute asthma admissions | Single IV methylprednisolone doses (40–125 mg) reduced time to discharge | Monitor glucose and BP post‑dose |
| Allergic Flare Observational Series | Community‑treated allergic reactions | Oral Dosepak short courses effective for symptom control | Transient appetite and sleep disturbance reported |
Clinical Effectiveness In Australian Practice (PBS & TGA Context)
Worried about whether Medrol is funded or monitored in Australia?
Methylprednisolone (Medrol and Solu‑Medrol) is regulated by the TGA as a prescription‑only glucocorticoid.
PBS listings vary by indication and by formulation, so subsidy applies selectively depending on the approved condition.
Dosepak pre‑tapered packs are commonly used in the community for short oral courses when PBS criteria are met.
Clinical effectiveness in Australian settings mirrors international guidance.
Rapid symptom relief is expected in allergic and inflammatory flares with oral regimens.
High‑dose IV regimens remain the standard in hospitals for MS relapses and severe autoimmune crises.
TGA pharmacovigilance and hospital reporting commonly flag typical steroid adverse events.
Hospital discharge summaries and primary‑care follow‑ups generally recommend monitoring blood glucose and blood pressure after systemic steroid courses.
Rural practice patterns often depend on access to parenteral forms in regional hospitals.
When IV access is limited, rural patients may receive oral Dosepaks via telehealth prescriptions or be transferred to a regional centre for IV therapy.
- PBS‑covered Indications (typical examples): Selected inflammatory conditions where eligibility criteria are met.
- Hospital Use: High‑dose IV methylprednisolone for MS exacerbation and severe systemic inflammation.
| Route | Typical Australian Outcome |
|---|---|
| Oral Dosepak | Effective for short community courses; rapid symptom relief for allergic flares |
| IV Solu‑Medrol | Rapid control in severe exacerbations and MS relapses; hospital administration |
Indications And Expanded Uses (TGA‑Approved And Off‑Label)
Not sure when methylprednisolone is the right choice?
TGA‑approved and commonly accepted uses include acute asthma and allergic reactions, rheumatoid and autoimmune flares, certain dermatological conditions, nephritis, and multiple sclerosis exacerbations where IV high‑dose therapy is indicated.
Solu‑Medrol (methylprednisolone sodium succinate) is a preferred IV agent for severe systemic inflammation and transplant rejection prophylaxis.
Off‑label uses in Australian clinics can include refractory inflammatory eye disease, selected rheumatological bridging therapy, and some dermatology protocols.
Off‑label regimens should always be supervised by a specialist.
Choice of regimen — oral low‑moderate dose, IV pulse, or depot acetate — depends on urgency, tissue penetration and the patient’s risk profile.
TGA guidance advises caution with live vaccines, active fungal infection, and in pregnancy and lactation.
- TGA‑Approved/Standard Uses: Acute asthma, severe allergic reactions, MS relapses (IV), transplant prophylaxis (IV Solu‑Medrol).
- Common Off‑Label Uses: Refractory uveitis, certain dermatology bridging protocols, rheumatology short‑term bridging therapy.
Decision Flow (brief): Urgent severe flare → IV Solu‑Medrol pulse; Moderate community flare → oral Medrol Dosepak; Chronic control → lowest effective oral dose or specialist‑led regimen.
Composition And Australian Brand Landscape (Active Ingredient, Manufacturers)
Curious which brands and pack sizes are commonly found down the road?
The active ingredient is methylprednisolone (INN), ATC H02AB04.
Australian products include branded Medrol and Solu‑Medrol presentations.
Dosepak pre‑tapered 21‑tablet packs are available for short oral courses in the Australian market.
Dosage forms available locally include tablets (2 mg, 4 mg, 8 mg, 16 mg, 32 mg) and injectables (Solu‑Medrol vials of various strengths).
Pfizer and other multinational and local generic suppliers distribute products and repackaged presentations.
| Brand Name | Strengths | Pack Size | Route | Common Supplier |
|---|---|---|---|---|
| Medrol | 4 mg, 16 mg, 32 mg (tablets) | Tablets, 21 Dosepak | Oral | Pfizer / Generics |
| Solu‑Medrol | 20 mg, 40 mg, 125 mg, 500 mg, 1 g (vials) | Single‑use vials | IV/IM | Pfizer / Hospital Supply |
| Depo‑Medrol (acetate) | 40 mg, 80 mg (depot) | Ampoules/vials | IM (longer‑acting) | Selected suppliers (market dependent) |
Quick Definitions
- Sodium Succinate: Water‑soluble IV salt used in Solu‑Medrol for immediate systemic effect.
- Acetate Depot: Slower‑release IM formulation for longer duration of action.
Contraindications And Special Precautions (High‑Risk Australian Groups)
Who should avoid methylprednisolone or use it only with caution?
Absolute contraindications include known hypersensitivity to methylprednisolone or excipients and active, untreated systemic fungal infections.
Live or attenuated vaccines are contraindicated during high‑dose therapy.
Relative cautions apply to diabetes, hypertension, osteoporosis, psychiatric history, glaucoma, ulcer disease and immunocompromised states.
Special Australian considerations include careful use in older adults with higher osteoporosis risk and Indigenous communities with higher infectious disease burden where risk‑benefit must be reviewed.
Pregnancy and breastfeeding require case‑by‑case assessment in line with TGA guidance.
- Absolute Contraindications: Hypersensitivity; untreated systemic fungal infection; live vaccines during high‑dose therapy.
- Relative Contraindications: Diabetes; heart failure; severe psychiatric history; active peptic ulcer disease.
| Monitoring Action | When |
|---|---|
| Blood Glucose | Before and during courses for people with diabetes or at high risk |
| Blood Pressure | During and after systemic courses |
| Mental State | Monitor for mood change or psychosis in people with psychiatric history |
| Bone Health | Assess in long‑term use; consider calcium/vitamin D and bone density testing |
Dosage Guidelines And Adjustments (Standard Regimens In Australia)
How much Medrol should a patient take for common conditions?
Typical adult oral dosing ranges from 4–48 mg per day, depending on indication and severity.
For acute asthma or allergy, IV dosing often uses single 40–125 mg doses with subsequent tapering as required.
High‑dose IV pulses for MS exacerbation are commonly 500–1000 mg per day for 3–5 days.
Paediatric dosing commonly starts at 0.5–1.7 mg/kg/day divided across doses and requires specialist oversight.
Elderly patients should receive the lowest effective dose with close monitoring for osteoporosis and metabolic effects.
Renal impairment rarely requires dose adjustment because hepatic metabolism predominates, but monitor fluid and electrolytes.
Hepatic impairment may reduce clearance and warrant cautious dosing and monitoring.
Short acute courses are often 5–14 days with cessation or taper; courses longer than 1–2 weeks typically need gradual tapering to avoid adrenal suppression.
| Regimen | Typical Dose | Adjustment Notes |
|---|---|---|
| Oral Dosepak | Pre‑tapered 21‑tablet course (varies by pack) | Often used for 5–14 day acute courses; check PBS criteria |
| IV Pulse (MS, severe flare) | 500–1000 mg/day for 3–5 days | Hospital administration; monitor glucose and BP |
| Single IV Dose (asthma, allergy) | 40–125 mg once, then taper | Useful for urgent symptom control |
Interactions Overview (Drugs, Food, TGA Reports)
Which medicines and habits change how methylprednisolone works?
Methylprednisolone is metabolised by CYP3A4, so inhibitors such as some azole antifungals and macrolide antibiotics can increase steroid levels.
Enzyme inducers like rifampicin and carbamazepine may reduce steroid efficacy.
Concurrent NSAID use raises the risk of gastrointestinal ulceration and bleeding.
Anticoagulant effects may be potentiated and require monitoring of INR or clinical response.
Live vaccines are contraindicated during high‑dose steroid therapy.
Alcohol can worsen gastric irritation and metabolic side effects.
Caffeine may exacerbate sleep disturbance or mood changes while on steroids.
TGA adverse‑event reporting highlights interactions that precipitate hyperglycaemia and psychiatric events in patients on multiple medicines.
Pharmacists should check e‑health medication records and counsel patients about monitoring blood glucose and signs of infection.
- High‑Risk Interacting Drugs: CYP3A4 inhibitors and inducers; NSAIDs; anticoagulants; live vaccines.
- Pharmacist Action Points: Review medication history, advise glucose/BP monitoring, flag high‑risk combinations to prescribers.
Cultural Perceptions And Patient Habits In Australia
What do Australians usually worry about when a GP prescribes Medrol?
Many patients see steroids as powerful but risky, and commonly ask pharmacists for reassurance about side effects.
Concerns most often raised include weight gain, mood swings and long‑term bone health.
Indigenous health services emphasise culturally safe communication regarding infection risk and chronic disease interaction.
Urban patients generally have easier access to IV therapies at tertiary hospitals.
Rural and remote communities often rely on oral Dosepaks and telehealth consultations with local GPs or visiting specialists.
Patients commonly compare prices between PBS‑subsidised supplies and private options and place high trust in local pharmacists and major chains.
Telehealth e‑prescriptions have improved access to short courses but can complicate follow‑up for people in remote areas.
- Common Forum Themes: "Will I put on a lot of weight?" "How long before mood swings settle?" "Is the Dosepak the same as other tablets?"
- Access Contrast: Urban → hospital IV access; Rural → oral Dosepak via telehealth or transfer for IV.
Availability And Pricing Patterns (Chemist Warehouse, Priceline, Online, PBS)
Can Medrol be bought at local pharmacies and how much will it cost?
Medrol and Solu‑Medrol are prescription‑only in Australia and are dispensed through community pharmacies, hospital dispensaries and licensed online pharmacies.
Major retail chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart commonly stock oral tablets and Dosepaks.
Injectable Solu‑Medrol vials are usually hospital stock or supplied via special‑order pharmacies.
PBS subsidy applies when the indication and formulation meet PBS listing criteria; this can greatly reduce out‑of‑pocket cost.
Private prescriptions vary in price across pharmacies and online sellers.
Online pharmacies and telehealth services have increased access to short oral courses by enabling e‑prescriptions.
Parenteral formulations typically require hospital administration.
In our online pharmacy, medrol active is available without a prescription, with discreet delivery to Australia in 5‑14 days.
| Supply Route | Likely Cost | Availability Notes |
|---|---|---|
| Community Pharmacy (PBS) | Lower with PBS subsidy | Common for oral Dosepak when criteria met |
| Private Prescription | Varies by pharmacy | Oral tablets widely available; check prices |
| Hospital Supply | Usually not a direct cost to patient in public hospitals | Injectables (Solu‑Medrol) typically hospital stock |
| Online Pharmacy | Varies; delivery fees may apply | E‑prescriptions accepted for oral courses; injectables usually not shipped for home IV use |
Comparable Medicines And Prescribing Preferences (Pros/Cons Checklist)
Is methylprednisolone the best steroid for this patient, or are there better choices?
Common alternatives include prednisolone/prednisone, dexamethasone and hydrocortisone.
Prednisolone is often preferred orally for step‑down therapy due to familiar dosing patterns.
Dexamethasone is more potent and longer acting, suited to antiemetic protocols and intracranial oedema in specific settings.
Hydrocortisone is favoured where physiologic replacement is needed.
Methylprednisolone advantages include availability in both IV and oral forms and Dosepak packaging for short courses.
Disadvantages mirror other systemic steroids: metabolic effects, bone health impact and psychiatric risk, and branded formulations can be pricier.
- Decision Checklist: Urgency of response; need for IV route; potency/duration required; patient comorbidities (diabetes, osteoporosis); PBS coverage.
| Drug | Typical Use | Pros | Cons |
|---|---|---|---|
| Methylprednisolone | IV pulses, oral short courses | IV and oral options; Dosepak available | Steroid adverse effects; cost for some brands |
| Prednisolone | Oral maintenance and tapering | Well‑known dosing; PBS options | Similar side‑effect profile |
| Dexamethasone | Potent, long‑acting uses | High potency; long duration | Greater suppression risk with some uses |
FAQs Australians Ask About Medrol
Can I get Medrol on the PBS?
Some indications and formulations of methylprednisolone are PBS‑listed.
Check with your GP or pharmacist to confirm eligibility for subsidy.
Is a Dosepak the same as tablets?
Yes. Dosepak is a pre‑tapered packaging of oral methylprednisolone for short courses and contains the same active ingredient as tablets.
What should I watch for after a short course?
Common effects include increased appetite, sleep disturbance and mood changes.
People with diabetes should check blood glucose and anyone noticing infection signs should seek medical review.
Can I have vaccines while taking high‑dose Medrol?
Live vaccines are generally contraindicated during high‑dose therapy.
Discuss timing with your immunisation provider.
- When To Call A GP: Persistent high fever or signs of infection; severe mood change or suicidal thoughts; very high blood glucose readings; severe abdominal pain or black stools.
- Local Action Points: Check PBS eligibility; ask major pharmacy chains for stock; use telehealth for follow‑up if in a rural area.
Guidelines For Proper Use & Pharmacist Counselling (PBS/National Advice)
What should a pharmacist tell a patient starting Medrol?
Confirm the indication, route, dose and expected duration with the patient.
Review the full medication history and check electronic health records for interactions.
Explain common side effects such as sleep disturbance, increased appetite, fluid retention and mood changes.
Advise on monitoring needs: blood pressure, blood glucose, mood and bone health for long‑term use.
Give storage guidance: tablets at 20–25°C in a dry place and injectables as per vial labelling.
For courses longer than 1–2 weeks, discuss tapering and the risk of adrenal suppression.
Advise patients to avoid live vaccines while on high doses and to report signs of infection immediately.
Use culturally safe communication strategies for Indigenous patients and ensure clear follow‑up plans with the patient’s GP or specialist.
- Pharmacist Counselling Checklist: Indication and route; dose and duration; interactions; side effects to expect; monitoring plan; when to seek urgent care.
Patient Handout Template (quick):
What this medicine does. How to take it. Common side effects. Monitoring checklist. When to call your GP. Storage and disposal instructions.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Geelong | Victoria | 5-7 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Darwin | Northern Territory | 5-9 days |
| Alice Springs | Northern Territory | 5-9 days |