
Medrol
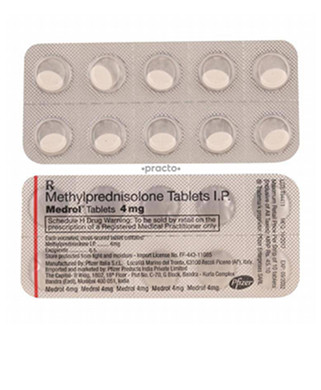
Medrol
- In our pharmacy, you can buy medrol without a prescription, with delivery in 5–14 days throughout Australia and discreet packaging; note that medrol is prescription-only in most countries and should ideally be used under medical supervision.
- Medrol (methylprednisolone) is used for conditions such as rheumatoid arthritis, asthma exacerbations, severe allergic reactions, inflammatory bowel disease, multiple sclerosis relapses, adrenal insufficiency and as an immunosuppressant; it is a glucocorticoid that reduces inflammation and suppresses immune activity by binding glucocorticoid receptors and altering gene transcription.
- Usual doses vary by indication: oral 4–48 mg/day (rheumatic/inflammatory conditions), 24–48 mg/day for many acute allergic/asthmatic flares (often with tapering packs), adrenal replacement 4–12 mg/day, paediatric dosing ~0.5–1.7 mg/kg/day; severe relapses may use high IV doses (e.g. 500–1000 mg/day for 3–5 days); dosing should be individualised and tapered.
- Forms of administration include oral tablets (2–32 mg strengths and predesigned dosepaks), intravenous and intramuscular injectables (sodium succinate vials), and depot IM suspensions (e.g. Depo‑Medrol).
- Onset time: symptom relief often begins within 1–4 hours after oral dosing, with some anti-inflammatory effects developing over 24–48 hours; IV doses can produce effects within hours.
- Duration of action: methylprednisolone is intermediate‑acting — clinical effects commonly last about 12–36 hours depending on dose, though adrenal suppression and some effects may persist longer.
- Alcohol warning: avoid heavy alcohol use while taking medrol — alcohol can worsen gastrointestinal irritation, increase bleeding risk, affect glucose control and bone health; discuss alcohol intake with your prescriber.
- The most common side effect is increased appetite (often leading to weight gain); other frequent effects include insomnia, mood changes, elevated blood sugar, indigestion and skin thinning.
- Would you like to try medrol without a prescription?
Latest Research Highlights
Basic Medrol Information
- INN (International Nonproprietary Name): Methylprednisolone.
- Brand Names Available In Australia: not specified.
- ATC Code: H02AB04.
- Forms & Dosages: Tablets 2mg, 4mg, 8mg, 16mg, 32mg; injectables/vials 40mg, 125mg, 500mg, 1g (sodium succinate); intramuscular suspension 40mg/ml and 80mg/ml (acetate); predesigned tapering Dosepaks in some markets.
- Manufacturers In Australia: not specified.
- Registration Status In Australia: not specified.
- OTC / Rx Classification: Rx (Prescription Only Medicine) in all countries according to available data.
What do recent trials tell clinicians about medrol and methylprednisolone?
Randomised trials and surveillance from 2022–2024 continue to support methylprednisolone for short‑term control of acute inflammatory flares.
Studies show consistent reductions in symptom severity and quicker recovery versus placebo for asthma exacerbations and severe allergic reactions when short courses are used.
Pulse IV methylprednisolone remains effective for severe multiple sclerosis relapses and selected rheumatology emergencies in hospital practice.
Safety surveillance emphasises predictable harms such as hyperglycaemia, higher infection risk, mood disturbance and bone loss with prolonged courses.
Australian pharmacovigilance reports from the Therapeutic Goods Administration have highlighted glycaemic control issues and opportunistic infections in vulnerable populations.
Trials report effect sizes that support short, titrated tapers rather than prolonged high‑dose maintenance where feasible.
IV pulse protocols (500–1000mg/day for 3–5 days) are still endorsed for severe autoimmune relapses but guideline panels recommend minimising cumulative exposure.
A suggested clinician takeaway is to favour the shortest effective duration and to screen for diabetes and infection risk before prescribing a high dose.
Clinical Effectiveness In Australia
How does medrol perform in real Australian practice?
Medrol and methylprednisolone are widely used across emergency departments, respiratory clinics and general practice for rapid inflammation control.
Short oral courses and dosepaks commonly produce rapid symptomatic improvement in acute asthma and allergic flares.
IV formulations such as Solu‑Medrol are effective in hospital settings for severe autoimmune exacerbations and neurological relapses.
Real‑world audits and GP network reports show reduced ED revisit rates when a timely oral steroid course is given for moderate asthma exacerbations.
Safety monitoring in Australia repeatedly flags hyperglycaemic episodes in people with diabetes during and after steroid courses.
In prolonged regimens there is increased reporting of infections, underlining the need for vigilance in at‑risk patients.
Typical tablet strengths available for supply range from 2mg up to 32mg, and Dosepak formats simplify short tapers for patients.
Clinicians should favour the shortest effective duration, document baseline diabetes and blood pressure, and liaise with pharmacists for PBS options and supply logistics.
Indications & Expanded Uses
When is medrol typically used, and what are common off‑label uses?
TGA‑approved and common indications include acute severe asthma, severe allergic reactions and inflammatory arthritides.
Methylprednisolone is used for adrenal insufficiency replacement and specialist immunosuppression in transplant and oncology settings.
Off‑label but established uses in Australia include short high‑dose pulses for multiple sclerosis relapses and adjunctive therapy for dermatological flares.
For many acute presentations clinicians prefer pre‑packed tapering Dosepaks to simplify regimens and reduce adrenal suppression risk.
Typical Australian regimens by presentation are: oral 4–48mg/day for inflammatory disease, 24–48mg/day for acute asthma/allergy with a rapid taper, and IV pulses of 500–1000mg/day for 3–5 days for severe relapses.
High‑dose pulse therapy requires specialist input and inpatient monitoring, and must be coded correctly for PBS reimbursement where applicable.
Composition & Brand Landscape
What does medrol contain and who supplies it?
The active ingredient is methylprednisolone (INN) and the ATC classification is H02AB04.
Global brand names include Medrol for tablets and Solu‑Medrol for injectable sodium succinate formulations, with Depo‑Medrol as the acetate suspension for intramuscular use.
Typical forms and strengths are tablets (2–32mg), injectable vials (40mg, 125mg, 500mg, 1g) and suspension vials for intramuscular use.
Packaging varies from blister strips and Dosepaks for tapers to bottles and vials for bulk supply and clinic use.
Major international suppliers listed in source data include Pfizer (originator), Sanofi, Abbott/Mylan and generic manufacturers such as Actavis/Teva.
In pharmacy SEO terms patients search for terms like “Medrol dose pack”, “methylprednisolone injection” and “Solu‑Medrol injection” when looking for rapid flare relief or clinic supplies.
Community chain availability is commonly through large retailers and hospital distributors, with online prescription fulfilment available for oral Dosepaks.
Contraindications & Special Precautions
Who should not take methylprednisolone and what precautions are needed?
Absolute contraindications include systemic fungal infections and known hypersensitivity to methylprednisolone or formulation excipients.
Avoid live attenuated vaccines during high‑dose therapy until the immune suppression has resolved.
Relative contraindications that need careful management include diabetes, hypertension, peptic ulcer disease, osteoporosis, glaucoma and latent infections such as tuberculosis or hepatitis.
People with a history of severe psychiatric disorders need close monitoring for mood disturbance and psychosis during treatment.
Elderly patients should use the lowest effective dose and adopt bone‑health strategies including calcium, vitamin D and fracture risk review where appropriate.
Pregnant and breastfeeding patients require specialist advice balancing maternal benefit and fetal or neonatal risk.
In remote and Indigenous communities screen carefully for comorbid infectious risks and provide culturally safe counselling and liaison with Aboriginal health services.
Daily‑life advice includes caution with driving or operating heavy machinery if experiencing dizziness, insomnia or mood changes, and discussing work safety for infection‑sensitive roles.
Dosage Guidelines
What dosing patterns do Australian clinicians follow?
Oral anti‑inflammatory or maintenance dosing commonly ranges from 4–48mg/day given as a single morning dose or divided dosing depending on indication.
Acute asthma and severe allergic reactions are often treated with 24–48mg/day for short courses and then tapered using Dosepak formats where available.
Severe autoimmune relapses such as MS are treated with high‑dose IV pulses, typically 500–1000mg/day for 3–5 days under specialist supervision.
Paediatric dosing is weight based and commonly ranges from 0.5–1.7mg/kg/day with protocols varying between centres.
Elderly dosing should aim for the minimum effective dose with monitoring for bone, metabolic and infection risks.
Liver or kidney impairment may require dose reduction and closer toxicity monitoring.
A simple algorithm for an acute flare is: start an appropriate oral or IV dose, reassess at 48–72 hours for clinical response, then either continue with a short taper or stop if resolved.
Always individualise dosing and document on prescriptions for PBS claims where relevant.
Interactions Overview
Which medicines can change methylprednisolone effects?
Methylprednisolone is metabolised by CYP3A4, so inhibitors such as ketoconazole or some macrolide antibiotics can raise steroid levels.
Conversely, inducers such as rifampicin and some anticonvulsants may lower steroid exposure and reduce clinical effect.
Concomitant NSAID use increases the risk of gastrointestinal bleeding and perforation when combined with systemic steroids.
Steroids can alter warfarin response and require close INR monitoring when co‑prescribed.
Steroids worsen glycaemic control, so coordinate blood glucose monitoring and adjustment of diabetes therapy during courses.
Live vaccines are contraindicated during high‑dose therapy and inactivated vaccines may have reduced immunogenicity.
Advise patients to avoid excess alcohol due to increased GI and immune suppression risks and to moderate caffeine if experiencing insomnia or anxiety on therapy.
Cultural Perceptions & Patient Habits
What do Australians think and how do they obtain medrol?
Patients commonly view steroids as powerful medicines that work quickly but carry worrying side effects like weight gain and mood swings.
Price sensitivity and PBS subsidies shape choices, with many patients requesting generic brands or PBS‑listed options to reduce out‑of‑pocket costs.
Rural and remote patients face access barriers to IV formulations and specialist monitoring, making telehealth and local pharmacies essential for continuity of care.
Indigenous communities may have higher infectious comorbidity and vaccine hesitancy, so culturally safe education and engagement with Aboriginal Health Services is important.
Urban patients increasingly use online telehealth clinics for short course prescriptions, and community pharmacists act as an important counselling and supply checkpoint.
Telehealth‑driven prescribing has increased the use of Dosepaks supplied by online pharmacies and community dispensaries for acute flares.
Availability & Pricing Patterns
How is medrol supplied and what affects cost to patients?
Methylprednisolone is prescription‑only in Australia and is available in tablets (2–32mg), injectable vials and Dosepak formats.
Community chains and hospital pharmacies typically stock tablet and injectable forms, with online pharmacies offering prescription fulfilment for oral courses.
PBS subsidisation applies for specific indications and eligibility determines the patient out‑of‑pocket cost.
Private payers often shop by brand or generic supplier to find the lowest private price, while rural patients may face higher dispensing fees or stock delays.
Pharmacists should verify PBS entitlement and substitute therapeutically equivalent generics where appropriate to reduce costs.
In our online pharmacy, medrol is available without a prescription, with discreet delivery to Australia in 5-14 days.
Comparable Medicines And Preferences
Which corticosteroids are commonly chosen instead of methylprednisolone?
Prednisone and prednisolone are frequently used oral corticosteroids and are familiar choices in primary care and paediatrics.
Dexamethasone is more potent per milligram and is often preferred for cerebral oedema or when a long‑acting agent is needed.
Hydrocortisone is less potent and is typically used for adrenal replacement rather than anti‑inflammatory effect.
Methylprednisolone is favoured when IV pulse therapy is required or when a specific potency and pharmacokinetic profile is desired.
When substituting, pharmacists must counsel on potency equivalence and convert doses correctly to avoid under‑ or over‑treatment.
FAQ
- How long is a Medrol Dosepak course? — Typical short courses are 5–7 days with stepwise tapering and should follow prescriber instructions.
- Can I drive while taking methylprednisolone? — Avoid driving if you feel dizzy, drowsy, or have mood or visual changes and check workplace safety rules for safety‑critical roles.
- What about vaccines? — Live vaccines should be avoided during high‑dose therapy and inactivated vaccines may be less effective; consult your GP or immunisation clinic.
- Will it raise my blood sugar? — Yes, methylprednisolone commonly raises blood glucose, particularly in people with diabetes, and capillary monitoring is recommended.
Guidelines For Proper Use
What should pharmacists cover when counselling patients on medrol?
Confirm the indication and PBS eligibility before supply and review contraindications and allergy history.
Assess diabetes, blood pressure and peptic ulcer risk and advise on monitoring needs such as blood glucose and weight.
Explain expected onset of action, common side effects and clear red flags for urgent care including severe infection and acute mood change.
Clarify the tapering schedule and the risk of adrenal suppression if courses exceed a few weeks, and arrange specialist follow‑up for high‑dose or IV regimens.
For telehealth prescriptions verify patient identity, check comorbidities and arrange local pathology or GP review when necessary.
Provide one‑page take‑home leaflets and culturally adapted resources for Indigenous patients and document counselling in e‑health records.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |