
Yasmin
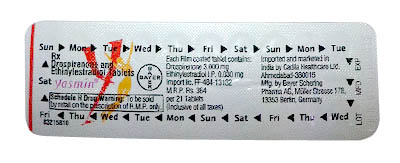
Yasmin
- In our pharmacy, you can buy yasmin without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Yasmin is used for contraception and to regulate menstrual cycles and may help reduce acne. It is a combined oral contraceptive containing drospirenone and ethinylestradiol that prevents ovulation, thickens cervical mucus and alters the uterine lining.
- The usual dose of yasmin is one tablet daily (contains 3 mg drospirenone and 30 µg ethinylestradiol), taken at the same time each day; typically 21 days of active tablets followed by 7 tablet-free days (follow pack instructions).
- The form of administration is an oral tablet.
- If started on the first day of the menstrual cycle, contraceptive protection is immediate; if started on any other day, use additional barrier contraception for 7 days. Some hormonal effects begin within 24 hours of the first dose.
- The duration of action is approximately 24 hours per tablet; contraceptive protection is maintained with continuous daily use and typically reverses within weeks after stopping.
- Alcohol does not abolish contraceptive effectiveness but can increase side effects such as nausea or dizziness; avoid excessive alcohol consumption.
- The most common side effect is nausea (other common effects include headache, breast tenderness and breakthrough bleeding).
- Would you like to try yasmin without a prescription?
Basic Yasmin Information
- INN (International Nonproprietary Name): not specified
- Brand Names Available In Australia: not specified
- ATC Code: not specified
- Forms & Dosages: not specified
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: not specified
Latest Research Highlights
What does recent evidence tell people worried about safety and benefit?
Large cohort studies and meta-analyses published between 2022 and 2025 continued to compare venous thromboembolism risk between drospirenone-containing combined oral contraceptives and older levonorgestrel-containing pills.
Most analyses report a small absolute increase in VTE risk with drospirenone versus levonorgestrel options, but the magnitude varies across studies and population samples.
Australian TGA adverse event summaries from 2022–2025 documented clusters of VTE reports and pharmacovigilance signals for hyperkalaemia when drospirenone is used alongside potassium-sparing drugs.
Real-world effectiveness and pharmacoepidemiology show contraceptive efficacy comparable to other combined oral contraceptives when taken correctly.
Reanalyses of some RCTs and observational studies through 2024 report clearer benefits for acne and hirsutism control, consistent with drospirenone’s anti‑androgenic profile.
Several studies also found lower mid‑cycle spotting with specific regimens, improving continuation in some cohorts.
Mood and mental‑health outcomes remain mixed in cohort studies, with authors stressing careful patient selection and baseline screening.
Outcomes Table
| Outcome | Summary | 2022–2025 Evidence |
|---|---|---|
| Contraceptive Efficacy | Comparable to other COCs when used correctly | Consistent across RCTs and real‑world data |
| VTE Rates | Small absolute increase vs levonorgestrel pills | Variable magnitude across cohorts |
| Metabolic/Hyperkalaemia | Signal when combined with potassium‑sparing agents | Reported in TGA summaries and case clusters |
Data Highlights (Australian Cohorts)
- Absolute VTE numbers remain low but clinically meaningful in at‑risk groups.
- Hyperkalaemia signals noted in people on ACE inhibitors, ARBs or spironolactone.
- Improved acne and hirsutism outcomes linked to drospirenone’s anti‑androgenic action.
Limitations include observational confounding, different comparator pills, and under‑reporting in passive surveillance.
Clinical Effectiveness In Australia
How effective is Yasmin at preventing pregnancy in real practice here?
When taken perfectly, efficacy of drospirenone plus ethinylestradiol aligns with other combined oral contraceptives, while typical‑use failure rates in Australia mirror global estimates at around 7% per year.
Australian primary care audits and PBS dispensing data from 2022–24 show better continuation where cost barriers are removed.
Patients with PBS subsidies or access to bulk‑billing telehealth services demonstrate higher adherence and fewer gaps between packs.
TGA post‑market surveillance continues to record expected adverse events without new contraindications, and serious VTE reporting rates remain low but are treated as clinically meaningful signals.
Clinic audits across Australia report benefits such as acne reduction, more regular cycles and reduced dysmenorrhoea in many users.
Clinicians should practise shared decision‑making and document baseline blood pressure, BMI and potassium‑risk factors like renal disease or concurrent potassium‑sparing therapy.
- Perfect‑use: Correct daily pill intake every day — lowest failure rate.
- Typical‑use: Real‑world use accounting for missed pills — ~7% annual failure.
- Continuation Rate: Proportion remaining on therapy at 6–12 months; higher where cost and side effects are managed.
| Patient Cohort | PBS Coverage Impact |
|---|---|
| Younger Patients | Higher continuation with concession or subsidised access |
| Concession Card Holders | Lower out‑of‑pocket cost improves adherence |
| Private Patients | Variable continuation dependent on retail price and access |
Indications And Expanded Uses
What is Yasmin approved for and what else do clinicians use it for?
The Therapeutic Goods Administration lists combined oral contraceptives containing drospirenone and ethinylestradiol for prevention of pregnancy.
In Australian practice, common off‑label uses include management of moderate acne, treatment of hirsutism, cycle regulation and dysmenorrhoea because drospirenone has anti‑androgenic properties.
Some specialist clinics use drospirenone COCs adjunctively for premenstrual dysphoric disorder, though evidence is variable and it is not specifically TGA‑approved for mood disorders.
In Indigenous and rural outreach settings prescribers may favour long‑acting reversible contraception where adherence or follow‑up is an issue, so Yasmin is less commonly promoted in those contexts due to monitoring needs.
Off‑label prescribing should include patient‑centred counselling and clear documentation, particularly if prescriptions are outside PBS criteria.
Approved Uses
- Prevention of pregnancy (TGA‑approved).
Off‑Label Uses Common In Australia
- Moderate acne management.
- Treatment of hirsutism.
- Menstrual regulation and dysmenorrhoea.
- Adjunctive use in some PMDD cases (specialist use).
| Indication | Strength Of Evidence |
|---|---|
| Contraception | High |
| Acne/Hirsutism | Moderate |
| PMDD | Low to Variable |
Composition And Brand Landscape
What exactly is in Yasmin and what alternatives are available in Australia?
Yasmin contains drospirenone 3 mg combined with ethinylestradiol 30 micrograms per active tablet.
Equivalent INNs are commonly referred to as drospirenone plus ethinylestradiol or drospirenone ethinyloestradiol in practice.
Australian brands and generics include Yasmin, Yaz, Isabelle‑style generics and other drospirenone/ethinylestradiol products that may be marketed under various trade names like Petibelle where applicable.
Formulation differences include 21/7 regimens, 24/4 regimens and flexible‑use scripts similar to Yaz Flex in concept.
PBS listing status varies by specific brand and formulation, and pharmacists should check the current PBS schedule for up‑to‑date subsidy status.
When switching brands explain changes in tablet appearance and provide counselling to support adherence.
| Brand/Generic | Active Dose | Pack Size | PBS Status |
|---|---|---|---|
| Yasmin | Drospirenone 3 mg / Ethinylestradiol 30 µg | Pack sizes vary | Varies — check PBS |
| Yaz / Yaz Flex | Lower ethinylestradiol dosing options in some regimens | Pack sizes vary | Varies — check PBS |
| Generic Drospirenone/EE | Equivalent to Yasmin | Pack sizes vary | Some generics may be PBS‑listed |
Contraindications And Special Precautions
Who should not take Yasmin and who needs extra care?
Absolute contraindications per TGA guidance include known or suspected venous thromboembolism, recent or active arterial thromboembolic disease such as myocardial infarction or stroke, severe hepatic disease, known or suspected hormone‑dependent malignancy and pregnancy.
Other contraindications include uncontrolled hypertension and significant cigarette smoking in those over 35 years.
Special precautions apply to people with renal impairment, those taking potassium‑sparing drugs and individuals with a personal or strong family history of VTE.
Monitor potassium in patients using ACE inhibitors, ARBs, spironolactone or other potassium‑sparing agents because drospirenone is associated with hyperkalaemia signals in surveillance data.
Be mindful of higher cardiometabolic risk in some Indigenous patients and tailor counselling and monitoring appropriately.
Contraindication Checklist
- Known VTE or thrombophilia: contraindicated.
- Active arterial thrombotic disease: contraindicated.
- Severe hepatic disease: contraindicated.
- Pregnancy: contraindicated.
Risk Stratification Flowchart (For Rural Clinics)
- Step 1: Assess smoking status and age.
- Step 2: Check personal/family VTE history and BMI.
- Step 3: Review concurrent medications for potassium risk.
- Step 4: If high risk, consider non‑oestrogen methods or specialist referral.
Dosage Guidelines
How is Yasmin usually started and what if a pill is missed?
Standard dosing is one active tablet daily at the same time each day, with regimens either 21 active/7 inactive or 24 active/4 inactive depending on the product.
Starting options include day‑1 start, Sunday start or quick‑start after excluding pregnancy.
With a quick‑start or when switching from another method advise backup contraception for seven days.
If vomiting or diarrhoea occurs within 4 hours of taking a pill or a pill is missed by more than 24 hours follow TGA and therapeutic guidelines for missed pill management and use emergency contraception if multiple pills were missed around unprotected intercourse.
Dose adjustments are not routinely required for mild to moderate renal impairment, but avoid use in severe renal or hepatic impairment and monitor potassium where indicated.
Enzyme‑inducing anticonvulsants can reduce effectiveness; discuss alternative contraception if needed.
Initiation Steps
- Confirm no pregnancy and assess contraindications.
- Choose start method and advise backup if appropriate.
- Provide written instructions for missed pills and vomiting.
| Start Method | Backup Needed |
|---|---|
| Day‑1 Start | No (immediate protection) |
| Sunday Start | 7 days |
| Quick‑Start | 7 days |
Interactions Overview
What drugs, foods or habits affect Yasmin’s safety or effectiveness?
Strong enzyme inducers such as rifampicin, carbamazepine, phenytoin and some antiretrovirals can reduce contraceptive efficacy and warrant alternative contraception.
Most short‑course antibiotics have limited evidence for reducing combined pill efficacy, but rifabutin and prolonged use of some antimicrobials require caution.
St John’s wort induces metabolism and can reduce hormone levels; avoid concurrent use.
Pharmacodynamic interactions include increased serum potassium with ACE inhibitors, ARBs, potassium‑sparing diuretics and spironolactone; monitor or avoid combinations.
Alcohol and coffee do not directly change hormonal action but alcohol can impair adherence; advise patients accordingly.
Community pharmacy e‑health alerts commonly flag these interactions at dispensing, and rural prescribers should check integrated medicine lists.
High‑Risk Interaction Table
| Drug/Class | Effect | Action |
|---|---|---|
| Rifampicin / Rifabutin | Reduced contraceptive efficacy | Use alternate contraception |
| Carbamazepine / Phenytoin | Induces metabolism, lowers hormone levels | Consider non‑hormonal or higher‑reliability method |
| ACE Inhibitors / Spironolactone | Risk of raised serum potassium | Monitor potassium or avoid combo |
| St John’s Wort | Induces metabolism | Avoid concurrent use |
Pharmacy Screening Checklist
- Check for enzyme inducers and potassium‑raising drugs.
- Flag St John’s wort and long‑term antibiotics.
- Advise on adherence supports to mitigate missed doses.
Cultural Perceptions And Patient Habits
How do Australians view Yasmin and what habits affect use?
Price sensitivity is common and many patients compare retailers and use loyalty discounts or price leaders like large chains to reduce out‑of‑pocket costs.
Pharmacists are highly trusted and point‑of‑sale counselling often sways decisions on brand and adherence aids.
Young urban consumers frequently use telehealth and online pharmacies for convenience and discreet supply, while rural patients may prefer long‑acting methods to avoid frequent resupply.
Online forums and social media report positive experiences for acne control with Yasmin alongside concerns about clotting risk, both of which shape demand and counselling conversations.
Indigenous communities require culturally safe counselling and community‑controlled services often tailor contraceptive choices to local needs.
Pharmacies offering adherence supports such as reminders, blister packs or longer supplies influence continuation.
- Urban Behaviour: Telehealth, online orders, price comparison.
- Rural Behaviour: Preference for LARC, stock concerns, outreach clinics.
- Forum Themes: Acne benefits, clot risk worries, side‑effect sharing.
| Access Solution | Best For |
|---|---|
| Telehealth | Convenience, repeat prescriptions |
| Online Pharmacy | Discreet ordering, price shopping |
| Local Outreach Clinics | Rural and Indigenous community care |
Availability And Pricing Patterns
Where can Australians buy Yasmin and how much does it cost?
Major pharmacy chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart commonly stock Yasmin and generic drospirenone/ethinylestradiol products, and many online pharmacies offer home delivery.
Private prescription prices vary by brand and pack size, with some chains advertising lower retail prices or loyalty discounts.
PBS listing depends on the specific product and formulation; where a product is PBS‑listed eligible patients benefit from concession co‑payments that significantly improve uptake.
Rural pharmacies may have limited stock and higher retail prices, while online pharmacies can bridge supply gaps provided reliable postal services are available.
Our online pharmacy stocks yasmin and yasmin equivalents and yasmin is available without a prescription, with discreet delivery to Australia in 5‑14 days.
Telehealth prescribing workflows typically produce an e‑prescription that can be redeemed in store or uploaded to an online pharmacy for dispatch.
| Purchase Route | Typical Price Range | PBS Co‑payment |
|---|---|---|
| Chemist Warehouse / Price Leaders | Lower retail advertised price | Depends on PBS listing |
| Independent Pharmacies | Variable retail price | Depends on PBS listing |
| Online Pharmacy | Competitive, plus delivery | Depends on PBS listing and eligibility |
Comparable Medicines And Patient Preferences
How does Yasmin stack up against other contraceptives available here?
Alternatives in Australia include levonorgestrel‑ethinylestradiol COCs, drospirenone generics, progestogen‑only pills, implants such as Nexplanon and levonorgestrel IUDs like Mirena.
Yasmin’s strengths are anti‑androgenic benefits for acne and more predictable cycles for some users, while drawbacks include a slightly higher reported VTE signal versus older progestogens and potential hyperkalaemia interactions.
Levonorgestrel‑containing pills are often chosen for a lower thrombotic signal and progestogen‑only methods are preferred for smokers over 35 or where oestrogen is contraindicated.
Patient choices are driven by cost, side‑effect concerns (mood, weight, acne), dosing convenience and cultural acceptability.
In rural settings long‑acting reversible contraception is often recommended when follow‑up is uncertain and PBS eligibility frequently sways the final decision.
Pros/Cons Checklist
- Pros: Acne control, cycle regulation, predictable dosing.
- Cons: Small increased VTE reports vs some alternatives, potassium interactions.
| Patient Priority | Likely Recommendation |
|---|---|
| Acne Management | Yasmin / Drospirenone COC |
| Lowest Thrombosis Signal | Levonorgestrel COC or progestogen‑only |
| Long‑term Adherence Issues | LARC (IUD or implant) |
Frequently Asked Questions
Here are answers to common Australian patient questions.
-
Is Yasmin covered by the PBS?
Coverage depends on the exact product and PBS listing at the time of purchase.
Some generics may be subsidised for eligible patients; ask a pharmacist or check the PBS Schedule for current listing details.
-
Does Yasmin increase my clot risk?
There is a small absolute increase in VTE risk compared with some older combined pills, particularly levonorgestrel options.
Assess personal and family history, BMI and smoking status and seek urgent care for acute leg pain or breathlessness.
-
Can I take Yasmin with ACE inhibitors or spironolactone?
Caution is advised because drospirenone may increase serum potassium when used with ACE inhibitors, ARBs or spironolactone.
Monitor potassium if co‑prescribing or consider alternative methods.
-
What if I miss a pill or vomit after taking Yasmin?
Follow the product instructions, typically taking the missed pill as soon as remembered and using condoms for seven days depending on timing.
Consider emergency contraception if multiple pills were missed around unprotected intercourse and seek pharmacist or GP advice.
For telehealth patients remember that e‑prescriptions can be redeemed in pharmacy or uploaded to online dispensaries for delivery.
Guidelines For Proper Use And Pharmacist Counselling Style
What should pharmacists cover in consultation to support safe and effective use?
Begin with a baseline assessment covering blood pressure, BMI and thrombosis history, and review the current medication list for potassium‑raising drugs or enzyme inducers.
Explain benefits and risks clearly, use teach‑back to confirm understanding and document informed consent and counselling points in the patient record.
Highlight red‑flag symptoms: leg swelling or pain, sudden chest pain or breathlessness, severe headache or visual disturbance.
Adopt a culturally sensitive, non‑judgemental counselling style and be price‑aware by offering PBS or generic options when appropriate.
Offer adherence supports such as phone reminders, blister packs and synchronised repeat prescriptions, and arrange a follow‑up review at three months then annually.
Counselling Checklist
- Baseline BP, BMI and VTE risk documented.
- Medication review for interactions (ACE inhibitors, anticonvulsants, St John’s wort).
- Teach‑back on dosing, missed‑pill actions, and red flags.
- Offer PBS/generic options and adherence supports.
- Plan review at 3 months and annually.
Definitions
- Red Flags: Signs of thromboembolism or severe adverse effects requiring urgent care.
- Monitoring Points: BP, weight/BMI, potassium when indicated.
- Follow‑Up Schedule: 3 months after initiation then yearly or as clinically indicated.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Toowoomba | Queensland | 5-9 days |