
Addyi
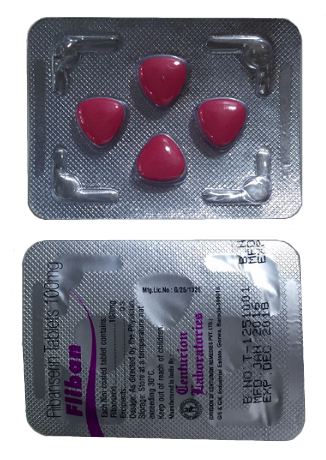
Addyi
- Addyi (flibanserin) is a prescription-only medicine in jurisdictions where it is authorised (notably the US and Canada) and should be dispensed only with a valid prescription; some online sellers or pharmacies may claim to supply it without a prescription or sell unauthorised/counterfeit products—avoid those sources.
- Addyi is used to treat acquired, generalized hypoactive sexual desire disorder (HSDD) in premenopausal women; flibanserin modulates central neurotransmitters (acts as a 5‑HT1A agonist and 5‑HT2A antagonist) to increase dopamine and noradrenaline and reduce serotonin in certain brain pathways.
- The usual dose is 100 mg taken orally once daily at bedtime.
- It is administered as an oral tablet (100 mg tablets, typically supplied in blister packs).
- Effects are not immediate — some people may notice changes after a few weeks, but clinical benefit is usually assessed after about 8 weeks of nightly dosing.
- Addyi requires continuous nightly dosing for maintained effect; pharmacologic activity is sustained with once‑daily dosing (clinical benefits persist while treatment continues) rather than being an acute or on‑demand treatment.
- Do not drink alcohol while taking Addyi — alcohol use with flibanserin significantly increases the risk of severe hypotension and syncope and is contraindicated in the US-labelled guidance.
- The most common side effect is dizziness (other frequent adverse effects include somnolence/sleepiness, nausea, insomnia and dry mouth).
- Would you like to try “addyi” without a prescription?
Basic Addyi Information
- INN (International Nonproprietary Name): Flibanserin.
- Brand Names Available In Australia: not specified.
- ATC Code: G02CX02.
- Forms & Dosages: Tablet, oral; 100 mg strength; Manufacturer: Sprout Pharmaceuticals; Packaging: blister packs (usually 30-tablet supply per carton; marketed in US and Canada).
- Manufacturers In Australia: not specified.
- Registration Status In Australia: not specified.
- OTC / Rx Classification: Prescription only (Rx) in jurisdictions where approved; status in Australia not specified.
Latest Research Highlights (Australian + Global)
Patients ask whether the research shows real benefit for hypoactive sexual desire disorder and what the safety picture looks like.
International randomised controlled trials and safety reviews since approval report modest but statistically significant improvements in sexual desire scores for premenopausal women with acquired, generalized HSDD.
Effect sizes are generally described as small-to-moderate and the clinical meaningfulness of those changes remains debated in the literature.
Australian-specific RCT data are scarce, so local inference depends on international trials plus TGA adverse‑event monitoring where the medicine is marketed.
Key safety signals described consistently from 2015 to 2025 include dizziness, somnolence and hypotension risk when flibanserin is combined with alcohol or moderate/strong CYP3A4 inhibitors.
The regulatory history is relevant: initial FDA rejections in 2010 and 2013 preceded approval in 2015, and ongoing reviews continue to inform labelling and monitoring.
| Outcome | Result (Summary) |
|---|---|
| Mean Change In Desire Scales | Modest improvement vs placebo; statistically significant in pooled RCTs; clinical importance debated. |
| Responder Rates | Higher than placebo in trials, but absolute responder percentages and definitions vary across studies. |
| Common Adverse Events | Dizziness, somnolence, nausea, insomnia, dry mouth—reported consistently. |
| Interaction / Safety Signal | Reported Frequency / Note |
|---|---|
| Alcohol Co‑Administration | Associated with severe hypotension and syncope in case reports and labelling; frequency not specified in supplied material. |
| CYP3A4 Inhibitor Interaction | Increased flibanserin exposure and hypotension risk; avoid moderate/strong inhibitors; exact frequency not specified. |
Top trials of note include pivotal phase III RCTs supporting approval, post‑marketing safety reviews and registry analyses in markets where Addyi is sold.
Clinical Effectiveness In Australia (TGA/PBS Context)
Clinicians want to know how trial evidence applies locally and whether PBS criteria or TGA monitoring change the decision to prescribe.
Because the supplied dossier lists approvals in the US and Canada only, clinical effectiveness in Australia must be inferred from international RCT data.
Local decision‑making should combine the RCT evidence base with real‑time TGA adverse‑event reporting and any PBS funding requirements if the product becomes registered.
| Evidence Source | Summary |
|---|---|
| Randomised Controlled Trials | Modest benefit vs placebo for premenopausal acquired, generalized HSDD; effect sizes small-to-moderate. |
| Real‑World Signals | Adverse events such as dizziness, somnolence and hypotension interactions reported in post-marketing surveillance. |
- Assess outcomes after eight weeks of nightly dosing and stop if no benefit, per product guidance.
- Baseline assessment should include diagnostic confirmation of acquired, generalized HSDD.
- Baseline Assessment Checklist: confirm HSDD diagnostic criteria, screen for depression and suicidality, review current medicines for CYP3A4 inhibitors and CNS depressants, check liver function status.
- Typical Adverse‑Event Rates: dizziness and somnolence are common; exact rates vary by study and are recorded in international trial reports and labelling.
Indications & Expanded Uses (Approved Vs Off‑Label)
Patients commonly ask who is actually eligible for this treatment and whether it can be combined with hormone therapy.
- Approved Indication: acquired, generalized hypoactive sexual desire disorder (HSDD) in premenopausal women.
- Recommended Dose (Per Product Information): 100 mg orally once daily at bedtime.
- Potential Off‑Label Scenarios: investigational use in peri‑ or postmenopausal women or combined use with hormone therapy; evidence for these uses is not established in approval data.
- Medico‑Legal Checklist For Prescribers: confirm lack of TGA approval in Australia before prescribing on an import or unapproved basis; document shared decision‑making; obtain informed consent for off‑label use; review hepatic function and concomitant medicines.
Decision Flow: define acquired vs lifelong HSDD → assess eligibility against contraindications → trial 8 weeks at 100 mg nightly → stop if no measurable benefit.
Composition & Brand Landscape (Packaging, ATC, Suppliers)
People searching for product facts often look for brand names, pack sizes and who supplies the medicine.
Active Substance: flibanserin (INN).
| Form | Strength | Manufacturer | Packaging |
|---|---|---|---|
| Tablet, oral | 100 mg | Sprout Pharmaceuticals | Blister packs (usually 30‑tablet supply per carton; marketed in US and Canada) |
- ATC Classification: G02CX02.
- Primary Supplier: Sprout Pharmaceuticals, Inc. is the sole FDA‑approved supplier as of 2025.
- Patent Notes: patents valid through 9 May 2028 in primary markets; no authorised generics recorded in supplied material.
- SEO Tip For Pharmacies: use both the brand name Addyi and the INN flibanserin in product listings to capture search traffic for female sexual desire medication and HSDD treatment.
Contraindications & Special Precautions (Australian High‑Risk Groups)
Many patients worry about liver problems, alcohol and drug interactions.
| Absolute Contraindications | Notes |
|---|---|
| Severe Hepatic Impairment | Contraindicated due to elevated flibanserin exposure. |
| Concomitant Moderate/Strong CYP3A4 Inhibitors | Avoid co‑administration because of increased hypotension/syncope risk. |
| Known Hypersensitivity | Do not prescribe. |
- Relative Cautions: alcohol use (labelling in some jurisdictions contraindicates alcohol co‑administration), use with CNS depressants, and history of hypotension or syncope.
- Australian High‑Risk Screening Considerations: check pregnancy and breastfeeding status, consider Indigenous health contexts including higher comorbidity and alcohol‑related harms, and assess occupational risks where somnolence/dizziness may be dangerous (driving, operating machinery).
Alcohol Interaction Risk: combination with alcohol has been associated with severe hypotension and is explicitly warned against in supplied labelling information.
Dosage Guidelines (Regimens & Adjustments)
Patients commonly ask how to take the medicine and when to stop.
- Standard Regimen: 100 mg orally once daily at bedtime.
- Assessment Timing: evaluate efficacy after eight weeks and discontinue if no benefit.
- Missed Dose: skip the missed dose and resume the next scheduled dose; do not double up.
| Patient Group | Dose Adjustment |
|---|---|
| Severe Hepatic Impairment | Contraindicated. |
| Paediatric / Children | Not approved; safety/efficacy not established. |
| Elderly | Product is indicated for premenopausal women; elderly not recommended. |
Overdose Management: supportive care and immediate medical attention for severe hypotension, drowsiness or syncope risks.
Interactions Overview (Food, Drink, Medicines; TGA Reports)
One of the first counselling points is what patients must avoid while taking flibanserin.
| Substance | Interaction | Clinical Action |
|---|---|---|
| Alcohol | Increases risk of severe hypotension and syncope. | Advise strict avoidance; contraindicated in some labelling. |
| Moderate/Strong CYP3A4 Inhibitors | Increase flibanserin exposure and adverse events. | Avoid co‑administration; adjust therapy if unavoidable. |
| CNS Depressants / Psychotropics | Potential additive sedation and dizziness. | Review concomitant prescriptions; counsel on sedation risks. |
| Food / Caffeine | No major documented interaction with caffeine in supplied data. | Standard counselling only; emphasise alcohol avoidance. |
- Top Drug Classes To Screen For: CYP3A4 inhibitors (eg, some macrolides, azole antifungals), benzodiazepines and opioids, certain antipsychotics/antidepressants, sedating antihistamines, and any medicines that lower blood pressure.
- TGA Reporting: pharmacists should report suspected adverse reactions to the TGA using official e‑reporting channels.
Cultural Perceptions & Patient Habits (Australia)
Patients often worry about stigma, privacy and whether a pharmacist will understand their needs.
| Area | Urban Pattern | Rural Pattern |
|---|---|---|
| Access To Specialists | Greater access to sexual health clinics and psychosexual therapists. | Limited specialist access; greater reliance on telehealth and pharmacists. |
| Help‑Seeking | Higher help‑seeking and anonymity options through private clinics. | Lower help‑seeking due to stigma and distance; telehealth commonly used. |
- Patient Communication Tips: provide private counselling spaces, normalise the conversation about hypoactive sexual desire disorder, and discuss behavioural and psychosexual therapy options alongside pharmacology.
- Indigenous Considerations: use culturally safe consent processes, prioritise discussions about alcohol use and comorbidities, and involve community health workers where appropriate.
- Telehealth Uptake: telehealth and e‑prescriptions increase reach for rural patients and support follow‑up assessments at 4 and 8 weeks.
Availability & Pricing Patterns (Pharmacies, Telehealth, PBS)
Customers ask whether addyi is stocked here, how much it costs and whether PBS covers it.
Supplied material lists marketing in the United States and Canada only; no Australian brand listing is provided.
Before assuming availability in Australia check TGA registration and PBS status; without PBS listing the medicine would be funded privately and likely costly.
In our online pharmacy, addyi is available without a prescription, with discreet delivery to Australia in 5-14 days.
- Pricing Comparison: PBS listing would reduce out‑of‑pocket costs significantly; private prescription costs are likely to be higher; importing from overseas carries authenticity and legal risks.
- Authenticity Risk: fraudulent generics have appeared online in the past; verify supplier legitimacy and avoid suspicious low‑price imports.
| Supply Route | Likely Process |
|---|---|
| Local Pharmacy Stock (If Registered) | Supplied via wholesalers; likely stocked by major chains if registered. |
| Telehealth / Online Clinics | e‑prescription followed by pharmacy supply; pharmacists must verify legitimacy. |
| Personal Import | Potential legal and authenticity concerns; pharmacist should counsel patients accordingly. |
Comparable Medicines And Preferences (Alternatives In Australia)
Patients and clinicians want to know what else can be offered when oral options are limited.
| Option | Pros | Cons / Evidence Strength |
|---|---|---|
| Addyi (Flibanserin) | Oral dosing; RCT evidence in premenopausal acquired HSDD. | Modest effect size; safety concerns with alcohol and CYP3A4 inhibitors. |
| Vyleesi (Bremelanotide) | Different mechanism; injectable as needed. | Available in some markets; not an oral option; approval status varies by jurisdiction. |
| Testosterone (Off‑Label) | Used in some cases for HSDD; sometimes considered with hormone therapy. | Off‑label for women in many jurisdictions; evidence and safety profile differ; monitor closely. |
| Non‑Drug Options | Psychosexual therapy, couples counselling, CBT approaches; low risk and often first‑line. | Require access to trained therapists; evidence supports use as first‑line or adjunctive therapy. |
- Evidence Strength Notes: Addyi has RCT data for its approved indication; bremelanotide has separate clinical data as an injectable; testosterone therapy for HSDD in women is often off‑label with variable evidence strength.
- Clinical Preference: consider psychosexual therapy before or alongside pharmacologic approaches for holistic care.
FAQ Section (3–4 Common Australian Patient Qs)
- Is Addyi Available In Australia? — The supplied material lists marketing in the US and Canada only; check current TGA registration and PBS status before seeking supply.
- How Soon Will I Notice An Effect? — Clinical guidance recommends assessing effectiveness at eight weeks of nightly dosing and discontinuing if there is no benefit.
- Can I Drink Alcohol While Taking Addyi? — No; alcohol co‑administration increases risk of severe hypotension and is contraindicated in some labelling—advise strict avoidance.
- Who Is An Appropriate Candidate? — Premenopausal women with acquired, generalized HSDD who have completed a holistic assessment and have no contraindications are the target population per approval.
Prescriber Checklist For Follow‑Up: confirm diagnosis, review medications and liver function, arrange 4‑week safety check and 8‑week efficacy review, document shared decision‑making and consent for any off‑label choices.
Guidelines For Proper Use (Pharmacist Counselling & Monitoring)
Pharmacists need a brief script and a monitoring plan to ensure safe supply and follow‑up.
Counselling Script: state the indication (HSDD in premenopausal women), instruct 100 mg nightly at bedtime, explain the 8‑week review, warn against alcohol, and advise on sedation and driving risks.
- Baseline: confirm diagnosis, check liver function and current medicines, screen for depression or suicidal ideation.
- Week 4 Check‑In: review adverse events, confirm alcohol avoidance and adherence, assess sedation and hypotension symptoms.
- Week 8 Efficacy Review: discontinue if no benefit; document outcome and next steps.
- Monitoring Items For The Pharmacy Patient Handout: dosing instructions, missed dose guidance (skip missed dose), storage (store at 20–25°C), what to do for severe dizziness or fainting, and how to report adverse effects to the TGA.
- Reporting: encourage patients to report side effects and remind pharmacists to use TGA e‑reporting for suspected reactions.
Patient Safety Reminder: counsel on avoiding alcohol, checking other medicines for CYP3A4 interactions, and seeking urgent care for syncope or severe hypotension.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–7 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Cairns | Queensland | 5–9 days |