
Eltroxin
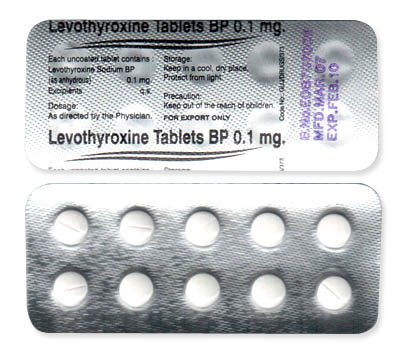
Eltroxin
- Eltroxin (levothyroxine) is normally dispensed from pharmacies with a prescription; it is prescription-only in most countries. Some community pharmacies or online vendors may supply it without a prescription in certain locations, but this is inconsistent, may be unlawful, and is not recommended — always follow local regulations and medical advice.
- Eltroxin is used to treat hypothyroidism and to provide thyroid hormone replacement; it is synthetic thyroxine (T4) which replaces the body’s natural hormone and, in some cases, is used at higher doses to suppress TSH after thyroid cancer.
- Usual adult starting doses for hypothyroidism are 25–50 mcg once daily, titrated every 4–6 weeks; full replacement is typically around 1.6 mcg/kg/day once daily. Specific doses vary for children, the elderly and for thyroid cancer management.
- Administered orally — tablets are the common form (colour‑coded by strength) and an oral liquid is available in some markets; take on an empty stomach 30–60 minutes before breakfast for best absorption.
- Biochemical effects begin within days, with some symptomatic improvement in 1–2 weeks for some patients; changes in TSH and full clinical response are commonly assessed at 4–6 weeks after dose changes.
- Eltroxin has a long duration of action with a plasma half‑life of around 7 days in euthyroid patients, permitting once‑daily dosing; steady state and maximal clinical effect are typically reached over several weeks.
- There is no absolute prohibition on moderate alcohol consumption, but excessive alcohol can worsen health, may affect liver metabolism and thyroid disease control; avoid heavy drinking and discuss alcohol use with your prescriber.
- The most common side effect is headache; other frequent effects reflect over‑replacement (hyperthyroid symptoms) such as nervousness, tremor, palpitations, insomnia and increased appetite.
- Would you like to try eltroxin without a prescription?
Latest Research Highlights
Basic Eltroxin Information
- INN (International Nonproprietary Name): Levothyroxine sodium
- Brand Names Available In Australia: not specified
- ATC Code: H03AA01
- Forms & Dosages: Oral tablets (25, 50, 75, 88, 100, 112, 125, 137, 150, 175, 200, 300 mcg); oral liquid (select markets) 25 mcg/mL, 50 mcg/mL
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription only (Rx)
Patients often ask whether recent studies change how levothyroxine is used.
Recent international meta-analyses and updated endocrine society statements from 2022–2025 consolidate levothyroxine as the standard replacement for primary hypothyroidism while refining target-setting and monitoring strategies.
New guidance emphasises individualised TSH targets and avoiding TSH over-suppression, particularly in older adults and people with cardiac disease.
Australian cohort analyses and TGA-adverse-event reporting from 2022–2024 mirror global safety signals, showing most adverse reports stem from over-replacement rather than intrinsic drug toxicity.
Pregnancy-focused studies in the last three years reaffirm increased levothyroxine requirements during gestation and better obstetric outcomes when TSH is tightly controlled.
Emerging comparative data for tablet versus liquid formulations show improved TSH stability with liquid levothyroxine in absorption-limited patients, such as those with malabsorption or significant gastrointestinal disease.
INN: levothyroxine sodium; ATC: H03AA01; multiple tablet strengths and oral liquid preparations are available in various markets.
- Key Studies (Author / Year, Population, Outcome, Safety):
- International Meta-Analyses (2022–2024): Consolidated TSH-target evidence; emphasised avoiding over-suppression.
- Endocrine Society Statements (2023–2025): Recommended conservative starting doses in older adults and those with cardiac disease.
- Australian Cohort Analyses (2022–2024): Showed long-term safety with adverse events mainly due to over-replacement.
- Pregnancy Studies (2022–2025): Confirmed increased dose requirements and improved obstetric outcomes with tight TSH control.
- Formulation Comparisons (2023–2025): Liquid levothyroxine improved TSH stability in malabsorption cohorts.
Clinical Effectiveness In Australia
People commonly want to know if levothyroxine reliably works in real-life practice.
In Australia, levothyroxine products — including generic formulations and equivalents of overseas brands such as Eltroxin or Euthyrox — are prescription medicines monitored by the TGA and commonly dispensed under the PBS for eligible patients.
When dosed appropriately, levothyroxine reliably normalises TSH and reverses hypothyroid symptoms.
PBS dispensing data show stable long-term use patterns across age groups, reflecting chronic therapy for primary hypothyroidism.
TGA adverse-event surveillance highlights that most reports are due to dosing errors, drug interactions, or switching formulations without retesting TSH.
Real-world PBS practice emphasises continuity of brand or formulation where possible to maintain stable TSH levels after treatment changes.
Data Highlights:
- PBS utilisation: steady long-term dispensing across adult age groups.
- TGA signal themes: over-replacement, interaction-related events, and formulation-switch effects.
Indications And Expanded Uses
Patients often ask what levothyroxine is approved for and when clinicians use it off-label.
TGA-aligned indications centre on replacement therapy for primary and secondary hypothyroidism and suppression therapy in differentiated thyroid cancer where TSH suppression is clinically indicated.
Off-label but clinically common uses include treating subclinical hypothyroidism in symptomatic patients or those planning pregnancy, and carefully titrated suppression therapy in some thyroid malignancy follow-ups.
Levothyroxine is not indicated for weight loss or obesity management.
- TGA-Approved Indications:
- Replacement therapy for primary and secondary hypothyroidism.
- TSH suppression where clinically required in differentiated thyroid cancer (individualised dosing).
- Common Off-Label Practices:
- Treatment of symptomatic subclinical hypothyroidism, especially in pregnancy planning.
- Cautious TSH suppression in selected thyroid cancer follow-up cases.
| Contraindication Type | Details |
|---|---|
| Absolute Contraindications | Untreated thyrotoxicosis; untreated adrenal insufficiency; recent acute myocardial infarction; hypersensitivity to levothyroxine or excipients. |
| Relative Contraindications | Diabetes mellitus, cardiovascular disease, elderly patients, osteoporosis risk, recent major surgery or acute illness — monitor closely. |
Composition And Brand Landscape
Patients ask which ingredient does the active work and what brands are common in Australia.
The active ingredient is levothyroxine sodium (INN), classed under ATC code H03AA01 as synthetic thyroxine (T4).
Globally known brands include Synthroid, Eltroxin, Euthyrox and multiple generics supplied by companies such as AbbVie, Merck KGaA, Mylan, Pfizer and others.
In Australia, levothyroxine generics are widely available on the PBS and dispensed by major chains including Chemist Warehouse, Priceline and TerryWhite Chemmart as well as community pharmacies.
Tablets are sold in multiple microgram strengths and are often colour-coded by dose to reduce dispensing errors.
Liquid levothyroxine is available in selected markets and may be accessed for patients with absorption issues through specialist supply routes or specific Australian suppliers.
| Strength | Formulation | Typical Australian Generic Name |
|---|---|---|
| 25 mcg | Tablet | levothyroxine sodium (generic) |
| 50 mcg | Tablet | levothyroxine sodium (generic) |
| 75–150 mcg | Tablet | levothyroxine sodium (generic) |
| 25–50 mcg/mL | Oral liquid (select markets) | levothyroxine oral solution (select supply) |
Contraindications And Special Precautions
Who needs special care when starting levothyroxine?
Absolute contraindications are untreated thyrotoxicosis, untreated adrenal insufficiency, recent myocardial infarction and hypersensitivity to levothyroxine or excipients.
High-risk groups that need careful titration include the elderly, people with cardiovascular disease, those at risk of osteoporosis and pregnant women who require dose increases.
Indigenous and remote communities may face delayed monitoring and clinics should plan outreach for blood tests and dose reviews.
Workplace and driving precautions are not usually required once euthyroid, but advise caution if symptoms such as palpitations, tremor or dizziness occur.
Monitoring Checklist By Risk Group:
- Elderly: start low (12.5–25 mcg/day); monitor TSH and cardiovascular signs every 4–6 weeks until stable.
- Cardiac Disease: conservative starting dose; liaise with GP/cardiologist; monitor for palpitations, chest pain.
- Osteoporosis Risk: avoid chronic supra-physiological dosing; monitor bone health with appropriate screening.
- Pregnancy: increase dose early and check TSH each trimester.
Dosage Guidelines
How is levothyroxine dosed and adjusted in Australia?
Typical adult replacement starts from 25–50 mcg once daily and is titrated every 4–6 weeks based on TSH.
Full replacement in young healthy adults commonly approximates 1.6 mcg/kg/day taken once daily.
Elderly patients and those with cardiac disease should start at lower doses of 12.5–25 mcg/day and increase slowly.
Pregnant patients usually require an early dose increase and TSH monitoring each trimester.
Children and neonates follow weight-based regimens, with neonates in severe cases needing 10–15 mcg/kg/day.
For patients with malabsorption or on interaction-prone regimens, consider liquid formulations or timing strategies to improve absorption.
Overdose presents with hyperthyroid symptoms such as palpitations and tremor and requires urgent assessment.
- Start low for at-risk patients and increase by small increments every 4–6 weeks guided by TSH.
- Aim for full replacement ~1.6 mcg/kg/day in young healthy adults when indicated.
- Increase dose promptly in early pregnancy and monitor per trimester.
| Patient Group | Typical Starting Dose |
|---|---|
| Young Healthy Adult | Approx. 1.6 mcg/kg/day (often split to equivalent tablet strengths) |
| Elderly / Cardiac Disease | 12.5–25 mcg/day |
| Pregnancy | Increase existing dose early; monitor each trimester |
| Neonate (Severe Hypothyroid) | 10–15 mcg/kg/day |
Interactions Overview
How do food, drink and other medicines affect levothyroxine?
Levothyroxine absorption is sensitive to calcium, iron supplements, aluminium-containing antacids, certain multivitamins, soy, high-fibre meals and coffee when taken together with the tablet.
Agents such as proton pump inhibitors, rifampicin, carbamazepine and some anticonvulsants can increase thyroxine metabolism and lower circulating levels.
Oral oestrogen and pregnancy raise thyroxine-binding globulin and often necessitate higher levothyroxine doses.
TGA and e-health systems flag interaction reports mainly when co-medications are started or when formulations are switched without retesting TSH.
Practical Australian advice is to take levothyroxine on an empty stomach 30–60 minutes before breakfast or at bedtime more than three hours after the last meal, and to separate interacting supplements by several hours.
- Major Interactors: Calcium, iron, antacids with aluminium, multivitamins, soy products, high-fibre meals, coffee.
- Enzyme Inducers: Rifampicin, carbamazepine, phenobarbital and some anticonvulsants.
- Binding Protein Effects: Oral oestrogen, pregnancy.
| Interacting Agent | Practical Timing Advice |
|---|---|
| Calcium/Iron Supplements | Separate by 4 hours where possible |
| Antacids (Aluminium) | Avoid concurrent dosing; take levothyroxine earlier |
| Food/Coffee | Take levothyroxine 30–60 mins before breakfast or at bedtime >3 hours post-meal |
Cultural Perceptions And Patient Habits
What do Australian patients commonly worry about with levothyroxine?
Many Australians see levothyroxine as a lifelong, necessary medicine but express concerns about brand switches, monitoring access and cost.
Patient forums and community feedback show trust in pharmacists for dose counselling and a preference for continuity of the same formulation to avoid TSH fluctuation.
Rural and remote patients report longer gaps between monitoring tests and rely more on telehealth and local pharmacy stock; Indigenous patients may face culturally specific barriers and benefit from tailored outreach and community liaison.
Price-sensitive consumers use the PBS where eligible and compare community and discount chains for non-PBS items.
Counselling that uses plain language, respects local idioms and directs patients to PBS and telehealth options improves adherence and follow-up.
- Patient Concerns: brand switching, testing access, cost.
- Rural vs Urban: longer monitoring intervals and stock variability in remote areas; telehealth reliance.
Availability And Pricing Patterns
Where do people buy levothyroxine and how much does it cost?
Levothyroxine is prescription-only and widely available through community pharmacies and major chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart, as well as accredited online pharmacies accepting e-prescriptions.
The PBS covers eligible patients with concessional pricing, while private prescriptions incur higher out-of-pocket costs.
Price-conscious Australians compare PBS dispensing with private supply and pharmacies commonly substitute generics under the same active ingredient.
Clinicians should note possible minor bioequivalence differences and recheck TSH after any brand switch.
Telehealth clinics facilitate e-prescriptions accepted by most pharmacies, but stock availability in remote areas can vary and may require advance ordering.
In our online pharmacy, eltroxin is available without a prescription, with discreet delivery to Australia in 5-14 days.
| Price Feature | PBS (Eligible Patients) | Private Prescription |
|---|---|---|
| Cost | Concessional pricing under PBS | Higher out-of-pocket cost |
| Substitution | Generic substitution common | Brand might be requested; patient pays difference |
| Access | Widespread via community pharmacies and PBS supply | Online pharmacies with e-prescriptions, varying stock in remote areas |
Comparable Medicines And Preferences
Patients sometimes ask about alternatives to levothyroxine.
Alternatives include liothyronine (T3), combination T4/T3 therapy and desiccated thyroid extracts, though these are less commonly recommended and have mixed evidence for benefit in most patients.
In Australia, levothyroxine in generic formulations remains first-line per TGA guidance and clinical practice.
Pros of levothyroxine include predictable pharmacokinetics, a long half-life and PBS availability.
Cons include absorption variability with certain foods and medicines and concerns when switching brands — which is why consistent supply is preferred.
Liquid formulations or sticking with a consistent generic brand are practical approaches when malabsorption or persistent symptoms occur despite normal TSH.
- When To Consider Alternatives: persistent symptoms despite normal TSH, specialist review, and documented reasons for trialing combination therapy.
- Decision Matrix: try optimisation (timing, interactions, formulation) before switching to less conventional therapies.
FAQ — Common Questions From Australian Patients
Q1: Can I take levothyroxine with breakfast?
A: Best taken 30–60 minutes before breakfast or at bedtime more than three hours after the last meal to maximise absorption.
Q2: Do I have to stay on the same brand?
A: Consistent formulation is preferred; if switched, retest TSH after 6–8 weeks.
Q3: Is levothyroxine on the PBS?
A: Yes — many levothyroxine products are PBS-listed for eligible patients; confirm with your GP or pharmacist.
Q4: What if I miss a dose?
A: Take as soon as remembered unless it is near the next dose; never double up to catch up.
Action List For Missed Dose / Overdose:
- Missed Dose: take promptly unless close to next scheduled dose; do not double the next dose.
- Overdose Signs: chest pain, rapid heartbeat, tremor, confusion — seek urgent medical attention.
Guidelines For Proper Use
What should pharmacists tell patients when dispensing levothyroxine?
Counselling should cover dosing timing (empty stomach 30–60 minutes before food), storage (20–25°C, protect from light and moisture) and the importance of TSH monitoring after starting or changing dose.
Pharmacists in community chains and independents reinforce separating calcium and iron supplements by several hours and advising pregnant patients to notify their prescriber promptly for dose review.
For PBS processing, ensure scripts are handled to maintain continuity and check for generic substitution — advise repeat TSH 6–8 weeks after any brand switch.
In rural settings arrange coordinated lab access and follow-up, and use telehealth where standard sampling is difficult.
Stepwise Counselling Checklist For Pharmacists:
- Confirm prescription and check for interacting medicines.
- Advise timing: 30–60 minutes before breakfast or bedtime >3 hours after eating.
- Explain storage: keep at 20–25°C, protect from light and moisture in original packaging.
- Recommend TSH monitoring 6–8 weeks after dose initiation, adjustment or brand switch.
- Advise pregnant patients to seek prompt review for likely dose increase.
Sample Script For A Pharmacist:
“This is levothyroxine sodium; take one tablet 30–60 minutes before breakfast each morning.
Keep it in the original pack at room temperature, and avoid taking calcium or iron within four hours of this medicine.
Your GP will check TSH in 6–8 weeks after any change.”
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |