
Coreg
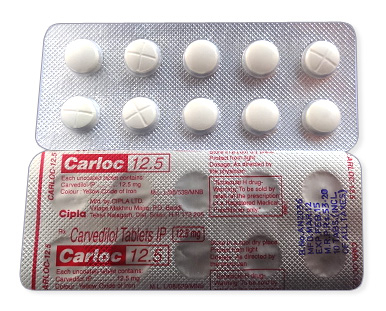
Coreg
- In our pharmacy you can buy coreg without a prescription, with delivery across Australia in 5–14 days and discreet packaging; note carvedilol is prescription-only in most countries but we supply without a receipt.
- Coreg (carvedilol) is used for heart failure, hypertension and left ventricular dysfunction after myocardial infarction; it is an alpha‑ and beta‑adrenergic blocker that reduces heart rate, cardiac workload and peripheral resistance.
- Usual doses: heart failure often starts at 3.125 mg twice daily titrated to 25 mg twice daily (higher doses may be used in larger patients); hypertension/post‑MI commonly start 6.25 mg twice daily titrated to 25 mg twice daily; extended‑release CR formulations are given once daily (equivalent 10–80 mg).
- Oral administration: immediate‑release tablets taken twice daily (with food), or extended‑release capsules once daily (Coreg CR).
- The effect on heart rate and blood pressure begins within about 1–2 hours; symptomatic and mortality benefits in heart failure develop over weeks to months with continued treatment.
- Duration of action: immediate‑release carvedilol typically provides about 12 hours of effect (hence twice‑daily dosing); the CR formulation is designed for once‑daily, roughly 24‑hour coverage.
- Alcohol warning: avoid heavy alcohol use — alcohol can increase dizziness and hypotension when combined with carvedilol; drink only in moderation and take care when standing up.
- The most common side effect is dizziness (also commonly reported are fatigue, diarrhoea, bradycardia and postural hypotension).
- Would you like to try coreg without a prescription?

Basic Coreg Information
- INN (International Nonproprietary Name): Carvedilol
- Brand Names Available In Australia: not specified
- ATC Code: C07AG02 (alpha‑ and beta‑blocking agent)
- Forms & Dosages: Tablets (immediate‑release) 3.125 mg, 6.25 mg, 12.5 mg, 25 mg; Capsules (extended‑release, Coreg CR) 10 mg, 20 mg, 40 mg, 80 mg
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription only (Rx)
Research Findings — Australian And International (2022–2025)
Patients and clinicians ask whether carvedilol still performs as well as other beta‑blockers in modern practice.
Recent literature from 2022–2025 continues to support carvedilol as an effective beta‑blocker with additional alpha‑blocking properties for heart failure with reduced ejection fraction and for hypertension.
Australian registry analyses and international meta‑analyses report sustained reductions in mortality and heart‑failure hospitalisations when carvedilol is added to ACE inhibitor/ARB and diuretic therapy for HFrEF.
Head‑to‑head comparisons suggest similar mortality benefits to bisoprolol and metoprolol, with differences in tolerability profiles between agents.
UK and US cohort data indicate better adherence with once‑daily extended‑release formulations (Coreg CR) in some groups, particularly where dosing simplicity matters.
Safety surveillance from 2022–2025 emphasises common early adverse effects such as dizziness, fatigue, bradycardia and hypotension, and notes rare hepatic reactions reported in pharmacovigilance systems.
| Study / Registry | Mortality | HF Hospitalisations | Adverse‑Event Rates |
|---|---|---|---|
| Major RCTs (pooled) | Reduced (qualitative) | Reduced (qualitative) | Early dizziness/fatigue common; bradycardia/hypotension dose‑related |
| Australian Registry Analyses | Reduced (consistent with RCT data) | Reduced | Tolerability similar to other beta‑blockers; hepatic events rare |
| UK/US Cohort Studies (real world) | Similar to selective beta‑blockers | Similar | Improved adherence with Coreg CR in some cohorts |
Data Highlight — TGA And Pharmacovigilance (2022–2025)
Common early adverse events reported: dizziness, fatigue, bradycardia and hypotension.
Rarely reported: hepatic reactions and severe symptomatic bradycardia requiring dose change or discontinuation.
Interpretation: observe closely during initiation and up‑titration and advise patients about orthostatic symptoms.
Clinical Effectiveness In Australia — TGA & PBS Context
Clinicians want to know how carvedilol fits into Australian practice and the TGA/PBS frameworks.
Australian practice mirrors international guidance, using carvedilol for HFrEF, hypertension and left ventricular dysfunction post‑MI under approved indications.
TGA adverse‑event reporting reinforces the real‑world profile seen elsewhere: postural hypotension and bradycardia are most frequent during initiation and titration.
Severe hepatic impairment is a recognised contraindication in product information and TGA guidance.
| Type Of Adverse Event | Common / Reported |
|---|---|
| Postural hypotension | Common during initiation |
| Bradycardia | Common, dose‑related |
| Hepatic reactions | Rare, serious |
PBS context: availability and subsidy can vary by presentation and listing.
When cost is a concern, prescribers often select generics and pharmacists are pivotal in switching to therapeutically equivalent brands while ensuring formulation equivalence.
Australian observational clinic series report symptomatic improvement and left ventricular ejection fraction gains consistent with global RCTs when standard titration protocols are followed.
- Clinician Checklist:
- Monitor blood pressure and pulse during initiation and up‑titration.
- Check liver function when clinically indicated or if symptoms suggest hepatic injury.
- Follow a staged titration schedule, increasing dose at intervals of at least two weeks as tolerated.
Available formulations to guide local prescribing include immediate‑release tablets 3.125–25 mg and Coreg CR capsules 10–80 mg.
Indications And Expanded Uses — TGA Approvals And Off‑Label Considerations
Patients ask, “What is carvedilol approved for, and what else might specialists use it for?”
TGA‑aligned indications include chronic heart failure (mild to severe), hypertension and left ventricular dysfunction after myocardial infarction.
Standard initiation for heart failure typically starts very low, for example 3.125 mg twice daily, with uptitration to maintenance doses up to 25 mg twice daily for many patients.
Specialist off‑label uses seen in practice include portal hypertension or variceal prevention and symptomatic management of certain arrhythmias, but evidence is limited and these uses are specialist‑led.
| Indication | Typical Starting Dose | Monitoring Priorities |
|---|---|---|
| Heart Failure (HFrEF) | 3.125 mg twice daily | BP, pulse, signs of fluid overload, LFTs if indicated |
| Hypertension | 6.25 mg twice daily | BP, pulse |
| Post‑MI LV Dysfunction | 6.25 mg twice daily | BP, pulse, clinical status |
Remember Coreg CR capsules are available in 10–80 mg strengths and may be chosen when once‑daily dosing is preferred to aid adherence.
Composition And Brand Landscape — Active Ingredient, Brands, Manufacturers
People often ask which brands contain carvedilol and whether they differ.
The active ingredient is carvedilol (INN), classified under ATC code C07AG02 as an alpha‑ and beta‑blocking agent.
Original brand products include Coreg and Coreg CR, with generics marketed under carvedilol or country‑specific names.
| Brand | Manufacturer | Formulations / Strengths |
|---|---|---|
| Coreg / Coreg CR | GlaxoSmithKline (originator) | Tablets 3.125–25 mg; CR capsules 10–80 mg |
| Carvedilol (generics) | Mylan / Teva / Accord / Zentiva (various) | Tablets 3.125–25 mg (typical) |
| Other International Brands | Dilatrend, Carvipress, Carloc, Kredex (regional) | Tablets in similar dose ranges |
ATC: C07AG02.
Carvedilol is prescription only in major territories.
Note for pharmacists: generics are commonly used to reduce cost for PBS‑sensitive patients, but confirm formulation equivalence (immediate‑release versus CR) before switching.
Contraindications And Special Precautions — High‑Risk Australian Groups
Patients ask, “Who must not take carvedilol?”
Absolute contraindications include bronchial asthma and other bronchospastic conditions, severe hepatic impairment, severe bradycardia (<50 bpm), second‑ or third‑degree AV block (unless a pacemaker is present), cardiogenic shock and known hypersensitivity to carvedilol or excipients.
Use with caution in stable COPD, peripheral vascular disease, diabetes (because carvedilol can mask hypoglycaemia symptoms), thyrotoxicosis and psoriasis.
- Elderly: start lower and titrate slowly due to increased sensitivity.
- Pregnancy/Breastfeeding: use only if benefits outweigh risks; seek specialist advice.
- Aboriginal and Torres Strait Islander Patients: account for higher comorbidity burden and access needs; provide culturally safe counselling and outreach.
| Risk Group | Clinical Action |
|---|---|
| Bronchospasm/Asthma | Contraindicated |
| Severe Hepatic Impairment | Contraindicated |
| Bradycardia / AV Block | Contraindicated unless pacemaker present |
| Diabetes | Educate on masked hypoglycaemia; monitor glucose closely |
Daily‑life precautions include warning patients about dizziness and advising not to drive or operate machinery until tolerance is established.
Dosage Guidelines — Initiation, Titration And Special Adjustments
One common patient worry is dose and how quickly it changes symptoms like dizziness.
Standard heart‑failure initiation is 3.125 mg twice daily, titrating at intervals of at least two weeks to a typical maintenance of 25 mg twice daily for many patients.
Patients over 85 kg may require higher doses, up to 50 mg twice daily in heart failure settings as tolerated and indicated.
Hypertension and post‑MI regimens often start at 6.25 mg twice daily with staged titration to similar maintenance doses.
Coreg CR capsules (10–80 mg) allow once‑daily dosing when clinically appropriate and may improve adherence.
| Indication | Start | Typical Target |
|---|---|---|
| HFrEF | 3.125 mg twice daily | Up to 25 mg twice daily (higher if >85 kg) |
| Hypertension | 6.25 mg twice daily | Up to 25 mg twice daily |
| Post‑MI LV Dysfunction | 6.25 mg twice daily | Up to 25 mg twice daily |
Dose adjustments: contraindicated in significant hepatic impairment and require cautious dosing in the elderly.
No routine renal adjustment is specified, but monitor hypotension and volume status in chronic kidney disease.
- Clinician Checklist Before Starting:
- Baseline blood pressure and pulse.
- ECG if conduction disease suspected.
- Liver function tests if risk factors for hepatic disease exist.
- Educate patient about missed doses (take when remembered; do not double up) and avoid abrupt cessation.
Interactions Overview — Drugs, Food And Lifestyle Factors
People often worry about what carvedilol does with other medicines or alcohol.
Major interactions include additive bradycardia or conduction slowing with other negative chronotropes such as digoxin, verapamil and diltiazem and some antiarrhythmics.
There is enhanced risk of hypotension when combined with other antihypertensives and nitrates.
Carvedilol may mask hypoglycaemia symptoms, so combine cautiously with insulin or sulfonylureas and advise closer glucose monitoring.
CYP interactions: inhibitors or inducers of CYP2D6 and CYP2C9 can alter carvedilol metabolism and clinical effect; adjust and monitor accordingly.
Alcohol can worsen hypotension and dizziness; counsel patients to avoid excessive alcohol while initiating therapy.
| Interaction | Severity |
|---|---|
| Digoxin, Verapamil, Diltiazem | Major — additive bradycardia/heart block risk |
| Other Antihypertensives, Nitrates | Moderate — increased hypotension risk |
| Insulin, Sulfonylureas | Moderate — may mask hypoglycaemia symptoms |
| CYP2D6 / CYP2C9 Modulators | Moderate — monitor for altered carvedilol levels |
Polypharmacy in older Australians is a common contributor to adverse events; perform a medicines review at initiation.
Cultural Perceptions And Patient Habits In Australia — Trust, Cost And Access
Patients often ask peers online whether carvedilol will leave them tired or affect sex drive.
Common patient concerns in Australia include fatigue, sexual dysfunction and dizziness, which can reduce adherence.
Price sensitivity pushes many to request generics or PBS options, and community pharmacists are a frequent first contact for advice and cheaper supply.
Rural and remote communities face access barriers such as stock shortages, longer waits and limited specialist care, increasing reliance on telehealth and e‑prescriptions.
Aboriginal and Torres Strait Islander communities highlight the importance of culturally safe communication and outreach when counselling about carvedilol.
Online forums commonly discuss switching between immediate‑release and CR formulations and ways to manage side effects in everyday life.
Telehealth / Remote Access Tips For Clinicians:
- Use e‑prescriptions for continuity of supply.
- Provide clear written instructions and culturally appropriate materials.
- Consider once‑daily Coreg CR for patients with adherence challenges where appropriate.
Availability And Pricing Patterns — Pharmacies, Online, PBS Vs Private
Where can patients buy carvedilol in Australia and how much will it cost?
Carvedilol is prescription only in major territories and available as immediate‑release tablets and Coreg CR capsules in the strengths given earlier.
Major pharmacy chains and accredited online pharmacies routinely stock generics and branded Coreg where permitted.
Private prices vary widely; generics generally reduce cost and may be listed on the PBS depending on current listings and concessions.
In our online pharmacy, coreg is available without a prescription, with discreet delivery to Australia in 5‑14 days.
| Purchase Route | Pros | Cons |
|---|---|---|
| Community Pharmacy (Chain) | Immediate pickup, pharmacist counselling | Price varies; may need script |
| Online Accredited Pharmacy | Convenience, home delivery, telehealth support | Delivery time varies; ensure accreditation |
| PBS‑Subsidised Supply | Lower cost for eligible patients | Dependent on PBS listings and patient concession status |
Rural supplies may require ordering and take longer; community pharmacists often manage substitution and continuity of supply.
Clinicians and pharmacists should confirm current PBS listings and advise eligible patients about concessions.
Comparable Medicines And Patient Preferences — Alternatives And Trade‑Offs
Patients ask which beta‑blocker is best for them.
Alternatives available in Australia include cardioselective beta‑blockers such as bisoprolol and metoprolol, and nebivolol which has a vasodilatory profile.
Other antihypertensive classes — ACE inhibitors, ARBs and calcium channel blockers — are options depending on comorbidities.
Trade‑offs: carvedilol’s combined alpha/beta action can be advantageous for blood pressure control and heart‑failure mortality reduction, but it may cause more hypotension or dizziness than selective agents in some patients.
Bisoprolol is sometimes preferred for tolerability in HFrEF patients who cannot tolerate carvedilol.
| Comparator | Pros | Cons |
|---|---|---|
| Bisoprolol | Cardioselective, often better tolerated | Less alpha blockade; different blood pressure effects |
| Metoprolol | Familiar, widely used | Lacks alpha blockade; differing side‑effect profile |
| Nebivolol | Vasodilatory effects, well tolerated in some | Availability and PBS status vary |
Choice should be individualised by comorbidities such as asthma, diabetes, and by drug interactions, cost and PBS availability.
FAQ
Q: Will carvedilol make me tired?
A: Fatigue and dizziness are common when starting carvedilol.
A: Counselling points: take with food, start low and titrate slowly, consider timing doses to match daily routine and review dose if symptoms persist.
Q: Can I stop carvedilol if I feel better?
A: No—do not stop abruptly because rebound hypertension or arrhythmia can occur.
A: Taper under clinician supervision according to clinical need.
Q: Is carvedilol safe with diabetes?
A: Carvedilol can mask symptoms of hypoglycaemia such as palpitations.
A: Advise patients to monitor glucose closely and review glucose‑lowering therapy if needed.
Q: Which is better, Coreg or generic carvedilol?
A: Therapeutic effect is the active carvedilol molecule; choose based on cost, supply and whether immediate‑release or CR is needed for adherence.
Pharmacist Counselling Prompts: confirm indication, review current medicines for interactions, discuss side‑effect expectations and arrange follow‑up BP/pulse checks.
Guidelines For Proper Use — Pharmacy Counselling & PBS/National Advice
Patients expect clear, practical advice at dispensing.
Counselling priorities: confirm indication and baseline vitals, review comorbidities and concurrent medications, explain starting‑low and slow‑uptitration and warn about dizziness and driving until tolerance is established.
Missed‑dose rule: take as soon as remembered unless near the next dose; do not double up.
Monitoring plan: schedule follow‑up blood pressure and pulse checks during titration.
Consider baseline LFTs if liver disease risk factors are present and an ECG if conduction disease is suspected.
- Pharmacy Counselling Checklist:
- Confirm why carvedilol was prescribed and expected benefits.
- Review other medicines that may interact (digoxin, verapamil, insulin, etc.).
- Provide written dosing schedule and advise on missed doses.
- Discuss side effects and when to seek urgent care (severe dizziness, syncope, severe bradycardia).
Pharmacy Practice Pointers:
Use PBS concessions where eligible and document any generic substitution.
Collaborate with GPs and specialists using e‑prescriptions or telehealth for patients in rural areas.
Provide culturally appropriate written advice for Aboriginal and Torres Strait Islander patients and offer follow‑up support.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–7 days |
| Newcastle | New South Wales | 5–9 days |
| Gold Coast | Queensland | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Ballarat | Victoria | 5–9 days |